What the brainstem actually is, beyond the textbook diagram
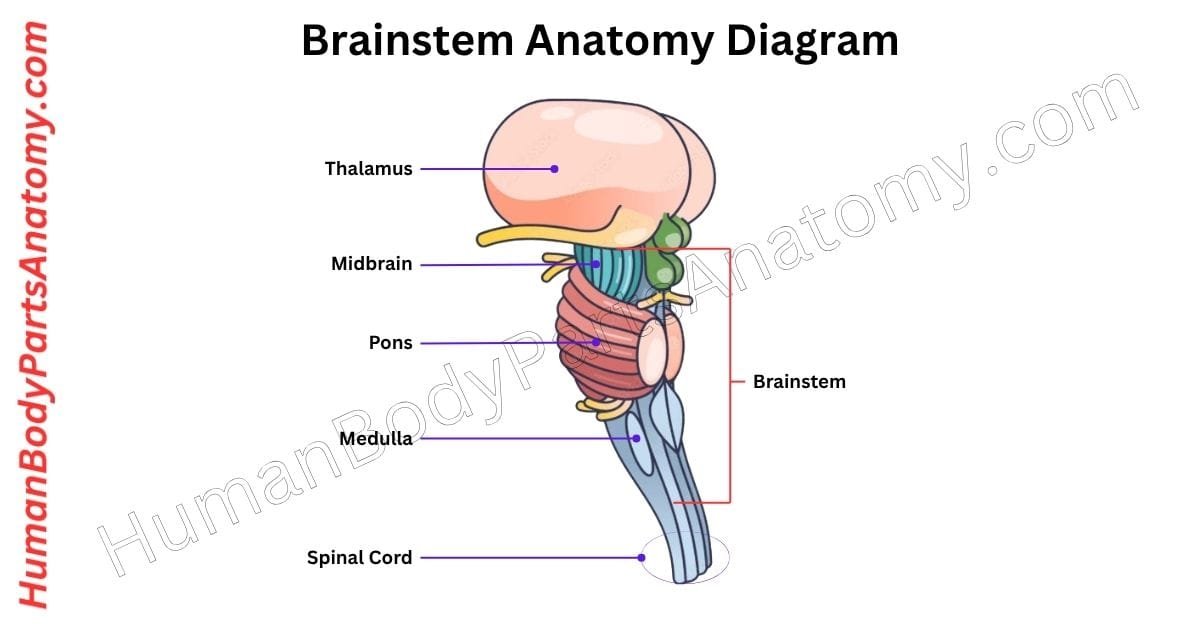
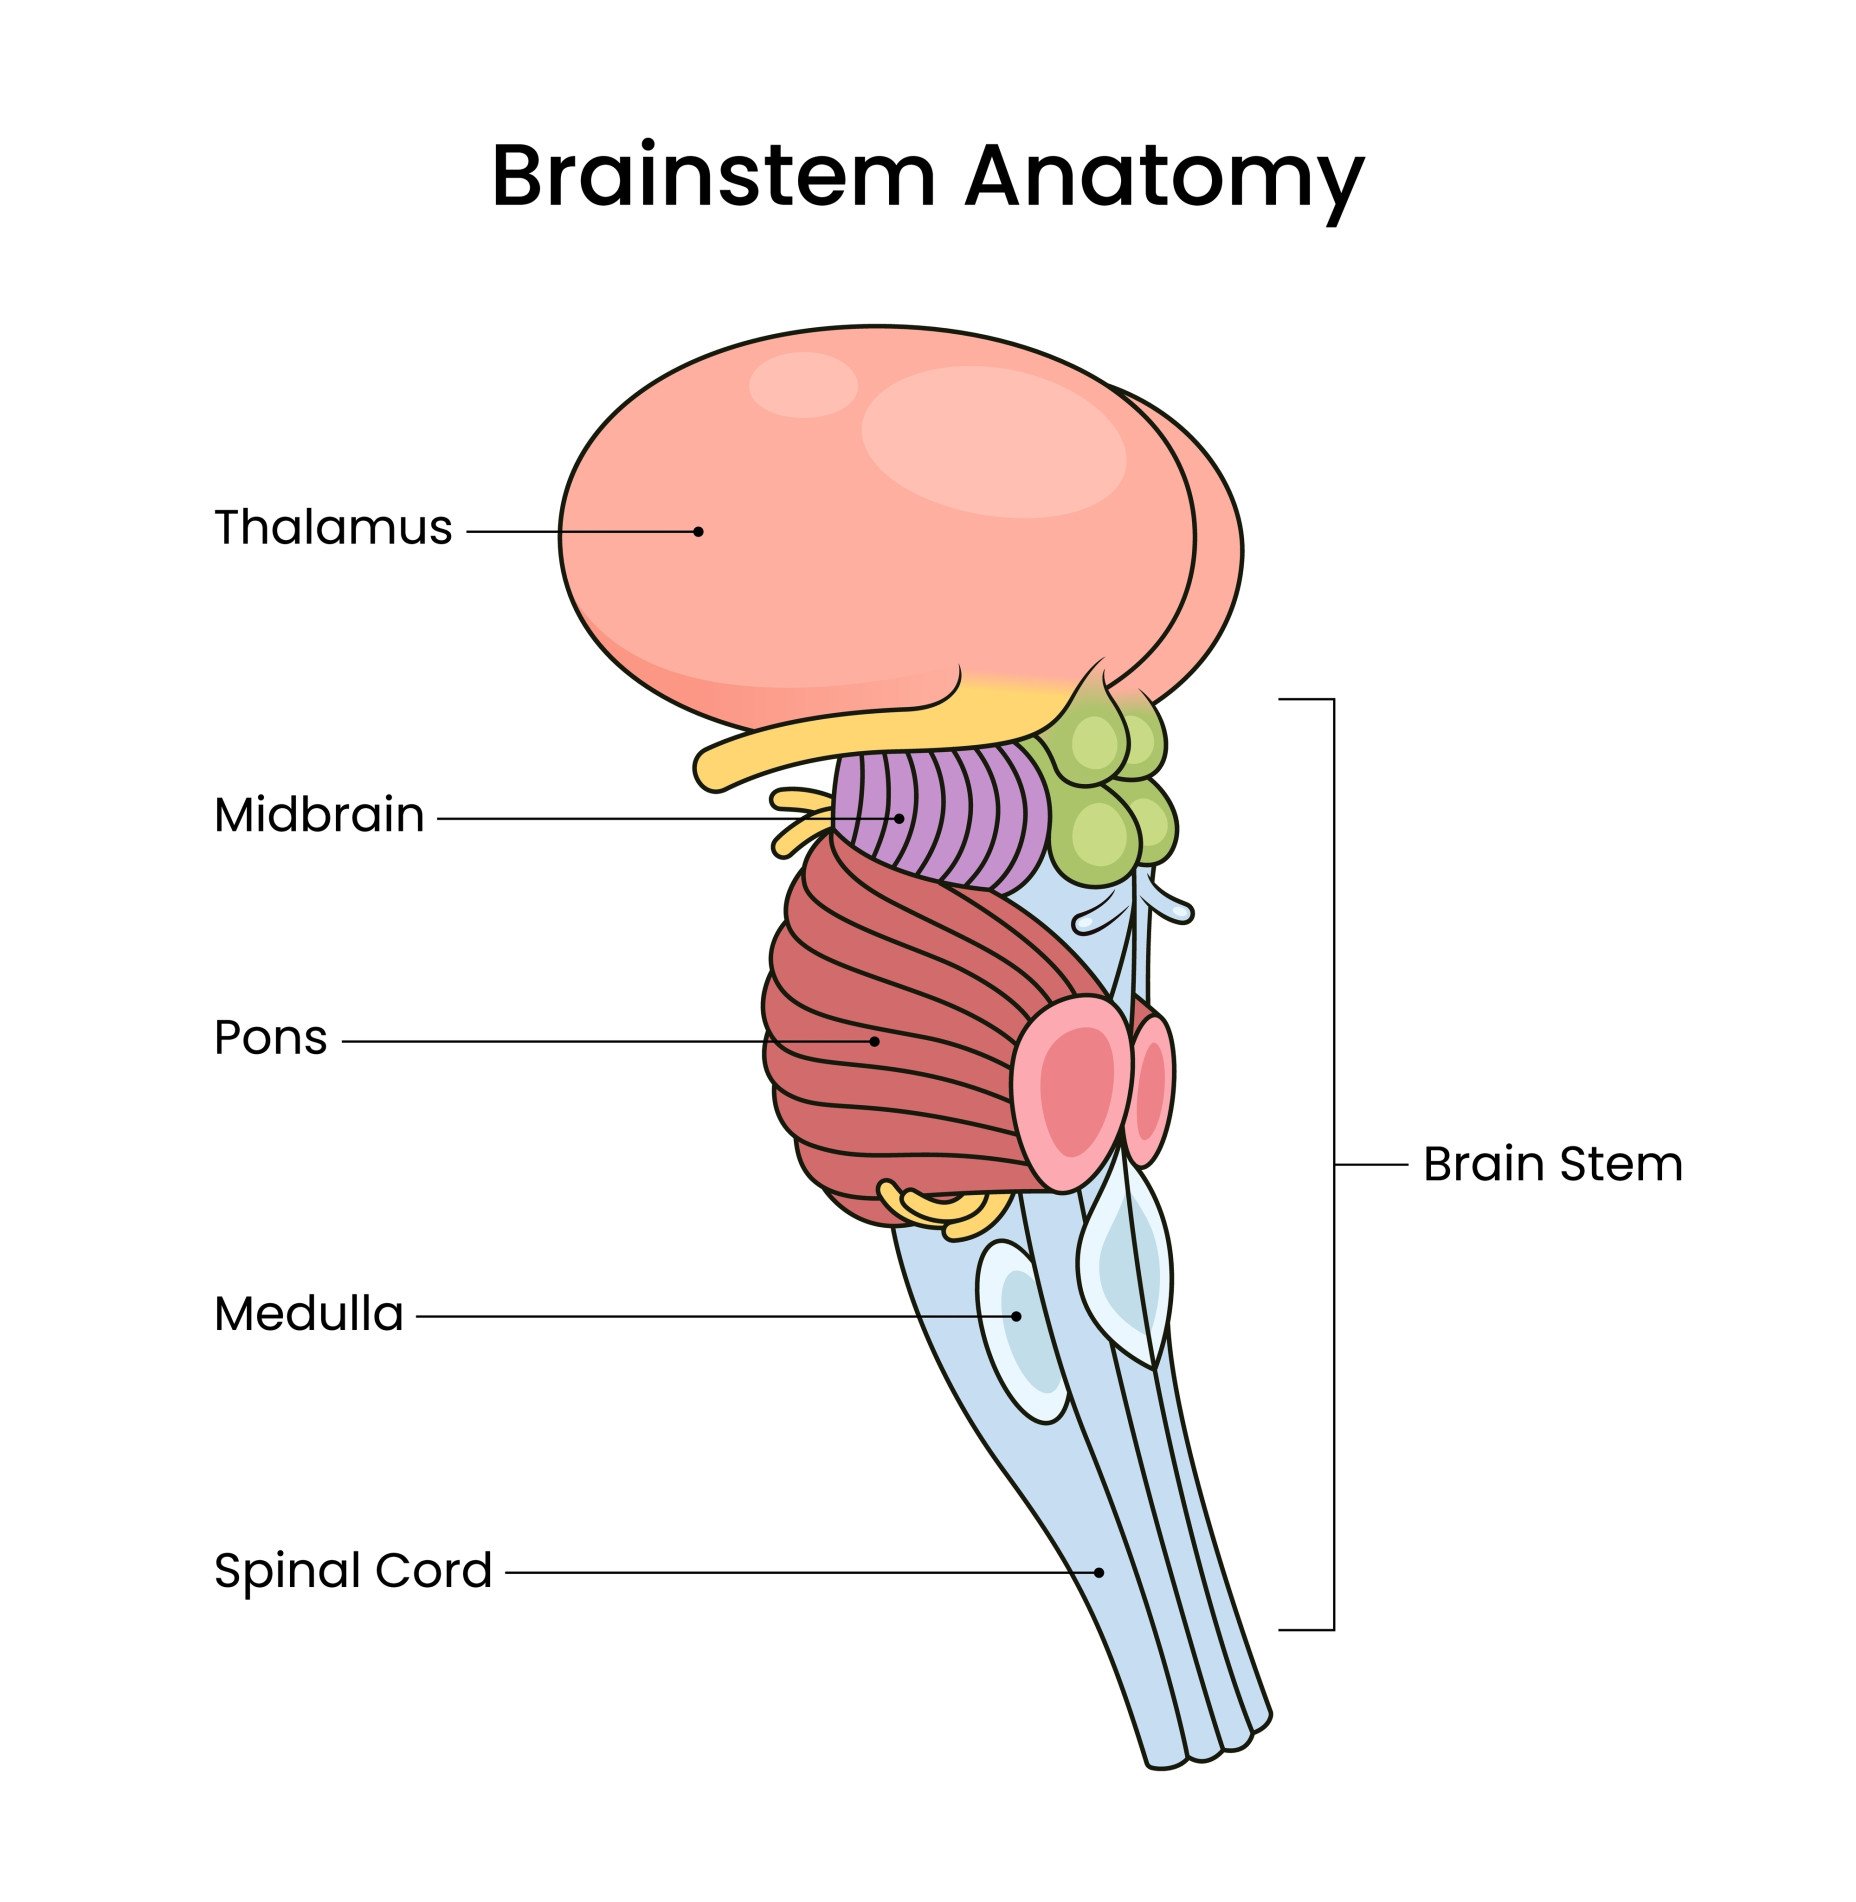
The brainstem is the bundle of nerves and tissue connecting the cerebrum to the spinal cord. It runs from the base of the brain down through the foramen magnum. Most people stop at three names — midbrain, pons, medulla — and move on. That covers the basic anatomy but misses why it matters when you are actually dealing with a patient or a scan. I spent years reading brain MRIs and watching residents miss subtle lesions because they treated the brainstem as a single functional unit. It is not. Each segment does something different, and damage in one area produces a very specific set of signs that can localize a problem fast if you know where to look.
Breaking Down the Parts Of The Brainstem
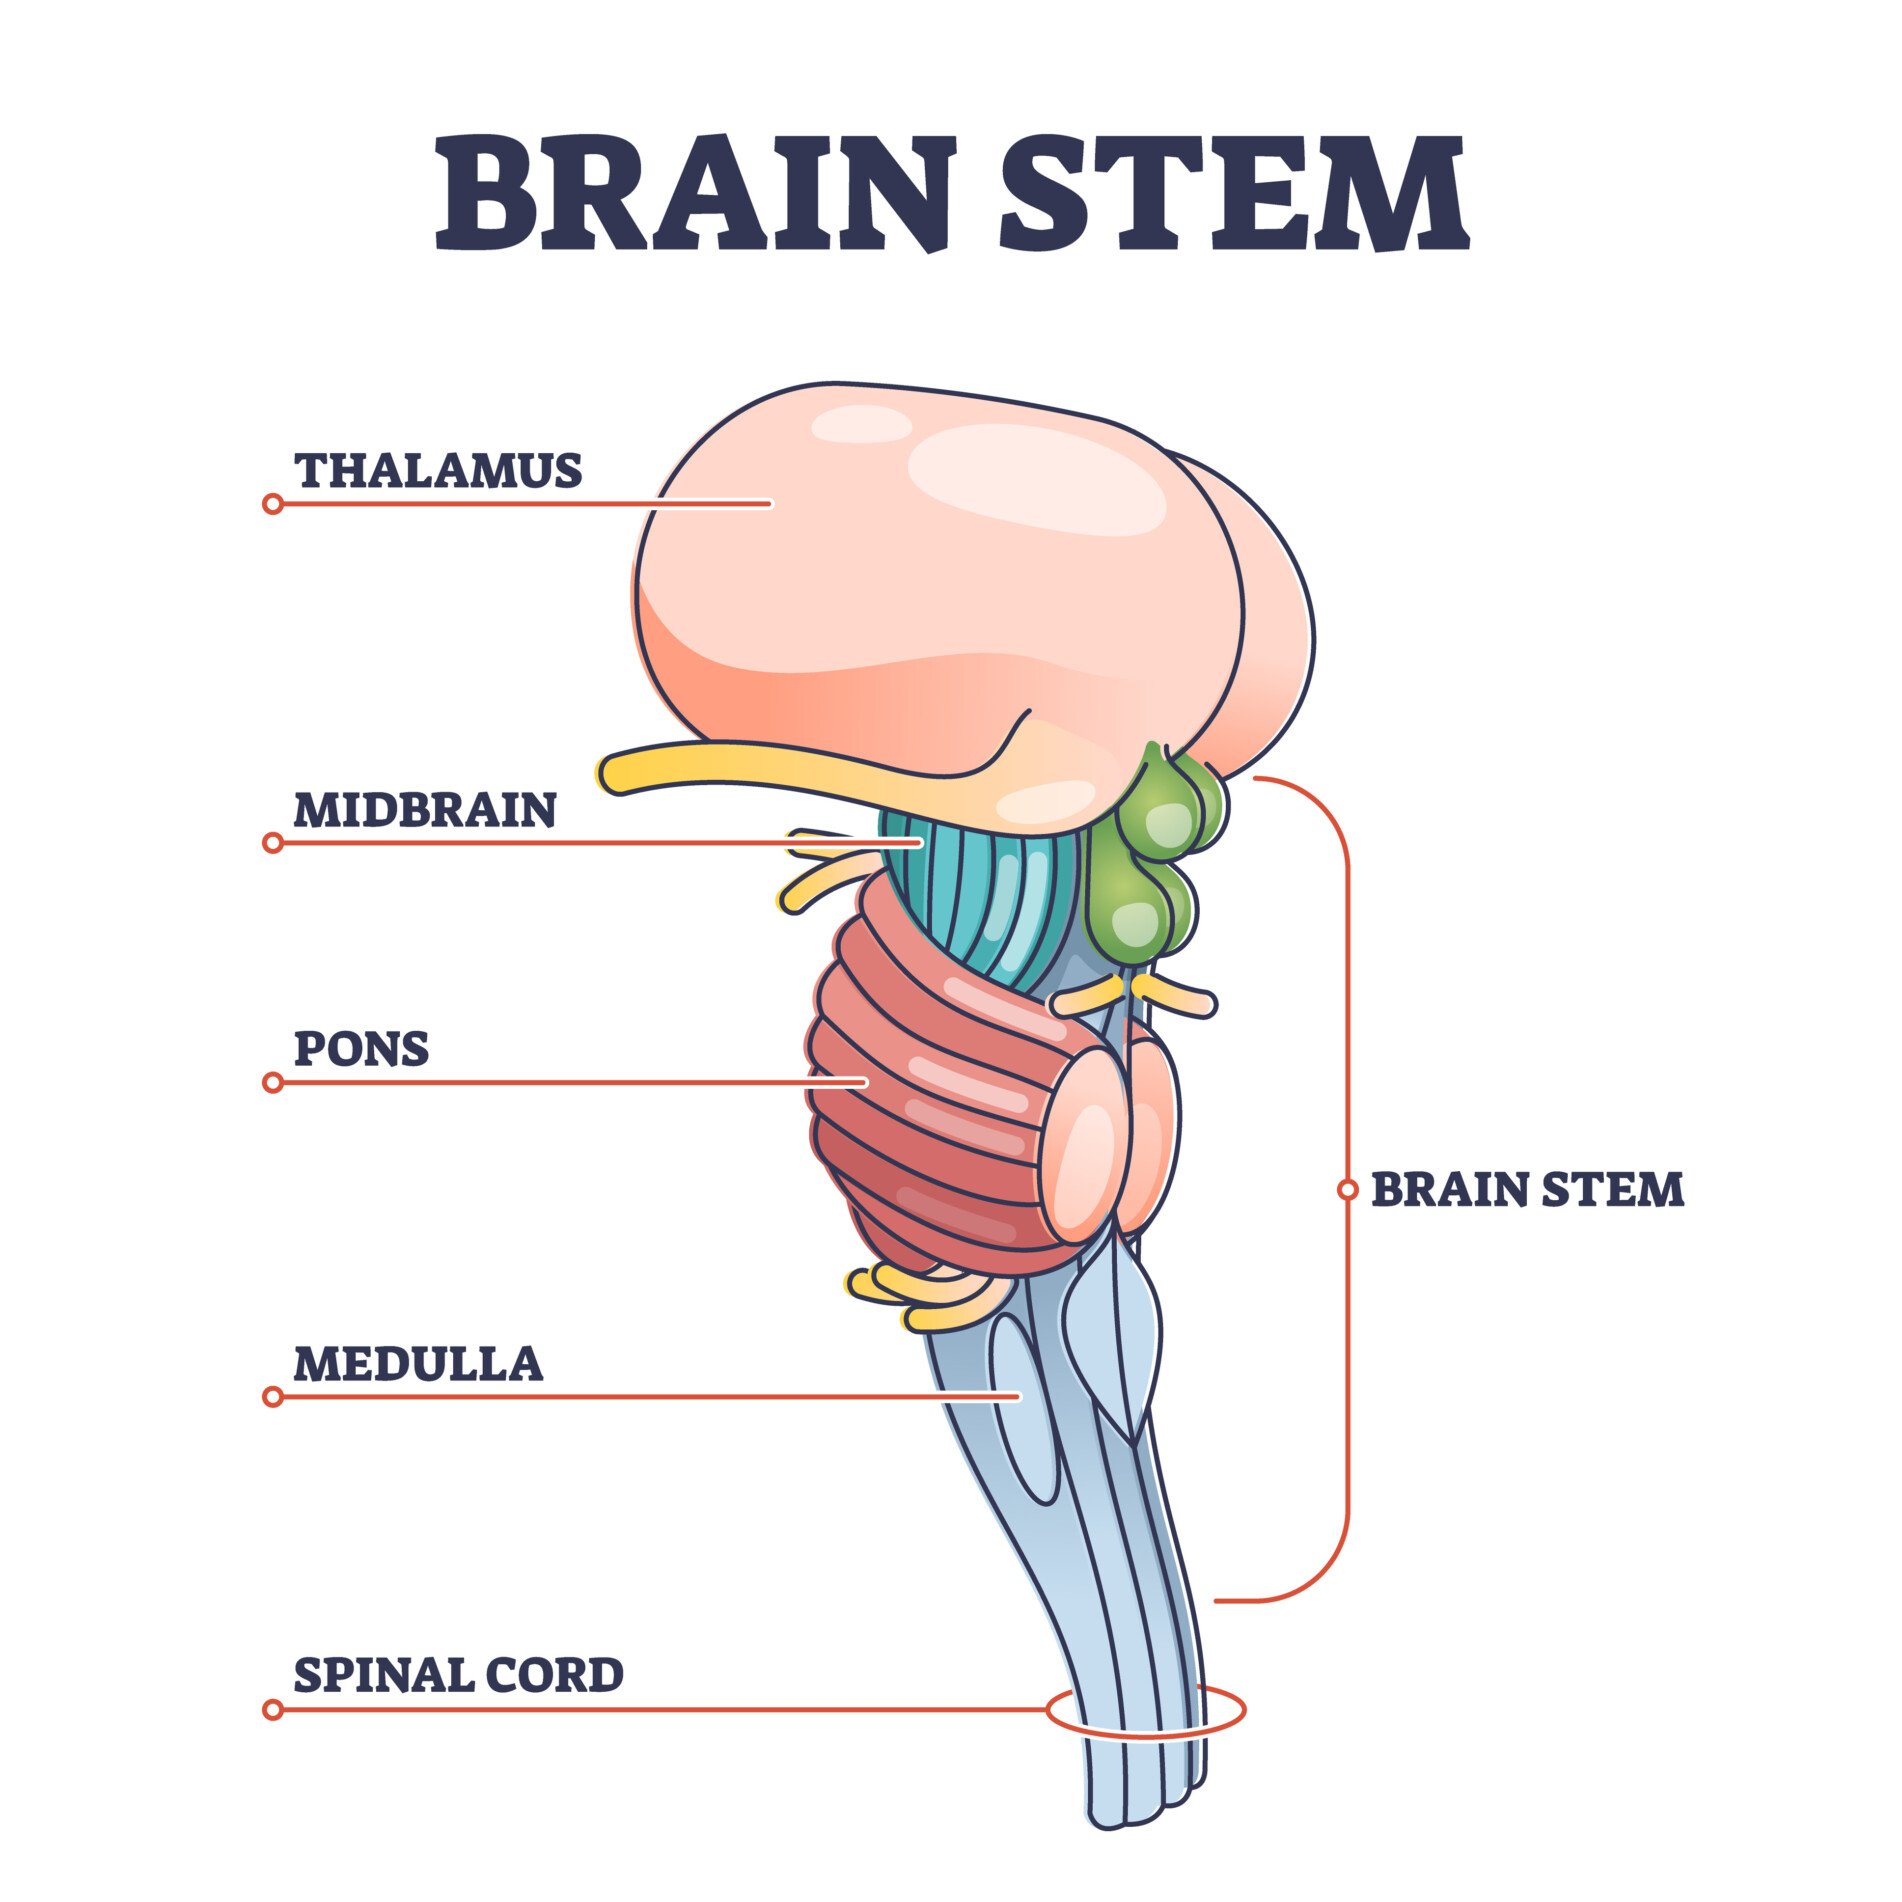
The midbrain sits at the top. It contains the cerebral peduncles, the substantia nigra, the red nucleus, and the tectum with the superior and inferior colliculi. This is where the oculomotor (CN III) and trochlear (CN IV) nuclei live. If someone comes in with a "down and out" pupil-dilated eye, you are looking at a midbrain or CN III issue, not a peripheral nerve problem. The pons is the middle section. It is visibly bulged because of the massive transverse pontine fibers connecting the cerebral hemispheres to the cerebellum. The abducens (CN VI), facial (CN VII), and vestibulocochlear (CN VIII) nuclei are here. A lateral pontine lesion can knock out facial sensation, hearing, balance, and eye abduction all at once. That pattern tells you exactly where the damage is without needing a long workup. The medulla oblongata is the lowest part. It transitions directly into the spinal cord. The hypoglossal (CN XII), vagus (CN X), glossopharyngeal (CN IX), and accessory (CN XI) nuclei sit in or near it. The medial lemniscus, spinothalamic tracts, and corticospinal tracts all pass through here. A medullary stroke can cause contralateral loss of body sensation with ipsilateral face numbness — that is the classic crossed finding that separates brainstem lesions from everything else.
Beneath all three lies the reticular formation, a diffuse network running the entire length. It controls arousal, breathing rhythm, and cardiovascular tone. This is the part that keeps you alive when nothing else is working. There is also the fourth ventricle sitting dorsal to the pons and upper medulla. Blood flows through it, cerebrospinal fluid circulates through it, and tumors like ependymomas like to grow right up against its floor. If you are interpreting an MRI and see a mass obliterating the fourth ventricle, the differential gets narrow fast.
Get the Full Details
How to actually use this knowledge in practice
When I was still in fellowship, I had a patient who presented with isolated vertical gaze palsy. No weakness, no sensory changes, just could not look up or down. Everyone on the team was throwing differential diagnoses at the wall. The lesion was tiny — about 4 millimeters — in the dorsal midbrain at the level of the superior colliculus. It was compressing the vertical gaze center. A CT missed it entirely. The MRI picked it up within ten minutes of knowing exactly where to look. The lesson is simple but easy to forget: the brainstem is small. Lesions are small. Clinical correlations are precise. If you do not know which structure does what, you are just guessing at a black dot on a scan. Here is a practical framework I use now. When I see a brainstem abnormality, I go through it in order. Midbrain first — check the colliculi, the cerebral peduncles, the periaqueductal gray. Pons second — check the corticospinal tracts, the pontine nuclei, the facial nerve pathway. Medulla third — check the pyramids, the olives, the vestibular nuclei. This takes about thirty seconds on a good scan and saves about twenty minutes of back-and-forth with radiology when you can tell them exactly what you are concerned about.
Common mistakes people make
The biggest one is assuming that bilateral brainstem symptoms mean bilateral disease. They do not. The brainstem is tightly packed. A single lesion on one side can hit multiple structures that serve opposite sides of the body. That crossed deficit pattern — face on one side, body on the other — is the hallmark. If you miss it, you will chase peripheral causes that do not exist. Another mistake is underestimating the vascular territory map. The brainstem is supplied by the vertebrobasilar system, with branch arteries that have very specific zones. Anterior spinal artery hits the medial medulla. Posterior inferior cerebellar artery (PICA) hits the lateral medulla. Superior cerebellar artery (SCA) hits the midbrain and upper pons. Knowing which artery feeds which region lets you predict the clinical picture before you even look at the imaging. Wallerian degeneration in the brainstem is also more clinically significant than in the cerebrum. A small tract injury here can produce disproportionate deficits because there is nowhere else for the signal to go. The corticospinal tract at the medullary pyramids is a good example. A five-millimeter infarct there can cause dense contralateral hemiparesis that takes months to partially recover from.
What the textbooks leave out
The reticular formation is usually described in a single paragraph. In practice, it is the most variable and individually distinct part of the brainstem. People have different thresholds for arousal, different breathing patterns at rest, and different autonomic baselines — all governed by this network. When I manage patients on ventilators or with altered mental status of unclear origin, the brainstem reticular formation is always on my mind. It is the only explanation when everything else is ruled out. The brachium conjunctivum — the superior cerebellar peduncle — is another structure that gets glossed over. It carries outgoing cerebellar fibers through the midbrain and pons. Damage here causes contralateral ataxia and intention tremor, but it is easy to miss on standard sequences unless you are specifically looking for it. I learned this the hard way when a follow-up scan showed a lesion that should have been visible on the first one if anyone had paid attention to that tract.

When the brainstem diagnosis falls apart
Not every strange cranial nerve finding is a brainstem lesion. Multiple sclerosis can mimic brainstem strokes. Brainstem encephalitis can look identical to ischemia. A basilar artery aneurysm can compress the brainstem without actually infarcting it. And metabolic encephalopathies — especially osmotic demyelination — can selectively damage the pons while sparing everything else. If you are relying solely on clinical localization without imaging, you will be wrong sometimes. The brainstem is too crowded for clinical diagnosis alone. An MRI with diffusion-weighted imaging and MR angiography of the vertebrobasilar system is the standard. If those are unavailable, a CT angiogram of the head and neck is the minimum acceptable alternative. Skipping imaging in an acute brainstem presentation is not something I recommend under any circumstances. The brainstem is not mysterious. It is compact, it is organized, and it follows predictable rules. The problem is that most people learn the parts as a list to memorize instead of as a map to navigate. Once you treat it like a map, everything gets simpler.