What Actually Happens When You Take Pepto Bismol While Nursing
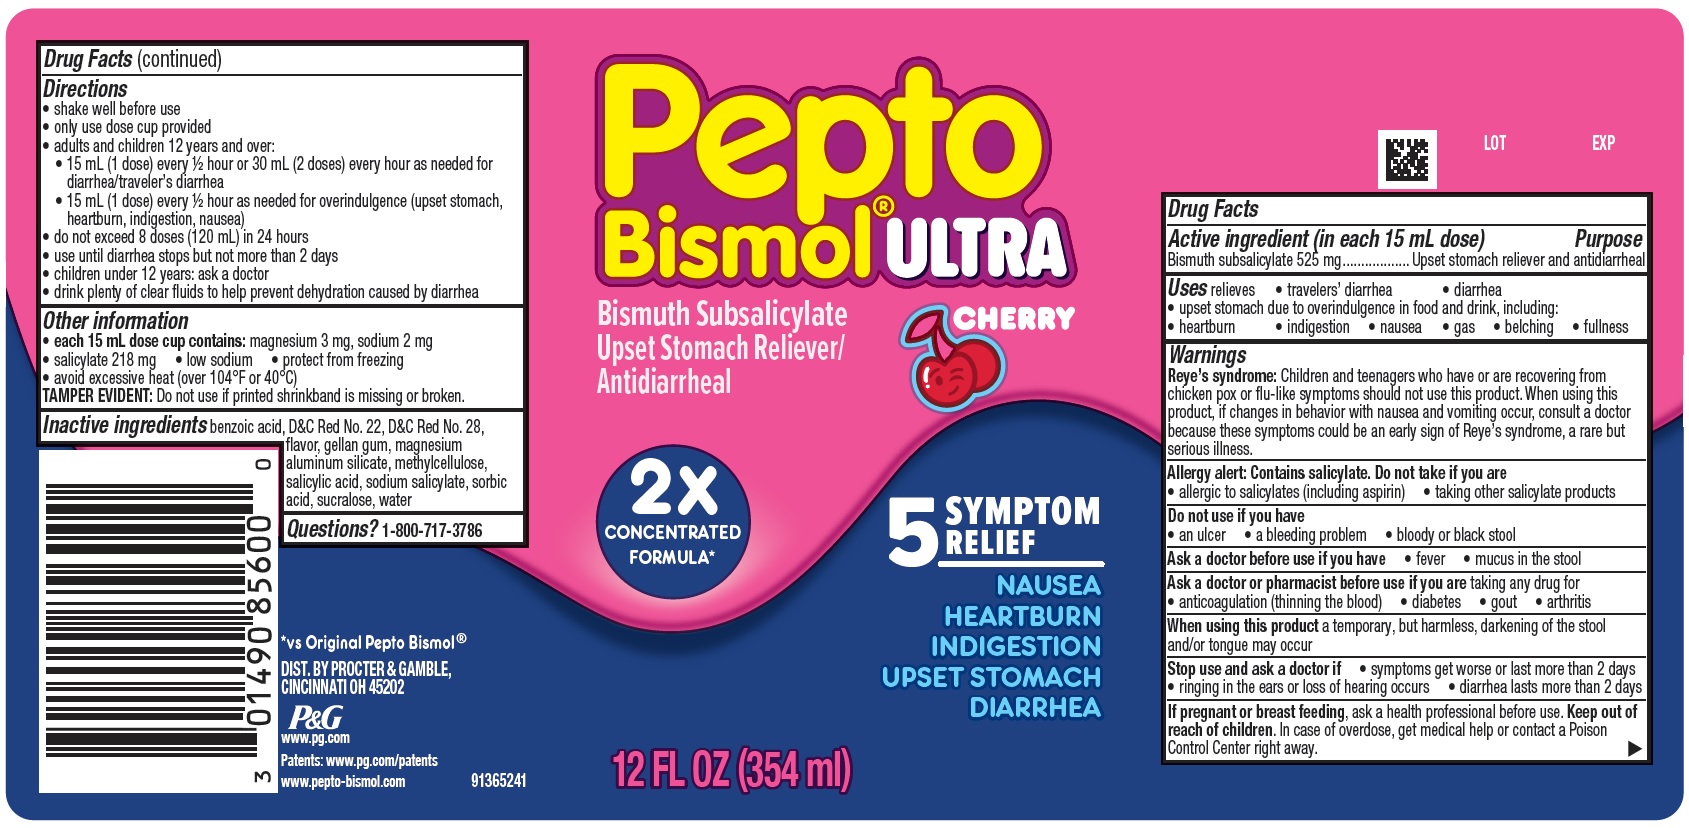
Pepto Bismol contains bismuth subsalicylate, which is related to aspirin. A small amount of salicylate passes into breast milk, and most sources say the quantity is low enough that occasional use is generally considered acceptable by pediatricians. That said, "acceptable" does not mean risk-free, and there are specific situations where you should skip it entirely. The primary concern is the salicylate component. Salicylates can accumulate in infants, and in rare cases have been linked to Reye's syndrome, a serious condition affecting the liver and brain. The risk is considered extremely low with occasional, single-dose use in older infants, but the concern shifts significantly for newborns, premature babies, or infants under six months old. Their livers and kidneys simply cannot process it as efficiently as an older baby's. I dealt with this head-on when my first child was about three weeks old and I couldn't keep anything down from a stomach bug. I went back and forth on whether to take the standard two-tablet dose or push through it. My pediatrician at the time said a single dose was unlikely to cause harm, but recommended I wait at least two hours after dosing before nursing next, since that's roughly when the peak concentration in milk would occur. I did that. No issues surfaced with the baby afterward.
But here is the nuance most people miss: bismuth subsalicylate is not well absorbed systemically even in adults, meaning only a fraction of the dose reaches your bloodstream and therefore your breast milk. Studies estimate the relative infant dose — the amount the baby gets through milk compared to a therapeutic dose — to be around 0.5% to 1% of the maternal weight-adjusted dose. That sounds small because it is. It is also not zero. Another thing nobody mentions enough: Pepto Bismol turns stool black. Both yours and, if it passes through milk, potentially the baby's. This is harmless and completely expected, but if your baby happens to be on any medication that also causes GI bleeding as a side effect, or if you notice actual blood in the diaper, that black color makes it much harder to tell what is going on. I learned this the hard way with my second child. He was six weeks old, I took Pepto for an upset stomach, and the next day his diaper had dark stools. I panicked briefly before remembering what I was taking. Still, it is worth flagging to your pediatrician proactively so they are not caught off guard. If you need something for occasional heartburn or indigestion instead of diarrhea or nausea, an H2 blocker like famotidine (Pepcid) has a far more extensive safety profile in nursing mothers and transfers into milk at negligible levels. It is not a panacea for every symptom, but it is a much safer default if your issue is acid-related rather than infectious or motility-related.
For actual diarrhea, the bigger issue is hydration. Oral rehydration solutions matter more than the anti-diarrheal itself, especially while breastfeeding, because you are already losing fluid through milk production. Loperamide (Imodium) is another OTC option with less systemic absorption than bismuth subsalicylate and minimal transfer to breast milk, though it does carry its own set of contraindications if you have an inflammatory bowel infection. The safest approach, honestly, is to check with your pediatrician or a lactation pharmacist before taking anything, even OTC. They can look at your baby's specific age, weight, and health history and give you a definitive yes or no. The internet will give you ranges and caveats. A professional who knows your kid will give you an answer you can actually act on.
Get the Full Details