A Practical Guide to Pericranial Tenderness Assessment
Most headache clinics still use the Pericranial Tenderness Assessment Test as a routine part of their physical exam, but there's almost no standardized way anyone is actually teaching it. I've watched dozens of residents and even attending neurologists vary wildly in how they apply pressure, which sites they check, and how they document the results. That inconsistency matters because pericranial tenderness is one of the softer diagnostic criteria in the ICHD-3, and poor technique can either inflate findings or miss real pathology entirely. The Pericranial Tenderness Assessment Test involves systematic palpation of the pericranial and cervical musculature using a standardized pressure point method. You are looking for areas where normal tissue compression produces localized tenderness that the patient can reliably identify and rate. The six standard sites are bilateral: temporalis, masseter, sternocleidomastoid, anterior trapezius, suboccipital, and the pericranial insertion at the superior nuchal line. I'll walk through the technique, the common mistakes, and a specific edge case that cost me a full hour of my time once. Start with the temporalis. Position your fingertip over the muscle belly just anterior to the tragus, then press downward with firm but controlled pressure—roughly equivalent to what you'd use to press into a ripe avocado, not a firm potato. Ask the patient to rate tenderness on a 0 to 3 scale while you press. Zero means no tenderness. One is mild and easily dismissed. Two is moderate and noticeable. Three is severe and causes the patient to flinch or pull away. Move systematically through each site. Don't rush. Each point takes about ten seconds to assess properly.
The masseter is trickier. The muscle sits deep behind the mandibular ramus, and too much lateral pressure just compresses skin and fascia without reaching the actual belly. Angle your finger slightly posteriorly and press medially toward the inner surface of the jaw. Patients with bruxism often have striking asymmetry here, and missing that subtlety makes your assessment less reliable. The sternocleidomastoid requires a different approach entirely. You're not pressing down. You're compressing the muscle between your fingers against the underlying structures. Pinch the belly gently between your thumb and index finger and roll. Tenderness here is common in cervicogenic headache but also shows up frequently in pure tension-type headache, so it's not pathognomonic for anything on its own. Anterior trapezius is the easiest site to palpate incorrectly. Most examiners press too superficially. The trapezius belly sits deep to the muscle's upper fibers. Ask the patient to relax their shoulders completely—dropping them away from their ears—then press into the midpoint between the shoulder prominence and the base of the neck. You should feel the muscle tense slightly under your fingers. If you're only pressing on subcutaneous tissue, the result means nothing.
Suboccipital tenderness is the site most people skip because it's uncomfortable for the examiner as much as the patient. Tilt the patient's head forward into slight flexion to relax the nuchal ligament, then press with your thumbs just lateral to the occipital protuberance where the obliquus capitis and rectus capitis posterior muscles originate. Two thumbs, symmetric pressure, slow compression. This area is often tender in both tension-type headache and cervicogenic headache, so note it but don't overinterpret it alone.
Get the Full Details

Documenting Results and Interpreting Findings
The ICHD-3 beta and later versions define pericranial tenderness as a supporting criterion for tension-type headache when tenderness is present at two or more pericranial sites bilaterally. But the literature on inter-rater reliability is frankly terrible. A 2014 study by Kosek and colleagues showed kappa values hovering around 0.3 between different examiners, which is barely above chance agreement. Another study from 2017 found that even the same examiner reassessed tenderness scores differently on repeat testing roughly 20 percent of the time. So here's the practical reality: document your findings with specific site notation, pressure grade, and patient-reported score. Write it down like this—temporalis bilaterally 2/3, masseter right 1/3 left 2/3, SCM bilateral 2/3, trapezius bilateral 2/3, suboccipital 3/3. That level of detail matters when someone else is reading your notes later, or when you're tracking changes over time during a treatment trial. The counter-intuitive part most beginners miss: pericranial tenderness does not reliably differentiate tension-type headache from migraine. Multiple studies including work from Bigal and Lipton have shown that up to 60 to 70 percent of migraine patients also exhibit pericranial tenderness during an attack. Using tenderness as a sole differentiator between TTH and migraine is not supported by the evidence. It's a useful supportive finding, not a decisive one.
Another thing nobody tells you: body mass index and skinfold thickness at the palpation sites significantly affect your ability to assess tenderness accurately. I've had cases where a patient with a higher BMI showed no tenderness on the temporalis and trapezius sites simply because my pressure was dissipating through subcutaneous fat before reaching the muscle. In those situations, I increase the applied force deliberately and press more slowly to allow deeper transmission, then I document that adjustment. It changes the scoring slightly but improves validity.
A Specific Edge Case That Changed How I Approach This Test
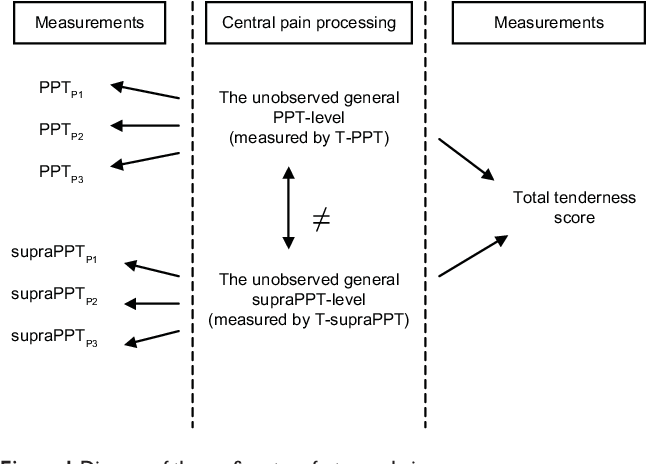
About three years ago, I had a patient presenting with chronic daily headache who scored zero on the entire Pericranial Tenderness Assessment Test. Every site, both sides, zero tenderness. By ICHD-3 criteria, pericranial tenderness was absent, which initially pushed me toward new daily persistent headache rather than tension-type headache. I started treatment down that pathway. Three weeks later, the patient returned saying the headaches were worsening significantly and the treatment wasn't touching it. I went back and re-examined with more attention to technique. The issue turned out to be central sensitization combined with a high pain threshold at superficial palpation sites. The patient's pericranial muscles were pathological, but the tenderness was located deeper than standard palpation could reach. I switched to using a palpometer for objective pressure measurement and adjusted my technique to press through the galea aponeurotica with sustained compression lasting five seconds per site instead of the usual one or two seconds. When I did that, the tenderness score jumped to bilateral 3/3 at temporalis and suboccipital regions. The diagnosis shifted. The treatment plan changed accordingly and the patient responded. The takeaway: standard digital palpation has a depth limitation. If the clinical picture strongly suggests pericranial myofascial involvement but the tenderness exam reads negative, consider that you may simply not be reaching the pathological tissue with your technique. Deeper sustained compression or a palpometer can reveal what light touch misses.

Limitations and When the Test Fails Completely
Let me be clear about where this test breaks down. It has poor sensitivity for diagnosing tension-type headache in primary care settings. Studies consistently show that a significant minority of patients who meet full ICHD-3 criteria for episodic tension-type headache do not exhibit pericranial tenderness on examination. Some estimates put that number at roughly 20 to 30 percent. A negative Pericranial Tenderness Assessment Test does not rule out tension-type headache. It also has poor specificity. Fibromyalgia, cervical radiculopathy, occipital neuralgia, and even internal carotid artery dissection can all present with pericranial tenderness. The test cannot distinguish between these conditions. If you're relying on it to separate migraine from tension-type headache, you will be wrong approximately half the time in a mixed headache clinic population. For patients with allodynia—where even light touch is painful—the standard pressure technique needs modification. Reduce applied pressure by half and use the lightest force that still contacts the muscle belly. Document the modification. Failing to adjust for allodynia produces artificially elevated tenderness scores that don't reflect true pericranial myofascial pathology.
If you need a more objective measurement tool, a digital palpometer such as the SOMASoft or equivalent devices provide quantitative force delivery and reduce examiner variability. They cost roughly $800 to $1,500 and require a brief learning period, but they cut inter-rater reliability issues significantly. For a busy outpatient clinic, the investment pays off within six months in terms of assessment consistency.
Quick Reference: Pericranial Tenderness Assessment Test Protocol
Palpation pressure: firm but controlled, approximately 2 to 4 kilograms of force. Patient position: supine or seated with head supported. Scoring: 0 = none, 1 = mild, 2 = moderate, 3 = severe. Sites: temporalis bilaterally, masseter bilaterally, sternocleidomastoid bilaterally, anterior trapezius bilaterally, suboccipital bilaterally. Time per site: 10 to 15 seconds. Total examination time: 2 to 3 minutes if performed correctly. Documentation should include per-site scores, patient position, and any technique modifications such as deeper pressure for high BMI or reduced pressure for allodynia. The test is simple to perform and quick to administer, which is why it persists in clinical guidelines despite its well-documented reliability problems. Use it as one component of a broader examination, not as a standalone diagnostic tool. Pair it with headache history, neurological exam, and where appropriate, imaging. That combination is what actually moves the needle on diagnostic accuracy.