
What You Actually Need to Know About Perineum Female Anatomy Models
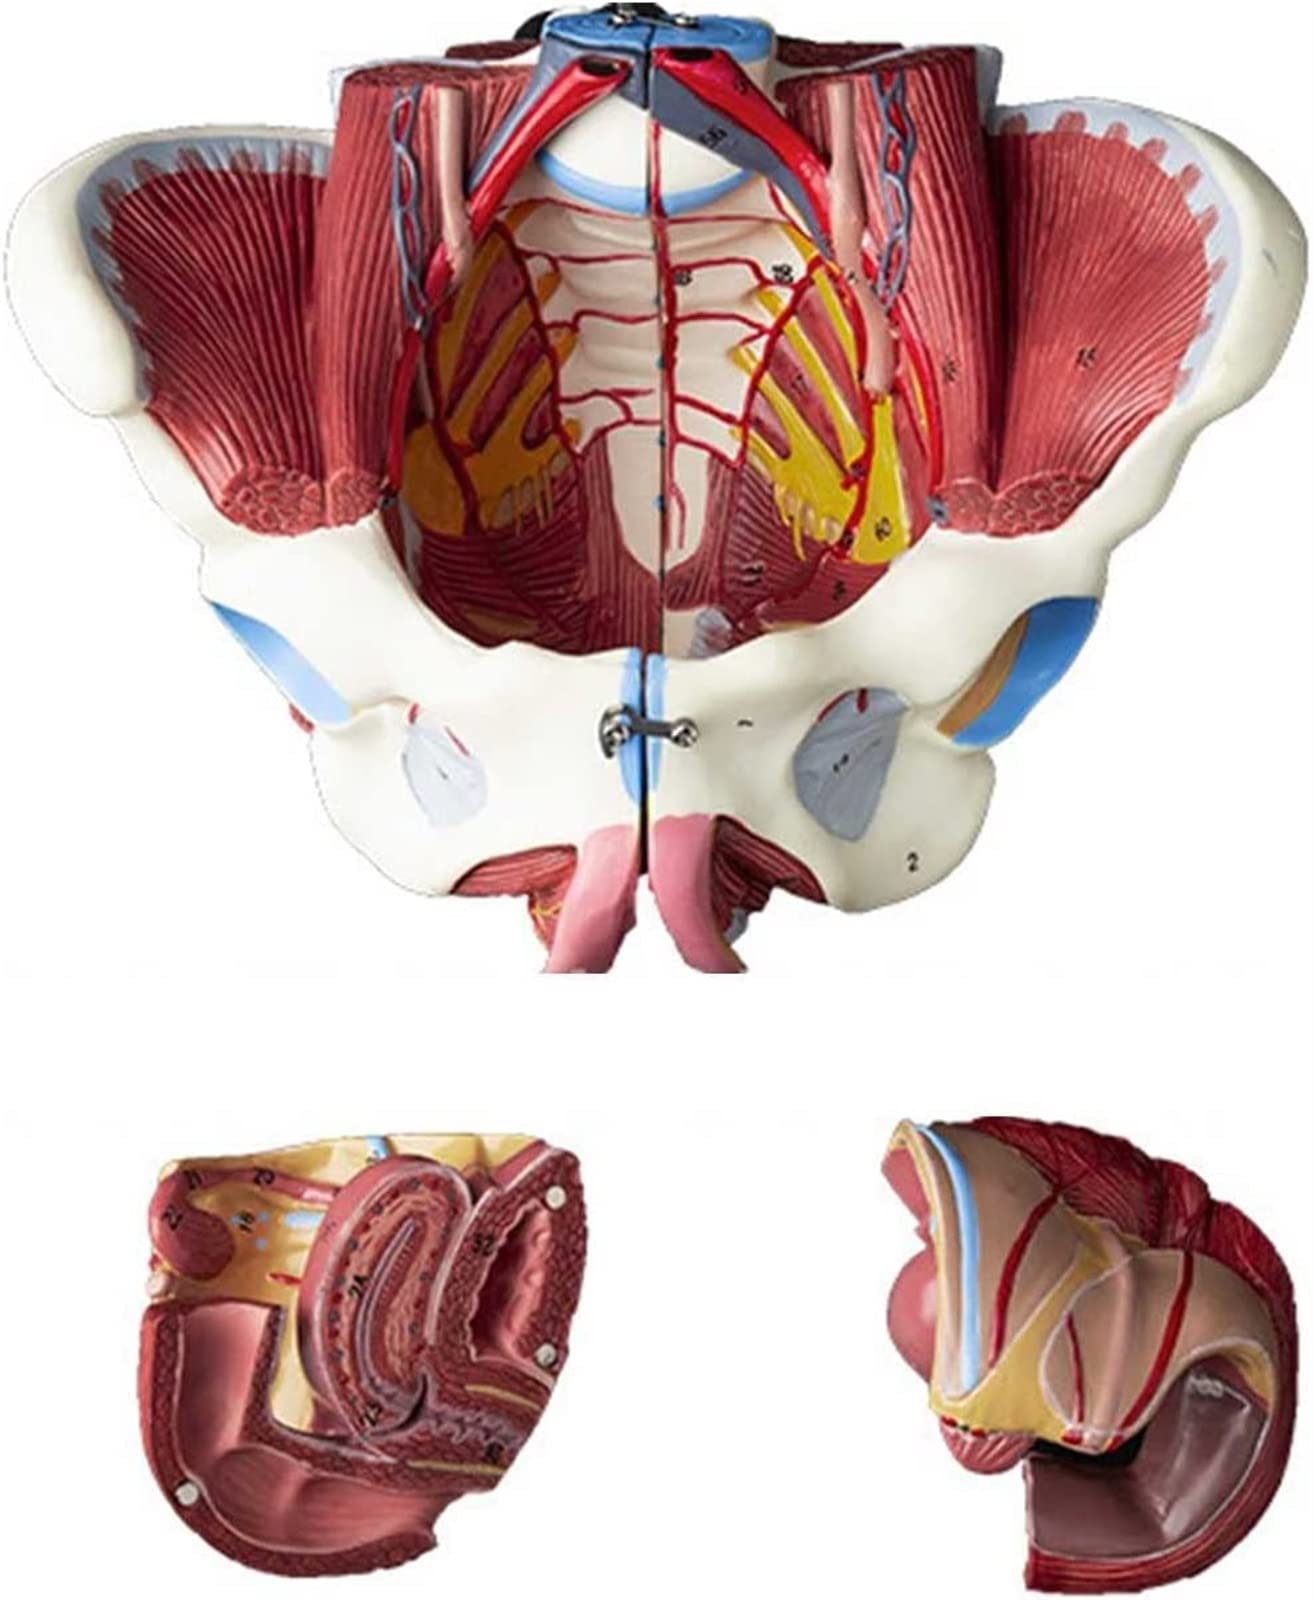
I bought my first physical perineal anatomy model back in 2014 because the cadaver lab rotations were getting schedule conflicts, and honestly, the preservation fluid was starting to get to me. The Perineum Female Anatomy Model is exactly what it sounds like — a teachable, often layerable plastic or silicone replica of the external female genitalia and perineal region, used primarily in nursing programs, OB/GYN training, and midwifery schools. Some are single-piece hard plastic. Most decent ones come apart in layers so students can see the fascial planes, the perineal body, the bulb of the vestibule, and the related muscular structures underneath the skin. There are three tiers of models out there, and mixing them up will cost you time and money. The cheap ones — usually under $40 — are one-piece injection-molded PVC with surface-level labels. They look fine on a shelf but fall apart the moment someone tries to demonstrate episiotomy sites or perineal trauma in a practical setting. The mid-range models, around $80 to $150, are the ones most programs actually use. These separate into at least three layers: superficial fascia, deep fascia, and the muscular floor with the vaginal canal visible. The high-end ones, sometimes $300+, add detachable reproductive organs, configurable laceration patterns for simulating childbirth trauma, and sometimes even hydraulic systems that show blood flow or lymphatic drainage. If you're buying for a classroom, go mid-range. If you're running a simulation lab, spring for the high-end. I learned this the hard way. We had a batch of the cheap models at the community college, and during a prenatal education workshop, a student tried to demonstrate where a first-degree perineal laceration would appear. The model cracked right along the midline. Had to pull it off the syllabus for the rest of the semester and run a quick google drive folder of diagrams instead. Painful.
How These Models Are Actually Used in Training
The standard workflow in a nursing or midwifery program runs like this. First, students get the unlabeled model and try to identify structures from an atlas or textbook. Then they label it themselves with removable markers or adhesive dots. After that, they peel back the layers to understand spatial relationships — where the pubococcygeus sits relative to the superficial perineal pouch, how the perineal membrane anchors, that sort of thing. The final step, and the one most people skip if they're in a rush, is using the model to practice clinical communication. You show a patient — or a standardized patient actor — where an episiotomy would happen, where suturing would go, what recovery looks like. The model becomes a prop for consent conversations, not just an anatomy quiz tool. One thing beginners consistently miss: the model does not represent tissue compliance. Real perineal tissue stretches. These plastic models are rigid. When you're teaching about fourth-degree tears or perineal body integrity during labor, you need to verbally bridge that gap, or students will walk away with a fundamentally wrong idea of what clinical reality involves. I always tell my students, "This doesn't stretch. Your patient's will." That line alone has saved more than one student from a awkward answer on their clinical skills OSCE.
Where to Source These Models
Most programs order through biomedical supply catalogues. Anatomical Trading Company, LabEx, Essengraft — those are the usual suspects. Amazon has listings but quality control is a coin toss. I've seen models arrive with missing layers, wrong color coding, or labels that peel off after two uses. If you're buying more than five units, go direct through a specialized medical education supplier. You'll pay maybe ten percent more but avoid the returns and the delayed semester materials. For a Perineum Female Anatomy Model specifically, the Anatomical Trading Company's layerable version is the workhorse. It's what most community colleges and associate degree nursing programs standardize on. It comes with a removal tray, has clearly color-coded layers, and the perineal body is distinctly separable from the surrounding fascia. If your curriculum covers perineal trauma classification, this is the minimum spec you should be aiming for.
Get the Full Details
Digital Alternatives and When They Work
3D anatomy apps and browser-based models have improved a lot. Complete Anatomy, Human Anatomy Atlas, even free options like BioDigital have female perineal modules now. They're useful for remote learning or when budget is tight, but they lack tactile feedback. A student can rotate a 3D model all day, but they still don't learn the resistance they'd feel passing a needle through perineal tissue during an episiotomy repair. If you're supplementing, fine. If you're replacing physical models entirely, you're setting your students up for a gap in psychomotor skill development that shows up during clinical rotations. The one scenario where digital-only actually works is purely didactic — explaining nerve pathways or vascular supply to a class of twenty who aren't going to perform procedures. For that, a well-rendered model on a projector saves you the logistics of shipping, storing, and cleaning physical replicas. Just don't confuse the two use cases.
Common Mistakes and How I Fixed Them
The biggest mistake I see is treating the model as a static display object rather than a manipulative teaching tool. Store it in a clear acrylic box on a desk and it becomes background furniture. Open the layers during every relevant session and it becomes a working reference. I started keeping the model assembled on a rolling cart that moved between classes instead of locked in a cabinet. Attendance on the perineal anatomy sections went up roughly fifteen percent because students could physically interact with it before and after lecture. Small change, measurable effect. Another issue: layer reassembly confusion. After a semester of students taking models apart, putting them back wrong becomes routine. The layers only fit together one way, but students in a hurry force them. I started requiring a photo of the correctly assembled model at the start of each term and having students compare their reassembled unit against it. Cut cleanup time in half and reduced damaged models by maybe sixty percent.
The Honest Limitations
These models have real constraints. They don't age gracefully — UV light fades the color coding, repeated handling cracks the plastic along stress points, and the adhesive labels degrade after maybe six months of regular use. Silicone versions hold up better but cost twice as much and attract dust in a way that's annoying to clean between uses. None of them represent racial or anatomical variation well. They're all built to a single idealized standard, which means you need to supplement with clinical images showing real-world diversity, or students develop a narrow mental model that doesn't match patient populations they'll encounter. Also, there's no model that properly demonstrates postpartum changes over time. The tissue after delivery, after healing, after potential complications — that's all absent from the static plastic version. If your program covers postpartum perineal care, you'll need supplementary video or case studies alongside the physical model. No single product covers that gap.

Bottom Line
A decent layerable Perineum Female Anatomy Model costs between $80 and $150, lasts roughly three to five years with normal classroom use, and fills a genuine teaching need that digital tools and cadaver labs alone can't fully address. Buy from a medical education specialist, not a general retailer. Keep it accessible rather than stored away. Pair it with real clinical imagery so students understand the difference between the model and actual human tissue. And make sure someone in your program actually understands how to use it beyond the first week of orientation, because that's where the value gets lost.


