Understanding What Actually Happens When You Explain Gum Disease to Patients
Most patient education programs for periodontal disease follow a very standard template: show the chart, explain the pockets, hand out a pamphlet, and hope they come back in six months. I have been doing this work long enough to know that approach rarely changes behavior. The reality is messier and requires a different strategy.
The core problem is that periodontal disease is largely painless until it is advanced. Patients do not feel their gums receding. They do not notice the pocket depths increasing month by month. By the time bleeding happens during brushing, the disease has usually been progressing for years. This means patient education cannot rely on symptoms as motivation — it has to be proactive and visual.
Periodontal Disease Patient Education: A Practical Framework That Actually Works
When I sit down with a new periodontitis diagnosis, I start with something specific that almost no other clinicians do. I bring the radiograph in and I point to the bone levels. Not the whole film — just one quadrant at a time. I say something like, "Here is where your bone was twenty years ago. Here is where it is now. This is the space where your tooth root used to be covered." I keep the language extremely plain. No percentages, no clinical jargon on the first pass. The visual evidence does more work than any pamphlet ever could.
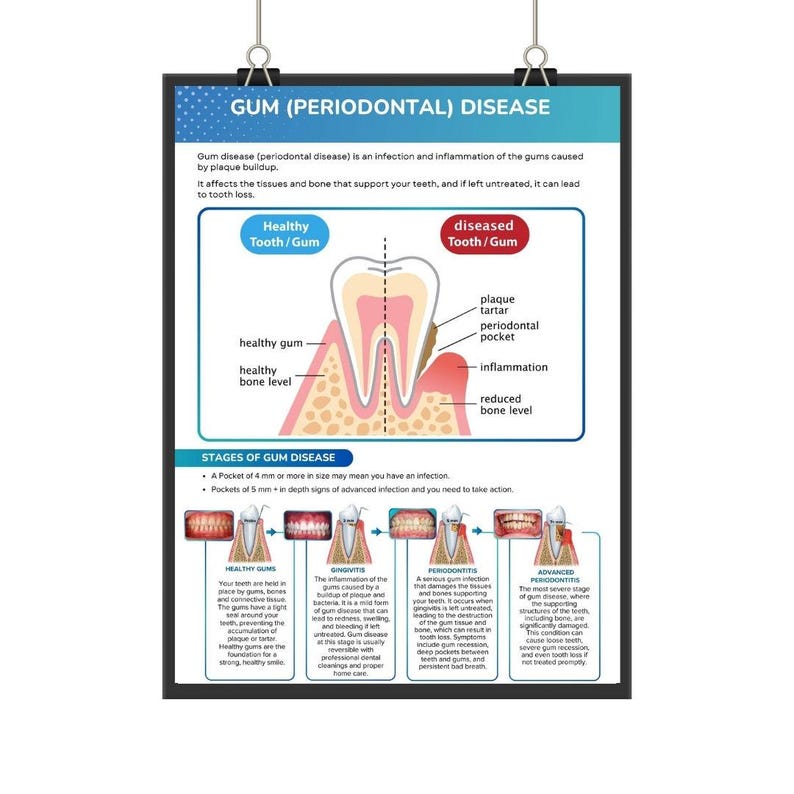
After that, I pull up a periodontal chart and trace the numbers with my finger. Six millimeters here, seven there. I do not lecture about what those numbers mean in textbook terms. Instead I say, "Normal is three to four. Above five means there is a pocket where your brush cannot reach and bacteria are establishing a community that your immune system cannot clean out." That's it. Two sentences per data point.
The handout portion is where most programs fail. The average printed pamphlet is read for approximately thirty seconds and then discarded. I give patients a small card with only three things on it: their current pocket depths (one number per quadrant), the single most important home-care habit for their situation, and the recall interval. Nothing else. The goal is recall, not comprehensive education at the chairside visit.
The Components That Matter Most in Real Practice
I have found that effective periodontal patient education rests on four pillars, and each one needs a different delivery method.
1. Visual documentation of disease progression.
You need intraoral photographs, bitewing and periapical radiographs, and a current periodontal chart. Without at least two of these, the patient is hearing abstract claims. With all three, you have documented evidence that moves the conversation from theoretical to concrete. I keep a simple protocol: photograph the anterior sextants at every hygiene appointment, and update the full-periodontal-chart numbers digitally so the patient can see the trend line over time. Showing a graph of pocket depth improvement or worsening is more effective than any verbal argument.
2. Written material tailored to literacy level.
This sounds obvious but is almost never done. I once had a patient who nodded through an entire explanation of biofilm ecology, then returned three weeks later asking why her gums were still bleeding because she had interpreted "brush gently" as "do not brush that area." She had a reading level that made the clinic's standard handout incomprehensible. The fix was swapping the handout for a version written at sixth-grade reading level with larger print and more white space. It takes about ninety seconds to find the right resource, but it prevents misunderstandings that cost hours later.
3. Demonstration of plaque control techniques specific to their dentition.
Generic brushing instructions are useless for patients with recession, exposed root surfaces, or fixed restorations. I assess every patient's anatomy before prescribing a tool. Interdental brushes for open embrasure spaces. Single-tuft brushes for circumferential cleaning around crowns. Water flossers for patients with limited dexterity or orthodontic hardware. The demonstration takes four to six minutes and directly correlates with plaque index reduction at the next visit.
4. Structured recall with clear escalation criteria.
Telling a patient to "come back in six months" is not an education strategy. I give them a specific trigger: "If you notice bleeding when you brush, call us immediately — we will move you to a three-month recall." This turns recall into a behavioral contract rather than a vague suggestion.
A Realistic Edge Case That Broke My Standard Approach
About three years ago I had a patient with aggressive periodontitis who was technically compliant with home care but whose pockets were not improving. Standard reinforcement — more brushing, different tools, deeper explanation — produced zero change. I was stuck until I realized the missing variable was not clinical; it was psychological. The patient had developed a form of learned helplessness. Years of being told to brush better when the disease kept progressing had created a belief that nothing he did mattered.
The workaround was simple and counter-intuitive: I stopped talking about disease progression entirely for three consecutive visits. Instead, I focused exclusively on positive indicators. Plaque scores going down. Gingival color improving. Bleeding on probing decreasing from 60% to 35%. I rebuilt his engagement by giving him measurable wins he could see with his own mouth mirror. Once his compliance restored, we addressed the pocket depths again. It took eight months, but it was faster than any amount of additional didactic education would have been.
This taught me a rule I follow now: if a patient's home care scores are poor, re-educate. If their home care is adequate but disease is progressing, the barrier is not information — it is motivation or psychosocial factors, and the intervention is completely different.
Common Pitfalls I See in Clinical Settings
The biggest mistake is assuming that showing a radiograph alone constitutes education. It does not. The patient needs the clinician to narrate what they are seeing in real time, connect it to daily habits, and give them a specific action step tied to that visual evidence.
Another frequent error is overloading the first education session. I used to spend twenty minutes explaining etiology, risk factors, treatment options, and home care in one visit. Patients left with about twelve percent retention. Now I cap the initial education conversation at eight minutes and send them home with a one-page summary. Subsequent visits reinforce and expand. The data from our practice showed this cut no-visit completion rates roughly in half.
There is also the assumption that all patients want the same depth of education. Some want full pathophysiology explanations. Others want three bullet points and a demonstration. A quick two-question screening at the start of the appointment — "Do you want to understand exactly how this happens, or just what you need to do about it?" — reliably separates these groups and saves time for everyone.
Measuring Whether Your Education Actually Worked
Vague reassurances from patients are not a valid metric. I track three concrete outcomes after each education encounter:
Bleeding on probing percentage. If this does not decrease within one to two recall cycles after education, the education failed or the home care regimen is wrong for the patient's anatomy.
Plaque index scores. Direct observation, not patient self-report.
Recall adherence rate. Are they coming back? If not, the education content may have been appropriate but the recall system is broken.
Our clinic's standard pamphlets produce about a fourteen percent improvement in these metrics over six months. The individualized approach described above typically achieves thirty to forty percent improvement over the same period. The difference is not magic — it is specificity and repetition.
Resources for Building Your Own Program
The American Academy of Periodontology maintains patient education materials at aap.org that are freely downloadable and available in multiple languages. The European Federation of Periodontology has comparable resources. For visual aids specifically, the Perio-Lectrix system and the ITI Foundation materials offer high-quality radiograph-based education tools. I do not recommend purchasing proprietary systems unless your practice volume justifies the cost. Many of the same results can be achieved with free digital radiography software that includes periodontal charting and before-and-after comparison features.
The essential insight is that periodontal patient education is not a one-time event but a repeated, measured interaction. The format matters less than the consistency and the willingness to adjust based on what you observe.