Where to Actually Stick a Peripheral IV and What Goes Wrong
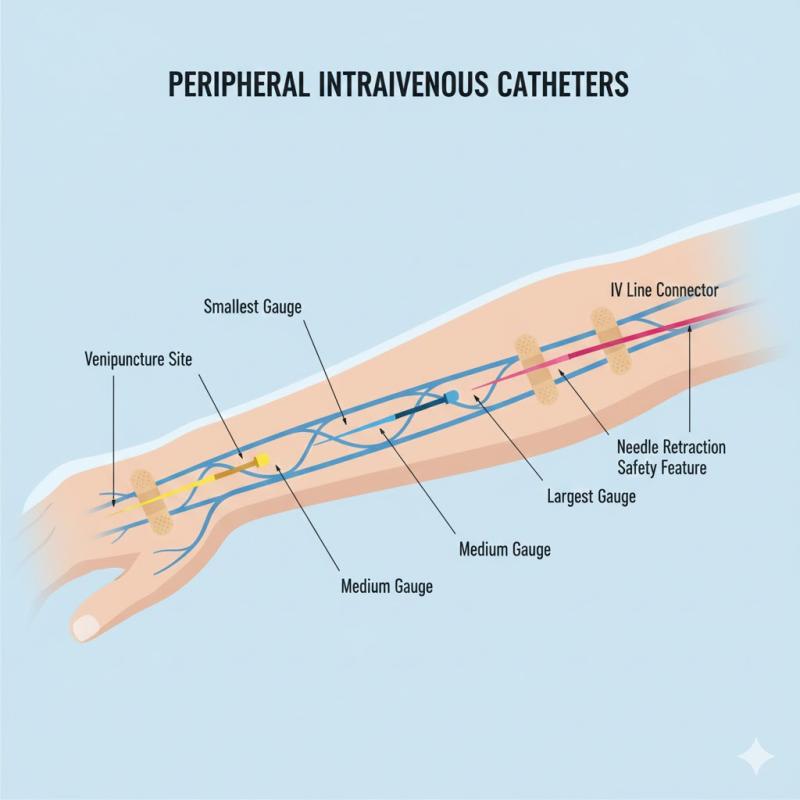
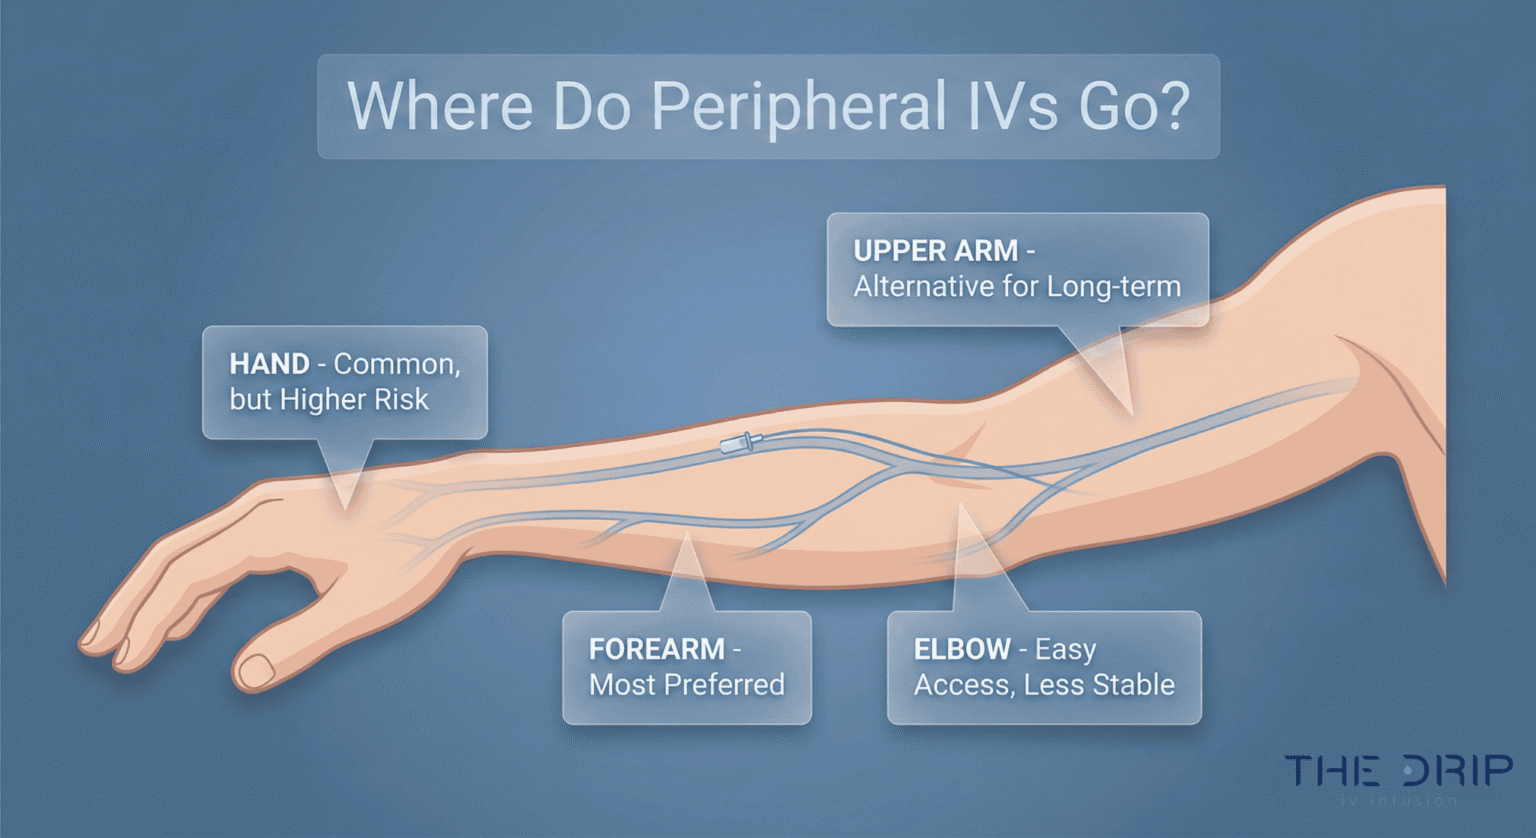
The forearm remains the standard first choice for peripheral iv line sites because it gives you a stable surface, decent vein caliber, and easy patient access without competing with the legs or neck. I used to place them in the dorsal hand because it was fast, but I stopped after watching three infiltrations in a single shift. The hand veins are smaller, the skin moves too much, and patients will dislodge them before you finish securing the dressing. Forearm is slower to find but stays in significantly longer. Here is the basic algorithm nobody writes down anymore. Palpate first. Look is overrated. A vein you can feel that slides a little under the skin but not too much is your candidate. If it rolls, that means loose connective tissue around it, which translates to the needle walking off when you start advancing. If it feels hard and tubular with no give, that is likely thrombosed or sclerosed from prior sticks. Move on. The cephalic vein at the wrist runs from the radial side up toward the elbow. It is usually the most reliable. The basilic vein is bigger but sits closer to the brachial artery and median nerve, so I avoid it unless I am in a trauma resuscitation scenario and need volume fast. Antecubital fossa veins work for short procedures but you cannot flex the arm afterward without bending the catheter against the vessel wall. That causes phlebitis and infiltration within hours.
I once had a patient whose medial antebrachial cutaneous nerve was running directly across the path where the vein was visible. She was dehydrated, the vein was small, and everything looked perfect on inspection. I placed the 22-gauge without thinking and she screamed immediately. The nerve had been right there under the skin where I thought was safe tissue. I withdrew, held pressure for five minutes, and went to the contralateral arm. Never trust a vein map from a textbook when the patient has low BMI and poor hydration. Ultrasound guidance would have shown me the nerve as an anechoic structure right next to the target vein. I learned that quickly.
What the Literature Actually Says About Site Selection
The Infusion Nurses Society guidelines recommend rotating sites every 72 to 96 hours in adult patients who do not need continued access. That rotation schedule is not about the catheter failing physically. It is about reducing the risk of catheter-related bloodstream infection and phlebitis. A study from the Journal of Infusion Nursing showed that sites left beyond 96 hours had a 2.3 times higher incidence of phlebitis compared to those changed at the 72-hour mark. The difference was statistically significant and the effect size was moderate, not trivial. Another counter-intuitive point: smaller gauge catheters do not necessarily last longer. A 24-gauge may cause less vessel trauma initially, but it clogs more often with certain medications like antibiotics suspended in lipids. When the lumen partially obstructs, the nurse restarts the infusion, the patient gets extra discomfort, and you end up replacing the site anyway. A 20-gauge in a robust forearm vein might actually outlast a 24-gauge in the same location when you are running multiple infusions. I work in a general medical unit where we run broad-spectrum antibiotics, maintenance fluids, and the occasional vasopressor drip during code situations. We use 20-gauge or 18-gauge on the non-dominant forearm as our default. The dominant arm gets avoided because patients will inadvertently compress the dressing against their body while eating or writing. That pressure changes the angle of the catheter tip inside the vein and can cause the tip to abrade the vessel wall.
Get the Full Details

Practical Problems You Will Encounter
Veins collapse when you insert the needle at too steep an angle. Forty-five degrees is the standard teaching, but if the patient has thin skin and superficial veins, thirty degrees is more appropriate. I have seen nurses punch in at forty-five and blow the vein before the catheter even enters the lumen. The vein punctures through and blood flashes back into the hub, but the catheter is now sitting in perivascular tissue. You start the infusion and the arm swells within twenty minutes. Infiltration grades range from zero to three on the Infusion Nurses Society scale, and by grade two you are losing the limb function to edema. Securement devices matter more than people admit. I switched our unit to transparent semi-permeable dressings with built-in sting-free prep pads about four years ago. Before that, we used standard gauze and tape, and the adhesive irritated the skin on elderly patients within a day. The dressing alone reduces mechanical phlebitis because it keeps the catheter from migrating out of the vein with movement. A catheter that migrates out by even two millimeters can pierce the anterior wall of the vein. Scanning with ultrasound is not reserved for ICU. I carried a portable linear probe on my med-surg floor and scanned every difficult stick. Veins that were not palpable became visible. The femoral vein shows up on ultrasound even in obese patients where you would never attempt a peripheral stick by palpation alone. The downside is that femoral sites carry a higher infection rate and the patient has to remain relatively still. I only used it when the forearm and upper arm options were exhausted.
When to Stop Trying
If you have attempted two peripheral sticks with no return and the patient needs ongoing IV access, call for a venous access team or an ultrasound-guided placement. Continuing past two failures increases the risk of hematoma, arterial puncture, and patient anxiety to a point where cooperation drops and you make more mistakes. I lost count of how many hematomas I formed by pushing through a third attempt after two failures. It does not indicate skill. It indicates stubbornness. Medications that are vesicants or have a pH outside the 5 to 9 range require careful site selection regardless of gauge. Vancomycin at high concentrations causes tissue necrosis if it infiltrates. Phenytoin is another classic offender. For those drugs, a large bore catheter in a proximal forearm vein with good flow rate confirmation before starting the infusion is non-negotiable. I check flow by aspirating blood return and observing that the infusion runs freely under gravity before attaching the medication. A sluggish run under gravity means the tip is against the vessel wall or the catheter is partially kinked. Do not push medication into a compromised line. There is no perfect site. The best you can do is pick the vein that minimizes movement, maximizes flow, and keeps the catheter stable for the duration of the therapy. Everything else is incremental refinement.