Getting Past the Basics
The Peripheral Vascular System Assessment is the process of evaluating blood flow through the arteries and veins of the extremities, most commonly the legs and arms. It involves a combination of visual inspection, palpation of pulses, auscultation for bruits, and measurements like the ankle-brachial index. I keep saying this because a lot of guides skip the messy reality of how this is actually done on a real patient with a real body, not a textbook diagram. Let me walk through what it looks like when you're in the room doing the work.
Peripheral Vascular System Assessment: The Practical Walkthrough
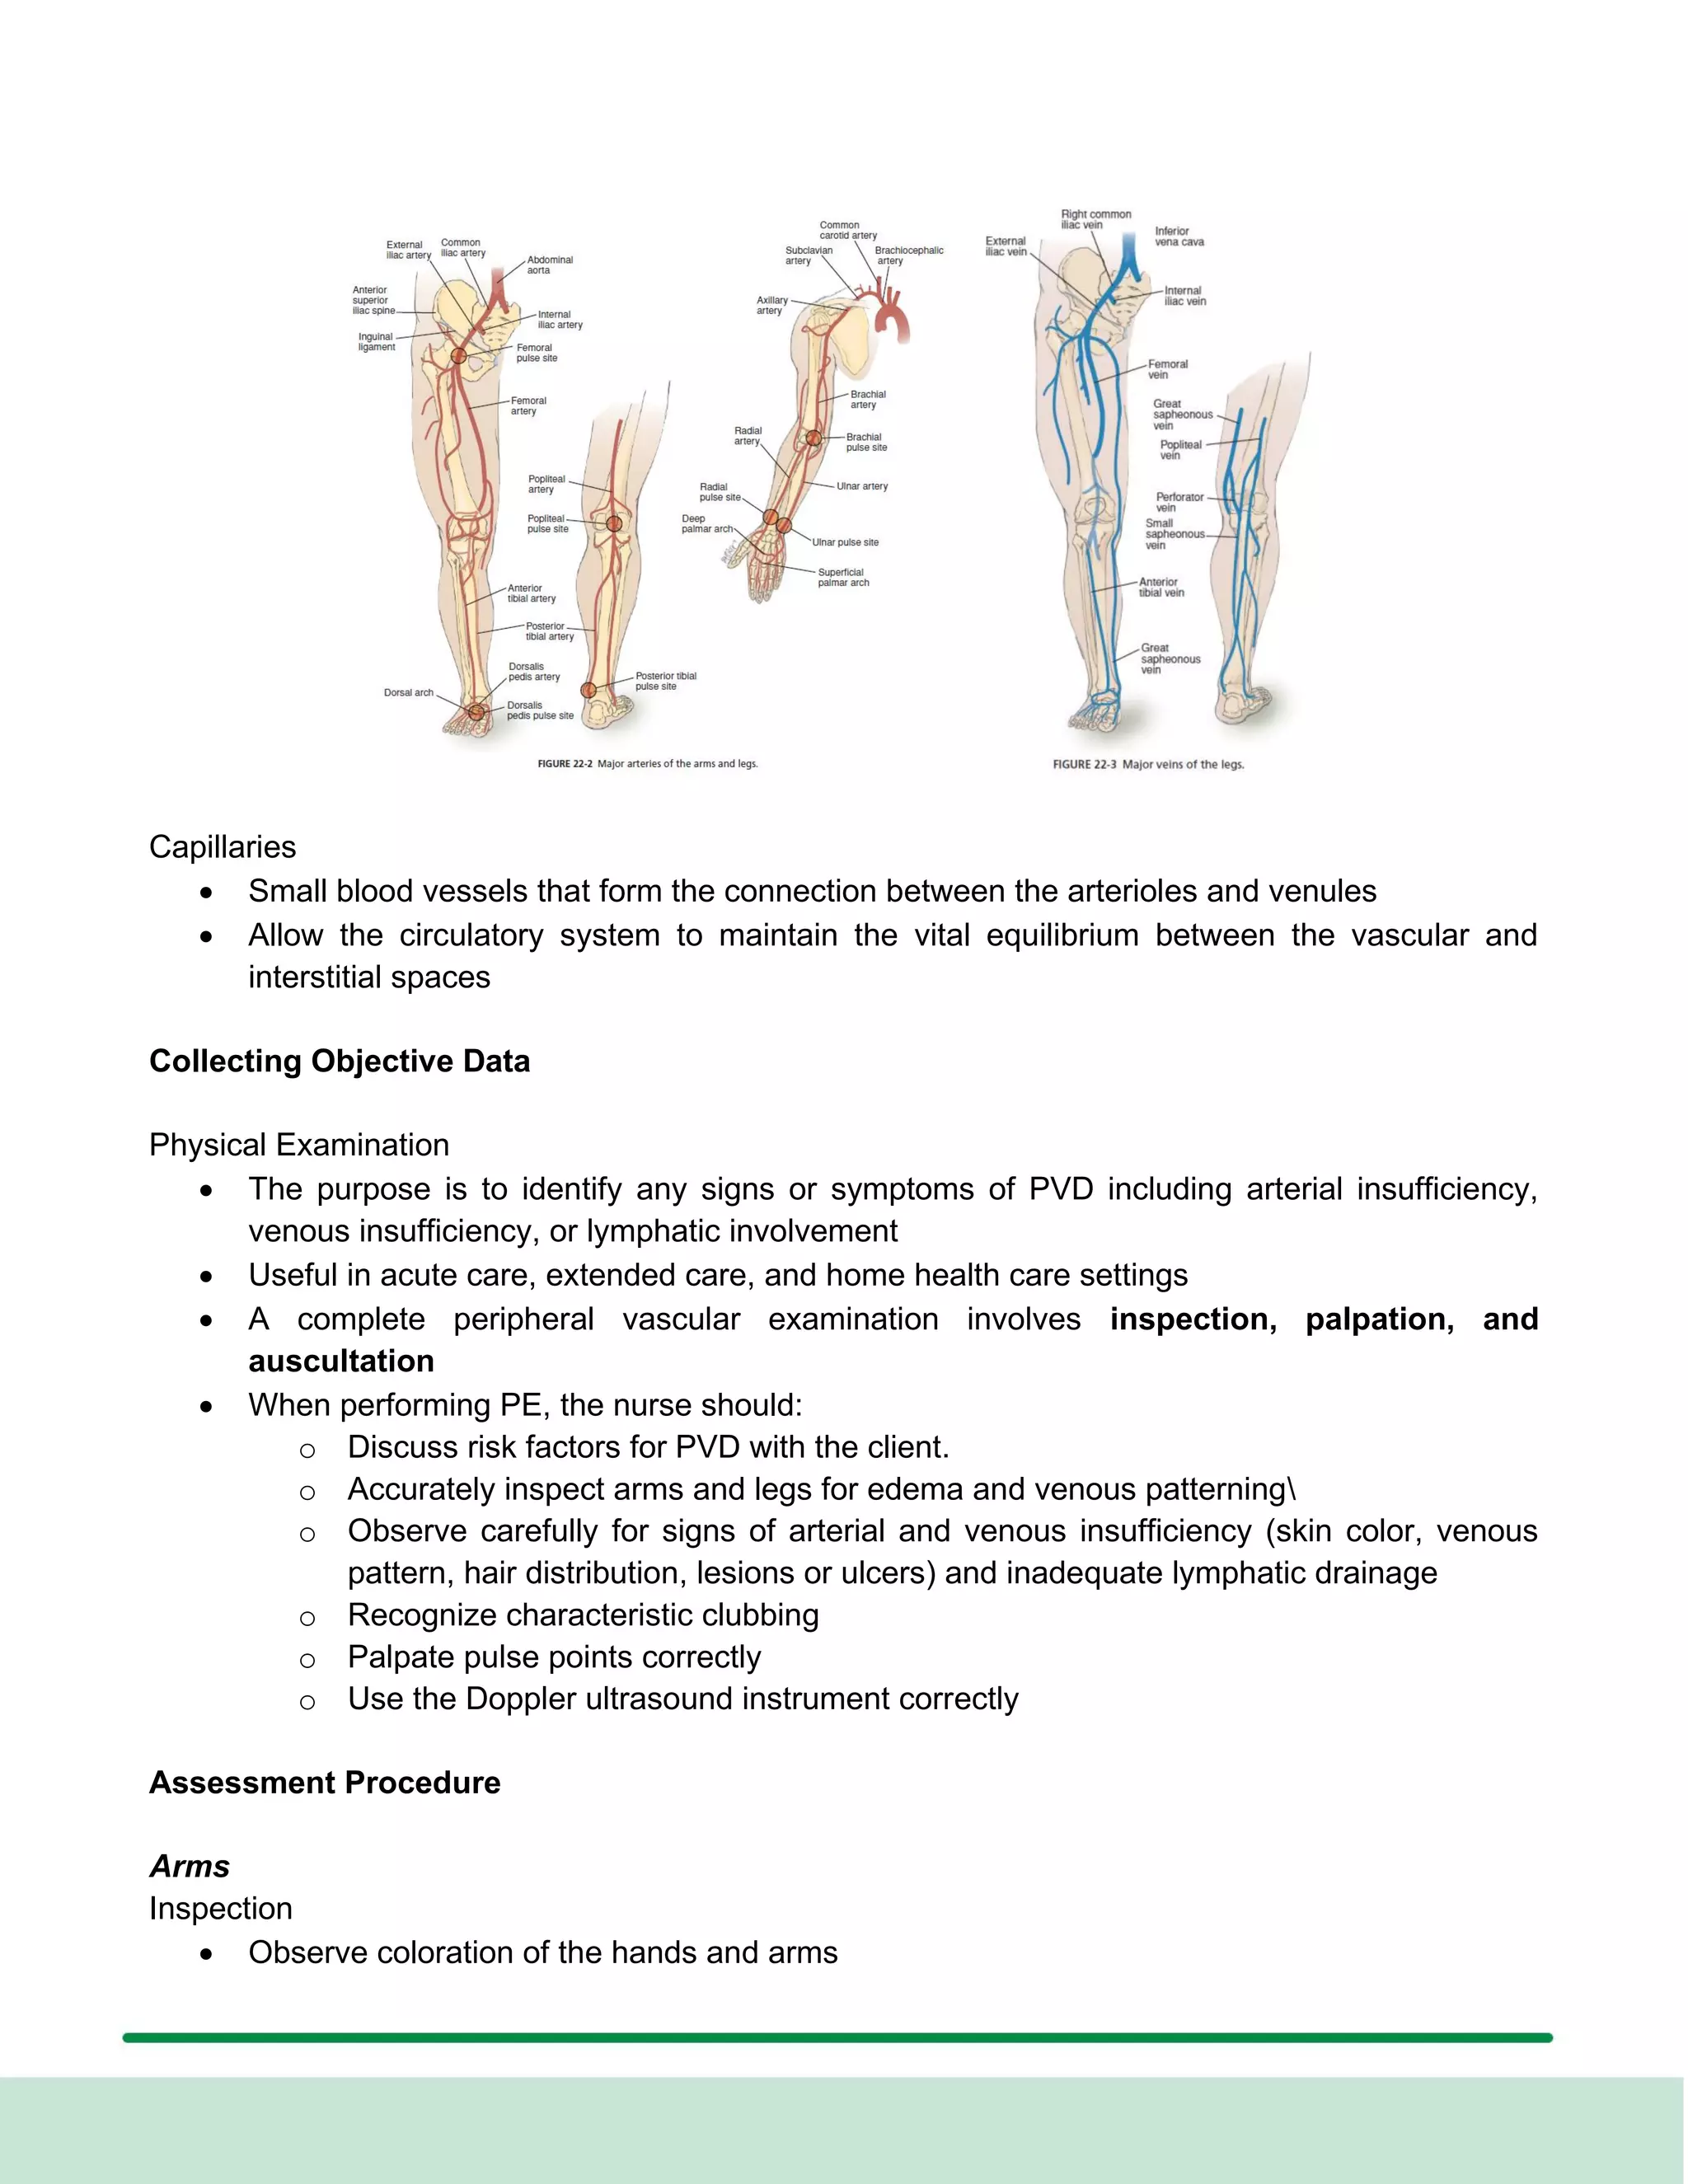
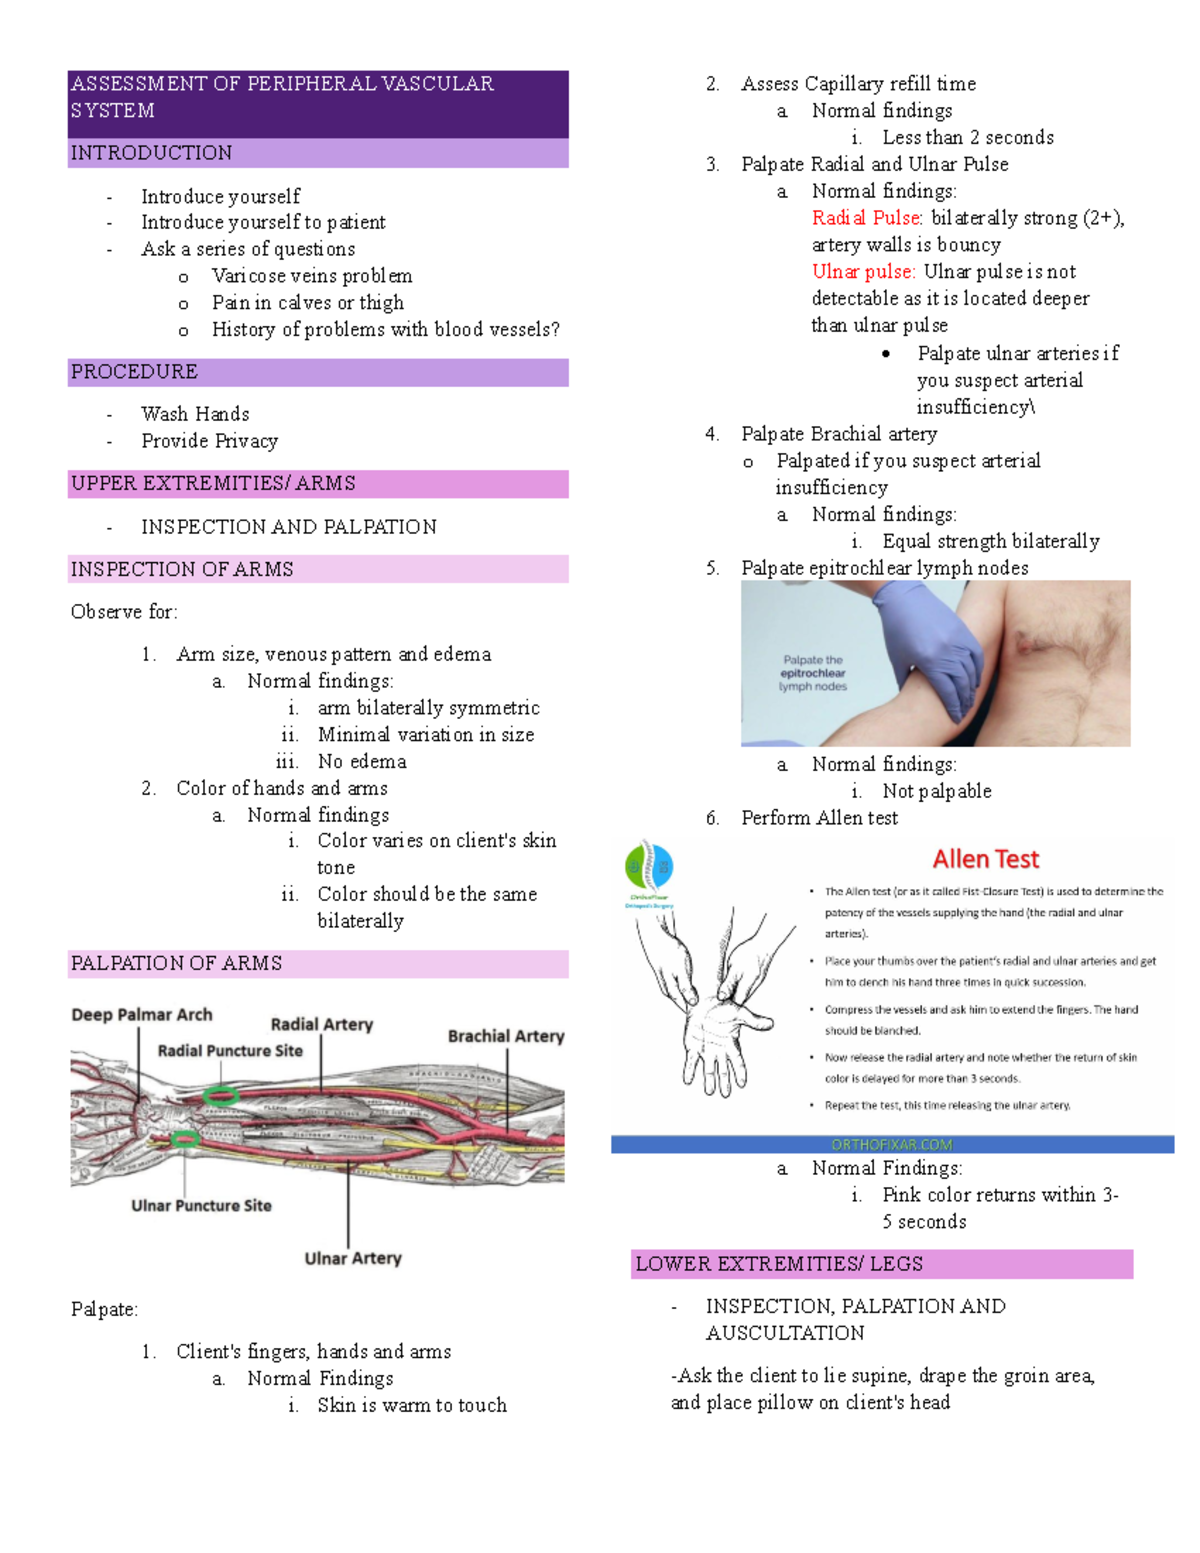
Start with the patient seated or supine, whichever position gives you the best access to the area you're examining. Remove compression garments if they're wearing any. You need to see the skin properly. Visual inspection comes first. Look for color changes — pallor with elevation, rubor when dependent. Check for hair loss on the toes and shins, which suggests chronic ischemia. Note any ulcers, especially those positioned on the lateral malleolus or distal toes rather than pressure points. Look for venous stasis changes: hemosiderin deposition, lipodermatosclerosis, varicosities. The skin texture tells you something even before you touch anything. Palpation of pulses is where most people rush. Don't. Use the pads of your fingers, not the fingertips. Assess the radial, brachial, femoral, popliteal, posterior tibial, and dorsalis pedis pulses bilaterally. Grade them as 0 (absent), 1+ (diminished), 2+ (normal), 3+ (bounding), or 4+ (water-hammer). Document each one. I've seen people document "palpable" for all pulses and then realize later they couldn't actually differentiate between a 1+ and a 2+ because they never trained their hands to feel the difference.
The popliteal pulse is particularly difficult to palpate in most adults. If you can't find it after two minutes, stop trying to dig for it and move on. Use Doppler. This isn't failure, it's pragmatism. Auscultation for bruits should be done before palpation, ideally, because the pressure from your fingers can temporarily alter the sound. Listen over the carotid, femoral, and renal arteries if you're doing a comprehensive exam. A bruit doesn't necessarily mean critical stenosis — it means turbulent flow somewhere upstream. A harsh, systolic bruit over the femoral artery with a diminished pulse distally is a much more concerning combination than a soft, early systolic whoosh. The ankle-brachial index is the single most useful objective measure you can take at the bedside. You need a Doppler device that costs around $40 to $150 and a blood pressure cuff. Measure the systolic pressure at the brachial artery bilaterally and take the higher value as your denominator. Then measure systolic pressures at the dorsalis pedis and posterior tibial arteries on each ankle. Divide each ankle pressure by the brachial pressure. A normal ABI ranges from 0.9 to 1.3. Below 0.9 indicates peripheral arterial disease. Above 1.3 suggests non-compressible vessels, which is common in diabetes and chronic kidney disease, and means the ABI is unreliable for that patient.
Get the Full Details

What People Miss
Here are a few things I learned the hard way. Pulse volume matters more than pulse presence. A strong, bounding pulse in one leg and a thready pulse in the other is clinically significant even if both pulses are technically "palpable." Compare side to side every time. Asymmetry is information. The timing of pulse assessment changes with patient position. When you elevate the leg to check for pallor, hold it at 60 degrees for about 60 seconds. Watch how long it takes for color to return when you dangle the leg. Delayed capillary refill in the great toe — more than 3 seconds with the foot elevated — is a sign of significant arterial insufficiency. This test, the Buerr test, is old and nobody uses it enough.
Venous assessment is part of the same encounter. Don't finish the arterial part and walk away. Perform the Homan's sign gently — though I acknowledge its sensitivity and specificity are poor — and do a more reliable assessment: look for calf tenderness, measure circumference at the widest point of the calf and compare sides, check for pitting edema and grade it. A unilateral swollen tender calf in a patient who recently flew somewhere or had surgery is a pulmonary embolism waiting to happen until proven otherwise.
A Real Problem I Ran Into
Years ago I was assessing an elderly patient with known peripheral artery disease and diabetes for a pre-operative clearance. Her dorsalis pedis pulses were completely absent bilaterally by palpation, and her ABI came back at 1.5 on both sides, indicating calcified vessels. The numbers told me nothing useful about whether her legs actually had adequate perfusion for surgery. I couldn't rely on the ABI. I couldn't rely on palpation. What I did was use a handheld Doppler to assess the waveform morphology at the dorsalis pedis and posterior tibial positions. A normal triphasic waveform with a sharp systolic upstroke and flow reversal indicates healthy vessels. A biphasic or monophasic dampened waveform suggests significant stenosis proximal to the point of measurement. Her waveforms were monophasic and dampened, confirming that despite the unreliable ABI, she did have significant distal arterial disease. I recommended vascular surgery consultation before the planned procedure. The surgeon agreed and adjusted the surgical approach accordingly. Doppler waveform analysis is the workaround when palps and ABIs fail you. It doesn't require expensive equipment or a radiologist. It requires a Doppler device and the ability to recognize waveform patterns.
Common Pitfalls
Using the wrong cuff size is the most common technical error. If the cuff bladder doesn't encircle at least 80% of the limb circumference, the reading will be falsely elevated. A thigh cuff on a large calf will give you a misleading result. Measure the limb before you slap a cuff on it. Assuming a normal ABI rules out disease in diabetics. As I mentioned, calcified vessels produce artificially high readings. In these patients, consider toe-brachial index instead. The pressure at the toe is less affected by medial calcinosis. A toe pressure below 0.7 is abnormal regardless of the patient's diabetes status. Skipping the comparison. Always measure both sides. A right arm blood pressure of 140 and a left arm blood pressure of 110 isn't a normal variant — it could indicate subclavian stenosis on the left. Document both. If there's a persistent inter-arm systolic difference greater than 20 mmHg, that warrants further vascular investigation.
When This Assessment Falls Short
The Peripheral Vascular System Assessment has real limitations. It cannot quantify the degree of stenosis in a specific vessel. It cannot visualize anatomy. It is a screening and monitoring tool, not a definitive diagnostic one. If you detect abnormal findings — diminished pulses, asymmetric ABI, abnormal Doppler waveforms — the next step is referral for imaging, typically duplex ultrasonography or CT angiography, depending on the clinical question. The assessment also depends heavily on the examiner's skill. Two clinicians performing the same assessment on the same patient can arrive at different pulse grades. This isn't a reason to abandon the technique, it's a reason to be honest about its variability and to use objective measures like ABI whenever possible to supplement the physical exam.


