How Permanente Emdr Therapy Actually Works in Practice
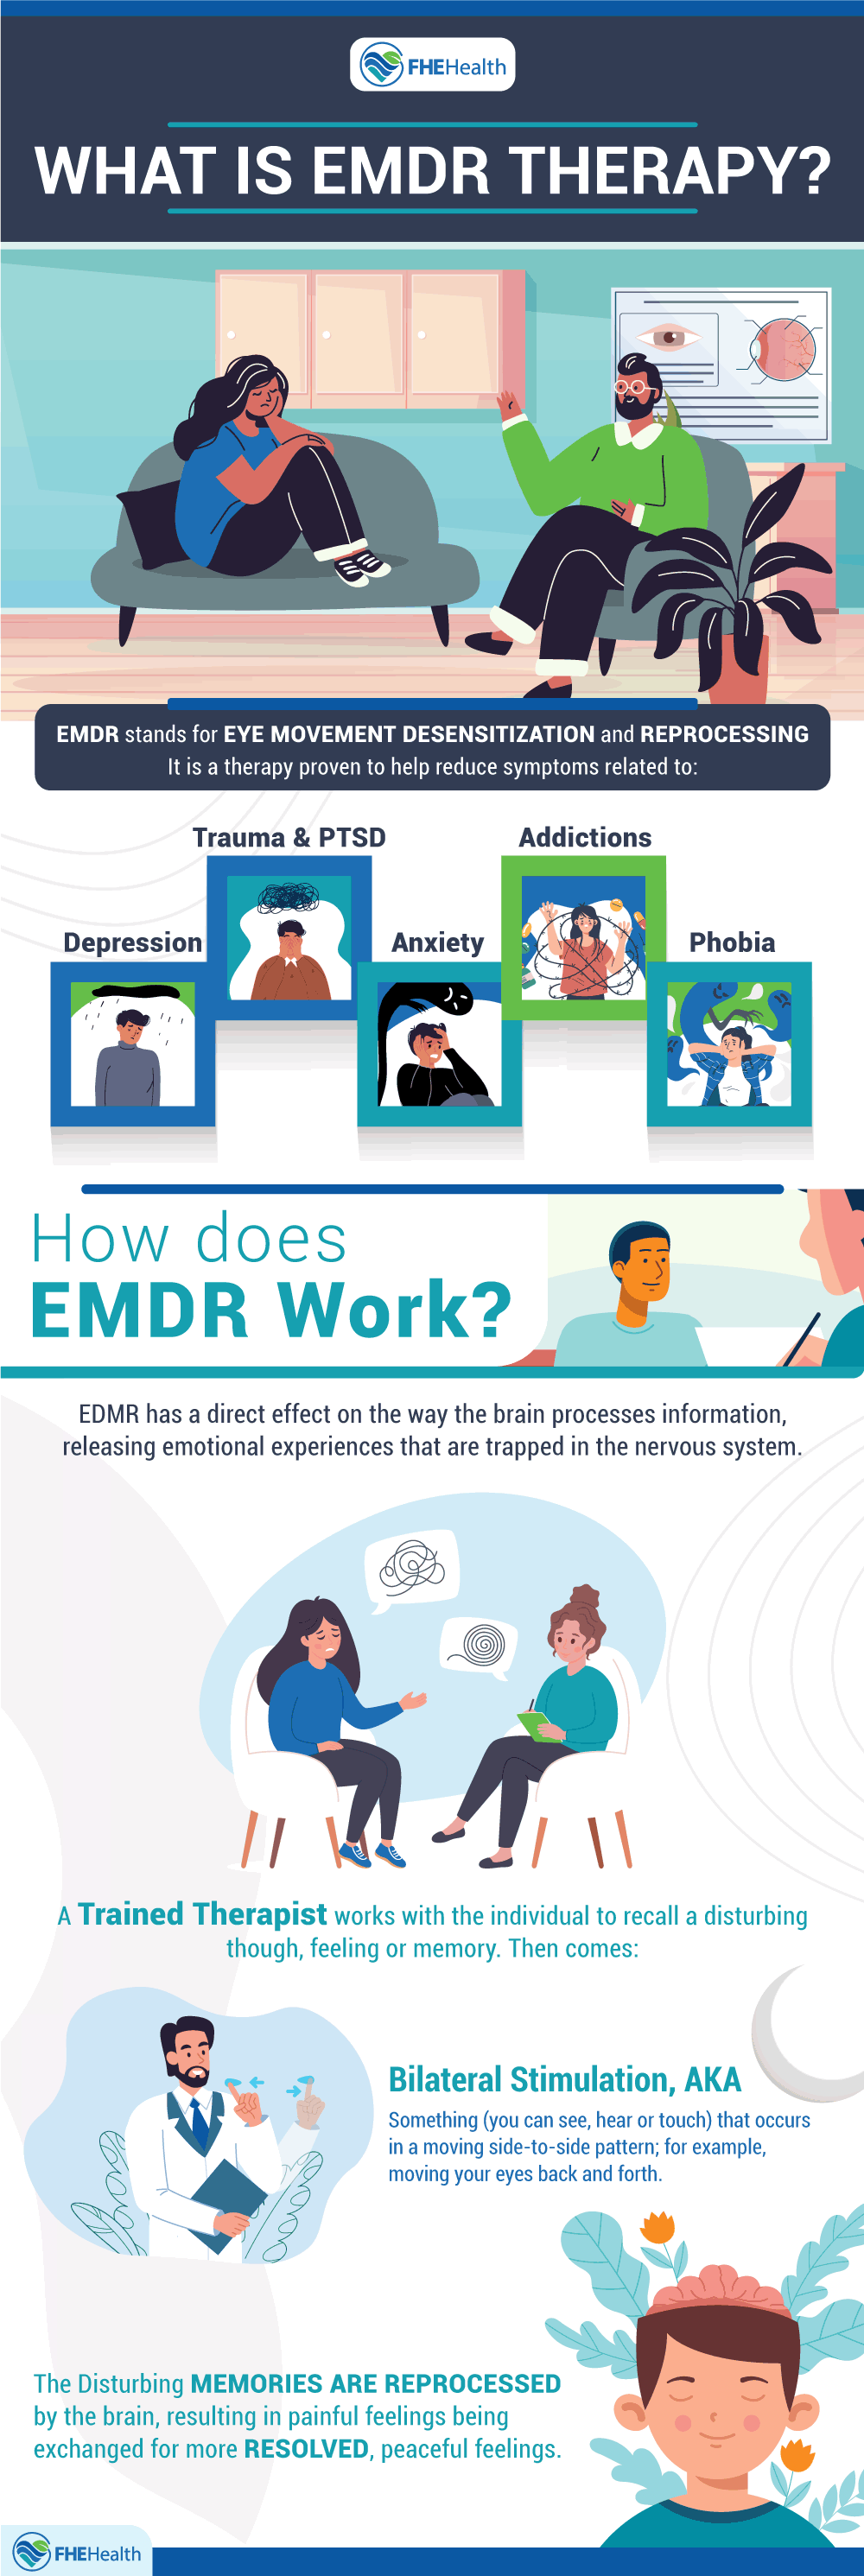
EMDR, or Eye Movement Desensitization and Reprocessing, is a structured therapy that helps people process traumatic memories. The Permanente Emdr Therapy model follows the standard eight-phase protocol established by Francine Shapiro. The most common misunderstanding is that it is just bilateral stimulation with a counselor watching you follow their finger. That is only phase one and part of phase four. The real work happens in the preparation, history-taking, and integration phases, which most clinicians rush through. The eight phases break down like this. Phase one is history and treatment planning, where the therapist identifies target memories and assesses whether you are a good candidate. Phase two is preparation, where you learn coping strategies like the safe place exercise and emotional stability techniques. This phase is critical and usually takes at least two to three sessions. Phase three is assessment, where the therapist activates the memory network by having you identify a negative self-belief, a visual image, and where you feel it in your body. Phase four is desensitization, where bilateral stimulation — typically eye movements, taps, or tones — is applied in sets while you hold the memory in mind. Phase five is installation, where you reinforce a positive self-belief until it feels true. Phase six is body scan, checking for residual tension. Phase seven is closure, making sure you are stabilized before leaving. Phase eight is reevaluation at the start of the next session. What people skip over is that desensitization is not one-size-fits-one. The standard protocol assumes a linear memory trace, but complex trauma does not work that way. With complex PTSD, you are often processing layered memories that trigger each other. You may spend more time in phases two and three than most first-time clinicians realize. Rushing into bilateral stimulation without solid grounding skills is where things go wrong.
A Specific Problem I Encountered
I ran into a case with a client who had severe somatic flashbacks during EMDR sessions at a Permanente Emdr Therapy clinic. Every time we tried to target a memory, they would go into full physiological dysregulation — rapid heart rate, dissociation, inability to stay in the room. Standard grounding wasn't working. What eventually helped was switching to a modified approach: instead of continuous bilateral stimulation, we used stop-and-start tapping. The client would tap their own knees with alternating hands for ten seconds, then pause and check their emotional state on a zero-to-ten scale. We kept the arousal below a four before continuing. This slowed the sessions down considerably, but it prevented the dissociation episodes that were derailing progress. It took about six extra sessions of stabilization before we could even attempt targeted processing. One thing most beginners miss is that EMDR is not primarily about the eye movements. The bilateral stimulation is a catalyst, but the memory processing depends on the adaptive information system, which is the brain's natural ability to reorganize distressing memories. If the client does not have the cognitive and emotional resources to do that reorganization, stimulation alone will not produce results. This is why phase two preparation is non-negotiable. Another pitfall is the assumption that fewer sessions equal better outcomes. With single-incident trauma, eight to twelve sessions is typical. With complex trauma, it can take twenty to thirty or more, and sometimes ongoing monthly maintenance sessions are necessary for years. A less discussed limitation is that EMDR is not effective for everyone. People with certain dissociative disorders, untreated psychosis, or significant frontal lobe impairments may not process memories the way EMDR requires. There is also the issue of overgeneralization, where a client reports that a specific memory has been desensitized but the underlying belief system has not shifted. The positive cognition may feel intellectual but not embodied. This is why the installation phase and body scan matter more than the number of sets you run.
What to Expect Session by Session
In a typical EMDR session, after the initial check-in and reevaluation, the therapist will move through target memories one at a time. Each target gets processed until its disturbance score drops to zero or one. A single set of eye movements might last thirty to sixty seconds. Most clients process one to three targets per hour. Fatigue is real. The brain is doing heavy lifting during these sessions, and it is common to feel drained afterward. Some people experience vivid dreams or emotional surfacing between sessions, which is normal and usually resolves within a few days. If it does not, the therapist needs to adjust the approach. Training requirements matter here. Not everyone who calls themselves an EMDR practitioner has completed a full certification. Look for someone who has finished the EMDRIA-approved training and has ongoing consultation. At Kaiser Permanente and similar health systems, the clinicians vary in their level of EMDR-specific training. Some have done the full protocol and supervised hours. Others may use adapted versions or blend EMDR with other modalities. That is not inherently bad, but it affects the fidelity of the treatment. Ask about your provider's background before starting.
Get the Full Details
The Bottom Line on Permanente Emdr Therapy
EMDR works when applied correctly to appropriate cases. It is not a quick fix, and it is not suitable for every type of psychological distress. The strongest evidence supports its use for PTSD from single-incident trauma. The evidence for complex trauma is more mixed, and the treatment duration tends to be longer. If you are considering EMDR, the most important factors are the therapist's experience level, your readiness, and a realistic expectation that this is a process, not a procedure. There is no shortcut around the preparation phase, and there is no shortcut around the therapist knowing when to slow down.