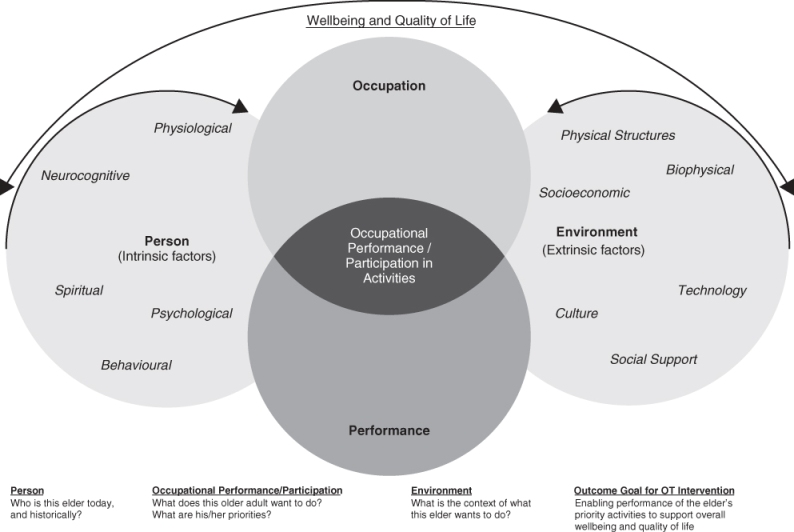
Personal Factors in Occupational Therapy Practice
Most people think occupational therapy is just about adapting tasks for disability. It is bigger than that, and when you ignore the personal factors side of it, your outcomes get messy fast. Personal factors are the baseline characteristics of a person that aren't part of a health condition but still shape how that person functions day to day. Things like age, gender, education level, coping style, habits, interests, and even personality traits. The WHO ICF framework calls them out as real variables, not just demographic checkboxes on an intake form. The trouble is that most therapists don't track these systematically. They note the diagnosis and move on. I found this out the hard way about five years ago when I was working with a client who had suffered a mild stroke and needed retraining for returning to work as a junior accountant. Standard OT approach would have been task modification and pacing strategies. But this client was also a known type-A perfectionist with deeply ingrained work habits shaped over fifteen years. The standard approach flat-out failed because I wasn't accounting for the personal factor of his need for control and precision. He kept abandoning each intervention the moment it didn't feel perfectly structured.Personal Factors Occupational Therapy
The workaround I ended up using was to map his personal factors first, before designing any intervention. I spent two full sessions just doing an informal life history and routine audit. I asked him to describe an ideal workday, then a typical workday, then what happened when things went wrong. That gave me the raw material to build an intervention that aligned with his natural tendencies rather than fighting them. Instead of a generic return-to-work plan, I designed a graduated system with built-in checkpoints and documentation requirements. It satisfied his need for structure while still pushing him toward the flexibility he needed. We cut the expected timeline from twelve weeks down to about seven because he was actually engaged instead of sabotaging the process.
One of the most counter-intuitive things I have learned is that high motivation is not always a good thing in occupational therapy. A client who is extremely motivated can push so hard during sessions that they overshoot their actual capacity, leading to setbacks that delay real progress. I had a client with chronic low back pain who was determined to return to her job as a construction site supervisor. She showed up to every session ready to max out. We had to slow her down deliberately and reframe rest as part of the therapy, not the enemy of it. That took about three weeks of just convincing her that backing off was itself an active treatment choice. Another thing beginners miss is the difference between a personal factor and a health condition. Personality traits like conscientiousness or neuroticism are personal factors. A personality disorder diagnosed under DSM-5 criteria is a health condition. Both influence OT outcomes differently. Conscientiousness helps with home exercise program adherence. A diagnosed anxiety disorder requires a different intervention tier, possibly involving mental health professionals. Mixing those up leads to either over-treating a personality trait or under-treating a clinical condition.How to Actually Assess Personal Factors
There isn't a single standardized instrument that covers all of this well. The MITBI and the COPM give you some data points, but they lean heavily toward function and participation, not the deeper personal factor landscape. What I use is a combination approach. First, a semi-structured interview covering life history, current routines, stressors, and coping patterns. I typically spend 45 minutes on this for new clients. Second, I look at the client's own description of their daily patterns. When did they start problems? What triggers worsening? What helps them reset? This takes about 20 minutes and usually reveals patterns that the clinical interview misses.
I also recommend keeping a simple personal factors log alongside your standard progress notes. One page per client, updated every session. Columns for the date, the factor observed, the influence on treatment, and the adjustment made. It doesn't take more than five minutes per session once you are used to it, but it creates a record that shows you are actually tracking these variables instead of just mentioning them in passing.The biggest bottleneck with personal factors is time. You cannot do a thorough assessment of all relevant personal factors in a single session, especially in a busy outpatient clinic where you might have twenty-minute slots. I found that spreading the initial assessment across the first three sessions works better than trying to cram it into one. You get better data and the client feels less interrogated. Your initial session becomes intake and rapport building. The second and third sessions fill in the personal factor profile. By session four, you are designing the actual intervention plan with enough context to make it stick.
Get the Full Details

Intervention Design Using Personal Factors
When you have a decent personal factors profile, you can move into intervention design with a lot more confidence. The core principle is alignment. Match the intervention to the person's natural tendencies and values rather than fighting them with a one-size-fits-all protocol. A client who values independence will respond differently to the same balance training program than a client who values social connection. Same exercise, different framing, different adherence rate. I use a simple decision matrix when building plans. On one axis, I list the target outcome. On the other, I list the relevant personal factors. Then I draw lines between them and note how each factor supports or blocks progress. It sounds basic but it forces you to be explicit about your reasoning instead of just writing a generic treatment plan that could apply to anyone. Takes about ten minutes per client and dramatically improves the specificity of your interventions.The other common mistake is over-indexing on negative personal factors. Every client has some trait or habit that is working against their goals. Focusing exclusively on those creates a deficit-based approach that doesn't stick. I make sure to identify at least two personal factors that are actually helping. A client with anxiety might also be highly observant and detail-oriented. That detail orientation is useful for fine motor retraining. Pointing it out and building on it changes the entire dynamic of the therapeutic relationship.
Documentation wise, make sure you record which personal factors you considered and how they shaped each decision. Insurance reviewers and other professionals who read your notes need to see that connection. A plan that says "improveADL performance" without explaining why you chose a particular approach for this particular person is weak documentation. Adding two or three sentences about the relevant personal factors strengthens it considerably and usually takes less than a minute to write. In practice, the personal factors approach does not solve everything. It is not a magic framework that guarantees better outcomes. But it is one of the simplest ways to make your occupational therapy work actually fit the person in front of you instead of forcing them to fit your standard protocols. I would suggest starting small. Pick one recent client and spend fifteen minutes mapping their personal factors before your next session. See what you missed and what you already knew. From there, you can expand it to more clients as it becomes a habit rather than an extra step.