How I Actually Code Personal History Of Subdural Hematoma Icd 10 In Real Practice
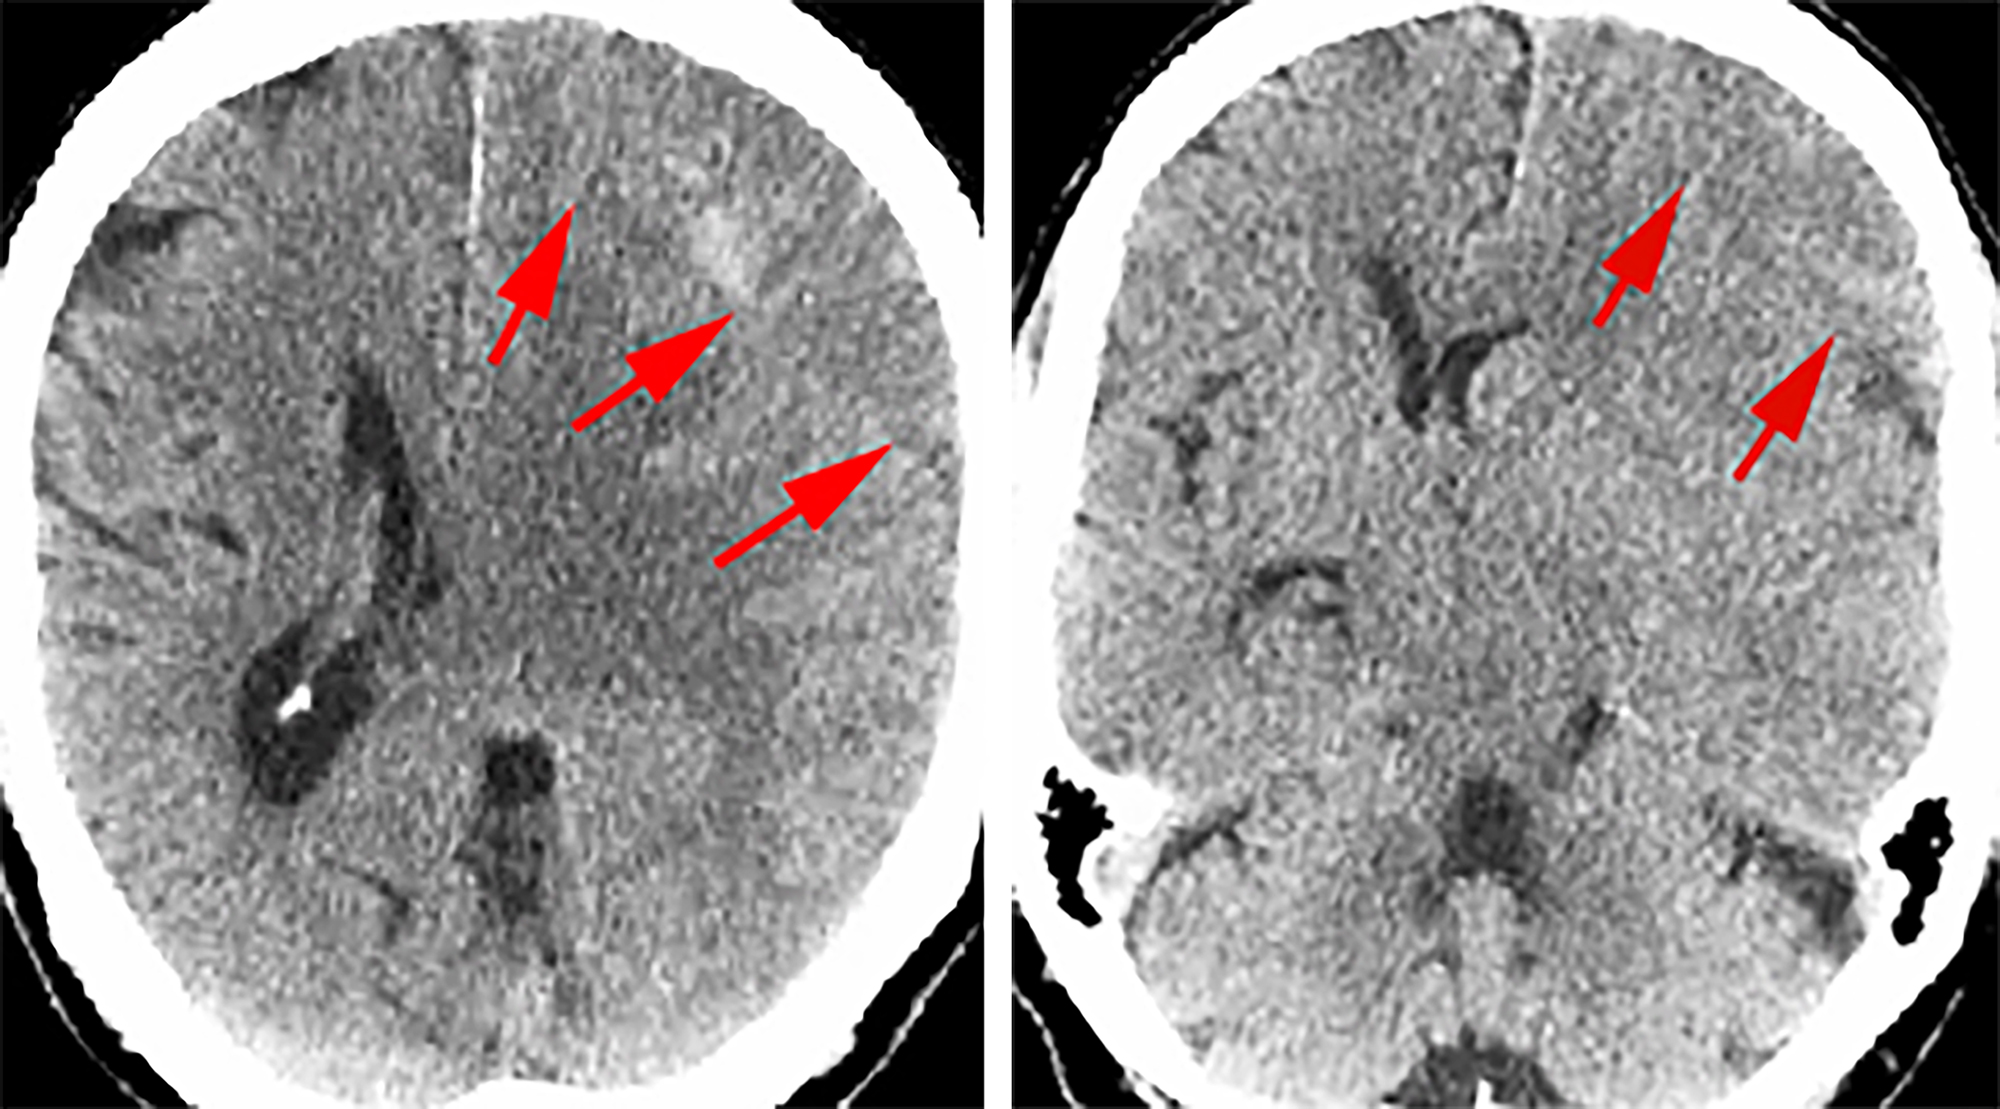
I spent years fighting with payers over this specific code. It seems straightforward on paper but the practical application has enough edge cases to make you question your career choices. Let me walk you through how this works when you're dealing with an actual patient chart instead of a practice exam. The code is Z86.62. It sits under the broader category of personal history of certain other diseases, specifically the cardiovascular section. I use this code when a patient had a subdural hematoma in the past, it resolved completely, and they have no residual effects. That last part matters more than most coders realize. A subdural hematoma is bleeding between the dura mater and the brain surface. It usually comes from trauma. The tears in the bridging veins are what cause it. Elderly patients are at higher risk because their brains atrophy and the veins stretch more easily. A minor fall that wouldn't bother a younger person can cause a significant bleed in someone older. This clinical background is useful because it tells you why the history matters even when the acute episode is long over.
When I encounter a chart where the patient is being seen for a follow-up on hypertension and the only mention of a prior subdural hematoma is in a discharge summary from two years ago, that's when Z86.62 comes into play. The reason for the current encounter is the hypertension visit. The history code is secondary. You list Z86.62 after the primary diagnosis code. That sequencing is non-negotiable. Put it first and you're telling the payer the visit was for the history itself, which is almost never correct. Here's where it gets messy. I had a case recently where a patient came in with ongoing right-sided weakness. The chart said they'd had a subdural hematoma three years ago. My first instinct was to pull up Z86.62. Then I caught myself. Residual hemiplegia after a cerebrovascular event has its own coding pathway. The correct approach here was to code the residual effect, not just the history. The subdural hematoma was the cause, but the current problem is the deficit. Using Z86.62 in that scenario would have been wrong and would have triggered a denaturalization review faster than you can imagine. The ICD-10-CM official guidelines make this distinction clear. If residual effects are present, you code the residual condition. The history code is only for when everything resolved and there are no lingering symptoms. This catches people out constantly. I see it in roughly one out of every four charts I review that mention a prior hematoma.
Another practical issue is the overlap with active disease codes. An acute subdural hematoma is I62.0. A traumatic subdural hematoma is coded under S06.5-. These are completely different from Z86.62. The confusion happens because some clinicians write "history of subdural hematoma" in the problem list even when the patient is currently being treated for one. If the bleeding is active, you don't use Z86.62. You use the appropriate acute code and document the acuity clearly. Using a history code for an active condition is a compliance red flag. I've had audit requests started by exactly this kind of error. There's also the question of whether a resolved subdural hematoma without surgical intervention can use this code. Yes it can. The code doesn't specify whether there was surgery or not. It just requires that the patient had the condition in the past and doesn't have it now. A conservatively managed hematoma that resolved on its own still qualifies. The clinical documentation just needs to support that resolution. If the physician documented "complete resolution" or "fully recovered," you're good. If the note says "chronic subdural hematoma" without any language about resolution, you can't assume it's a history code. You need to clarify with the provider first. One thing most coding guides don't emphasize enough is that Z86.62 is an F/U code in a practical sense. It describes past medical history that affects current care decisions. If the patient is on anticoagulants because of the prior hematoma, or if the surgeon is avoiding a certain procedure because of it, that history is clinically relevant. But it still goes on the secondary position. The relevance doesn't change the sequencing rules. I've seen junior coders put it first just because the chart mentions the anticoagulation decision prominently. That's incorrect and it will come back to haunt you during a claim review.
Get the Full Details
The workaround I use when the documentation is ambiguous is simple but time-consuming. I flag the chart and send a physician query asking specifically whether the prior subdural hematoma is considered resolved with no residual effects. If they confirm, Z86.62 is appropriate. If they say there are ongoing issues, I code accordingly. This adds maybe ten minutes to the coding process but it prevents denials that take weeks to resolve. The denial rate on this code is low when the documentation is clear but it spikes dramatically when the coder has to guess. I also want to mention the interaction with ICD-10 code Z86.7-. This is the personal history of cardiovascular disease category. Someone might think Z86.62 falls under this umbrella and try to code it differently. It doesn't. Z86.62 is the specific code for this condition. Specificity always wins in ICD-10 coding. Using a general category code when a specific one exists is a common error that audits catch immediately. The biggest limitation of relying on Z86.62 as a status code is that it carries no clinical weight by itself. It won't drive treatment decisions. It's purely informational for the record. Some payers still treat it as clinically significant because it appears on the claim, which means you'll occasionally get requests for additional documentation just to justify the code's presence. I've had one payer ask for the original discharge summary from 2018 for a visit that had nothing to do with the hematoma. That's not a coding problem. That's a payer problem. You document correctly and move on.
If you're working in a setting where subdural hematomas are common, like a neurology or neurosurgery practice, having a quick reference for the distinction between acute I62.0, traumatic S06.5-, and historical Z86.62 is worth keeping at your desk. The difference is clinically obvious but the coding impact is significant and the financial consequences of mixing them up are real.