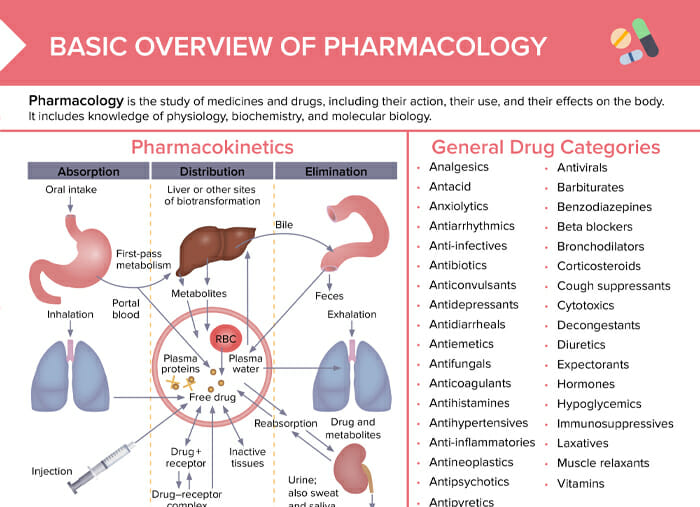
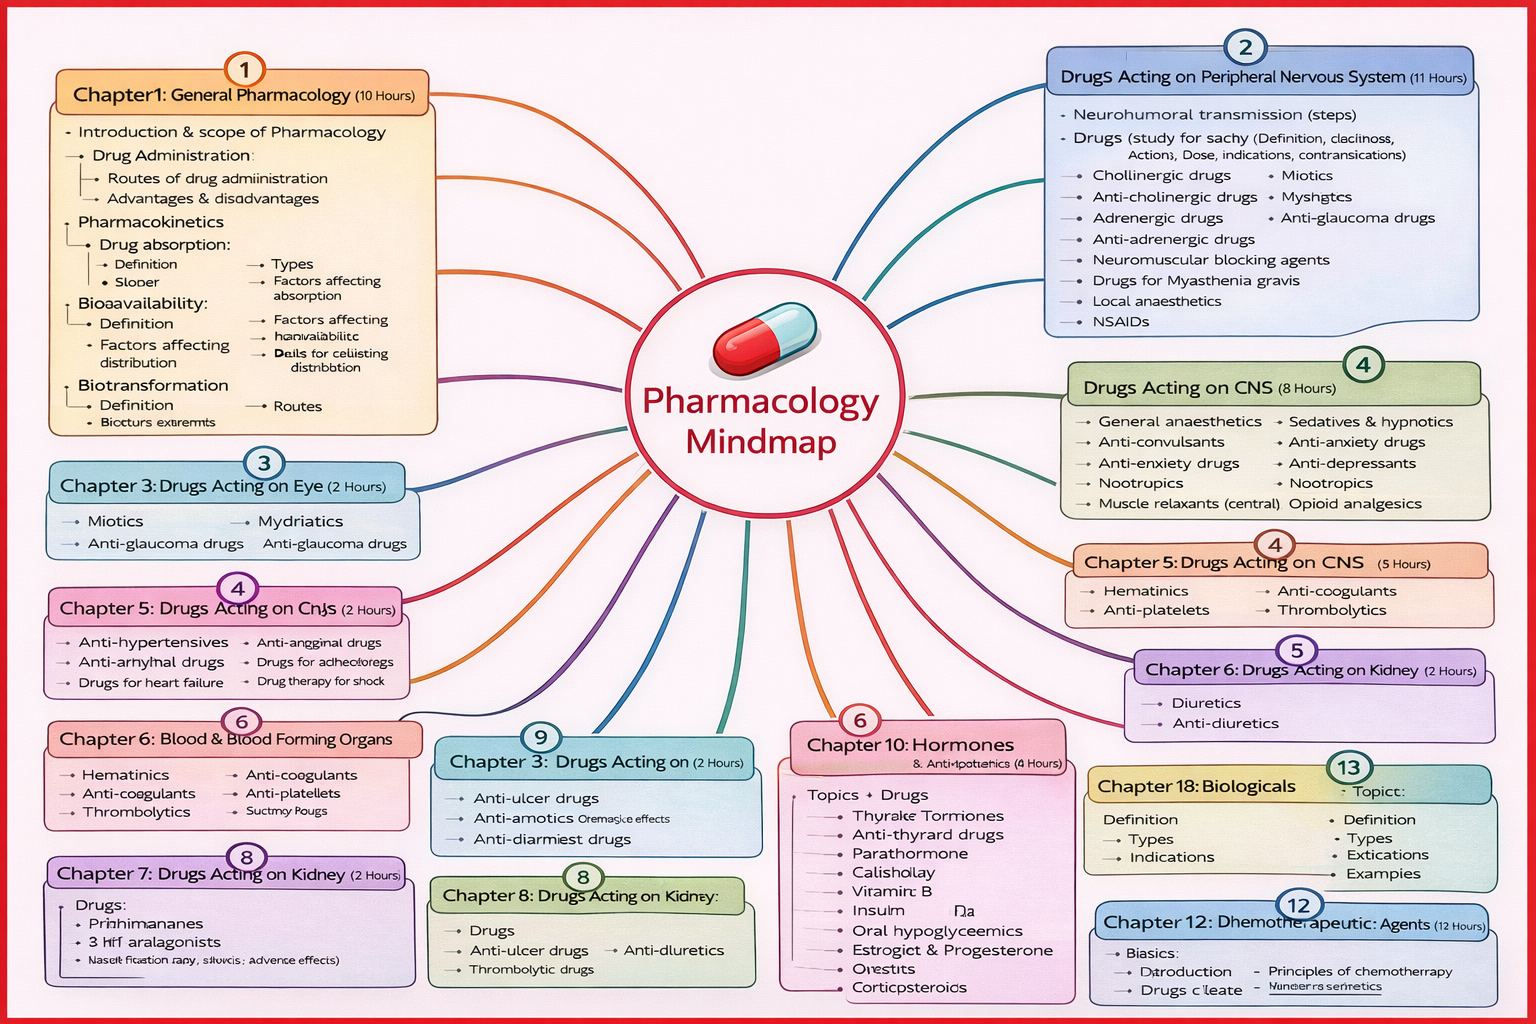
Building Your Pharmacology Ideas Framework
Most people approach pharmacology study the wrong way. They try to memorize drug names and mechanisms in isolation, which is an inefficient method that breaks down under pressure. What actually works is organizing Pharmacology Ideas around clinical scenarios and mechanistic relationships before you ever touch a flashcard deck. I spent two years doing it the hard way. I was in med school and my pharmacology grades were mediocre because I treated it like a vocabulary exercise. Then a senior resident showed me how pharmacologists at research institutions actually organize their thinking. It changed everything for me.
Practical Pharmacology Ideas for Real Study Sessions
The core concept is simple but most students skip it. You build a decision tree for each drug class. Start with the receptor or enzyme, work backward to the disease state it treats, then forward to the side effects and contraindications. Do this for every major class before you dive into individual drugs. Here is what that looks like in practice. Take beta-blockers. Instead of memorizing metoprolol, atenolol, and propranolol separately, you map them on a single chart showing selectivity profiles, half-lives, and lipid solubility. The differences between these three drugs become obvious once you see them ranked against each other rather than studied in isolation. I ran into a specific problem during my third year rotation. A patient on warfarin came in with a new prescription for amiodarone. The interaction was obvious on paper, but when I actually tried to explain the mechanism to the attending, I fumbled. I knew warfarin was a blood thinner and amiodarone was an antiarrhythmic, but I could not articulate why they interacted at the metabolic level.
My workaround was straightforward. I built a CYP450 interaction chart for every drug class I encountered that rotation. Fluconazole, metronidazole, cimetidine — these are all CYP inhibitors that show up constantly in clinical practice. I stopped treating pharmacology as a memorization task and started treating it as a systems problem. That chart took me about forty minutes to build but saved me hours of last-minute studying over the next three months.
Get the Full Details

Advanced Mechanistic Grouping
Beginners group drugs by their therapeutic use. Experts group them by their molecular targets. This distinction matters more than people realize. When you understand that losartan and valsartan share the same AT1 receptor antagonism mechanism, you can predict their side effect profiles without memorizing each drug individually. They both cause hyperkalemia and renal dysfunction through the same pathway. Another counter-intuitive point: generic drug names tell you more than you think. The suffix of a generic name encodes the drug class. Drugs ending in –pril are ACE inhibitors. Those ending in –olol are beta-blockers. This is not a coincidence and it is not arbitrary. The naming system exists precisely so clinicians can group drugs mechanistically. If you are not using the nomenclature to organize your study material, you are missing a built-in classification system. The downside of this approach is that it requires upfront investment. Building comprehensive mechanism maps takes time, usually three to four hours per drug class if you are doing it thoroughly. Some students skip this step because they want immediate results from their study sessions. The short-term gain becomes a long-term liability. You will spend more time relearning individual drugs later than you would have saved by building the framework upfront.
For students who need a faster entry point, there is an alternative. Flashcard applications with spaced repetition algorithms do work well for basic drug information retention. Anki decks covering major drug classes can get you through the foundational material in roughly six to eight weeks of consistent daily use. The drawback is that spaced repetition alone does not teach you to think like a pharmacologist. It teaches you to recognize facts. Clinical reasoning requires something else entirely. I recommend combining both approaches. Use the mechanism mapping method for conceptual understanding and spaced repetition for factual recall. The combination covers both the why and the what, which is what exams and clinical practice actually test.
Common Pitfalls in Pharmacology Study
The most common mistake I see is studying drugs alphabetically within a class. There is no logical reason to learn acebutolol before metoprolol. Alphabetical ordering has nothing to do with clinical relevance or mechanistic similarity. Start with the prototype drug in each class, learn its mechanism thoroughly, then branch out to the variants. This reduces cognitive load because your brain can anchor new information to existing mental models. Another mistake is neglecting pharmacokinetics. Many students treat absorption, distribution, metabolism, and excretion as separate topics. In practice, pharmacokinetic principles determine almost every dosing decision you will make clinically. A drug with a long half-life like amiodarone behaves very differently from one with a short half-life like heparin. Understanding the kinetics explains why amiodarone requires a loading dose and why heparin needs continuous infusion. The pharmacology landscape has changed significantly in recent years. New drug classes like GLP-1 agonists and SGLT2 inhibitors have reshaped treatment guidelines for diabetes and heart failure. Any study framework you build needs to account for this. Outdated material will mislead you more than no material at all. Always cross-reference your resources against current clinical guidelines published within the last two years.

If you are preparing for board exams, focus your effort on high-yield drug classes: cardiovascular agents, antibiotics, CNS drugs, and endocrine medications. These four categories typically represent over sixty percent of pharmacology questions on standardized exams. Spend proportionally less time on niche specialties unless your exam specifically covers them. The method I described above is not perfect. It assumes you have access to reliable reference material and enough time to build the frameworks from scratch. For students with extremely tight schedules, the comprehensive mapping approach may not be feasible. In those cases, prioritize prototype drugs and high-yield interactions, then fill in gaps as needed. Perfection in organization is not required for competence. Just getting started is what matters.