What This Thing Actually Looks Like When You're 0300 and Confused
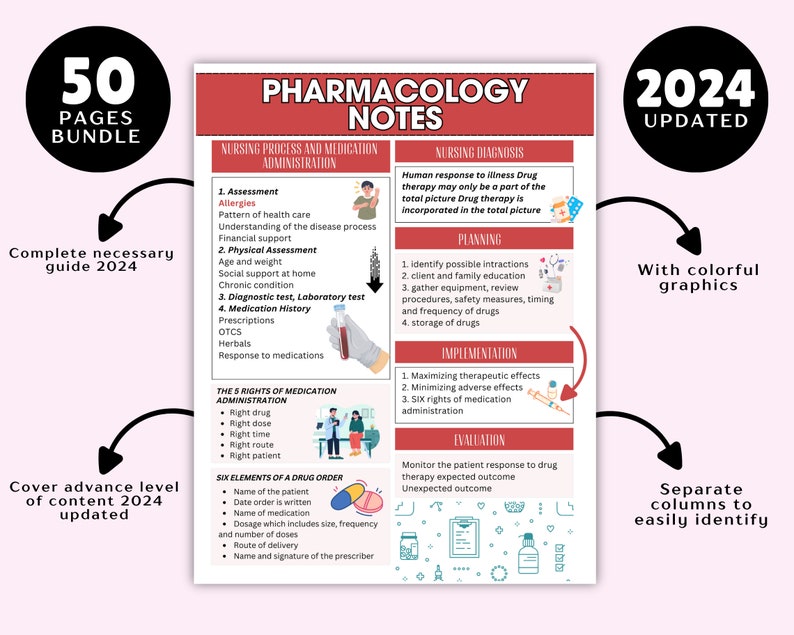
You will get assigned a new patient on a med pass and realize you do not actually know what drug you are about to hang. That is when you wish you had a Pharmacology Study Guide For Nurses New Hire sitting somewhere you can access without scrolling through five different tabs. I spent three weeks on a med-surg floor before I figured out the most useful version of this was not some polished textbook PDF but a set of flashcards I built myself and a one-page sheet I kept folded in my scrub pocket. Here is how I would build something that actually works during orientation. Start by picking the drugs you see every day on your unit. If you are on a telemetry floor, that is heparin, warfarin, amiodarone, metoprolol, losartan, furosemide, and morphine. If you are on ortho, it is tramadol, celecoxib, enoxaparin, and gabapentin. Do not study every drug in the hospital formulary. You will drown in information that will not show up for six months. Focus on the top twenty to thirty medications your unit runs through in a single shift. For each drug, write down five things. The trade name and generic name. The class and what receptor or enzyme it hits. The indication your unit actually uses it for. The dose range you are allowed to give and the parameters you must check before administering. The two or three adverse effects or interactions that matter on your floor.
I learned that last part the hard way. Second week of orientation, I almost pushed a dose of IV metoprolol without checking a blood pressure first. The MAR showed the order but did not flag the hold parameter. The pre-printed study sheet I had made clearly stated to hold for a systolic under one hundred or a heart rate below sixty. That small habit of writing parameters next to the drug name saved me from a phone call I did not want to get at the time. I still use that same pocket sheet format three years later.
The Method Most People Skip
Reading a textbook chapter on pharmacokinetics will not help you remember the conversion factor for vancomycin dosing during a code. Active recall works better. Close the book and recite the drug info out loud. If you cannot say it without looking, you do not know it yet. That sounds obvious until you are trying to study during a fifteen minute break between admissions. Spaced repetition is what keeps these drugs from leaking out of your head. The first review should happen the same day you learn the medication. The second review two days later. The third review a week later. If you get it right, push the next review out further. If you get it wrong, go back to the two day mark. Anki handles this automatically if you are willing to spend an hour importing or building your deck. That hour pays off within a week. Most new hires try to memorize everything at once. They binge forty drugs before their first shift. You will forget seventy percent of it within forty eight hours. Spaced repetition keeps the retention curve from crashing. I saw this happen to my own study habits and adjusted after the first two weeks on the unit. Instead of one long session, I broke it into three ten minute sessions across the week. The results were noticeably better.
Get the Full Details

What Most Guides Get Wrong
A lot of study guides list drug classes in alphabetical order. That feels organized but it is useless when you need to differentiate two drugs in the same class. Here is a more practical grouping method. Organize by condition, not by class name. Put all the heart failure drugs together. Digoxin, lisinopril, carvedilol, furosemide, spironolactone, hydralazine, isosorbide dinitrate. Study how they interact with each other in the same patient. Study which one you monitor with a potassium level and which one you monitor with a creatinine level. That context sticks better than isolated entries. Another common mistake. The guide includes rare side effects that no one on your unit will ever see. Skip them. Focus on the side effects that show up in real practice. With IV antibiotics, watch for infusion reactions and nephrotoxicity. With opioids, watch for respiratory depression and constipation. With anticoagulants, watch for bleeding. You do not need a detailed list of adverse events pulled from the package insert. You need the ones that will trigger a page to the rapid response team. I ran into a specific edge case once with phenytoin. The study guide I had listed the therapeutic range as ten to twenty micrograms per milliliter. It did not mention that the free phenytoin level changes with albumin. A patient came in with a low albumin and a total phenytoin level of twelve, which looks normal on paper. The drug was actually therapeutic at the free level, but the math did not add up on the surface. I used the Sheiner-Tozer equation to adjust and caught that the free level was elevated. The guide I was using did not cover that at all. That is the kind of thing you will not find in a standard new hire packet. It took me a while to find a reliable reference for it, but the workaround was straightforward once I knew the equation existed.
How to Build Your Own Quick Reference
Get a small notebook or use a notes app. Create one entry per high yield medication. Use this structure. Keep the entries short. Four to six lines per drug is enough. You are not writing a chapter. You are writing something you can read in thirty seconds during a med pass. Another thing most people do not do. Make a separate section for high alert medications. Heparin, insulin, morphine, potassium chloride, sodium bicarbonate, chemotherapy agents. These get their own space because the stakes are different. Write down the double check policy for your unit. Write down the infusion rates you are allowed to run. Write down the pump programming steps. I keep that section on the first page of my pocket reference because I pull it up more often than any other part.
Where to Find Reliable Content
The Lexicomp and Micromedex apps are the standard references. Your hospital likely already pays for access. Use those instead of random websites. The drug interaction checker there is updated regularly and reflects your formulary. The dosing tables include renal and hepatic adjustments, which matters more than people realize. For a free option, the NIH Daily Med database has the full prescribing information. It is not formatted for quick reading but it is accurate. The CDC and FDA websites have alert notices that are worth checking before you start using a new medication on a regular basis. Drug recalls do not stop during orientation. There is no single perfect PDF you can download and expect to carry you through your entire first year. A static guide becomes outdated as your hospital changes formularies, adds new orders, or updates protocols. The best study material is the one you maintain yourself. Add drugs as you encounter them. Remove drugs your unit rarely uses. The process of building the guide is itself the study.

What Fails and What to Do Instead
Memorization without context is the biggest failure point. You can memorize that enoxaparin is a low molecular weight heparin and that the dose is one milligram per kilogram subcutaneously twice daily. That information means nothing if you do not understand why you hold it before a procedure, how it interacts with epidural catheters, or what the reversal agent is. Every drug entry should include the clinical reasoning, not just the facts. Another failure mode is studying in isolation from the electronic health record. You will see the drug listed in the system differently than you studied it. The abbreviation, the concentration on the label, the documented allergy alerts. Spend time in the EHR med administration module during orientation. Match your study entries to what you actually see on screen. The gap between study material and clinical interface is where mistakes hide. Some units will give you a pre made pharmacology packet. Use it as a starting point, not the final product. I found the orientation packet helpful for the first week but it covered too many drugs I would never use and missed some unit specific protocols. I revised it heavily and ended up with something much smaller and much more useful.
There is also a limit to how much pharmacology you can absorb before you have seen the clinical outcomes. Reading about hypoglycemia from insulin is different from watching a patient become diaphoretic and confused because their blood glucose dropped to fifty. The clinical correlation reinforces the study material. Pay attention during med passes. Watch the patient. The experience will make the pharmacology stick faster than any amount of passive reading.
A Practical Routine
During your first two weeks, spend twenty minutes each morning before your shift reviewing two to three drugs. Not twenty drugs. Two or three. Write out the key points from memory before checking your reference. Do this for the drugs you expect to see that shift. On your break, if you have one, quiz yourself on those same drugs without looking. The active recall during the break locks it in before you start your next task. After each shift, write down one or two drugs you encountered that you felt unsure about. Add them to your flashcard deck or your pocket sheet the next day. This targeted approach keeps your studying focused on gaps instead of reviewing stuff you already know. It takes about fifteen minutes per day. The cumulative effect over four weeks is substantial. You will make mistakes. I made plenty during my first few months. The goal is not perfection. The goal is building a working knowledge base that grows with each shift and shrinks the gap between what you studied and what you actually administered. A good Pharmacology Study Guide For Nurses New Hire is not a document you finish. It is a working tool you maintain.