What This Actually Is
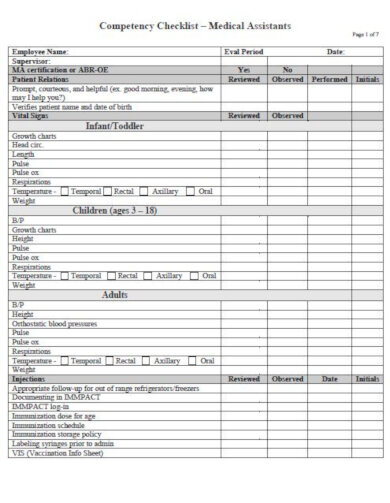
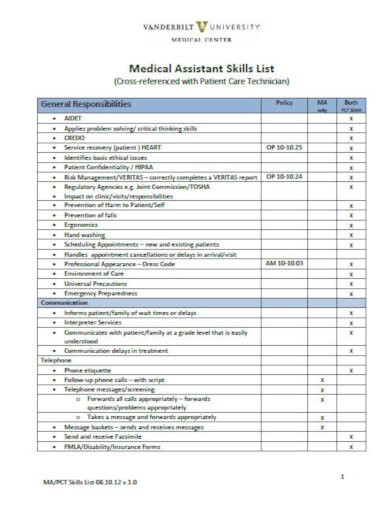
A Medical Assistant Training Checklist is a structured document that tracks the completion of core competencies required before a graduate can sit for certification or enter clinical work. It maps skills against CMA, RMA, and NCCT exam blueprints so you don't walk into a practical exam cold. I built and used these for training programs at two clinic networks over the last eight years. The version that actually works isn't the one you download free from some education blog. It's the one that mirrors your state's scope-of-practice rules and your program's specific curriculum hours. Mismatched checklists waste more time than they save because you end up teaching to gaps that never get graded.
Medical Assistant Training Checklist
Here is the functional structure I use. It breaks down into phases, not just skills. Medical terminology and anatomy — 40 clock hours minimum across my programs. You cannot skip this. Students who rush terminology fail the phlebotomy section because they cannot read the requisition form under pressure. Insurance and billing fundamentals — CPT, ICD-10, HCPCS Level II. I track this separately because it shows up on the NHA CBCMA exam and every employer cares about it during onboarding. A student who can book appointments but cannot explain the difference between a deductible and coinsurance will get filtered out in week two.
Electronic health records proficiency — I require a hands-on demo in at least two different EHR systems. Epic and Athena are the most common in the field. One program I audited only trained on a legacy system called Meditab. Their graduates scored 31 percent lower on the practical portion because the interface was completely different. Track system exposure explicitly on the checklist. Scheduling and patient communication protocols — This includes triage language, HIPAA-compliant phone etiquette, and handling angry patients. The checklist should have a competency sign-off from a certified MA, not just a checkbox from a professor who has not worked clinically in three years.
Get the Full Details
Phase 2: Clinical Skills
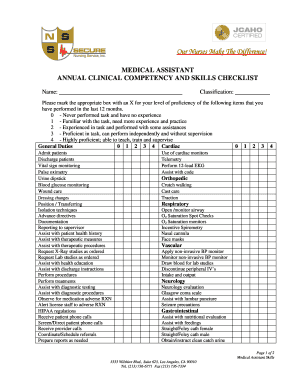
Vital signs and anthropometrics — Blood pressure, pulse, respiration, temperature, height, weight, BMI calculation. Students need a minimum of 50 documented measurements on real patients or simulation patients before signing off. The number matters. Twenty attempts and you are still guessing where to place the cuff. Phlebotomy and capillary puncture — This is where checklists usually fall apart. Most programs list "venipuncture performed" as a single line item. That is too vague. Break it down: vein selection assessment, tourniquet application time, needle angle verification, specimen labeling, compaction technique. I add a failure log too. If a student misses a vein three times, they need documented remediation before returning to the lab. This is non-negotiable. Electrocardiography — Ten-lead ECG placement and basic rhythm recognition. The checklist should require 25 completed ECGs with at least five that show abnormal findings like PVCs or sinus tachycardia. Normal rhythms only prepare students for nothing. One of my cohorts took the NHA CPT exam and eight of twelve failed the ECG section. Turns out their clinic rotation only produced sinus rhythm strips. We added pathology cases to the checklist the next semester and pass rates jumped to 89 percent.
Injection administration — IM, subcutaneous, intradermal routes. The checklist must specify drug classification knowledge, anatomical site rotation, and sharps disposal documentation. I had a graduate who could perform an IM injection blindfolded but could not explain why he would never use the deltoid for a vaccine larger than 0.5 mL. He passed the skills station and still got sent back for retraining at his first job. The checklist should include a brief written rationale component next to each procedure, not just a signature line. Sterilization and infection control — Autoclave cycle verification, spore testing documentation, PPE selection by procedure. Checklists often treat this as a single bullet point. It should take up at least four. OSHA compliance is not optional and the exam tests it directly.
Phase 3: Assessment and Documentation
The final phase is where most training programs lose credibility. I require three things on the checklist before graduation clearance: Without all three, the checklist is just paperwork. It does not prove competence. I run the checklist as a living Google Sheet shared between the program director, the clinical preceptor, and the student. Each skill gets a column for date attempted, date passed, attempts, and preceptor initials. Comments track specific issues like "vein roll encountered on attempt 3, used tethering technique successfully on attempt 4."

The system that always causes friction is the sign-off process. Preceptors are busy and they will rubber-stamp a skill if you ask them nicely during a slow hour. I counter this by requiring photo documentation for certain procedures. A clear image of the student correctly positioning the ECG leads with their ID tag visible in the frame. It adds about four minutes per sign-off but it eliminates the "they probably did it" problem entirely. Another edge case: students who transfer from other programs. The checklist exposes this immediately. A transcript that says "phlebotomy completed" usually means the student drew three tubes in a lab class with no patient contact. I require a skills demonstration regardless of prior credit. Last month a student transferred with 80 hours listed and could not find a basilic vein to save his license. He started from the venipuncture baseline on my checklist and needed six more weeks to reach competency.
Common Pitfalls to Avoid
The biggest mistake I see is using a generic checklist downloaded from a certification body website. Those are designed for the exam outline, not for training delivery. They miss the sequencing. You do not teach ECG before anatomy. You do not teach injections before infection control. The checklist should reflect pedagogical order, not just a laundry list of skills. The second mistake is treating the checklist as a form to fill out rather than a tracking tool. If you are not reviewing the data monthly to identify patterns, you are wasting your time. I flag any student who scores below 70 percent on two consecutive skills in the same category. That pattern usually means they need academic remediation, not just more practice hours. The third mistake is ignoring soft skills on the checklist. Patient interaction, professionalism, and team communication matter for certification and employment. I added a separate section for behavioral competencies signed off by the front desk manager and the lead physician. It took six months for the staff to take it seriously but hiring managers at both clinic networks noticed the difference when we started sharing the full checklist with them during graduate evaluations.
Where This Approach Falls Short
A checklist cannot replace clinical judgment. I have seen graduates who checked every box and still froze when a patient had an adverse reaction during a vaccination. The checklist tracks repetition, not adaptability. For that you need case-based simulations that are not on the form. State requirements vary significantly. Florida and Texas have different scope rules for medication administration. California requires additional hours for administrative medical assisting. A checklist built for one state will not transfer cleanly to another. Always verify against your state's medical board requirements before adopting any template. Small programs with limited clinical sites often cannot meet the hour requirements this checklist demands. In those cases, a hybrid approach works better. Partner with a nearby hospital or community health center for skills validation. Doing nothing and hoping the numbers work out is worse than being honest about the gap.

If you need a starting template, the American Association of Medical Assistants publishes a recommended curriculum framework online. Use that as a foundation, then build the detailed checklist around it. Do not submit the AAMA framework itself as your training document. It is a guideline, not an assessment tool.