Conversions That Actually Matter on the Floor
Most people think pharmacy math is about memorizing formulas. It's not. It's about knowing which conversion to reach for when a doctor writes 0.5 mg and the medication comes in 250 mcg tablets. You don't need a formula sheet for that. You need to know that milligram and microgram are six orders of magnitude apart, and you've done this calculation enough times that it's just... done. I still see techs pull out a conversion chart every single shift. Don't. The ones you need are the ones where a mistake puts a patient at half-dose or double-dose. Everything else you can look up in thirty seconds.
Essential Pharmacy Technician Math Formulas
Here's what I actually use, in order of frequency. Dose calculation: Desired dose divided by what's on hand, multiplied by the vehicle. D / H × V. If you have 500 mg tablets and need 250 mg, that's 250 / 500 × 1 tablet = 0.5 tablet. Standard stuff. The trap here is when the on-hand amount and desired dose are in different units. Convert first. Always convert first. I watched a tech once calculate 10 / 500 without noticing one was in grams and the other in milligrams. Patient got 1/50th the dose. She was shaking for the rest of the shift. Quantity to dispense: Days supply times daily dose divided by strength per unit. This is the one that trips people up on insurance claims because the numbers have to line up exactly. Payer systems reject claims when your quantity doesn't match their days supply calculation to the decimal. Know your payer's rounding rules. Some round up, some truncate, some require exact ratios. Keep a note of each major payer's policy somewhere. Takes two minutes to write down, saves you three hours of resubmissions per week.
Molarity and dilution: C1 times V1 equals C2 times V2. The classic. C1V1 = C2V2. It works for anything where you're concentrating or diluting a solution, including compounding IVs and reconstituting powders. The version that catches people is when they mix two solutions of different concentrations and need the final strength. That's not a simple C1V1 = C2V2 problem. That's a mass balance equation. I spent six months before someone explained that distinction clearly. My pre-compounding checks were wrong on about 15% of dual-solution requests because I was forcing the simple formula into a situation it didn't fit. Body surface area: Most common is the Mosteller formula. Square root of height in centimeters times weight in kilograms, divided by 3600. BSA = square root of (H × W / 3600). Chemotherapy dosing runs through this number. The chart method is easier but less precise. I use the formula because my state requires documented calculations for chemo orders, and chart interpolation doesn't satisfy the audit trail. Infusion rate: Volume in milliliters divided by time in minutes, multiplied by the drop factor. Or for electronic pumps, just milliliters per hour. mL/hr = total volume / hours. The drop factor method is for manual IVs. You'll rarely do those anymore unless you're in a rural facility or a surgical suite. Still, the exam tests it. Know both.
Get the Full Details
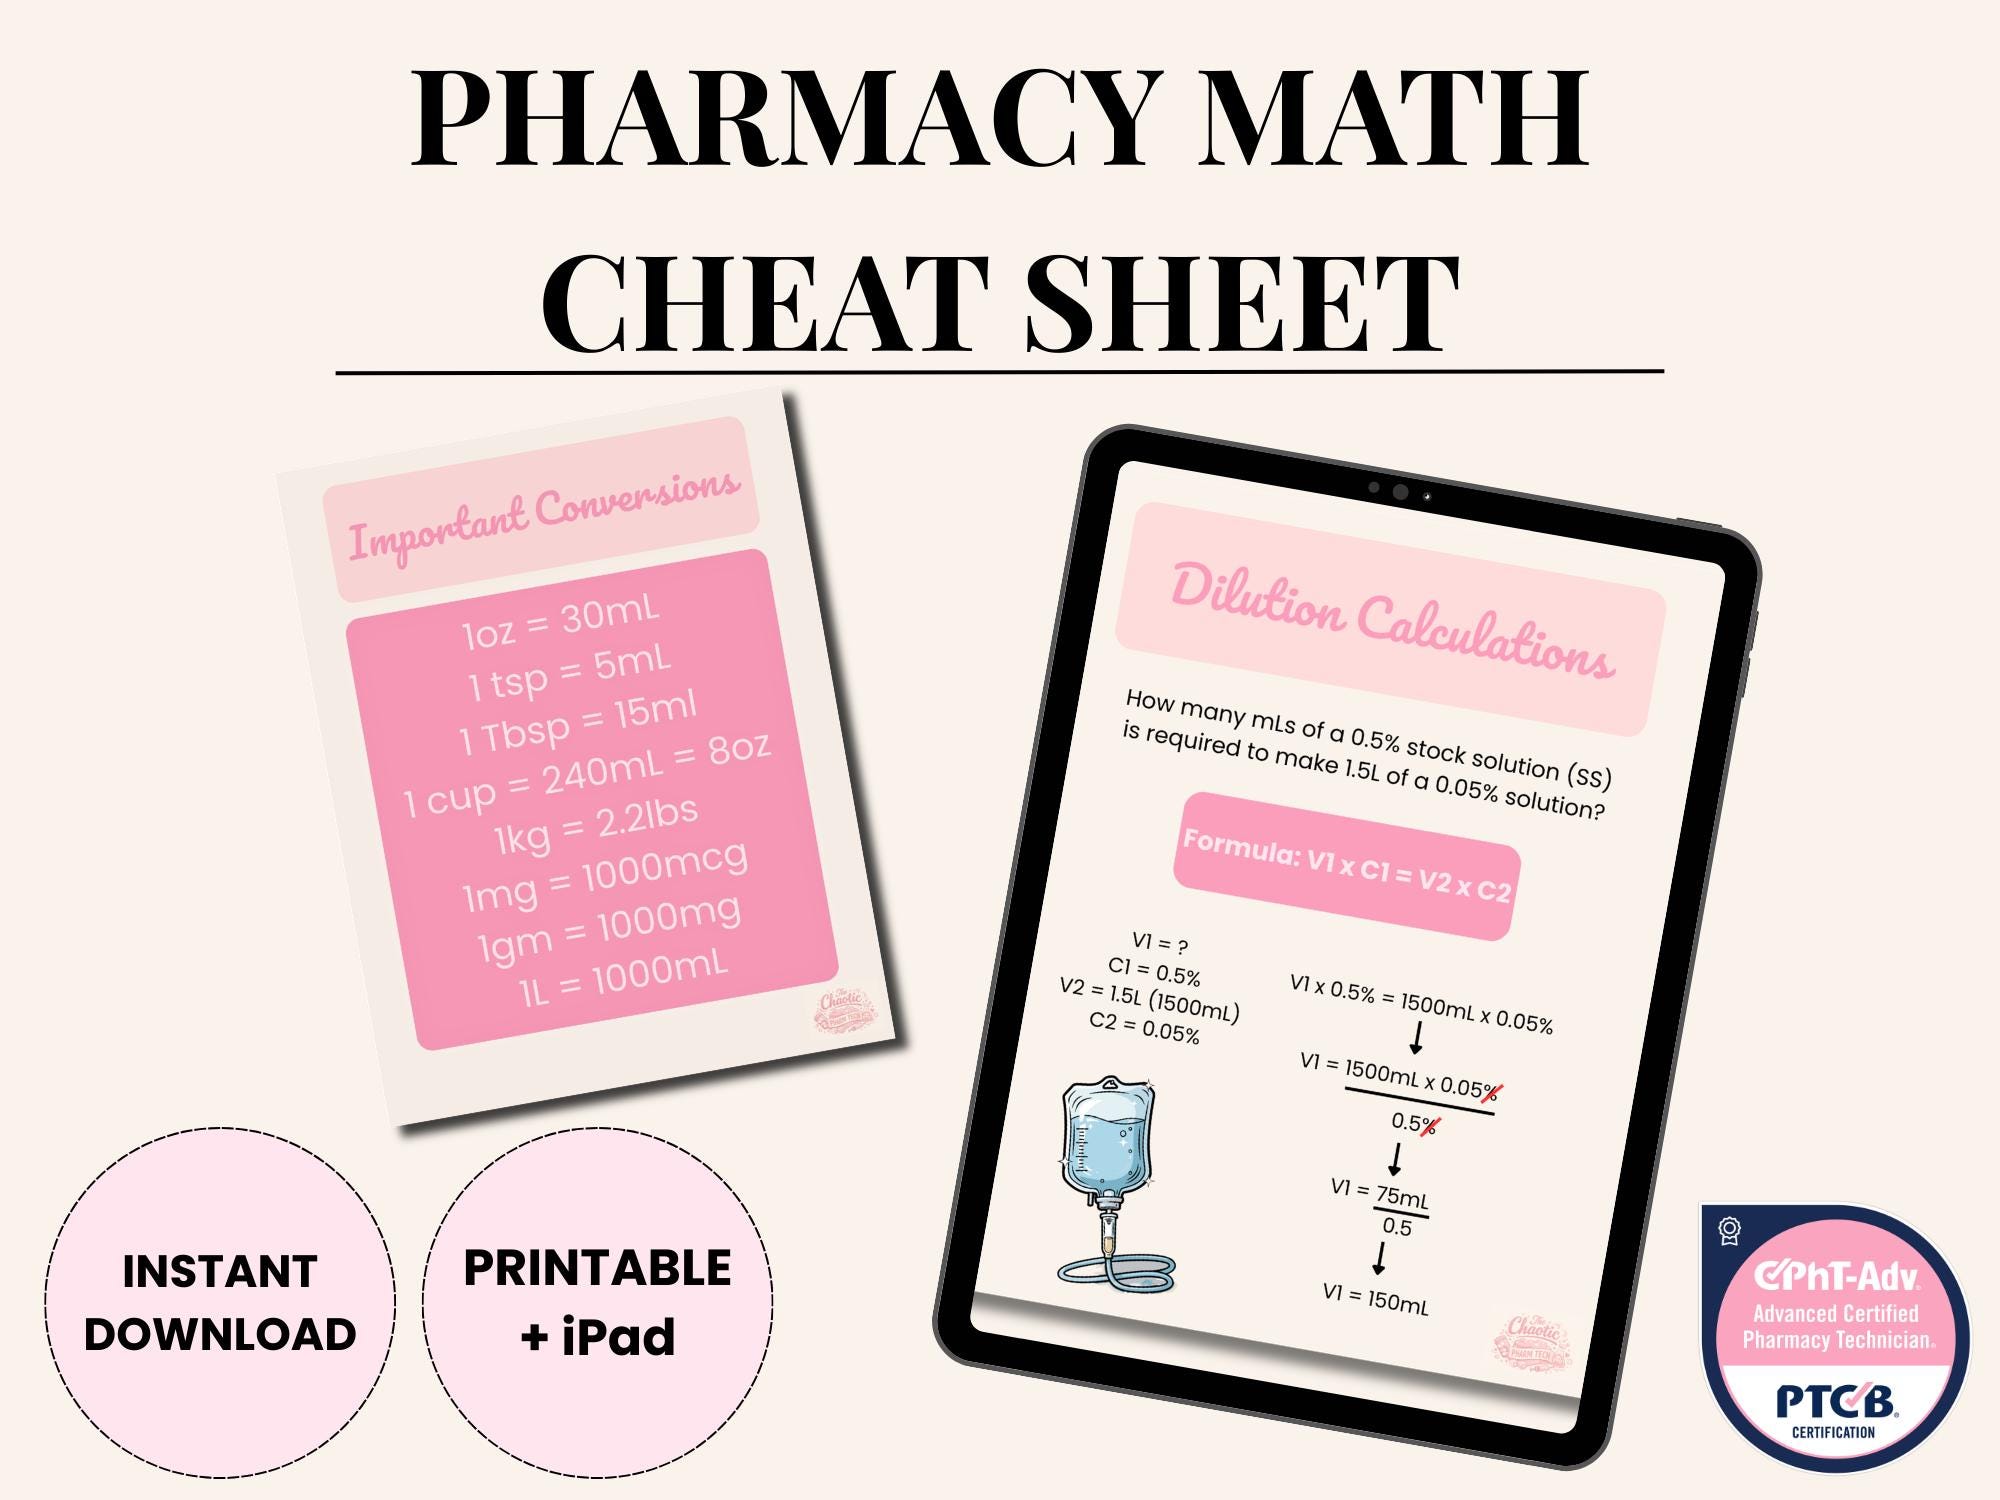
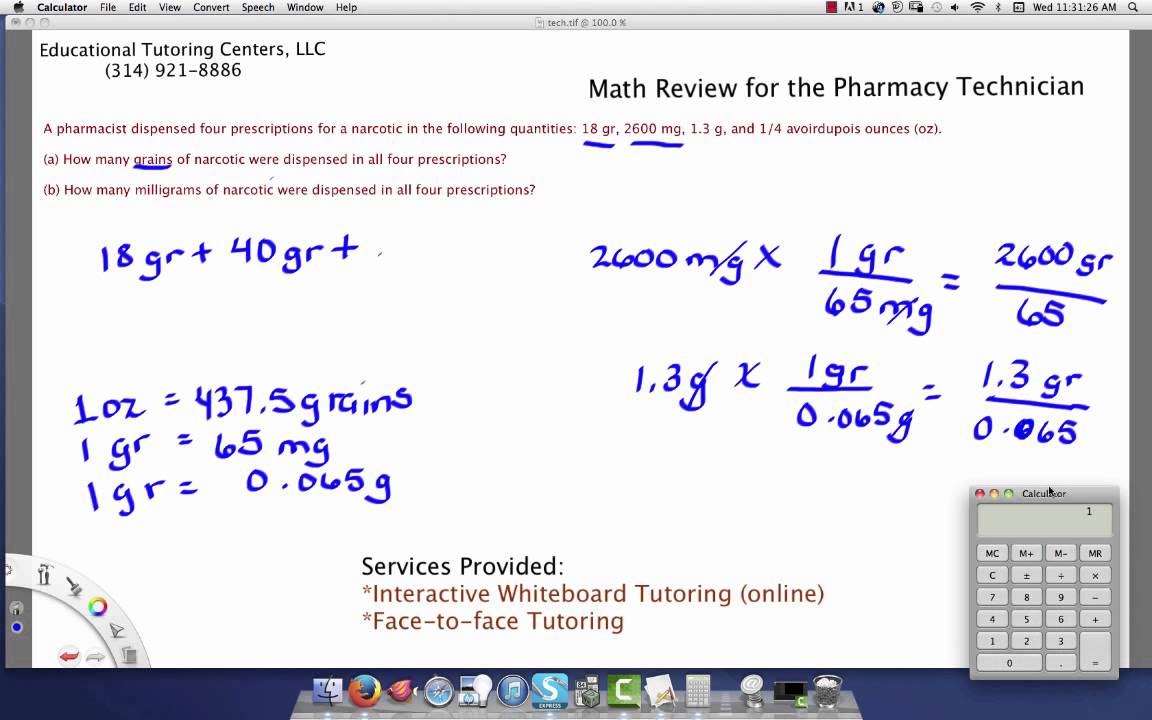
Unit conversions you must have memorized: 1 gram equals 1000 milligrams. 1 milligram equals 1000 micrograms. 1 liter equals 1000 milliliters. 1 teaspoon equals 5 milliliters. 1 tablespoon equals 15 milliliters. 1 grain equals approximately 60 to 65 milligrams, depending on which reference you trust. 1 ounce avoirdupois equals approximately 28.35 grams. 1 troy ounce equals 31.1 grams. Yes, pharmacy uses troy ounces for some precious metal compounds. Yes, it's annoying. Yes, you'll get it wrong on the exam if you assume avoirdupois.
The Problem Nobody Talks About: Significant Figures and Rounding
Pharmacy math has a dirty secret. The formulas are easy. The rounding is where everything falls apart. Pediatric doses require rounding to the nearest measurable amount. Insulin is measured in units, not milliliters, and the concentration varies by product. Warfarin tablets come in specific increments and you can't split them arbitrarily without checking stability data. I had a compounding order for a topical steroid suspension where the calculation came out to 3.47 milligrams of active ingredient per gram of base. The balance in our lab reads to 0.01 grams. That's 10 milligrams resolution. I couldn't weigh 3.47 milligrams. What I did was scale the entire formula up by a factor of ten, weigh the larger amount, and then divide the final product into the correct number of doses. This is called geometric dilution when you're mixing powders, but the principle applies to liquids too. Scale up, mix thoroughly, scale back down. Takes longer. More material waste. But it's the only way to hit the target accuracy with the equipment you have. Another thing nobody warns you about: the difference between weight and volume in compounding. "5 grams of petrolatum" and "5 milliliters of petrolatum" are not the same thing. Petrolatum has a density close to 0.8 g/mL, so 5 grams is about 6.25 mL. If a formula says grams and you measure milliliters because your graduated cylinder is more convenient, your concentrations are off. Always check whether the ingredient is specified by weight or volume. If it's ambiguous, call the pharmacist. Don't guess.
When the Formula Breaks
Some situations don't fit neatly into any formula. Renal dosing adjustments are one. Creatinine clearance calculations use the Cockcroft-Gault equation, but that gives you a number you then have to match against a drug-specific dosing table. There's no single formula that takes clearance and outputs the adjusted dose. You need the table, and the table differs by drug, by indication, and sometimes by patient population. I keep a laminated renal dosing reference at my workstation. It costs about four dollars at the office supply store and has saved me from about two dozen wrong dose calculations in three years. Hepatic dosing is even worse. There's no standardized equation like Cockcroft-Gault for liver function. Child-Pugh scores are the closest thing, and they're subjective. Bilirubin, albumin, INR, ascites, encephalopathy — each gets one to three points, you add them up, and you get a class. But the class-to-dose adjustment mapping is drug-specific and often poorly defined in the package insert. I've seen pharmacists spend twenty minutes on a single order debating whether a Child-Pugh B patient should get a 25% reduction or a 50% reduction on a particular antibiotic. The formula doesn't help you there. Experience and institutional protocol do. Drug-drug interaction dosing is another area where formulas fail. CYP450 inhibitors and inducers change clearance rates, but the magnitude of change varies wildly between individuals. A strong CYP3A4 inhibitor might double the exposure to simvastatin in one patient and increase it fivefold in another. There's no equation for that. The best you can do is flag the interaction and let the pharmacist apply clinical judgment.

Practice That Actually Works
Doing practice problems from a review book helps, but it doesn't prepare you for the actual work. The problems in books have clean numbers. Real orders have 0.375 mg when the tablet is 0.5 mg, or 1.5 mL of a liquid that's measured in 2 mL increments. Practice with messy numbers. Use a calculator. Learn to estimate before you calculate so you can spot when the answer is wrong. If your dose comes out to 47 tablets for a thirty-day supply, something is wrong. Re-check your units. I started doing one real compounding calculation per shift during slow periods. Not a practice problem, an actual order. It kept my skills sharp without the pressure of a deadline. After about six months, I could do most calculations in my head as a sanity check before running them through the computer. The mental math isn't about speed. It's about catching errors before they reach the patient. The PTCB exam covers more ground than what you use daily. Ratio and proportion, percentage concentration, alligation, apothecary units. You'll see alligation on the test even though I've probably done it twice in ten years of work. Study for the exam separately from studying for the job. They reward different things.
Resources
The ASHP pharmacy math modules are free and cover the core topics adequately. The calculation worksheets are useful because they include the messy real-world scenarios that review books skip. Mosby's Pharmacy Technician textbook has a dedicated math section that goes deeper than most review guides. For quick reference, the Handbook of Pharmaceutical Calculations is what I keep on the shelf, though it's expensive and dense. The free version from the FDA's website covers the basics but stops short of the advanced compounding calculations you'll encounter in specialty pharmacy. If you're preparing for the exam, take a timed practice test before you start studying. It shows you exactly where your gaps are instead of making you study everything at once. I took one cold and scored about 62%. The weakest area was unit conversion with derived units like mEq and mOsm. Two weeks of targeted practice brought me to 84% on the next attempt. That focused approach saved me probably twenty hours of study time compared to just working through a review book cover to cover.