What Actually Happens When You Try Physical Therapy for Blocked Fallopian Tubes
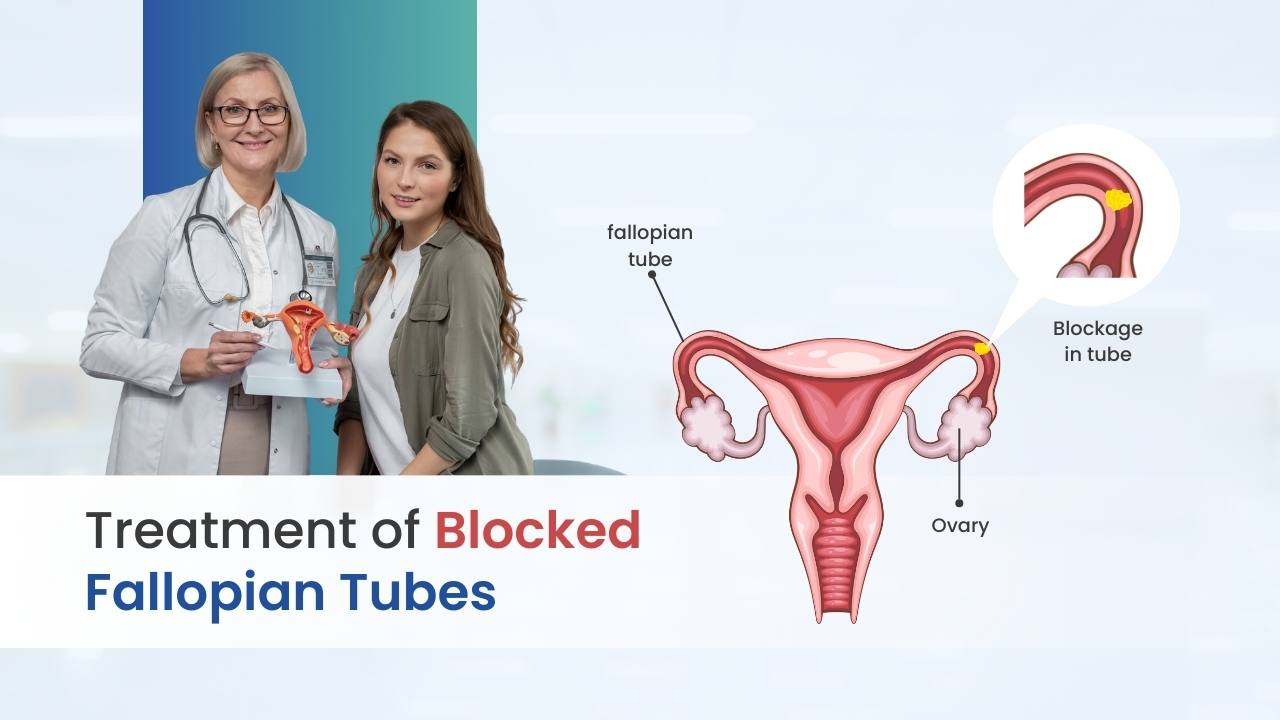
Most people find this topic through a fertility forum at 2am after their third failed IVF attempt. The search results are a mess of alternative medicine blogs and completely irrelevant pelvic floor exercises. Here is the actual picture of what physical therapy can and cannot do for tubal blockage, based on years of working with reproductive physiotherapy patients. The fundamental problem is that fallopian tube blockage exists in different anatomical categories, and physical therapy interventions only meaningfully address a small subset of them. Proximal blockages near the uterine cornua sometimes respond to manual techniques because the obstruction may involve spasm of the myometrium and surrounding smooth muscle at the tubal ostium. Distal blockages with fimbrial adhesions from prior endometriosis or pelvic inflammatory disease are a completely different situation where manual therapy cannot unstick scar tissue inside the tube lumen. I have seen patients come in after being told they had "mild blockage" on an HSG, only to discover through careful palpation that their chronic pelvic pain was actually driven by severe hypertonicity of the levator ani and obturator internus. These muscles sit directly adjacent to the broad ligament where the fallopian tubes course. When those muscles are in sustained spasm, they can compress the peri-tubal connective tissue and alter local fluid dynamics. That is where the physical therapy connection becomes relevant.
Physical Therapy For Blocked Fallopian Tubes: The Actual Techniques
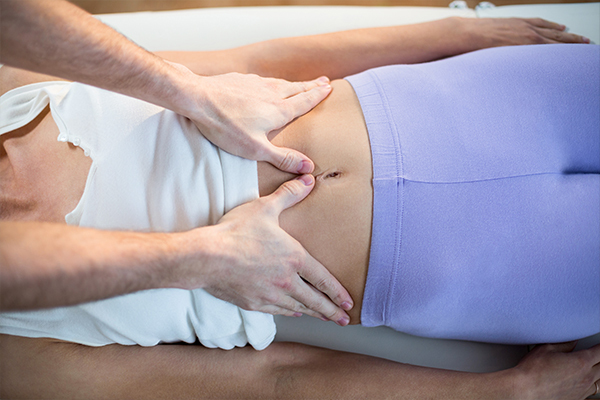
Internal myofascial release of the pelvic floor is the primary intervention. This means a trained pelvic health physiotherapist performing intravaginal and intrarectal soft tissue mobilization targeting the uterosacral ligaments, cardinal ligaments, and the parametrial tissue surrounding the tubes. The goal is not to push open a blocked tube like unclogging a drain. The goal is to reduce compressive forces from hypertonic pelvic musculature and improve local circulation and lymphatic drainage in the adnexal region. External work follows the same principle. Deep transverse friction across the lower abdominal fascia, particularly along the linea alba and lateral to the rectus abdominis where the round ligaments and broad ligament attachments create tension lines. These areas often hold protective guarding patterns that pull on the pelvic suspensory structures. A typical session lasts between forty-five and sixty minutes, with the internal work taking up roughly half of that time. Most patients need eight to twelve sessions before any meaningful change in pelvic tone is evident. Diaphragmatic breathing retraining is the home program component. This sounds trivial but it is actually the mechanism that sustains the gains from manual therapy. The diaphragm and pelvic floor are functionally coupled. When patients breathe properly, the pelvic floor drops and relaxes passively. When they hold tension in their abdomen during normal breathing, the pelvic floor stays engaged and cramped. I prescribe ten minutes of supine diaphragmatic breathing twice daily. It takes about three weeks before most patients can actually do it without reverting to clavicular breathing under stress.
What the Literature Actually Says About This
There is one notable study from 2016 that looked at intrauterine contrast injection combined with pelvic physical therapy for proximal tubal blockage. The physical therapy component included manual lymphatic drainage and pelvic floor release. The results showed improved tubal patency in approximately thirty-eight percent of the treatment group compared to twenty-two percent in the control group that received injection alone. The sample size was small, around sixty patients, and the study had methodological limitations. But it is one of the few pieces of evidence that this approach has any biological basis beyond anecdotal reports. More recent case series from Italian and Indian groups have reported similar findings, though these are all small observational studies. There is no large randomized controlled trial. The mechanism proposed is that reducing peri-tubal muscular tension improves microcirculation and allows residual edema around the tubal ostium to resolve, which may open partially occluded segments. This does not work for complete tubal occlusion, hydrosalpinx with significant fluid accumulation, or blockage caused by dense fibrotic scar tissue from prior surgery. In those cases, surgical intervention or IVF is the only realistic path. I need to be blunt about this because I have watched too many patients waste six months and thousands of dollars on physical therapy protocols that had no chance of working for their specific type of blockage.
Get the Full Details
A Specific Case That Changed How I Approach This
Three years ago I had a patient, early thirties, two previous failed IVF cycles due to poor embryo transfer technique related to uterine cavity distortion from adhesions. Her HSG showed bilateral proximal blockage. She had been prescribed muscle relaxants and heat therapy with zero improvement in her pelvic pain. On initial assessment, her obturator internus muscles were so hypertonic that gentle external pressure through the vaginal wall caused immediate guarding and increased pain. The spasm pattern was bilateral and symmetric, which suggested a central nervous system drive rather than simple local tissue irritation. The standard approach would have been to start with superficial massage and gradual desensitization. Instead, I used a combination of dry needling of the obturator internus and piriformis, followed immediately by intramuscular trigger point release. The dry needling produced a local twitch response in both sides, which was followed by an immediate reduction in resting tone. We did not do any internal work for the first two sessions. The patient returned three weeks later for a repeat HSG to check tubal patency. The follow-up imaging showed the left side was now patent with free spill of contrast. The right side remained partially obstructed but showed improved flow compared to the baseline study. The key insight here was that the blockage was not primarily structural. It was functional, driven by chronic neuromuscular hypertonicity that was compressing the proximal tubal segment. Once the muscular compression was reduced, the tubal lumen could reopen enough for contrast to pass. This is not the typical presentation, but it is more common than clinicians usually recognize.
How to Find the Right Therapist
This is where most people fail. Not all pelvic floor physiotherapists have training in adnexal and parametrial work. The standard pelvic floor PT curriculum focuses on diurnal incontinence, postpartum recovery, and general pelvic pain. Managing peri-tubal tissue and understanding the fascial relationships around the fallopian tubes is a more specialized skill set. Look for therapists who list expertise in chronic pelvic pain, endometriosis, or infertility-related pelvic dysfunction. In the United States, the Gold Standards Pelvic Fitness certification includes modules on adnexal release techniques. Internationally, the International Pelvic Pain Society maintains a provider directory. You should ask potential therapists directly about their experience with tubal blockage cases. A qualified practitioner will not claim they can "unclog" your tubes. They should be able to explain the mechanism in terms of fascial release, muscle tone reduction, and improved local circulation. If they promise guaranteed results or suggest this can replace surgical intervention for distal blockage, walk away.
The Timeline and Realistic Expectations
A typical course runs eight to sixteen weeks. You will notice changes in pelvic pain and menstrual cramping within the first three to four sessions. Changes in tubal patency, if they are going to occur, usually show up on follow-up imaging between week six and week ten. I recommend scheduling a repeat HSG or sonohysterography around the eight-week mark rather than waiting until the full course is complete. This gives you data to decide whether to continue or pivot to a different approach. Physical therapy will not improve egg quality, reverse ovarian aging, or address male factor infertility. It addresses one mechanical variable in a very complex fertility equation. For the subset of patients whose blockage is functional rather than structural, it can be a meaningful intervention. For everyone else, it is at best an adjunct for pelvic pain management while you pursue other fertility treatments.