Understanding Bone Marrow Edema and How PT Actually Helps
Bone marrow edema is fluid showing up inside the bone on an MRI. It looks dramatic on the scan but it's essentially a stress response from the bone. The marrow gets irritated, fluid accumulates, and you get deep, aching pain that often worsens with weight-bearing. I've seen this in the knee, the hip, and the ankle most often. The good news is that in the vast majority of cases, it resolves on its own. The bad news is that "on its own" can mean anything from three months to a year, and a lot of people want help getting through that faster. Physical therapy for this condition isn't about aggressive intervention. It's about managing load. The primary mechanism is straightforward: you reduce mechanical stress on the affected bone, then gradually reintroduce it as the edema resolves. You can't exercise your way out of bone marrow edema the same way you'd rehab a muscle strain. The bone needs time. Pushing too hard too early is the single most common mistake I see patients and some therapists make. The typical approach starts with offloading. That means crutches, sometimes a boot, sometimes just activity modification. How long you offload depends on severity. A mild case might get two weeks of reduced weight-bearing. A moderate case could need six to eight weeks. I base this on symptoms and follow-up MRIs, not arbitrary timelines.
Once pain allows, you begin gentle range of motion. Then you move to isometric strengthening around the affected joint. Isometrics are useful because they maintain muscle activation without significant joint movement or compressive load through the bone. A straight leg raise with a quad set, for example, can be done even when walking is still painful. Progressive loading comes next. This is where most protocols differ. Some clinicians jump into weight-bearing strength training quickly. Others take a much more conservative approach with water-based therapy first. I generally prefer a phased approach: partial weight-bearing in water, then partial on land, then full weight-bearing with strengthening, then functional movements. Each phase takes at least two to three weeks minimum before progressing, and I only advance when the patient has minimal pain during and after the session.
The Loading Paradox
Here's something most people don't understand about bone marrow edema rehab: some mechanical loading is actually beneficial for resolution. Complete immobilization isn't the answer. The bone needs controlled, graduated stress to stimulate remodeling. But there's a very narrow window between therapeutic loading and re-injury. Load too low and nothing improves. Load too high and you extend the healing timeline significantly, sometimes turning a six-week case into a six-month one. The principle is Wolff's Law - bone adapts to the loads placed on it. But the adaptation only happens if the load stays below the threshold that causes further microdamage. In practice, this means staying in a pain range of about 3 out of 10 during activity, with no significant increase in pain the next morning. If next-morning pain is worse, you did too much that day.
Get the Full Details
Specific Protocol Details
For a knee-based bone marrow edema, which is by far the most common presentation, here's what a typical progression looks like over roughly twelve to sixteen weeks: Weeks 1-3: Crutches with partial weight-bearing as tolerated. Isometric quad and hamstring sets. Ankle pumps for circulation. Pool walking if a pool is available. No impact. No deep knee flexion under load. Weeks 4-6: Gradual weaning off crutches as gait normalizes. Stationary bike with low resistance, seat high to limit knee flexion. Continue isometrics, add mini-squats to thirty degrees. Balance work on firm surface.
Weeks 7-10: Full weight-bearing if pain-free. Resistance band work for hip abductors and external rotators. Closed-chain exercises progressing from shallow to deeper range. Elliptical machine replaces bike. No running yet. Weeks 11-16: Progressive strengthening through full range. Introduction of low-impact cardio. Plyometric prep begins only if the patient is completely asymptomatic with daily activities and a follow-up MRI shows significant resolution. Return to sport decisions are made individually based on imaging and functional testing, not on a fixed timeline.
A Real Problem I Encountered
I had a patient with persistent lateral femoral condyle edema who wasn't improving despite a compliant program. We were at week eight and she was still relying on a cane. Everything seemed right on paper. Then I looked at her foot mechanics more carefully. She had subtle but significant rearfoot valgus with excessive pronation, which was creating a rotational force through the knee with every step. No amount of quad strengthening was going to fix that. The workaround was a custom orthotic with a medial post and a slight varus wedge, combined with targeted peroneal strengthening. Within three weeks of adding this to her program, her pain dropped from a 5 to a 2 on most days. She weaned off the cane two weeks later. It took another eight weeks to reach full activity. Without addressing the biomechanical driver, she would likely have remained stuck in that prolonged inflammatory cycle.
Common Pitfalls to Avoid
Returning to activity too soon is the biggest one. Patients feel better before the bone is actually healed. The edema lingers on MRI even after symptoms resolve, so symptom-only monitoring isn't sufficient. I always get a follow-up MRI before clearing someone for impact activities, typically around the eight-to-twelve-week mark for moderate cases. Another mistake is focusing only on the joint with the edema. The kinetic chain matters. Hip weakness, especially in the abductors and external rotators, directly increases load on the knee. Ankle stiffness forces compensatory mechanics upstream. I assess and treat the entire chain, not just the painful area. Neglecting nutrition is also common and underrated. Vitamin D deficiency, inadequate protein intake, and low caloric availability all slow bone healing. I routinely check vitamin D levels in patients with persistent or recurrent edema. Supplementation when deficient can make a measurable difference in resolution speed.
When Physical Therapy Isn't Enough
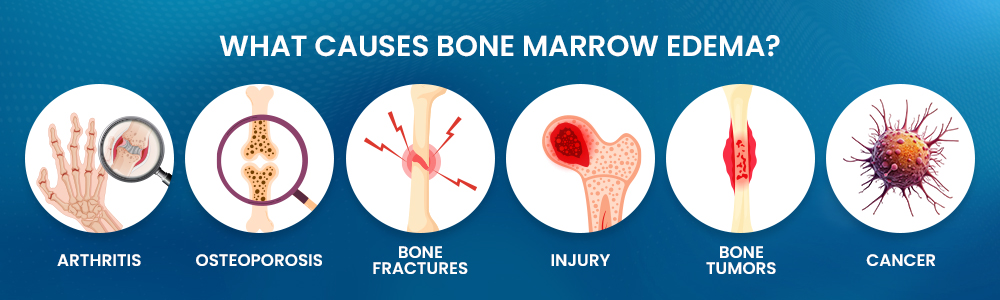
Sometimes the standard approach doesn't work. If the edema is large, involves a weight-bearing surface, or hasn't improved after three to four months of appropriate conservative care, you need to reconsider the diagnosis. What looks like bone marrow edema on MRI might be a stress fracture that needs stricter protection, or it could be something else entirely - transient osteoporosis of the hip, avascular necrosis in early stages, or even a bone tumor mimicking edema. For persistent idiopathic bone marrow edema of the hip, some clinicians use bisphosphonates like alendronate. The evidence is mixed but there are decent case series showing accelerated resolution. Extracorporeal shockwave therapy has also shown promise in some studies. These aren't first-line treatments but they're worth discussing with an orthopedic specialist if conservative management stalls. Bone marrow edema is frustrating because it operates on a timeline that doesn't match human impatience. The physical therapy approach is straightforward in theory - reduce load, gradual re-loading, address contributing factors - but execution requires patience and careful monitoring. The patients who do best are the ones who understand that this is a marathon, not a sprint, and who follow through consistently without rushing the progression.