Gait Re-education for Plantigrade Loading
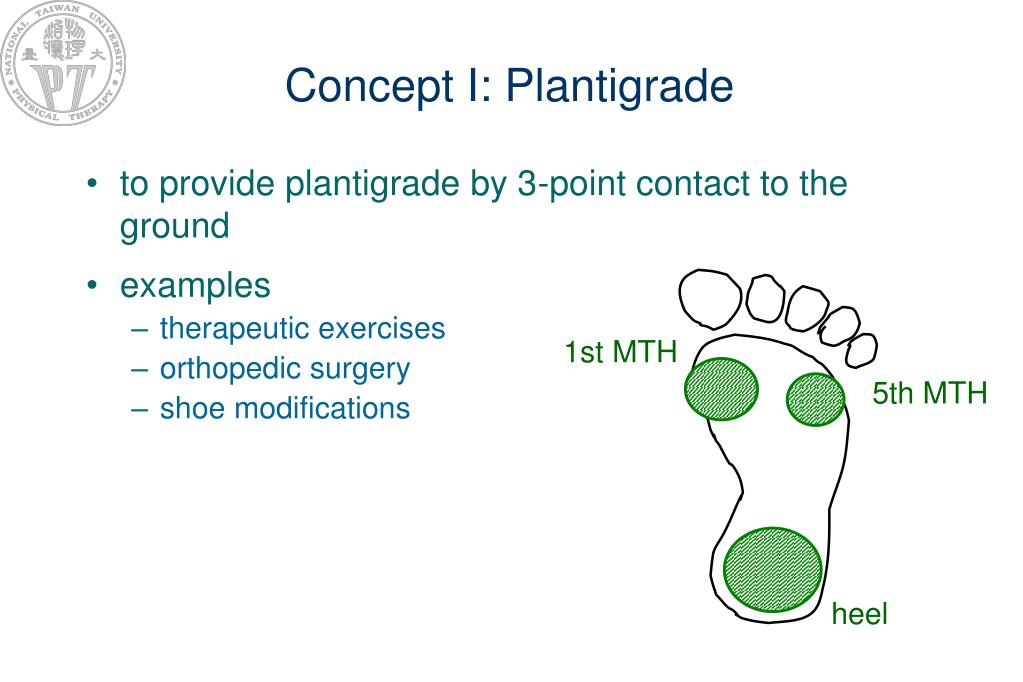
Most people who end up in PT for foot or ankle problems are not actually using their feet properly when they walk. They're loading the midfoot poorly, collapsing the arch, or staying on their forefoot because something hurts. Plantigrade Position Physical Therapy is just a structured way of teaching the body to accept full foot contact again. It's not a proprietary brand name, it's a descriptor. You'll see it used in pediatric neuro, post-op ortho, and adult gait retraining clinics. Same concept, different label. The core mechanic is simple. You train the client to land heel-first, roll through the midfoot, and push off the forefoot without bypassing any phase. The problem is that most people skip phases out of habit or pain avoidance. The therapy builds each phase back in isolation before chaining them together. In practice, sessions usually look like this. The patient stands barefoot on a firm surface. Weight is distributed so you can draw a line down the center of the foot and have roughly equal mass on both sides. From there, you cue heel contact, then tibial progression over the foot, then metatarsal loading, then big toe extension for push-off. Each segment gets held for a few seconds initially. Repetition comes after control is established.
I worked with a guy last year who'd been cleared for full weight bearing after a navicular fracture. Six weeks post-op he still couldn't get his heel to stay on the ground during swing phase. He was essentially forefoot striking out of fear. We spent three weeks just doing seated weight transfers and single limb balance on a low ramp before he could walk forty feet without limping. The plantigrade drills came later. You don't bolt a car's engine in before the frame is straight.
Setup and Equipment
You don't need much. A flat firm floor or a therapy mat. Some tape for proprioceptive marking. A low step or ramp if balance is the issue. Mirror feedback helps a lot, either a full length mirror or a tablet propped up so the patient can watch their own foot roll. Pressure mats are nice but not required, and most clinics don't have them lying around anyway. If you're doing this at home, a simple piece of paper on the floor works as a target. Have the patient press their full foot onto it and hold. Mark where the pressure is concentrated. Most people will surprise you by finding out they're already loading the lateral border or the hallux exclusively.
Get the Full Details

Progression Ladder
Phase one is static. Weight shifts in standing, marching in place with deliberate heel strike, and single leg balance. This phase alone usually takes two to four weeks for someone with chronic dysfunction. Patients want to move faster. They don't. Phase two introduces slow walking with cues. Heel contact, midfoot roll, toe push. Tempo is deliberately sluggish. Speed kills the pattern before it's wired in. Twenty paces with rest breaks is a full set at this stage. Phase three adds complexity. Uneven surfaces, turning while walking, walking while carrying a load, tandem gait. This is where the pattern either holds or falls apart. If it falls apart, you go back to phase two for another week.
Phase four is functional integration. Stairs, slopes, different footwear, sport specific drills. Shoes with stiff soles or high heels defeat the purpose entirely. That's a feature of the method, not a bug.
Common Pitfalls and What I've Learned the Hard Way
The biggest mistake is rushing the midfoot loading phase. People can touch their heel to the ground. They cannot keep the arch from collapsing while doing it. I've seen therapists skip this because the patient says "I'm doing it fine" and the patient is doing it fine until they walk more than fifty feet and develop medial knee pain three blocks later. Arch endurance is a real measurable thing. Build it slowly. Another issue is compensatory hip hiking. Patients who can't get proper dorsiflexion at initial contact will just lift their whole leg higher to avoid dragging the toes. This looks like clearing but it's not plantigrade mechanics. The fix is anterior capsule mobilization and tibialis anterior strengthening before gait drills. I wasted a month on one patient trying to cue around a tight capsule. Switched to joint mobs and calf release and she started rolling through her feet the next session. Footwear matters more than patients think. A lot of modern running shoes have rolled soles and thick medial posting that make plantigrade loading almost impossible without conscious effort. I had a marathoner come in with recurrent plantar fasciitis who was wearing maximalist cushioned shoes. We switched him to a flatter shoe with a wider toe box and his heel strike pattern changed within a week. The shoes were part of the problem.

When This Approach Fails
Structural limitations exist. Cavus feet, equinus contractures, prior fusion surgery, Charcot changes, severe neuromuscular deficits. In these cases plantigrade loading may never be fully achievable and that's okay. The goal shifts to whatever foot contact pattern minimizes pain and prevents secondary damage. Forcing a rigid cavus foot into a neutral roll pattern will just overload the metatarsal heads. Adapt the protocol or refer out. Neuropathic feet need different handling entirely. Loss of proprioception means the patient can't feel whether they're loading properly. You need external feedback systems or therapist guidance for every step. This isn't a home exercise scenario.
Measuring Progress
Don't rely on subjective reports. Use force plates if available, or video analysis at 120fps minimum. Watch the heel contact angle, the speed of pronation, and the timing of toe off. Time the whole stance phase. Normal is roughly sixty percent of the gait cycle. If it's under fifty percent, something is being skipped. Simple metrics that actually work: single leg balance time on the affected side, heel raise repetition count before form breaks down, and a timed twenty meter walk with video review. Track these every two weeks. Improvement is usually visible in three to six weeks for uncomplicated cases. This isn't a quick fix. It's a retraining protocol and it shows exactly how much work went into building that foot arch nobody thinks about until it stops working.


