
Understanding Internal Anatomy From the Outside
When you're studying Position Of Organs In Body, most people start with textbooks and diagrams. Those are fine for the basics, but they don't prepare you for what happens when organs shift. I spent years doing ultrasound imaging, and the first thing I learned is that anatomy atlases lie to you about consistency. The standard model puts the liver primarily in the right upper quadrant, the stomach on the left side beneath the diaphragm, and the heart slightly left of midline. That's textbook correct and it's also frequently wrong in real bodies. I remember one patient during a routine abdominal scan whose liver extended across the entire upper abdomen. The gallbladder was positioned lower than normal, tucked between the liver and the right kidney. A student reading the standard charts would have missed it entirely because they were looking for it in the typical location. Here's the thing about organ position that nobody emphasizes enough: your posture changes where things sit. When someone is standing upright versus lying supine, abdominal organs shift downward by roughly two to three centimeters. The diaphragm drops, the liver follows, and the intestines redistribute. If you're reading imaging scans taken in different positions, the organs will appear in slightly different locations even on the same person scanned on different days.
The heart sits on the pericardium and is suspended in the mediastinum. It rotates slightly with each beat, and its position shifts with breathing. During inhalation, the diaphragm contracts and moves down, pushing the heart slightly upward and rotating it. During exhalation, everything settles back. This matters if you're doing anything precise like cardiac catheterization or even interpreting ECG leads, because electrode placement assumes a relatively standard position that doesn't always match reality.
Practical Considerations When Working With Organ Position
I had a colleague who was reading CT scans for trauma cases. He once missed a small subphrenic abscess because he was looking for it on the right side where the liver sat, but the patient had situs ambiguus, a condition where organ placement is neither normal nor completely mirrored. The abscess was actually on the left side, where a normal person's stomach would be. That patient had been misidentified as having normal anatomy on previous imaging reports. It took three scans before someone actually looked carefully enough to notice the arrangement was atypical. There are conditions that shift organs routinely. Ascites, the accumulation of fluid in the peritoneal cavity, pushes organs around significantly. A moderate amount of ascites can displace the intestines toward the center and push the liver upward against the diaphragm. I've seen patients with advanced liver cirrhosis where the liver itself is so shrunken and nodular that it barely occupies its expected space, and the surrounding organs have rearranged to fill the void. Pregnancy is another obvious factor, but it's often underestimated in non-obstetric imaging. By the third trimester, the uterus displaces the intestines superiorly and laterally, pushes the stomach upward and to the left, and can compress the inferior vena cava against the spine. The heart itself shifts slightly because the diaphragm is elevated. If you're positioning probes or planning surgical access without accounting for these shifts, you're working blind.
Get the Full Details

Common Mistakes People Make
The biggest error I see is treating anatomical diagrams as rigid maps rather than approximations. Organs are not bolted in place. They're held by mesenteries, ligaments, and fascia, all of which have some flexibility. The kidneys, for example, are retroperitoneal but mobile. A normal kidney can move up to five centimeters during respiration. That's significant if you're planning a needle biopsy or tracking a tumor over time across different imaging sessions. Another mistake is assuming symmetry implies normalcy. Just because something appears balanced doesn't mean it's correctly positioned. I reviewed a case where a patient's spleen was enlarged enough to cross the midline into the right upper quadrant. It was mistaken initially for a mass in the liver because the radiologist was focused on finding pathology in expected locations rather than evaluating the actual arrangement. Body habitus affects organ position more than most people realize. In very obese individuals, the increased intra-abdominal fat pushes organs superiorly and alters their rotational orientation. In cachectic patients, the opposite happens. Organs drop and spread out differently. The same organ system in two different bodies can look fundamentally different on imaging, and both can be completely normal.
How to Approach This Subject Without Getting Lost
Start with the standard model. Learn it well enough that you can draw it from memory. Then immediately learn the common variations. Dextrocardia affects roughly one in ten thousand people but shows up regularly in clinical practice because the consequences of missing it are severe. A surgeon operating assuming a normal heart position on a dextrocardia patient is a catastrophic scenario that has actually happened. Use cross-sectional imaging when possible. CT and MRI show relationships between structures in ways that 2D diagrams cannot. When you can see the liver adjacent to the right kidney, the stomach anterior to the spleen, and the pancreas draping across the posterior abdominal wall, you understand position as a three-dimensional relationship rather than a list of locations. The duodenum is the hardest structure to pin down positionally because it wraps around the head of the pancreas in a C-shape and crosses the midline multiple times. Its position relative to the superior mesenteric artery and vein varies considerably between individuals. If you're studying gastrointestinal anatomy, spend extra time here. The rest of the tract follows more predictable patterns, but the duodenum and its mesenteric attachments are where textbook simplifications break down most often.
When Standard Positioning Information Fails You
Situs inversus totalis is the classic variation where every organ is mirrored. The heart is on the right, the liver on the left, the stomach on the right. About a third of people with this condition also have Kartagener syndrome, which involves chronic sinus and lung infections due to ciliary dysfunction. The other two-thirds are otherwise healthy and may never know they have it until they seek emergency care and a doctor notes the heart sounds are coming from the wrong side. Malrotation is another condition where the intestines fail to rotate properly during fetal development. The small intestine and colon end up in abnormal positions, and the vascular supply can be compromised. This is a surgical emergency when it presents in newborns, but milder forms go undetected for years. Adults sometimes present with intermittent abdominal pain, and the diagnosis requires a high index of suspicion because standard imaging can be misinterpreted as normal. There's no shortcut for understanding these variations beyond exposure. Reading about them helps, but seeing them repeatedly in clinical settings is what builds the pattern recognition you need. I recommend looking at annotated imaging case collections when available, and paying attention to every case that doesn't look exactly like the atlas picture. Those exceptions are where you learn the most.
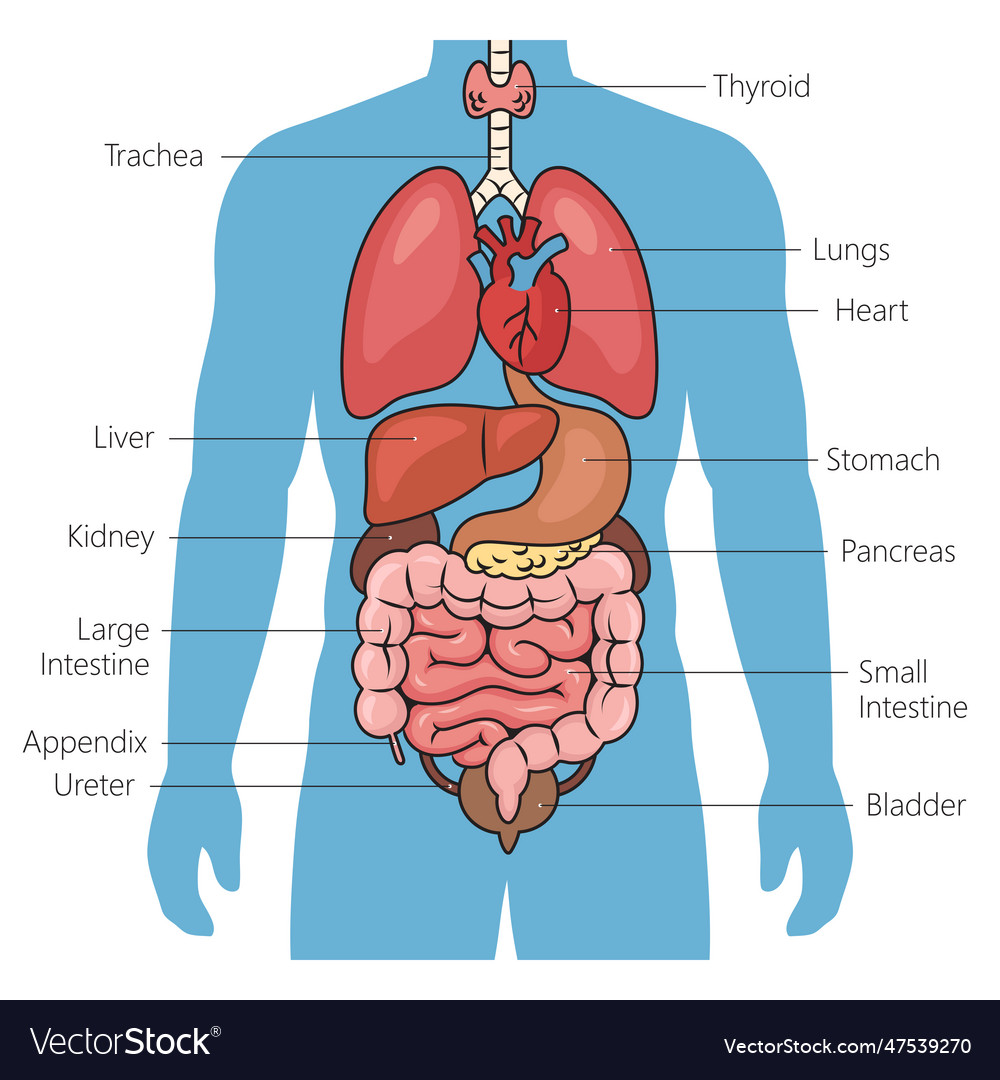
The human body is surprisingly variable, and the Position Of Organs In Body is a starting point rather than a rule. The variations exist for a reason, and most of them don't cause problems until someone tries to treat the body as if it follows a standard template. Keeping that in mind changes how you approach everything from reading scans to planning procedures to simply understanding what's happening when symptoms don't match the textbook presentation.


