Working With Press Ganey Patient Satisfaction Survey Questions
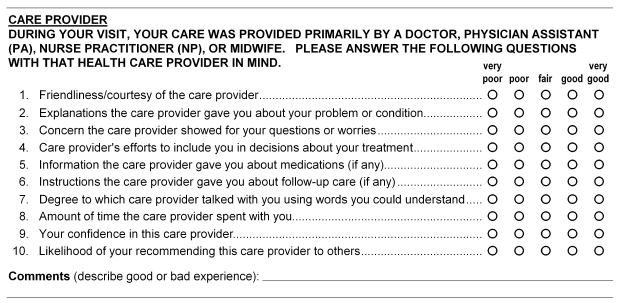
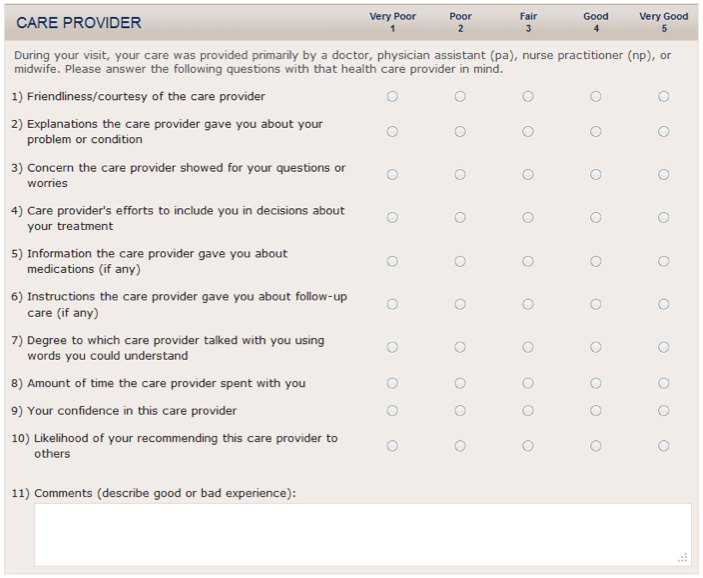
The Press Ganey Patient Satisfaction Survey Questions are what the vendor uses to measure patient experience across hospitals and health systems. They show up in patient satisfaction dashboards, drive star ratings, and get referenced constantly in leadership meetings. If you're dealing with them at your site, you already know how much weight they carry. Press Ganey sends out surveys after a patient encounter. The patient responds on a scale, usually 1 through 10, and then the system aggregates those numbers into composite scores. The most commonly referenced composites include overall experience, nursing communication, physician communication, pain management, discharge information clarity, and medication information. You'll see these broken down by department, by physician, by unit, and sometimes by individual shift.
Press Ganey Patient Satisfaction Survey Questions
I spent several years managing survey response programs at a mid-sized hospital system. One thing I learned quickly is that the raw data Press Ganey delivers is only as useful as the context you add to it. A physician can have a low score one month and a high score the next with no change in actual behavior. Seasonality matters. Census shifts matter. Staffing ratios matter. If you treat the numbers as literal truth without looking at the operational context behind them, you will make the wrong decisions. The survey questions themselves are fairly standardized across the Press Ganey hospital survey product. The core questions cover things like nurse courtesy, responsiveness to calls, doctor listening skills, explanation of medications, and overall rating of the hospital. Each question maps to a composite domain. The scoring structure weights some questions more heavily than others depending on the composite being calculated. That weighting is not always transparent in the standard dashboard export, which is why digging into the methodology documentation Press Ganey provides is important. Response rates have been declining industry-wide for about a decade. My site averaged around 35 percent response rate on standard mail-and-web surveys, which is typical for the sector. When response rates drop below 30 percent, statistical reliability becomes a real concern, especially for smaller units or individual provider reports. Press Ganey applies statistical adjustments for small sample sizes, but those adjustments introduce their own uncertainty. I learned this the hard way when a cardiology attending complained about a single-digit response rate making his quarterly report look unreliable. The actual number was twelve responses out of 147 discharges. Press Ganey's adjustment algorithm boosted his composite by nearly 8 points, which made his score look decent on paper while the underlying data was essentially noise. I stopped reporting at the individual provider level when n was under 20 and switched to rolling three-month aggregates instead. That gave us enough volume to work with without feeding false precision to people who didn't need it.
One counter-intuitive thing about these questions is that the top-box score, meaning the percentage of respondents who select 9 or 10, does not always move in lockstep with the overall composite score. A unit can improve its composite by increasing the middle-range responses while losing top-box percentages, or vice versa. This happens because the composites are weighted averages and the top-box metric is calculated differently. When our outpatient surgery unit focused exclusively on hitting top-box targets, their composite actually dropped slightly because we were optimizing for one metric at the expense of the broader weighted calculation. Leadership wanted the top-box numbers to go up, so I had to explain that chasing them in isolation could produce the opposite result on the reported score. We shifted the conversation to overall composite improvement and the top-box numbers followed naturally from there. Another common pitfall is treating all survey questions as equally impactful when they are not. Press Ganey publishes factor loadings in their methodology guides. Some questions contribute far more to a given composite than others. The question about whether nurses always seemed concerned about your comfort typically has a much higher loading on the nursing composite than the question about whether the room was quiet at night. If you're designing improvement initiatives based on survey results, prioritize the high-loading questions first. I once saw a unit waste three months implementing noise-reduction interventions because a patient mentioned it in a comment, when the real driver of their low nursing score was something completely different in the communication domain. The noise question had minimal impact on the composite anyway. The comment section is where most people look for qualitative data, and most people interpret it incorrectly. Comments are voluntary, which means they are heavily skewed toward extreme experiences. A patient who had a terrible stay is far more likely to write a comment than someone who had an adequate stay. I used to share raw comments with unit managers and get pushback when patients complained about issues that were not actually reflected in the scored questions. The comments describe the tail end of the distribution. The scored questions describe the center. They tell you different things. Keep them separate in your analysis.
Get the Full Details

If you need the actual survey instrument, Press Ganey provides it within the platform itself. You can access the full question list through the Survey Tools section under Survey Design. There is no public PDF you can download directly from the Press Ganey website. They do offer a sample questionnaire overview through their published materials, but the complete instrument with exact wording and response scales is accessible only to contracted clients. Your Press Ganey account representative can pull a current version if you do not have direct access. There are honest limitations to this system. The survey captures a moment in time from a self-selected group of patients. It does not measure clinical quality directly. A hospital can have excellent outcomes and mediocre patient satisfaction scores, or the reverse. Press Ganey scores should be used alongside clinical quality metrics, not as a substitute for them. I have seen executives use a jump in Press Ganey scores as proof that a clinical improvement initiative worked, when in reality the score change was driven entirely by a staffing adjustment that happened to coincide with the same timeframe. Correlation is not causation, and patient experience surveys are particularly vulnerable to that confusion because so many external factors influence the scores. The survey timing also matters more than most people realize. Press Ganey sends surveys at different intervals depending on the acuity level and length of stay. Inpatient surveys typically go out three to five days after discharge. Outpatient surveys go out shortly after the visit. If your facility changed discharge processes or call-center workflows during a measurement period, those changes can shift response patterns without any actual change in patient experience. Always check your operations calendar against your survey reporting periods before drawing conclusions.
Data export formats vary by subscription tier. The standard export includes composite scores, response rates, and top-box percentages. Detailed response-level data with demographics and cross-tabulations usually requires an additional license. If your organization needs to run segment analyses like racial and ethnic health equity breakdowns, make sure your contract covers that. Press Ganey added health equity dimensions to their survey product a few years ago, but not every site's account includes access to the disaggregated data needed to report on it properly. The benchmarking component is one of the stronger features if you use it correctly. Press Ganey compares your scores against a peer group you help define. Choosing the right peer group matters because an inappropriate comparison set can make your performance look better or worse than it actually is. A small critical access hospital should not benchmark against a large academic medical center. I had a client who kept their peer group static for four years without updating it, and by year three their peer group had drifted significantly because member hospitals came and went. The benchmarking data was stale and misleading. Review your peer group composition annually. Survey software integration varies by vendor version. Some health systems connect Press Ganey data to their electronic health records or internal performance dashboards through API feeds. Others manually export and rebuild reports. The API route reduces manual processing errors and cuts reporting time substantially, but it requires IT coordination and sometimes additional licensing fees. If you are still doing manual exports every quarter, you are probably spending several hours per month on data reconciliation that could be automated.
When interpreting trend data, use rolling averages rather than single-period snapshots. One month's data can swing wildly due to temporary factors like flu season surges, holiday staffing gaps, or IT outages that interrupt survey delivery. A three-month rolling average smooths out those anomalies and gives you a more stable signal. I started using six-month rolling windows for executive presentations because quarterly trends were creating unnecessary alarm during normal fluctuation periods. The survey has become a contractual requirement for many health systems as part of value-based purchasing arrangements and public reporting mandates. Medicare's Hospital Compare program incorporates patient experience data from Press Ganey and other vendors. This is why the scores matter beyond internal quality improvement. They affect public reputation and reimbursement calculations. Understanding the mechanics of how the scores are generated helps you protect your site from misinterpretation when those numbers go public. Bottom line: the Press Ganey Patient Satisfaction Survey Questions give you structured feedback about the patient experience, but they require careful handling. Use appropriate sample sizes, understand what each composite actually measures, account for operational context, and do not confuse correlation with causation. The data is useful if you treat it as one input among many rather than a definitive verdict on performance.