What the Guidelines Actually Say About Timing
The short answer is: on admission, then daily while the patient is acutely ill, and at every significant change in condition. That is what the major bodies like ACPEN, NICE, and the Wound, Ostomy and Continence Nurses Society all basically agree on. The Braden Scale or Waterlow tool isn't something you fill out once and file away. Skin breakdown doesn't wait for your paperwork schedule. I have worked through dozens of hospital policies over the years and the most consistent finding is this: the biggest failures happen because assessments stop being routine once the initial score is documented. You see it constantly. A patient comes in with a Braden of 14, they get the risk interventions, and then three days later their lab values have shifted, their nutrition intake has dropped, and their mobility has worsened but nobody recalculated because the original assessment was already in the system.
Pressure Ulcer Risk Assessment Should Be Completed How Often
This is the question that comes up most in my practice and the answer depends heavily on the care setting. In acute hospitals, daily is the floor, not the ceiling. I once worked a unit where the policy said weekly for stable patients on a general ward and I pushed back hard because the evidence doesn't support that. A patient can go from a Braden of 12 to a 9 overnight after surgery or a septic episode. Weekly reassessment in that environment is how Stage 2 ulcers slip through. In long-term care, the cadence is slightly different. Admission assessment, then at least monthly per CMS requirements, but any change in weight, appetite, functional status, or diagnosis warrants an immediate recheck. I had a resident once who lost twelve pounds over three weeks due to a dental issue. Her Braden dropped four points but the monthly schedule meant we missed the window where early intervention could have prevented the sacral ulcer that eventually developed.
The Tools Most Facilities Use
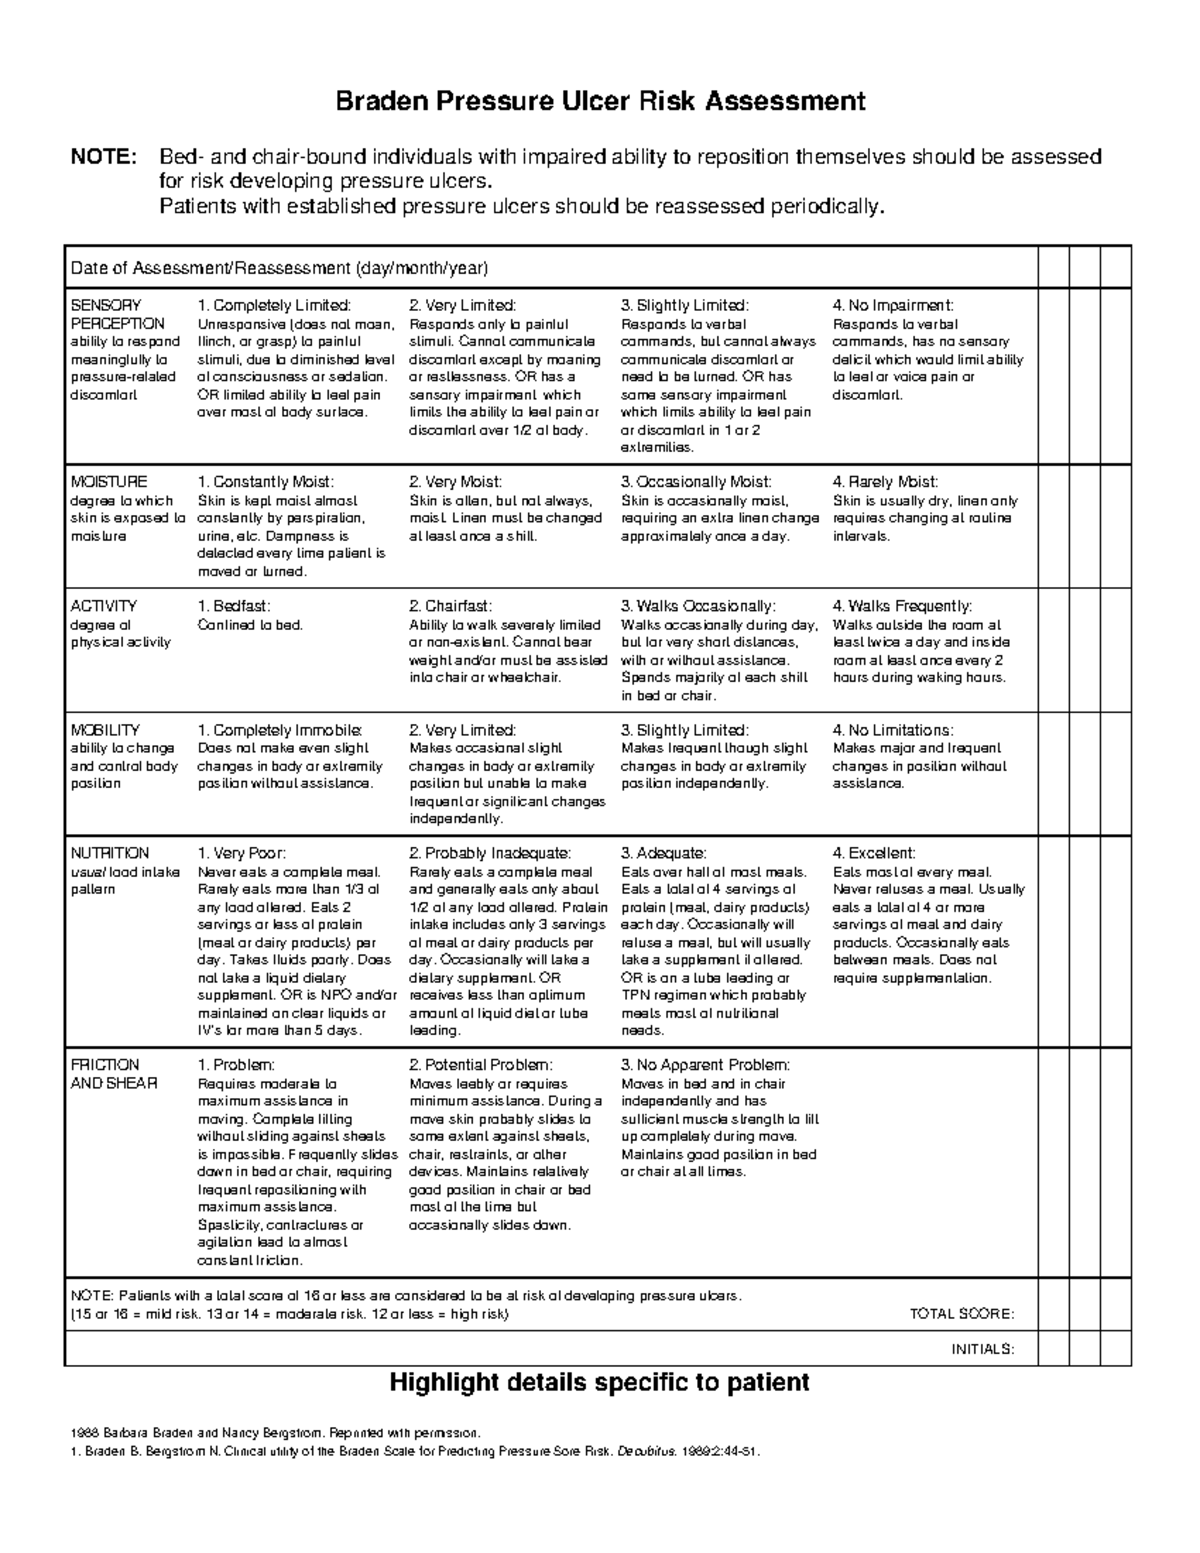
Braden Scale remains the most widely adopted in North America. It covers six domains: sensory perception, moisture, activity, mobility, nutrition, and friction and shear. Each gets scored from one to four or one to three, with lower totals indicating higher risk. A score of 15 or below generally triggers full wound prevention protocols in most hospital systems. Nortontool is more common in the UK and parts of Europe. It includes additional factors like BMI, skin temperature, and serum albumin, which makes it slightly more sensitive to metabolic and inflammatory changes. Martin Marietta area hospital and several NHS trusts have migrated toward it because the nutritional parameters catch deterioration earlier than Braden alone. Waterlow is another option you will encounter, particularly in community nursing. It weights nutrition and BMI more heavily and includes a body shape factor. The scoring thresholds differ from Braden so direct comparison between tools is unreliable. Switching assessment tools mid-stay without recalibration creates documentation gaps that auditors notice.
Get the Full Details
What Nobody Talks About
There is a well-documented problem with inter-rater reliability on these tools. Two nurses assessing the same patient can arrive at different Braden scores up to twenty percent of the time, usually on the mobility and friction shear domains. This isn't because people are careless. The domains are subjective. Friction and shear especially depend on clinical judgment about how much assistance a patient needs with repositioning versus how they actually move in bed. My workaround for this was simple but not universally applied. I started requiring paired assessments during competency validation. Two clinicians score independently, then compare and discuss discrepancies before finalizing the result. This didn't eliminate variation but it reduced it significantly over time as staff calibrated their interpretations. Facilities that skip this step tend to have the noisiest risk data across a shift. Another counter-intuitive point: a low-risk score does not mean zero risk. Patients with spinal cord injuries, vascular disease, or edema can develop pressure injuries at any Braden level. The tools were validated on mixed medical-surgical populations and don't account for impaired sensation from neuropathy or restricted blood flow from peripheral vascular disease. If a patient has a legitimate perfusion or sensory issue, the tool score should be overridden clinically regardless of what the number says.
Practical Execution in a Busy Unit
The theoretical framework is straightforward. The execution is where things break down. I have seen units where nurses completed assessments at the end of shift instead of at the beginning, meaning the risk data was already twelve hours old by the time it was relevant. I have seen residents in skilled nursing facilities reassessed only when a new wound appeared, which defeats the entire purpose of risk screening. Electronic health records can help or hinder depending on how they are configured. The best systems I have used trigger automatic reassessment prompts based on triggers like ICU transfer, post-operative status, or a weight change greater than ten percent. The worst systems add another checkbox to an already overloaded workflow and nobody pays attention to the alerts because they fire too frequently to be meaningful. Here is what actually works in practice. Integrate the assessment into existing admission and daily rounding workflows rather than treating it as a separate task. Assign a specific person accountable for the timing, not just the completion. Audit a random sample of assessments weekly to catch drift. Track whether risk scores correlate with actual ulcer development in your population, because if your facility's conversion rate is high relative to your risk identification rate, your assessment timing or quality is likely the bottleneck.
When the Tool Fails Completely
I want to be blunt about a scenario where formal risk assessment tools break down: patients with existing wounds at the time of admission. The Braden Scale is designed to predict new ulcer development, not to assess the progression of an existing one. A patient admitted with a Stage 3 sacral ulcer can still receive a low-risk Braden score because the tool doesn't factor in wound presence. Using the score to justify downgrading wound care intensity in that situation is a serious error. The fix is to treat wound assessment and pressure injury risk assessment as parallel but separate processes. Document the wound staging independently. Use the risk tool for prediction and prevention planning. Do not let a deceptively low risk score reduce the intensity of wound management for an existing injury. Malnourished patients present a similar edge case. Serum albumin isn't part of the Braden Scale despite strong evidence linking hypoalbuminemia to impaired wound healing. I have seen patients with albumin below three grams per deciliter receive appropriate risk-level interventions and still deteriorate because the tool simply doesn't capture that metabolic risk. In those cases, I recommend supplementing the standard assessment with a dedicated nutrition risk screen like the MST or NRS-2002 and treating the combined clinical picture rather than relying on the tool in isolation.

The reality of pressure ulcer risk assessment is that it is a useful screening instrument with well-defined limitations. Follow the frequency guidelines, train your staff on consistent scoring, build in automatic triggers for reassessment, and never let a numerical score override direct clinical observation. The tools inform decisions. They don't replace them.