What You Actually Need on a Diabetic Foot Exam Form
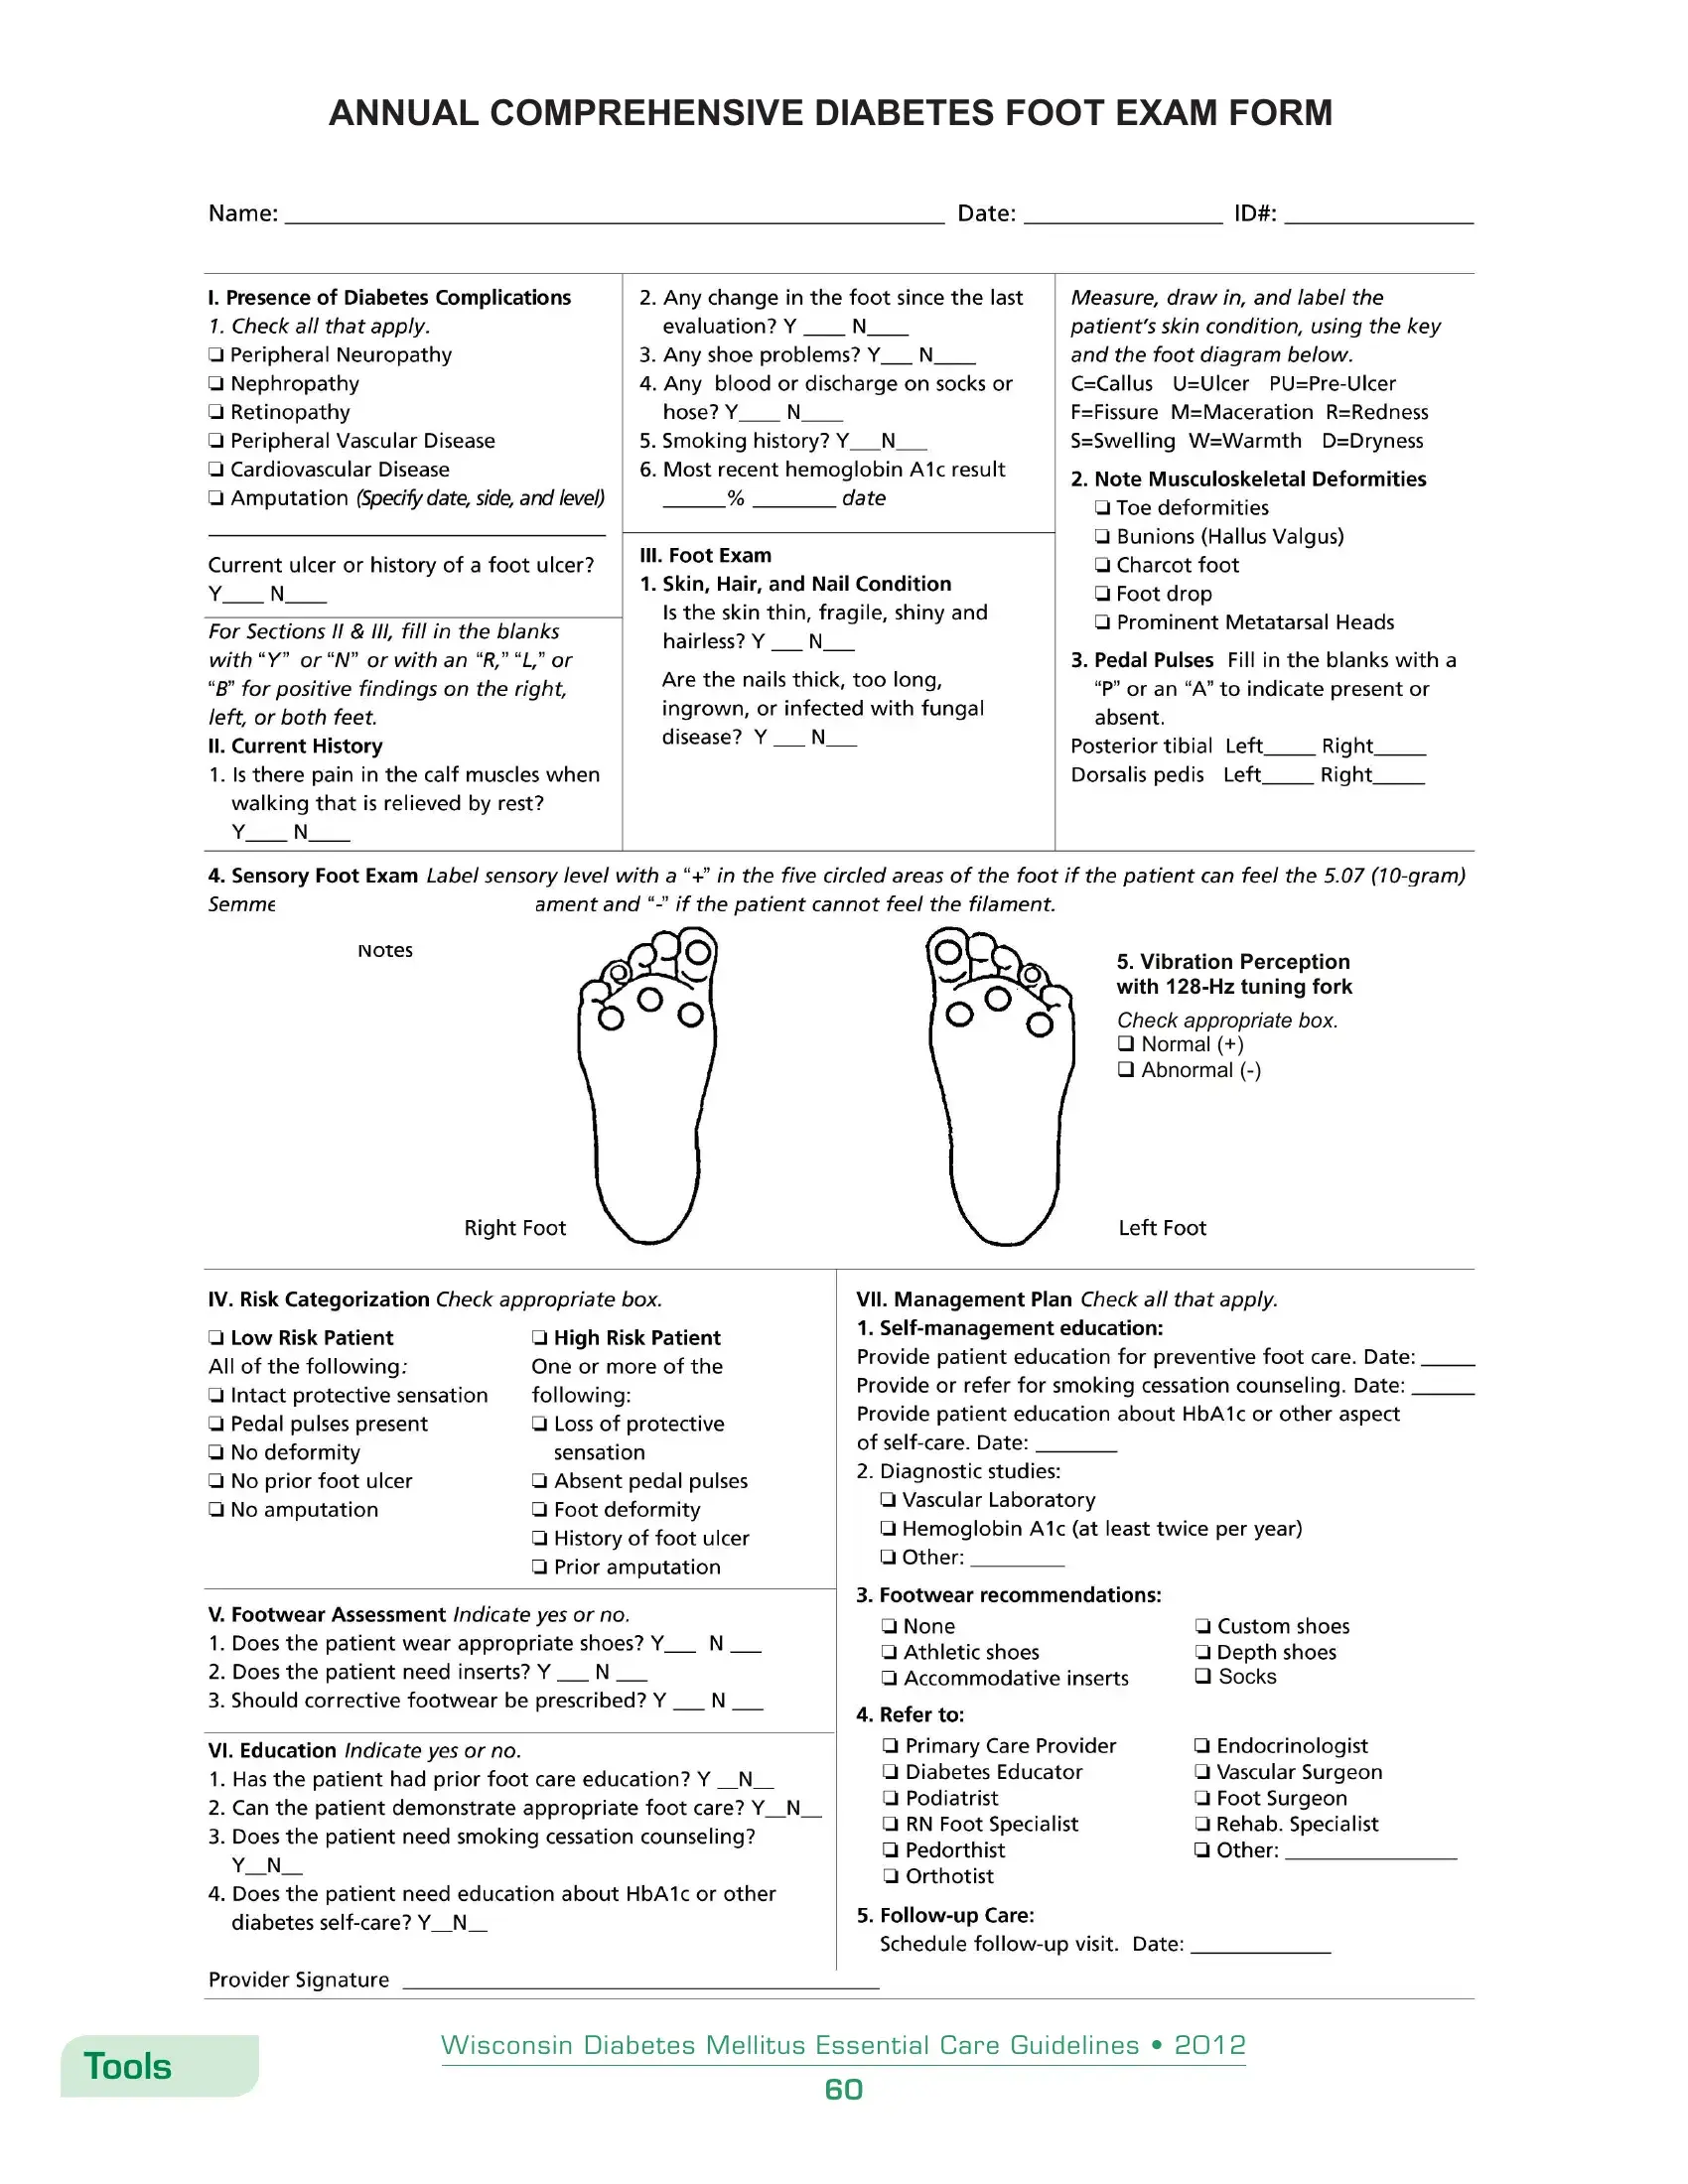
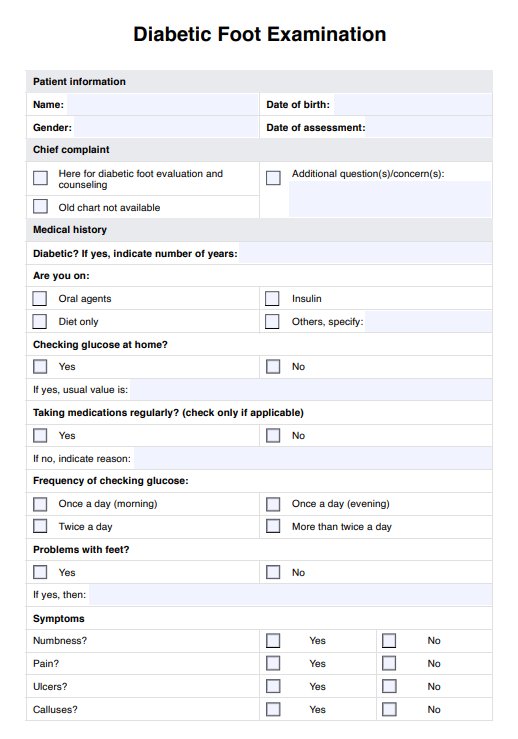
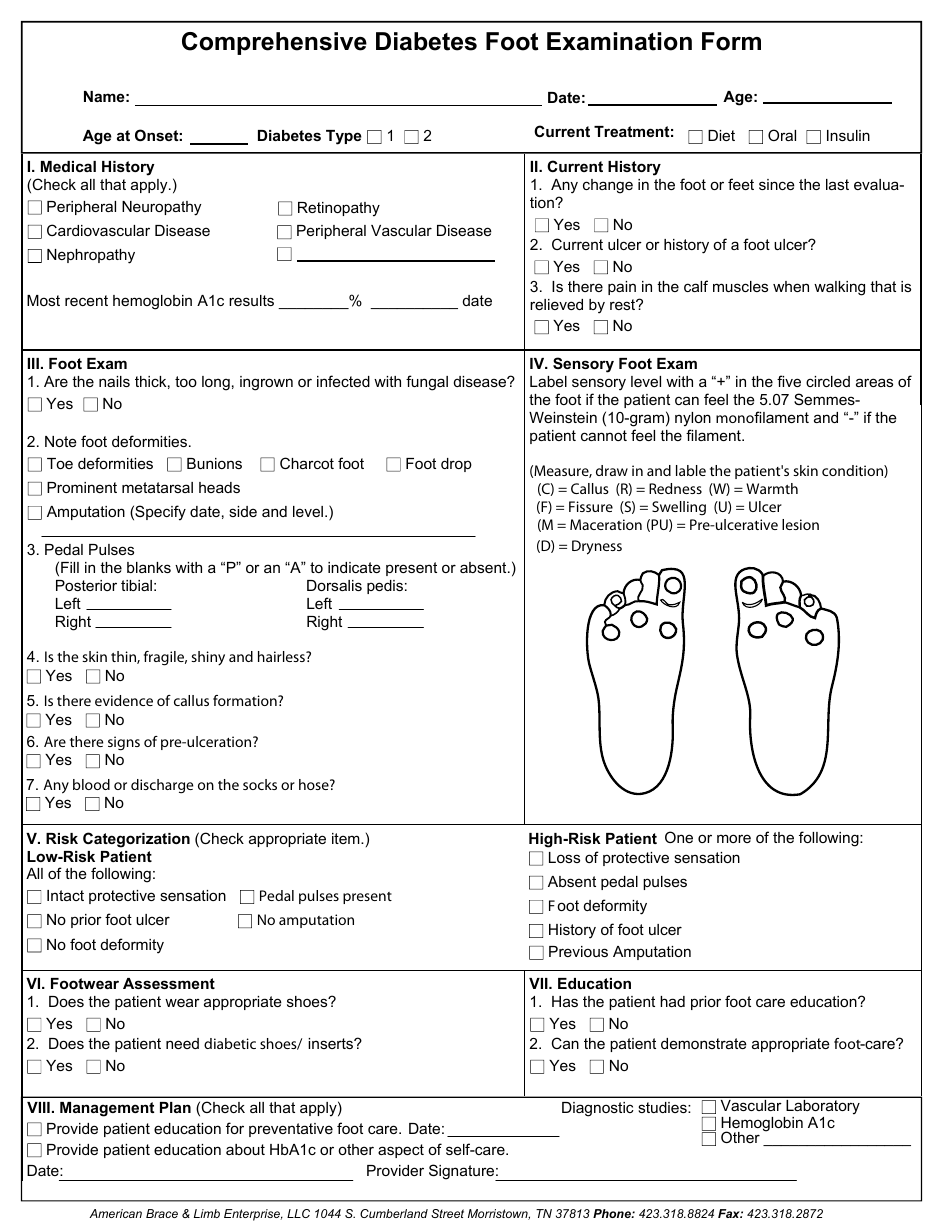
A printable diabetic foot exam form is just a structured checklist that captures the key elements of a lower-extremity assessment in diabetes. You're documenting pulses, sensation, skin integrity, nail condition, deformities, and footwear status so that future visits can show progression or decline. The form itself isn't the clinical work. It's the memory aid and the billing requirement. I pull mine from the American Diabetes Association's Standards of Care supplementary materials and from state nursing board template libraries. Those are the most commonly accepted formats in outpatient settings. A few clinics also use a modified version of the IWGDF screening form when they see high-risk patients. The one I settled on after three years of switching between vendors is the ADA-recommended annual foot exam template because it breaks out monofilament testing at eight specific plantar sites, which is what most payers want to see documented. You can download it directly from the ADA website's resource section, or search for Printable Diabetic Foot Exam Form from the CDC clinician resources page, which links to a PDF you can print double-sided without losing the legend on page two. Here's the process I use now, and it takes about four minutes per patient once you have the workflow dialed in. Start with inspection while the patient is seated. Note calluses, ulcers, amputation sites, and any obvious deformities like Charcot changes or hammertoes. Then move to vascular assessment. Palpate dorsalis pedis and posterior tibial pulses on both feet. If pulses are absent, document that and note whether you used Doppler. Then sensation. Use a 10-gram monofilament on the plantar surface of the big toe, first metatarsal head, fifth metatarsal head, and mid-sole on each foot. That's six sites per foot, twelve total. Press until the filament buckles, hold for one second, ask the patient to close their eyes and say where they felt it. Any missed site gets flagged.
Vibration testing comes next if you have a 128-Hz tuning fork. Strike it and place it on the bony prominence of the big toe. Ask the patient when the vibration starts and stops. Then range of motion and foot structure. Finally footwear counseling. Document what the patient wears daily and whether it has adequate coverage and fit. One thing most people skip and shouldn't: interdigital space inspection. I ran into a case where a patient had an untreated tinea pedis infection between the fourth and fifth toes that had progressed to a small fissure. The standard eight-point monofilament sites missed it entirely. Since then I always split the toes and look at each web space before closing the exam. It adds thirty seconds and caught three fungal infections and two early interdigital ulcers in six months.
Pitfalls That Will Get You in Trouble
The biggest issue I see is incomplete documentation of the monofilament test. Writing "sensation intact" without recording which sites were tested and which were missed is not defensible. Payers and auditors want to see the actual site results. If a patient cannot feel the monofilament at two or more sites, that's peripheral neuropathy and the risk categorization changes immediately. Document it as such. Don't gloss over it. Another common failure point is pulse documentation. "Pulses present" is too vague. Write "DP and PT 2+ bilaterally" or "DP absent bilaterally, PT 1+ with Doppler." The difference matters when you're referring someone for vascular studies or justifying a diabetic foot shoe prescription. I also learned the hard way that printing these forms on standard 8.5 by 11 paper creates a readability problem if you're handwriting in small clinic charts. The monofilament site grid gets cramped and your writing becomes illegible within a week. I switched to legal-size paper for the form and kept a separate quick-reference card with the twelve testing sites taped to my exam table. That reduced charting errors by about half and cut the time spent rewriting illegible entries.
Get the Full Details
When the Form Doesn't Cover What You Need
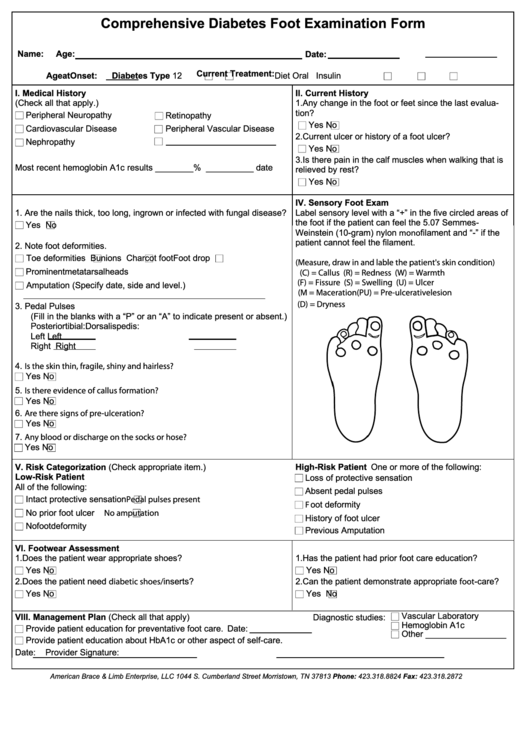
The standard printable forms are built for annual screening and basic risk stratification. They don't handle acute presentations well. If a patient comes in with a new ulcer, a possible infection, or signs of acute Charcot, you need more than the screening template. In those cases I supplement the form with a wound assessment sheet that tracks ulcer location using a foot diagram, measurements in centimeters, wound bed characteristics, exudate level, and perimeter. I also add a Wagner or University of Texas staging notation. The printable exam form alone won't capture that depth and trying to force it into the same box creates messy documentation that doesn't hold up under review. There's also the issue of digital adoption. Some health systems have moved to EHR templates that auto-populate parts of the foot exam. In those environments a printable form becomes redundant unless you're doing a quick reference copy for the patient or a paper backup for clinic visits without tablet access. I keep three printed copies in my supply cabinet specifically for those moments when the EHR is slow or the patient's device battery dies mid-visit.
What to Do With the Completed Form
File it in the patient's chart immediately. Don't stack it on a desk for later. I've lost count of how many completed forms ended up misplaced because they were set aside. Scan it into the EHR if your system allows, then file the original. Document the risk category based on the findings. No neuropathy and no deformity plus normal pulses is low risk. Neuropathy alone, or deformity alone, is moderate risk. Both neuropathy and deformity, or prior amputation, or PAD with any of the above, moves the patient to high risk and triggers more frequent follow-up and possible referral. That risk categorization should be visible in the problem list, not buried in a scanned PDF nobody checks. If you're prescribing therapeutic footwear, the completed form is your supporting documentation. Medicare requires documented peripheral neuropathy with evidence of loss of protective sensation, which means at least one missed monofilament site, plus either foot deformity or history of ulceration or amputation. Without that form in the chart, the DME claim gets denied every time. I've seen this happen repeatedly across different practices. The form isn't paperwork. It's the difference between a paid claim and a rejected one.