Getting Progesterone Therapy Right When Your Periods Start Acting Weird
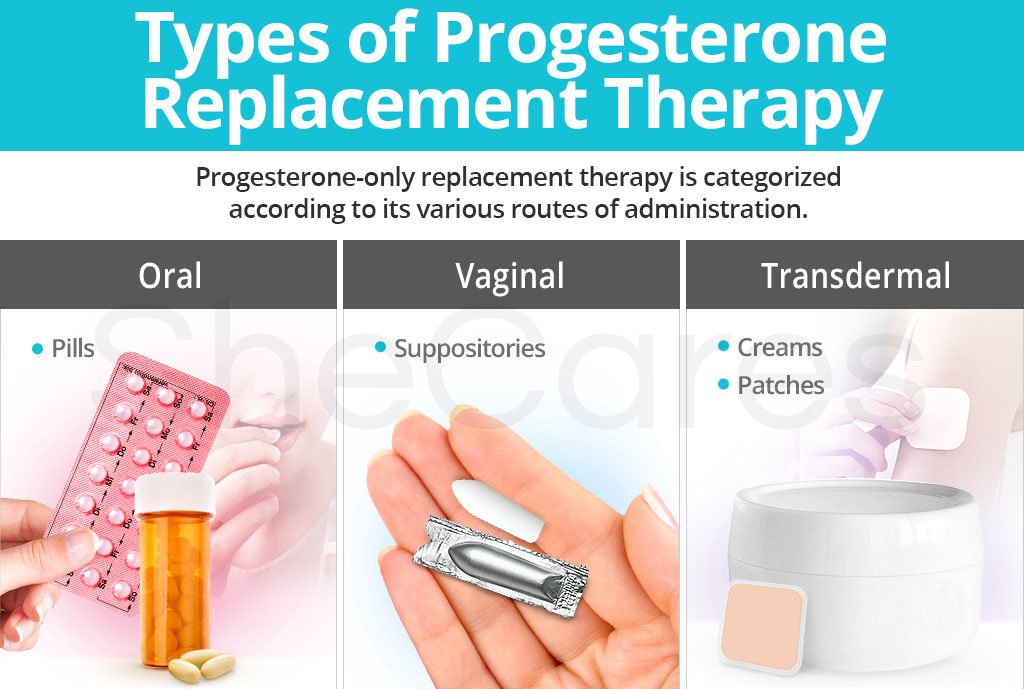
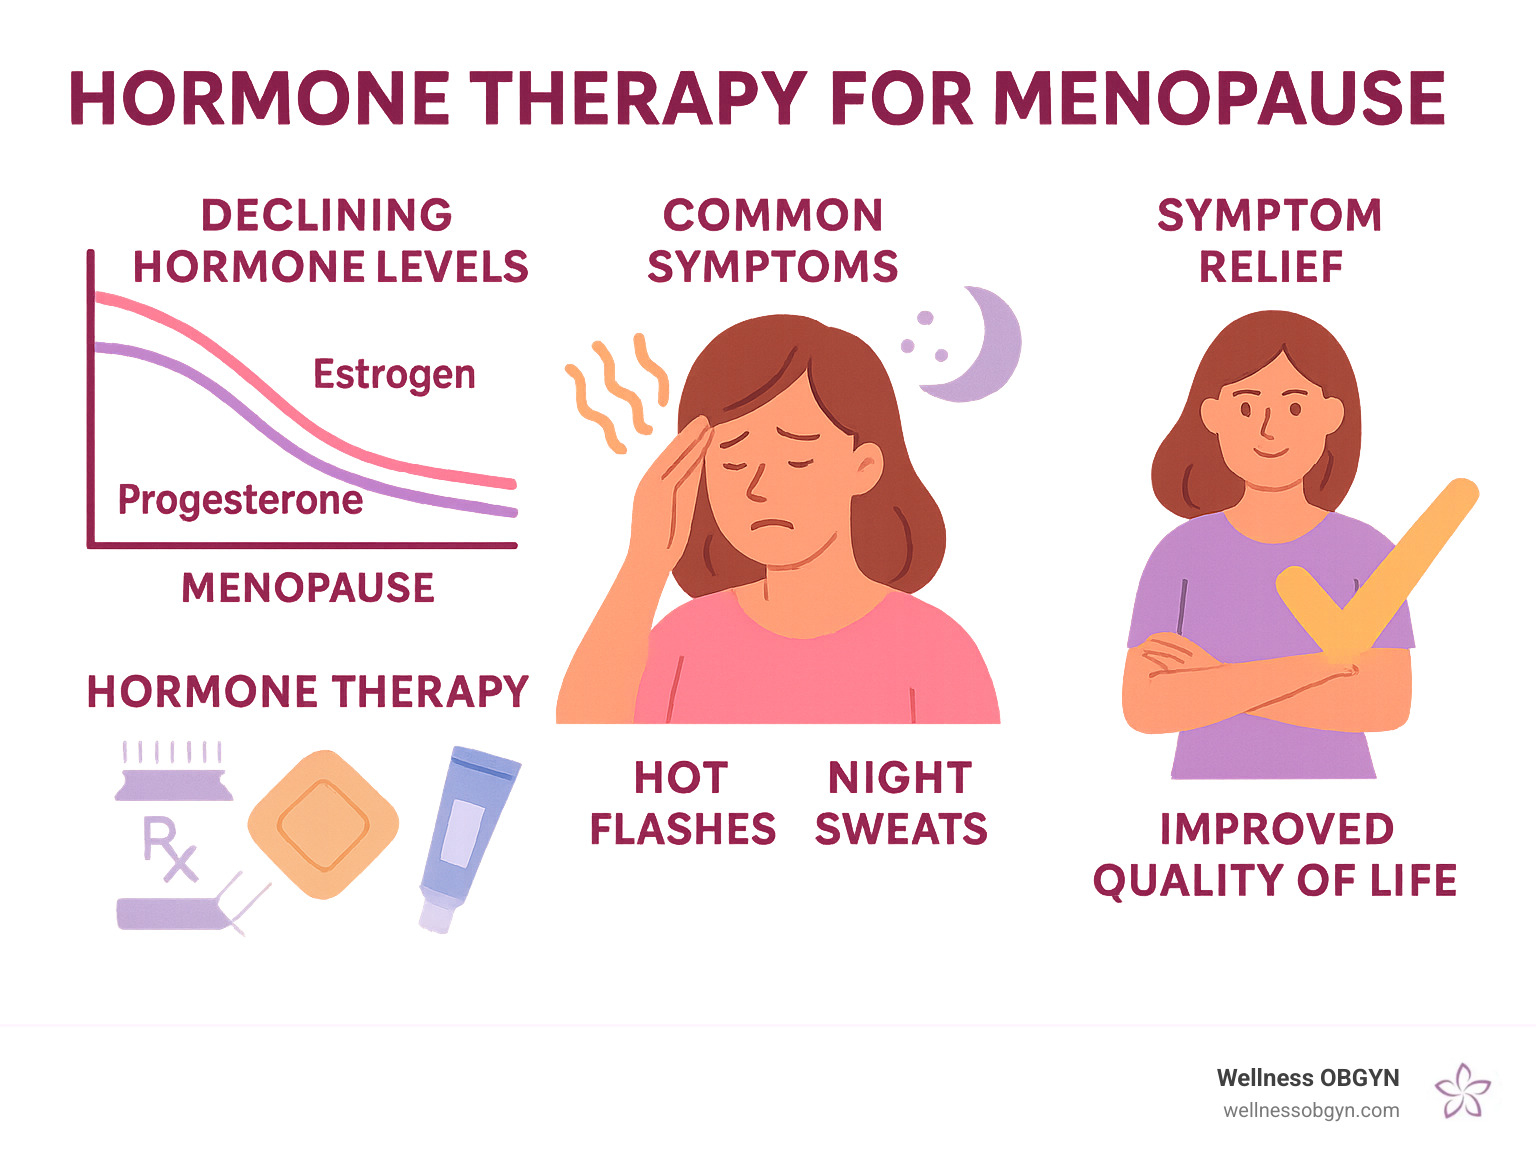
Perimenopause hits differently for everyone, but the cycle chaos is almost universal. Heavy bleeding, skipped periods, then two in one month. The progesterone drops first, usually, while estrogen stays stubbornly high. That imbalance is what causes the thickening of the uterine lining and all the symptoms that come with it. Progesterone therapy is basically replacing what your body stopped making consistently. There are a few delivery methods, and they matter more than people realize. Micronized progesterone in capsule form (the brand name is Prometrium, though generics exist) is taken orally, usually 100 to 200 milligrams daily, often at night because it makes some people drowsy. This is bioidentical, meaning it's molecularly identical to the progesterone your ovaries used to make. Then there are topical creams, which a lot of practitioners swear by, though dosing them accurately is honestly a mess. The skin absorption rate varies wildly depending on where you apply it, how much lotion you mix it with, and whether you just took a shower. I've seen patients who thought they were on a steady dose when they were really bouncing between adequate and deficient levels just because they rotated application sites randomly. Vaginal suppositories or creams are another route, mostly used for local symptom relief like vaginal atrophy, but they do get absorbed systemically to some degree. And then there are the prescription hormonal IUDs like Mirena, which release levonorgestrel directly into the uterus. That's progestin, not progesterone, and it's a whole different compound, but it's often the go-to for heavy bleeding because it thins the lining right where it matters most.
The Practical Side Nobody Talks About
Timing is everything with oral micronized progesterone. If your cycles are still happening but completely irregular, the standard approach is taking it for 10 to 14 days out of every month, starting on day 16 or 17 of your cycle and going through day 30. The problem is, a lot of perimenopausal women don't have a cycle to count from anymore. You might go 40 days without bleeding, then have a episode that lasts two weeks. In those cases, some clinicians recommend daily progesterone instead of cyclical, so you're not trying to reverse-engineer a period that may never come. It's a judgment call, and it depends on your endometrial thickness and bleeding pattern. I had a patient once who was on cyclical progesterone and kept getting breakthrough bleeding in the middle of her pill-free week. She was frustrated and ready to quit. Turns out her progesterone level was crashing too fast between doses because she was metabolizing it quickly. We switched her to split dosing — 100 milligrams in the morning and 100 at night instead of one big dose at bedtime. The bleeding stopped almost immediately. It's a small tweak that most guidelines don't highlight, but it matters.
What to Watch Out For
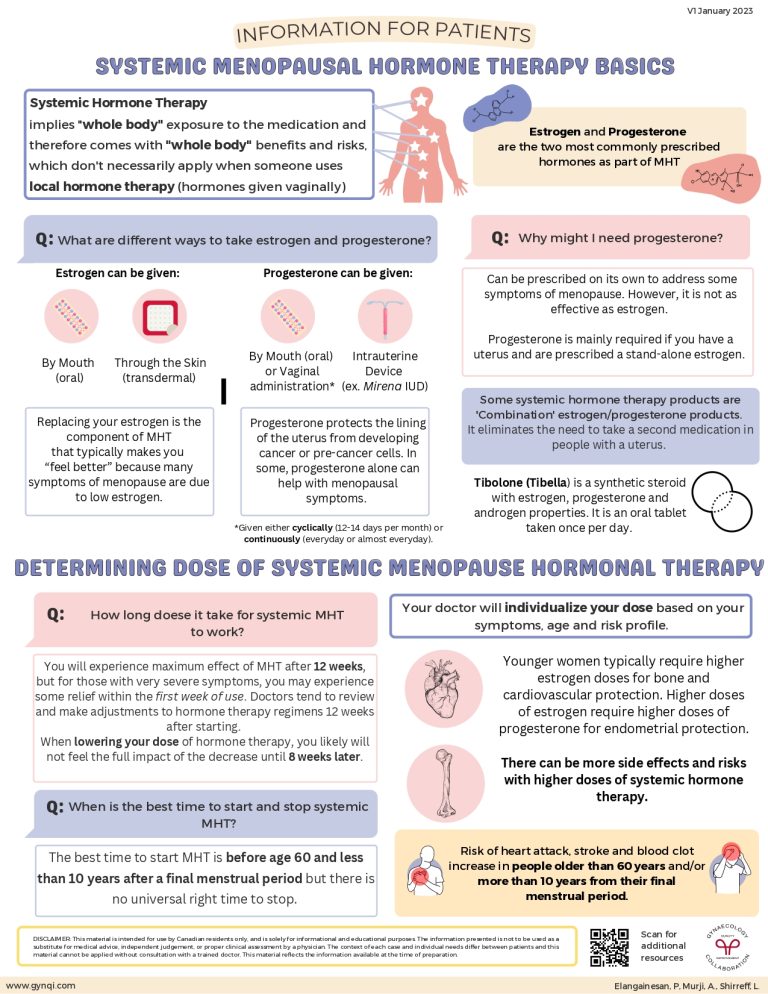
Drowsiness is the big one with oral micronized progesterone. It's not a side effect you can really ride out for most people. Taking it at bedtime helps, but if you're sensitive, even that might not cut it. Some patients report vivid dreams or nightmare activity, which sounds silly to mention but actually affects quality of life significantly. Mood changes are less common with bioidentical progesterone than with synthetic progestins, but they still happen. If you notice increased anxiety or low mood after starting, it's worth discussing a switch rather than just pushing through. There's also the issue of unopposed estrogen. If you still have your uterus and you're taking estrogen replacement without adequate progesterone coverage, you're increasing your risk of endometrial hyperplasia. That's not a scare tactic, it's basic physiology. The progesterone's job in this scenario is to shed and protect the lining. Missing that protection is how cancers start. Even if you're not on estrogen therapy, if your progesterone is chronically low and your estrogen is relatively high, you're still dealing with unopposed estrogen exposure.
Get the Full Details

How to Actually Get Started
You need blood work before anything else. A basic panel should include estradiol, progesterone (drawn on day 21 of a regular cycle or randomly if cycles are irregular), FSH, LH, and thyroid function. AMH can be useful too, though it's more about ovarian reserve than current hormone balance. Ask your doctor specifically about checking a progesterone level and an endometrial biopsy if you've had any abnormal bleeding. Abnormal bleeding in perimenopause is common, but it's also the number one red flag for endometrial pathology. Don't skip that step. If you're looking for a compounding pharmacy that makes progesterone cream, that's an option, but be aware that the FDA has issued warnings about compounded bioidentical hormones. The concern isn't that they don't work, it's that the dosing can be inconsistent and there's less regulatory oversight. Micronized progesterone capsules from a mainstream pharmacy are actually the more studied and reliably dosed option, despite what some alternative medicine sites claim.
When It Doesn't Work
Sometimes progesterone therapy just isn't enough. If you have fibroids, adenomyosis, or polyps causing the bleeding, no amount of progesterone is going to fix the underlying structural issue. The IUD might help with bleeding control even in those cases, but you'd still need the structural problem addressed separately. If you're going through menopause already and only taking estrogen, progesterone is non-negotiable if you have a uterus. There's no workaround for that. If you've had a hysterectomy, then progesterone is purely for symptom management — sleep, mood, bone health — and the conversation changes entirely. The other limitation is that progesterone doesn't address hot flashes directly. It can help with sleep disruption secondary to night sweats, but the vasomotor symptoms themselves respond better to estrogen, SSRIs, or newer medications like fezolinetant. Don't expect progesterone to be a one-size-fits-all solution for perimenopause. It's targeted, and it's powerful for what it targets, but it's not magic.