Writing Psychological Reports Without Losing Your Mind
I spent eight years in private practice before I realized I was spending more time formatting documents than actually doing therapy. Every diagnostic report, every insurance authorization note, every treatment summary followed some variation of the same structure. The problem wasn't the content. It was the repetitive mechanical work of assembling DSM criteria, billing codes, and progress narratives into something that looked professional. That's when I started experimenting with what I now call Psychological Report Writing Assistant Software — tools designed to reduce the friction between clinical observation and finished document. Some of these solutions are built into larger EHR platforms. Others are standalone programs you buy separately. A few are built on top of LLM APIs, which creates its own set of problems I'll get to.
What Psychological Report Writing Assistant Software Actually Does
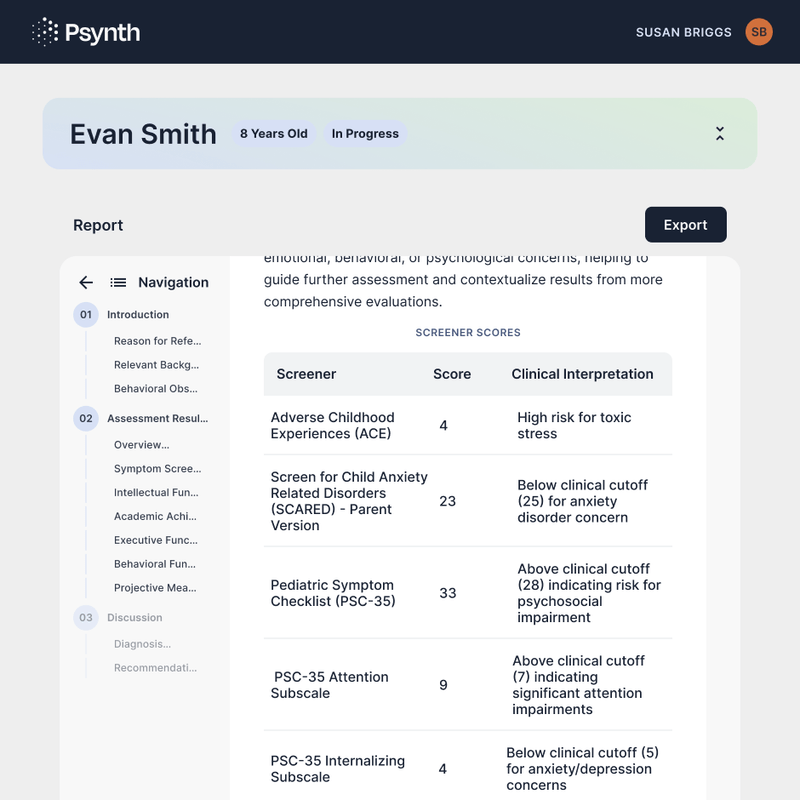
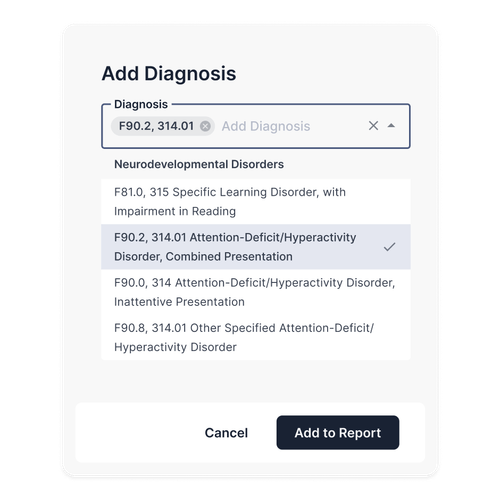
At the basic level, these tools automate the structural elements of clinical documentation. They fill in standard headers, apply DSM-5-TR codes to diagnostic statements, format progress notes according to SOAP or DAP conventions, and suggest language that meets insurance documentation standards. More sophisticated versions can cross-reference your clinical notes against billing requirements to flag potential compliance gaps before you submit a claim. The core value proposition is time savings. In my experience, a well-implemented writing assistant can reduce a 45-minute intake assessment write-up to about 12 minutes, depending on how thorough your source notes are and what template you're working from. That's not dramatic — it's just what happens when you stop manually typing the same diagnostic criteria and start using structured fields instead.
How I Actually Use These Tools in Practice
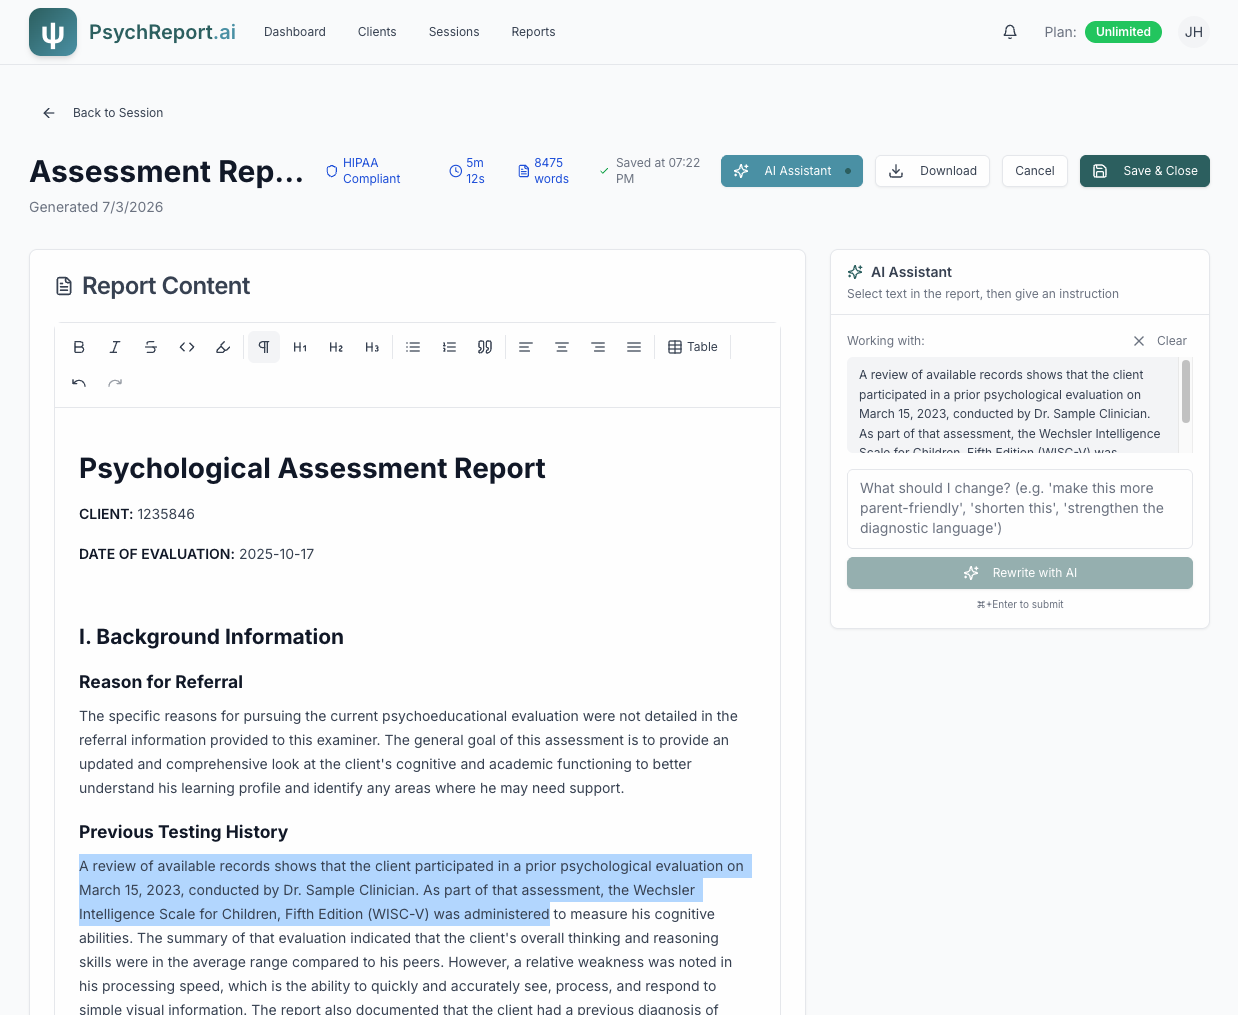
Here's the workflow that works for me. I draft my clinical observations in a plain text editor or directly in my EHR's note field. Then I run the content through a writing assistant that maps my language to standard clinical terminology, suggests appropriate DSM codes based on symptom descriptions, and reformats everything into the required document structure. Finally, I review the output, catch any inaccuracies or overgeneralizations the assistant made, and sign off. The review step is non-negotiable. I've seen too many clinicians blindly accept AI-generated diagnostic language and end up with reports that describe patients as "exhibiting pervasive sadness" when the actual clinical picture involved acute stress reactions with dissociative features. The tool doesn't understand nuance. You do. That's why the recommendation I always give is: use these assistants for structure and formatting, never for clinical judgment.
Get the Full Details
Common Pitfalls and What to Watch For
The biggest issue I encounter is over-reliance on template language. When every report sounds the same, insurance reviewers become desensitized, and you lose the ability to differentiate cases that genuinely require distinct documentation. I had a situation last year where two clients with similar surface-level anxiety presentations got flagged for unnecessary prior authorizations because their reports used identical phrasing patterns from the same writing assistant template. I had to go back and manually rewrite both assessments with client-specific language to get the referrals approved. Another problem is the HIPAA question. Some of these tools process your clinical content through third-party servers, usually under the guise of "cloud-based computation." If you're handling protected health information, you need a Business Associate Agreement before you upload anything. I learned this the hard way when I accidentally tested a free writing assistant on some de-identified case notes and later discovered the vendor's privacy policy allowed them to retain training data from uploaded documents. That's a violation I can't afford. I switched to self-hosted or on-premise solutions after that, even though they're less convenient.
Which Tools Actually Hold Up
TheraNest and TherapyNotes have built-in report writing features that are decent for small practice workflows. They're not fancy, but they handle the basic SOAP note formatting and insurance code mapping without requiring you to leave your EHR. For more advanced needs, I've had mixed results with standalone tools like DocuClinic and PsychWriter. Some features work well, others feel rushed and need manual correction. The LLM-powered options like Claude-integrated clinical note assistants are promising but create compliance headaches because you're sending PHI through a general-purpose API unless you've negotiated a BAA directly with the vendor. If you're working in a hospital or large clinic setting, your options are different. Most enterprise EHR systems include report generation modules, though they tend to be clunky and require IT support to customize. I recommend asking your vendor about available writing assistant integrations before you commit to any standalone purchase. Sometimes the built-in solution is adequate, and buying separate software just creates data silos between your charting and your report writing workflows.
The Realistic Timeline Expectation
Setting up a writing assistant workflow usually takes one to three days depending on your practice size and how many template variations you maintain. Training staff takes longer — about a week of supervised practice before they stop blindly accepting AI-generated language. The ongoing maintenance cost is minimal, mostly just keeping your template library updated as DSM criteria change or billing requirements shift. Most vendors don't charge separately for writing assistant features; they bundle them into subscription tiers that range from $50 to $200 per month depending on user count and advanced functionality. There are scenarios where these tools completely fail. Complex forensic evaluations, multi-system diagnostic assessments, and cases involving rare disorders often require custom narrative structures that no template can handle adequately. I've had situations where the writing assistant kept suggesting standard anxiety protocols for clients with complex trauma presentations, creating documentation that was clinically inaccurate and potentially harmful if used for treatment planning. In those cases, I disable the assistant and write manually, then use it only for final formatting and code verification. If you're considering implementing Psychological Report Writing Assistant Software in your practice, the key is starting small. Pick one document type — intake assessments, maybe — and build your workflow around that before expanding to other report categories. Track your time savings honestly. Some practitioners report 60 percent reductions in documentation time, but that usually includes the learning curve adjustment. After three months of regular use, realistic expectations are more like 30 to 40 percent time savings, which is still meaningful when you're looking at hundreds of reports per year.