Why Most People Get the Biopsychosocial Model Wrong
The biopsychosocial model isn't a checklist. You don't fill out three boxes — biological, psychological, social — and call it a diagnosis. That happens constantly in my clinical training rotations and in peer-reviewed case studies that never make it to publication. The model is an organizing framework, not a diagnostic algorithm. When you treat it like the latter, you end up with patients who get a laundry list of contributing factors and no coherent treatment plan.
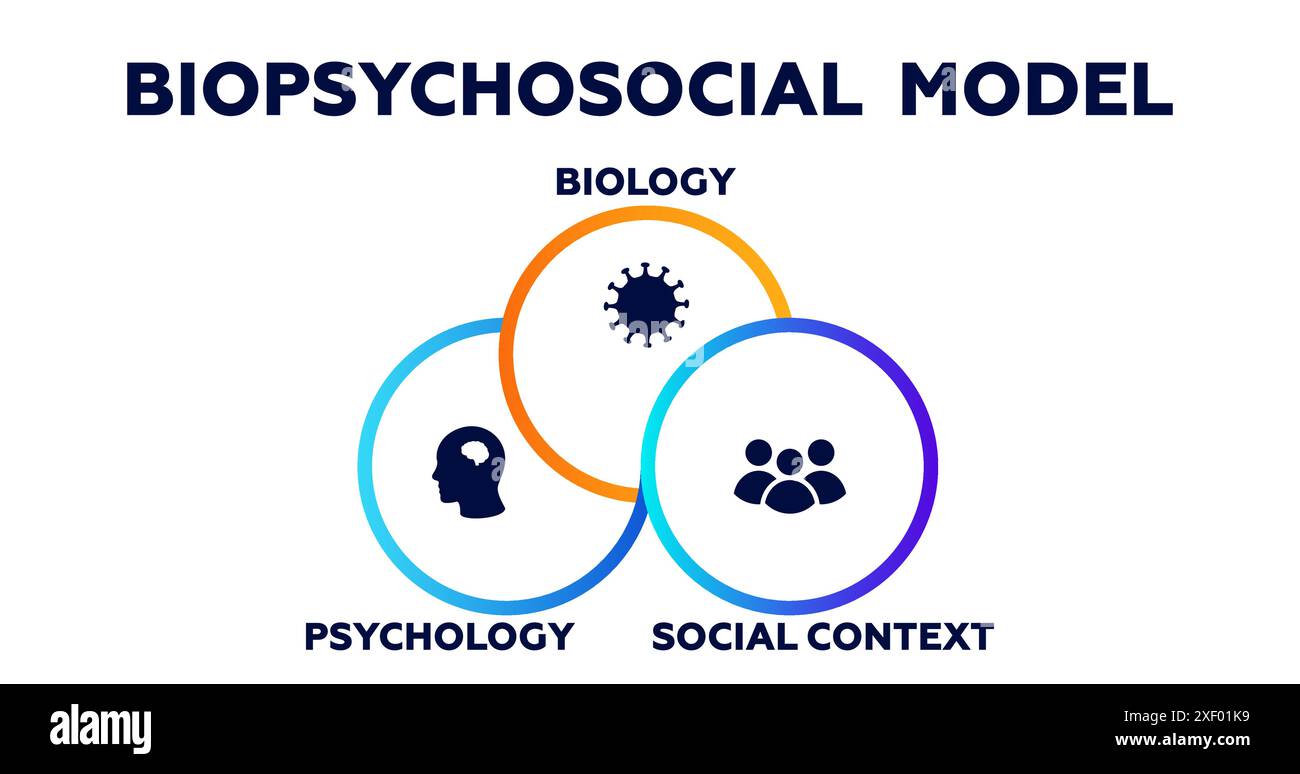
I still remember a case from my third year of practicum. A 34-year-old woman presented with treatment-resistant depression. She'd been on two SSRIs and an SNRI with minimal response. Every intake form I'd ever seen followed the same template: sleep quality, medication history, family stressors, employment status. Standard biopsychosocial screening. We identified all three domains. Thyroid panel came back normal. No family of origin trauma markers. Job was stable. The psychological assessment showed mild anxiety but nothing that explained the severity of her depression. We were stuck because we'd been looking for three separate causes instead of looking at how the domains interacted. The framework was introduced by George Engel in 1977 as a direct challenge to the dominant biomedical model of that era. Engel argued that illness and health couldn't be reduced to cellular or molecular dysfunction alone. That was already obvious to anyone who worked in general practice. You'd see patients with chronic pain, fatigue, or somatic symptoms whose labs came back completely clean. The biomedical model had no good answer for them. Engel's contribution wasn't introducing the idea that biology and environment matter — that was already assumed — but rather formalizing it as a systematic approach to clinical reasoning. At the operational level, the model has three components that overlap significantly more than most textbooks suggest.
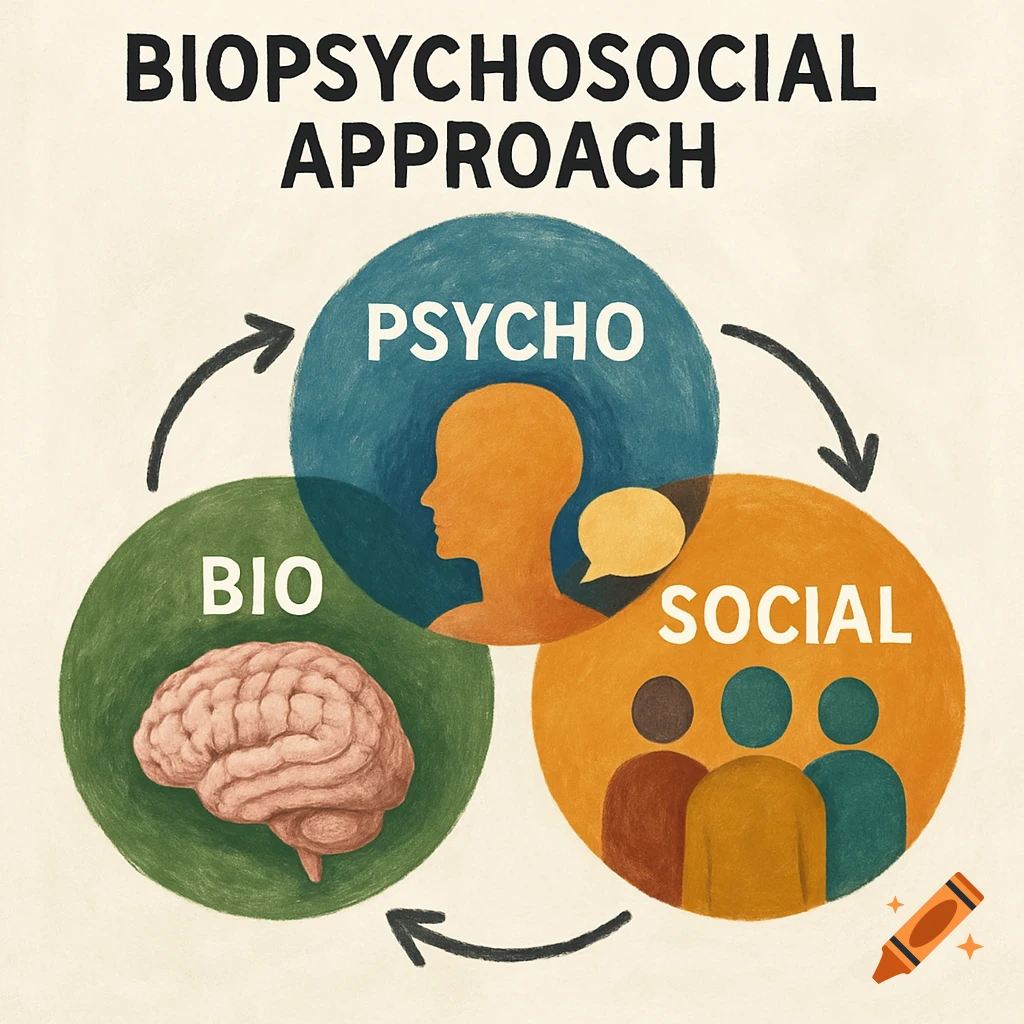
Biological encompasses genetics, neurochemistry, endocrine function, immune system activity, physiological conditions, and substance use. It also includes things that are often overlooked like gut microbiome composition, circadian rhythm disruption, and subclinical inflammation. These aren't fringe considerations anymore. There's a reason why IL-6 and CRP levels are increasingly being tracked in treatment-resistant depression protocols. Psychological covers cognitive patterns, emotional regulation capacity, personality structure, coping strategies, and mental health history. This domain includes things like learned helplessness, attachment style, and the specific ways someone interprets bodily sensations — which is clinically relevant because health anxiety and somatic symptom disorder often live at the intersection of psychological and biological factors. Social includes socioeconomic status, social support networks, cultural context, occupational environment, relationships, and systemic factors like healthcare access or discrimination. The social domain is where most clinicians underinvest time because it requires actual effort beyond filling out a standardized questionnaire.
The critical insight that most introductory courses miss is that these domains don't operate in parallel. They interact. A chronic inflammatory condition (biological) can produce depressive symptoms (psychological), which then reduces social engagement and employment participation (social), which in turn increases stress hormone output and worsens the inflammatory state (biological). This is called a vicious cycle in the literature, but in practice it's just what happens when you stop treating patients as systems and start treating them as collections of symptoms.
Get the Full Details

How to Actually Use the Model in Clinical Practice
The way most people apply this model is by generating a differential diagnosis that lists factors from each domain without establishing priority or causality. That produces a report that reads well but doesn't change treatment. The more useful application requires you to map directionality. Which domain is driving the others? Where is the point of leverage? I use a structured interview approach that takes roughly 45 minutes during the initial session. I don't use a formal biopsychosocial assessment tool because the standardized instruments tend to produce shallow data. Instead I ask specific questions designed to surface interaction patterns between domains. Here's the sequence I found works best after trying several variations over eight years. First, I establish the presenting problem in concrete terms. Not "I've been feeling down" but "I haven't been able to get out of bed before noon for six weeks and I missed three workdays last month." Specificity matters because it anchors the assessment. Vague presentations pull assessors toward vague formulations.
Second, I scan the biological domain for red flags and treatment modifiers. Sleep architecture, appetite changes, weight fluctuation, energy patterns across the day, substance use including caffeine and alcohol, current medications and supplements, family history of autoimmune or psychiatric conditions, recent infections or medical procedures, menstrual cycle regularity if applicable. This isn't a comprehensive medical workup. It's a screening pass to identify factors that could be mimicking or amplifying the primary complaint. A thyroid issue masquerading as depression is common enough that skipping this step is negligent. Third, I move to psychological factors with a focus on cognitive and behavioral patterns rather than deep personality assessment. What explanations does the person have for their condition? What coping strategies have they tried? What's their baseline resilience like before this episode? I pay particular attention to whether they're engaging in health-related rumination or avoidance, because these patterns directly influence treatment engagement and outcomes. Fourth, I assess the social context through concrete questions about daily interactions, financial stress, living situation, work environment, and cultural factors affecting help-seeking behavior. I ask who they'd call if things got worse, not because I expect a dramatic answer but because the quality and reliability of their social support network is one of the strongest predictors of treatment response across multiple conditions.
Once I've gathered this information, I spend another 15 to 20 minutes constructing a case formulation that explicitly states the hypothesized relationships between domains. This is the step that separates the model from a checklist. The formulation looks something like: primary biological vulnerability (family history of mood disorder) interacts with current psychological factor (catastrophic health anxiety following a recent viral illness) within a social context (remote work isolation reducing natural social contact), resulting in maintained behavioral avoidance that reinforces both the anxiety and the physiological dysregulation.
Where the Model Breaks Down
Let me be clear about the limitations because the literature rarely discusses them with the specificity that clinical practice demands. The biopsychosocial model provides no guidance on weighting. When biological and psychological factors are both present and potentially interacting, there's no established method for determining which should be addressed first. In practice, this decision gets made based on clinician training bias, patient preference, and insurance coverage — not on any principled framework within the model itself. I've seen good clinicians miss the biological component entirely because their training emphasized psychodynamic formulation. I've seen equally competent colleagues push pharmaceutical intervention first in cases where the primary driver was social isolation and economic precarity. Neither approach was wrong in absolute terms, but neither was particularly well-justified by the model alone. Another structural weakness is operationalization. The model doesn't specify how to measure "social factors" in a way that's clinically actionable. Socioeconomic status is easy to record. But the quality of social support, the impact of workplace culture, or the effects of microaggressions in a healthcare setting are significantly harder to assess reliably. Most clinicians end up using proxy measures like marital status or employment, which are inadequate for anything beyond the most basic formulation.
The model also struggles with acute crisis situations. If a patient presents with active suicidal ideation, the biopsychosocial assessment becomes secondary to risk management. There's nothing wrong with that priority shift, but it means the model isn't universally applicable. In emergency settings, the biomedical framework often takes over because it's faster and more immediately actionable. That doesn't make it better — it makes it pragmatically necessary. Perhaps the most important limitation is that the biopsychosocial model has been adopted so broadly that it's lost much of its original critical edge. Engel intended it as a challenge to reductionism. Today it's frequently used as a neutral-sounding way of acknowledging multiple factors without actually integrating them. A patient can receive a biopsychosocial assessment and still leave the clinic with a single-domain treatment plan. This happens because the model doesn't prescribe an integrated intervention strategy. It describes complexity without providing the tools to manage it.
A Practical Workaround I Developed
When I encountered the treatment-resistant depression case I mentioned earlier, the biopsychosocial assessment had been completed thoroughly but uselessly. All three domains were represented in the chart. Nothing was wrong with the documentation. The problem was that no one had identified the specific interaction pattern that was maintaining the condition. My workaround was to add a fourth analytic step: temporal mapping. I took the assessment data and plotted it against a timeline. What events preceded symptom onset? What patterns emerged over weeks and months? Where did changes in one domain correspond with changes in another? In that patient's case, the temporal analysis revealed something that a static biopsychosocial assessment completely missed. Her depressive episodes consistently worsened two weeks before her menstrual period, regardless of other life events. The biological domain (hormonal fluctuation) was the primary driver. The psychological and social factors were amplifiers, not causes. This insight redirected the entire treatment plan from antidepressant trials to a hormonal intervention strategy combined with CBT for the anxiety component. She responded within six weeks.

Temporal mapping takes approximately 20 additional minutes during the assessment phase. It requires basic graph paper or a simple spreadsheet. The method identifies lag effects and cyclical patterns that cross-sectional assessment formats systematically obscure. I've since applied this technique to cases involving PTSD, chronic pain, and obsessive-compulsive disorder with similar improvements in treatment accuracy. For patients where temporal mapping doesn't resolve the formulation, I sometimes supplement with a brief pilot intervention. If the biological versus psychological weighting is genuinely unclear, I'll start with a low-risk biological intervention — sleep hygiene optimization, caffeine reduction, or a basic anti-inflammatory protocol — for two to three weeks and track response. If there's no change, I pivot to the psychological domain. This isn't ideal evidence-based practice, but it's more efficient than the alternative of endless assessment without directional hypotheses.
When to Look Beyond the Biopsychosocial Model
There are clinical scenarios where the biopsychosocial framework simply isn't sufficient. Severe psychotic disorders often require primary psychiatric and pharmacological intervention where the biopsychosocial formulation, while relevant, doesn't drive the immediate treatment decisions. Neurodegenerative conditions follow different clinical pathways. Pediatric cases require developmental frameworks that go beyond the standard biopsychosocial categories. For most common clinical presentations — depression, anxiety, somatic symptom disorders, adjustment reactions, mild-to-moderate substance use — the model remains one of the most useful tools available. The trick is using it correctly. Most clinicians don't need a more sophisticated framework. They need to stop treating a heuristic model like a diagnostic manual and start using it as a thinking tool that actually generates testable hypotheses about their patients.