
Running a psychology practice isn't about hours billed. It's about whether you actually caught the things that matter.
I've been running individual and group therapy sessions for about fourteen years now. Most of that time was spent figuring out what actually prevents screw-ups versus what looks good on paper. The checklist habit didn't come from a textbook. It came from a malpractice scare and a patient who fell through the cracks because I was distracted by billing codes. A psychology checklist weekly is just a structured review routine you run once a week to audit your clinical practice. It covers liability items, documentation gaps, treatment progress, supervision needs, and administrative housekeeping. You're not trying to perfect everything. You're trying to catch the slow leaks before they become problems. Most clinicians skip this because it feels like homework. The version I use takes about forty minutes. I built it around the specific failures I'd seen in my own work and the complaints I'd received from patients and peers over the years.
What the weekly review actually covers
There are six categories. They're not exhaustive. They're the things that kept me up at night when I was younger and still figuring things out. Documentation and compliance. This is where most people get caught. You're checking that every session note from the past seven days is complete, signed, and filed. You're flagging any notes that are late, incomplete, or clearly rushed. You're also making sure consent forms, release of information documents, and any required disclosures are current. If you're seeing a new patient next week, their paperwork needs to be ready before they walk in the door. One thing nobody tells you: insurance panels don't care about your good intentions. They care about whether your documentation meets their criteria. I lost a contract with a major PPO once because my group therapy notes didn't include individual member contributions. I had to reconstruct three months of notes under time pressure. I never made that mistake again.
Clinical progress and treatment planning. Go through each active patient and ask: are we moving? If a patient has been in treatment for more than eight weeks and there's no measurable change in their target symptoms, that's a flag. It doesn't mean you failed. It means you need to adjust the treatment plan, consult with a supervisor, or discuss a referral with the patient. I used to let this slide because I thought I could tell by memory who was progressing and who wasn't. I was wrong. About a year ago, I realized I'd been seeing the same patient for six months without updating their treatment plan. When I finally pulled their records and compared the original goals to where they were now, the gap was enormous. Updating the plan took twenty minutes. Not doing it cost me credibility with that patient. Boundary and ethics check. This is the uncomfortable section. You review the past week for any boundary crossings, dual relationship concerns, or ethical dilemmas. Did you accept a small gift from a patient? Did you text a patient outside of scheduled hours? Did you cancel a session and reschedule in a way that felt convenient rather than clinically appropriate?
Get the Full Details
Most clinicians think ethics violations are dramatic. They're usually tiny. A late-night email. A Facebook friend request. A session that ran twelve minutes over because the conversation was going well. The checklist forces you to name these things instead of pretending they don't count. Scheduling and availability. Check your upcoming week. Are there gaps you should fill? Do any patients need a make-up session because of a holiday or emergency? Are there no-shows that need follow-up? This sounds administrative but it's clinically relevant. Untended scheduling issues create anxiety for patients and resentment for you. Self-care and burnout indicators. This is the part people skip. Write down how you actually felt this week. Were you angry in sessions? Detached? Exhausted? Did you look forward to seeing patients or dread it? Your emotional state is data. If you notice a pattern across multiple weeks, that's not a personal failure. That's a signal to take action.
Professional development. One thing per week. A journal article. A workshop recording. A consultation call. You don't need to complete a full continuing education unit every week. You just need to stay connected to the field. The moment you stop learning, you start practicing from fifteen years ago.
How I actually run mine
I use a simple spreadsheet with the six categories as columns and dates as rows. Every Friday afternoon, I spend forty minutes going through each category. It takes practice to be honest in the self-care section. The first few times I did this, I wrote things like "fine" and moved on. That wasn't helpful. Now I write actual observations. For the clinical progress section, I pull up each patient's file and review the last four sessions. I look at their symptom scores, their treatment goals, and any changes in diagnosis. If something doesn't add up, I add a note to discuss it with my supervisor next month. For documentation, I print out a list of all sessions from the past week and go through them line by line. I'm looking for missing signatures, incomplete assessments, and any notes that look like they were written in a hurry. This takes about fifteen minutes once you get used to it.

The ethics check is the hardest part. I force myself to write down every boundary-adjacent interaction from the week, even the tiny ones. Some weeks there are none. Some weeks there are five. Either way, writing them down makes them manageable instead of background noise.
Pitfalls to avoid
The biggest mistake I see clinicians make is treating the checklist as a compliance exercise. It's not. It's a clinical tool. If you're just checking boxes without actually reflecting on what you find, you're wasting your time. Another common error is making the checklist too long. I've seen versions that take two hours. Nobody follows those. Yours should take less than an hour. If it doesn't, you're including things that belong in a monthly or quarterly review instead. And don't skip the self-care section because you're "too busy." That's exactly when you need it most. Burnout doesn't announce itself. It accumulates.
Limitations
This system works well for solo practitioners and small groups. It breaks down if you're managing fifty active patients and don't have staff support. In that case, you need a delegated system where someone else handles the documentation audit while you focus on clinical review. It also doesn't replace supervision. If your checklist reveals ongoing ethical concerns or serious clinical stagnation, you need to bring that to a supervisor or consultant. The checklist is a detection tool, not a solution. And one more thing: if you're in a state or province with specific documentation requirements, your checklist needs to reflect those. What I use in Washington state wouldn't cover California's mandated reporter obligations or Texas's telehealth consent rules. Adapt it to your jurisdiction.
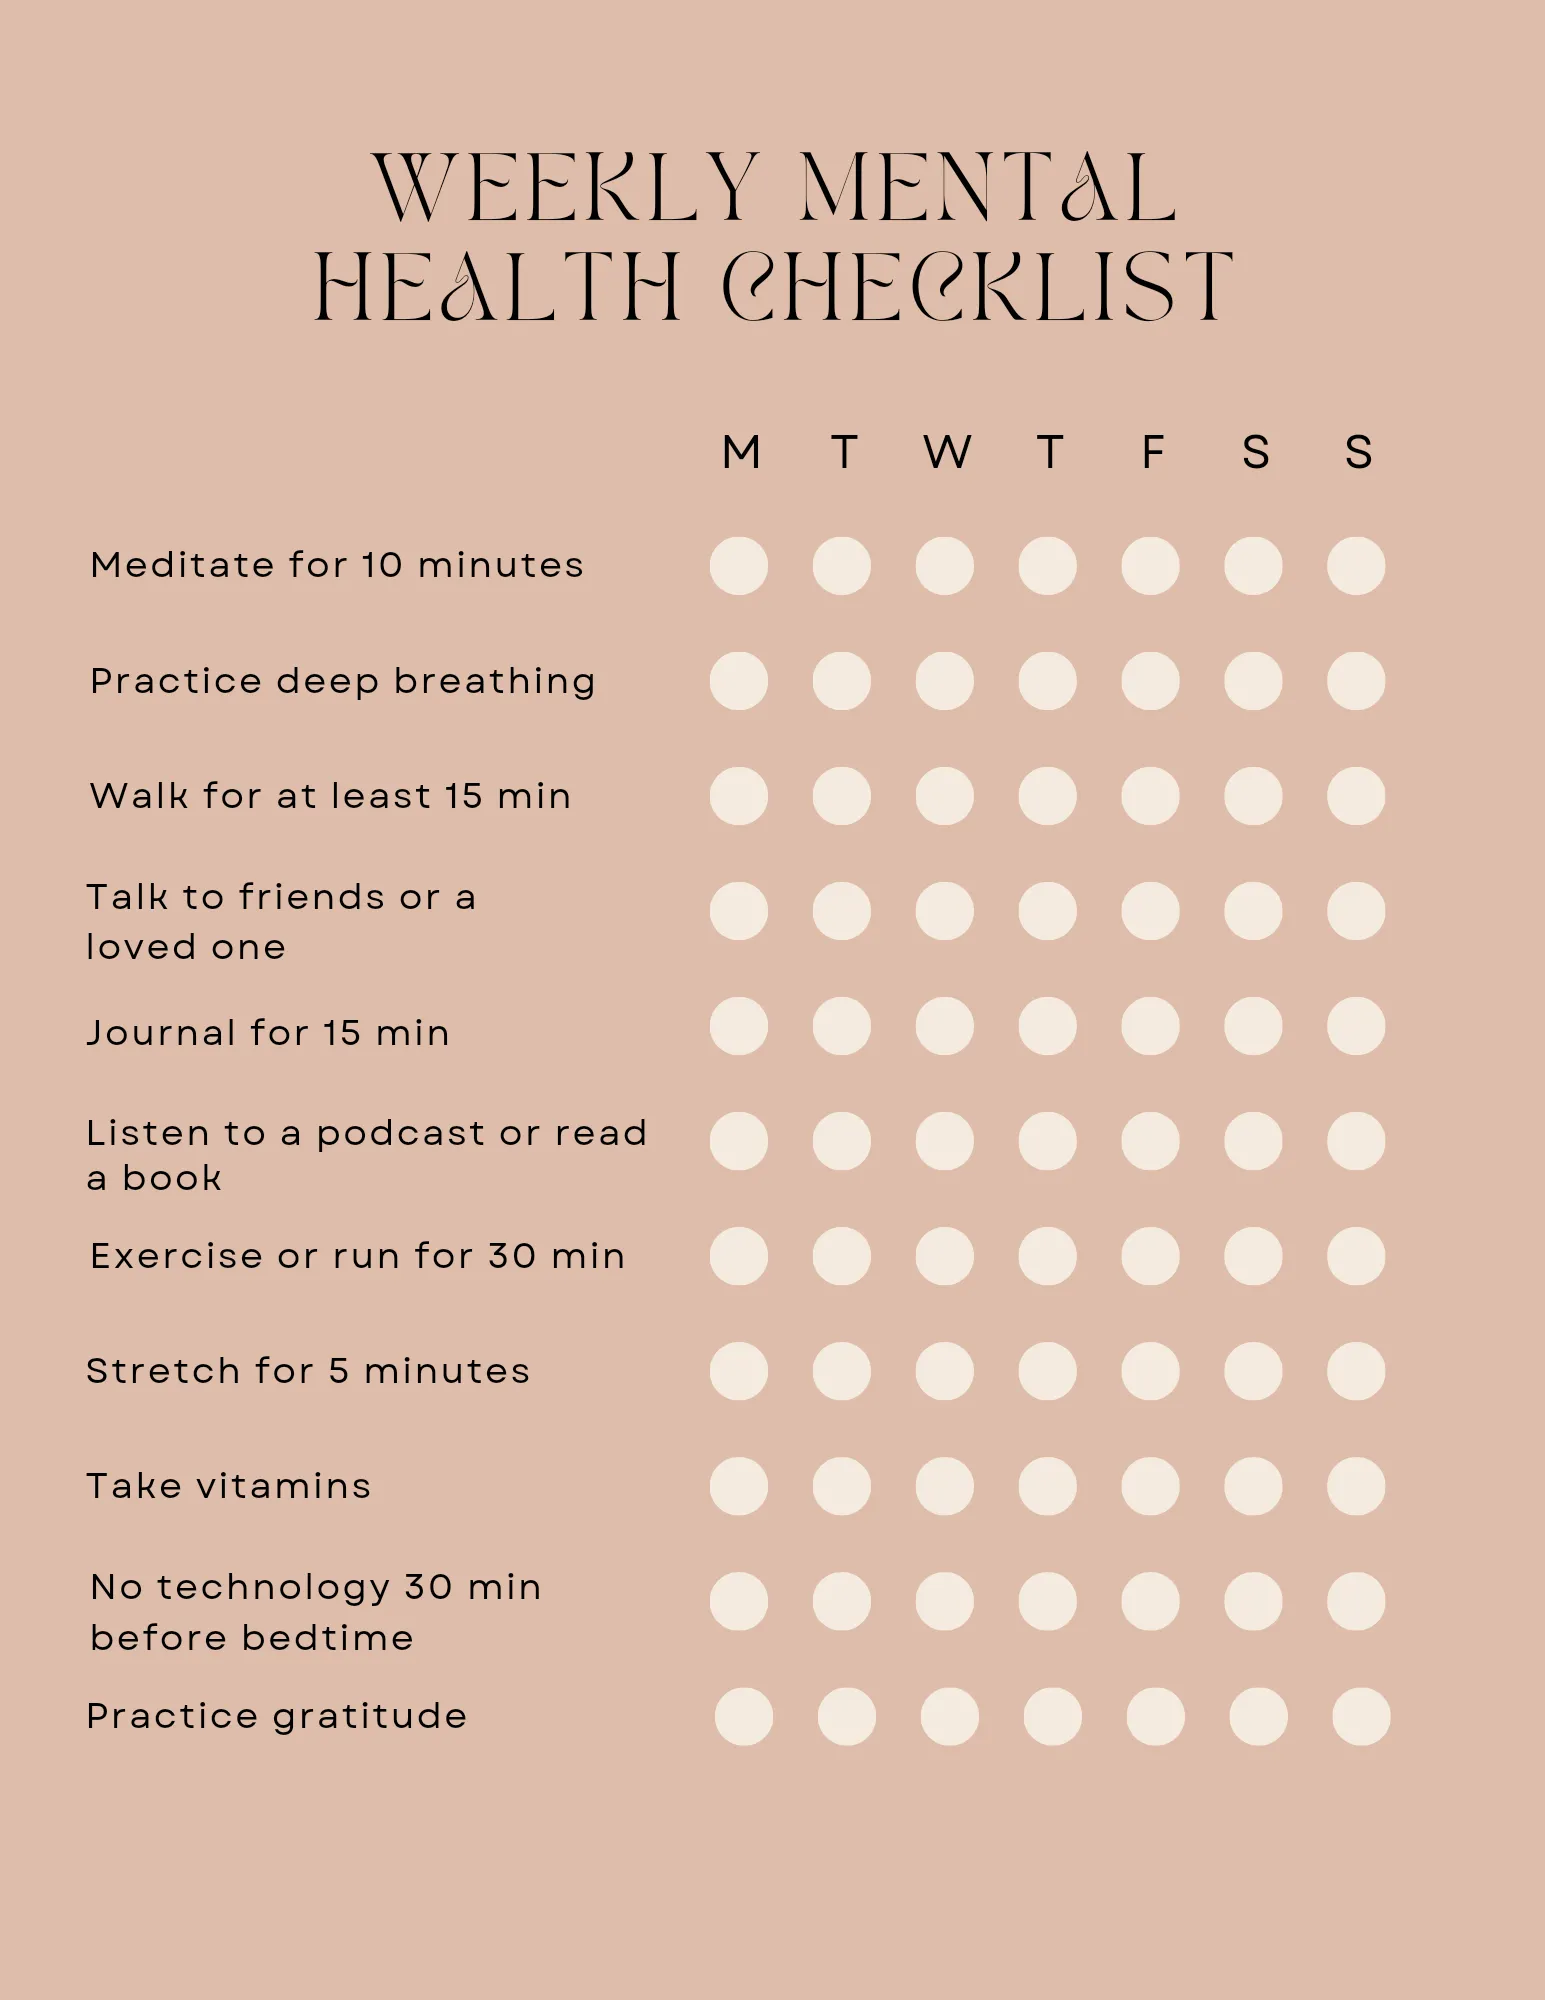
I don't have a download link for the exact spreadsheet I use. It's a Google Sheet I built incrementally over six years and it's filled with notes and reminders that would be useless to anyone else. But the structure is simple enough that you can recreate it in fifteen minutes. Six columns. One row per week. Be honest. The Psychology Checklist Weekly method isn't glamorous. It won't make you a better therapist overnight. But it will keep you from repeating the same mistakes, and it will catch problems before they become disasters. That's worth forty minutes a week.


