How QEEG Brain Mapping Actually Works in Practice
QEEG brain mapping takes raw EEG signals and turns them into color-coded topographic maps by comparing a patient's data against a normative database. The process is straightforward if you've done it enough times. You hook up the electrodes, run the acquisition, run the analysis, and get a map that someone with enough training can interpret. The real work isn't in the mapping itself. It's in understanding what the colors actually mean and, more importantly, what they don't mean.
Qeeg Brain Mapping Reviews: What People Get Wrong
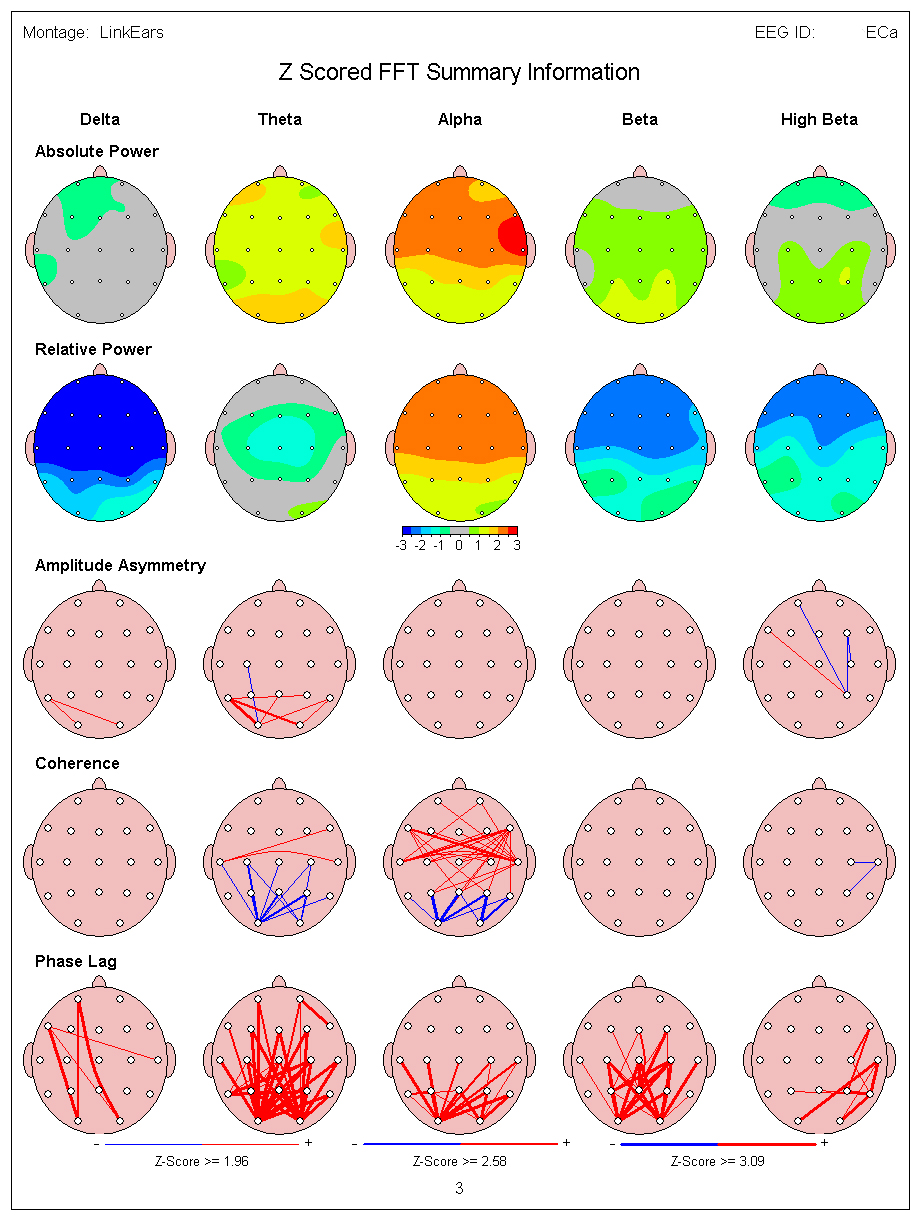
Most reviews online focus on whether the output looks pretty or whether the software is easy to use. That misses the point entirely. QEEG is a clinical tool first. If you're buying it because you saw a YouTube video with rainbow brain maps, you're going to be disappointed and potentially make mistakes. The core methodology involves recording 19 to 21 channels of EEG data, converting the signal from the time domain to the frequency domain using Fast Fourier Transform, then comparing power values at each frequency band against a normalized reference database. The standard brain map outputs show relative power, absolute power, coherence, phase lag, and asymmetry measures. Each one tells a different story. I spent about three years running QEEG assessments for a neuropsychology clinic before I really understood what I was looking at. The first six months were full of me confidently reading maps that turned out to be garbage. Not because the technology was bad, but because I didn't account for artifacts early enough in the process.
The Acquisition Problem Nobody Talks About
Good QEEG data is almost entirely dependent on clean signal acquisition. Impedance below five kilo-ohms on every channel. No muscle artifact from jaw clenching. No 60-cycle hum from bad grounding. A lot of people skip this part and blame the interpretation later. Here's a specific issue I ran into repeatedly: patients with high frontalis muscle tension will produce elevated gamma and high beta power across the frontal channels. On a power map, this looks like a genuine neurophysiological finding. It's not. It's EMG contamination. I learned to check the raw waveform first, always. If the trace looks spiky and narrow, that's muscle. Reject that epoch and move on. This alone fixed about half the "findings" my early interpretations were generating. The workaround I settled on was running a 60Hz notch filter during acquisition, then manually reviewing each epoch before committing to the average. It adds maybe eight minutes to the protocol, but it prevents you from building a map on contaminated data. That time investment pays for itself immediately if you've ever had to re-scan a patient because your results didn't match their clinical presentation.
Get the Full Details
Interpreting the Maps Without Losing Your Mind
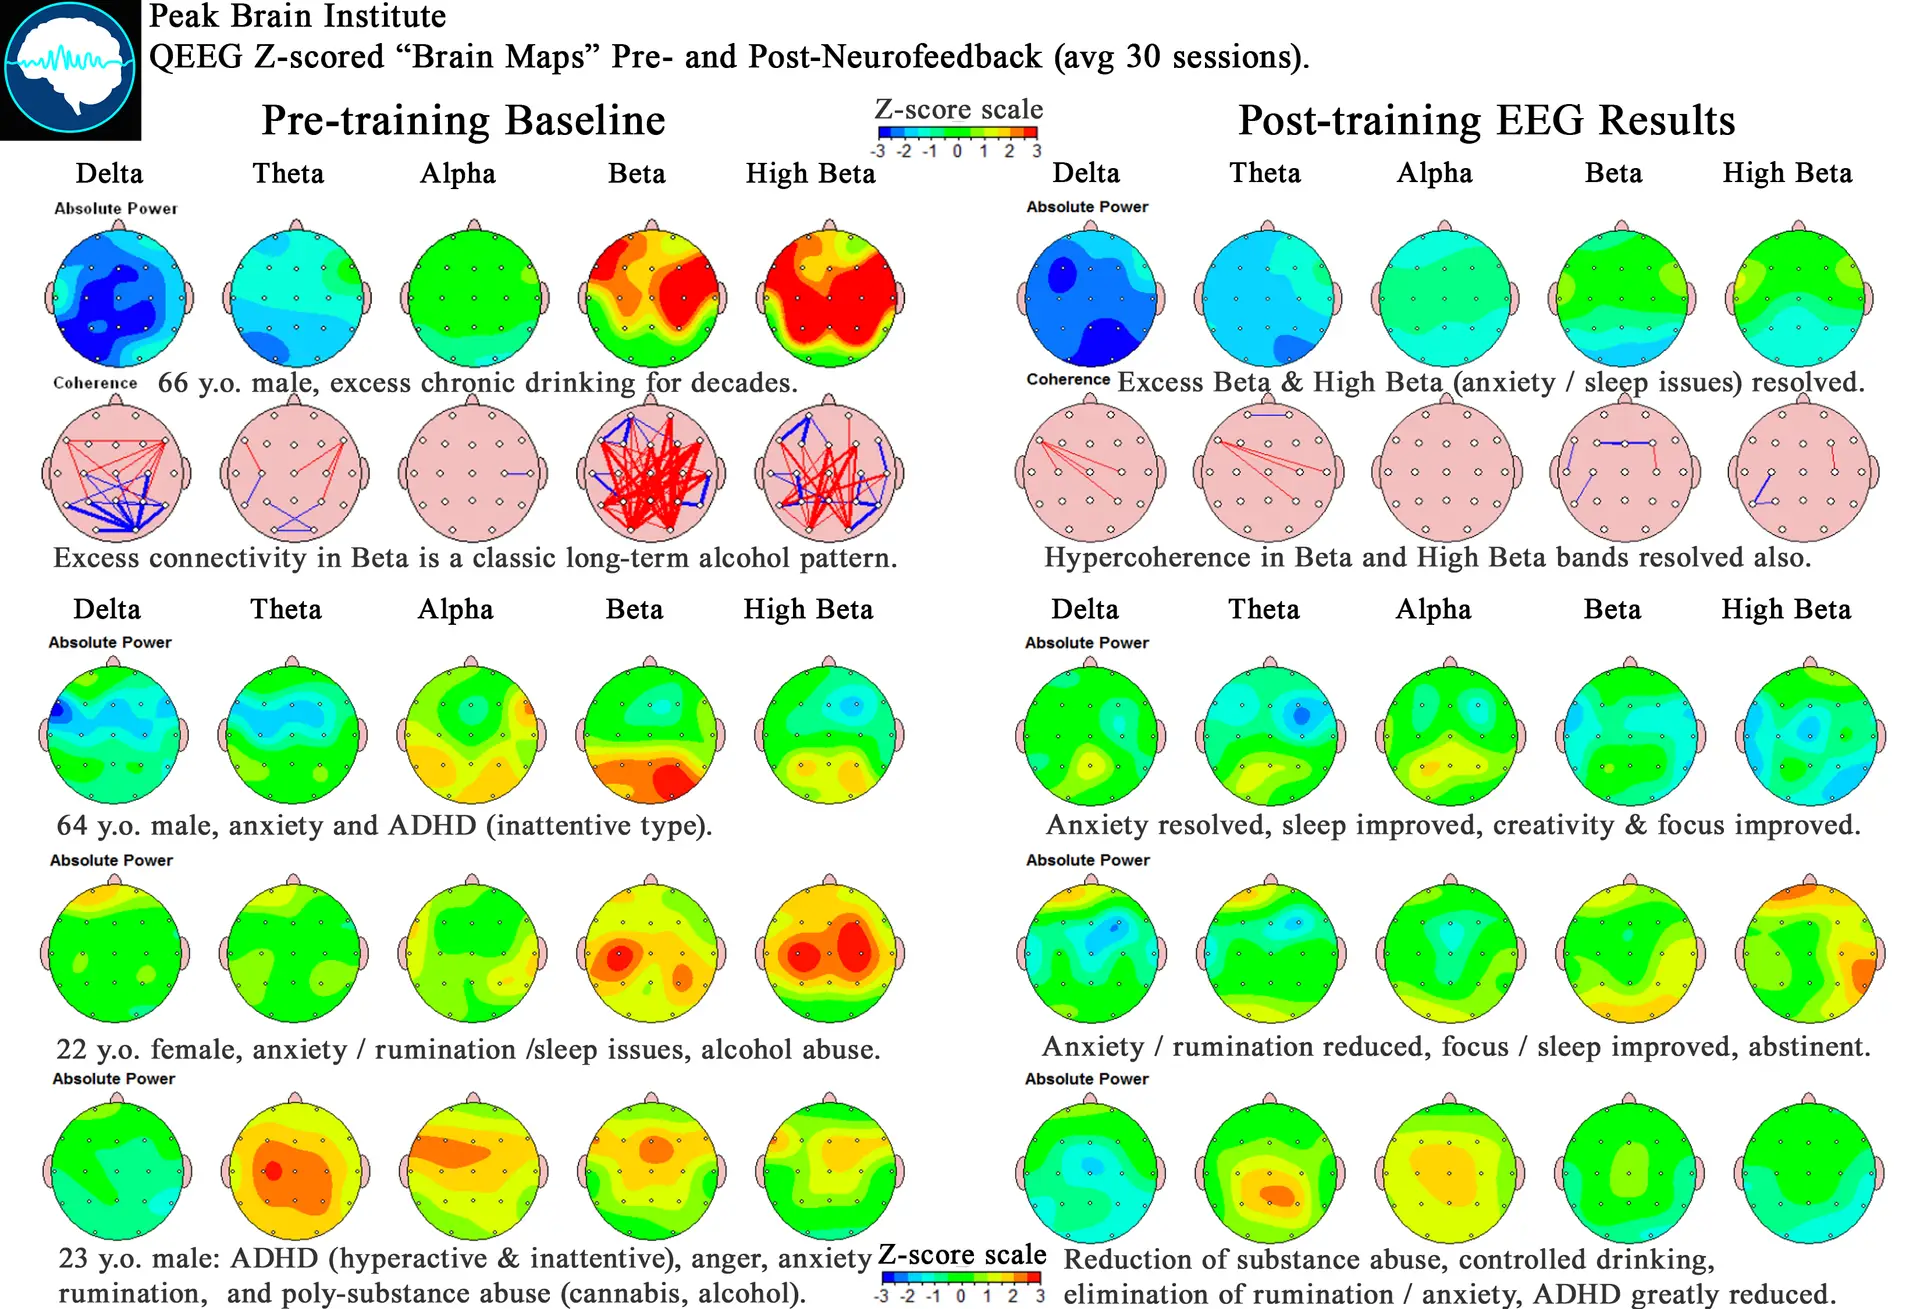
Power maps are the most commonly reviewed and the most misunderstood output. A red area on a relative beta map doesn't automatically mean ADHD. It doesn't automatically mean anxiety either. It means that region is producing more beta power relative to the rest of the brain compared to the normative sample. Context is everything. Coherence maps are where people get genuinely useful information, but only if they understand what coherence actually measures. High coherence between two regions means those areas are firing in synchrony. Low coherence means they're not. The clinical implication depends entirely on which nodes you're looking at and which frequency band is involved. Theta coherence between frontal and parietal regions, for instance, is a completely different finding than alpha coherence between the same regions. One counter-intuitive thing I learned the hard way: a "normal" QEEG map doesn't rule out a clinical condition. I had a patient with a thoroughly typical ADHD diagnosis and a QEEG that fell within normal limits across every metric. The qEEG didn't confirm or deny anything. It simply provided no additional discriminative information. That's a valid result. People who have never done this properly interpret a normal map as a failed test rather than what it actually is — an unremarkable finding.
Software Options and What They Actually Cost
The major platforms are Brainware, Neupro, Entner's NeuroGuide, and a few open-source options like BrainVision Analyser or EEGLAB if you want to build your own pipeline. NeuroGuide remains the most widely used in clinical practice, which means the normative databases are the most established. That matters more than most reviewers acknowledge. When looking at Qeeg Brain Mapping Reviews, pay attention to whether the reviewer is discussing the software or the interpretation. Those are two completely different problems. The software will do what it's told. The interpretation requires clinical judgment that no algorithm can replace. Pricing ranges from roughly $3,000 to $15,000 depending on the platform and whether you're buying just the analysis suite or a complete system that includes amplifiers and electrodes. Open-source routes exist but require significant programming knowledge. I'm not recommending either path universally. I'm saying both are viable if you know what you're getting into.
Where QEEG Falls Flat
Let me be clear about the limitations. QEEG has modest sensitivity and specificity for most psychiatric conditions. The brainmap.com study by John Sigford and others showed reasonable group-level discrimination for ADHD but poor individual-level classification accuracy. You cannot diagnose ADHD from a QEEG alone. You cannot rule it out either. The best use case is as an adjunct assessment tool within a comprehensive evaluation that already includes clinical interviews, behavioral rating scales, and cognitive testing. Another hard limitation: the normative databases are aging. Many were collected in the early 2000s with different electrode cap systems and different preprocessing standards. Global brain wave patterns shift slowly over decades, which means age-matched norms from 20 years ago may introduce systematic bias. It's a small effect but it accumulates, especially in the theta and alpha bands where inter-subject variability is already high. If you need something more granular than QEEG for certain applications, source localization methods like LORETA or sLORETA provide deeper tissue estimates but require more sophisticated hardware and analysis pipelines. For most clinical settings, that's overkill. But it's worth knowing the alternative exists when QEEG maps give you ambiguous results at the cortical surface level.

Practical Workflow for Getting Useful Results
Set impedance below five kilo-ohms. Record at least three minutes of eyes-closed resting baseline and three minutes of eyes-open. Run artifact rejection before averaging. Check raw traces for muscle, eye blink, and line noise. Compare power, coherence, and asymmetry across all metrics before drawing conclusions. Cross-reference every map finding against the patient's actual clinical presentation. If they contradict each other, trust the clinical presentation and note the discrepancy rather than forcing the data to fit. I've seen too many practitioners invert that logic. They find a statistical outlier on a map and then retroactively construct a clinical narrative to match it. That's not how evidence-based assessment works. It's how confirmation bias works, and it produces bad outcomes for patients. The takeaway isn't that QEEG is useless. It's that it's a specialized tool with specific strengths and well-documented weaknesses. Use it within its proper scope, and it adds genuine value to a comprehensive neuropsychological assessment. Treat it as a standalone diagnostic, and you'll generate more confusion than clarity.