How Reagent-Based Total Protein Testing Actually Works on the Bench
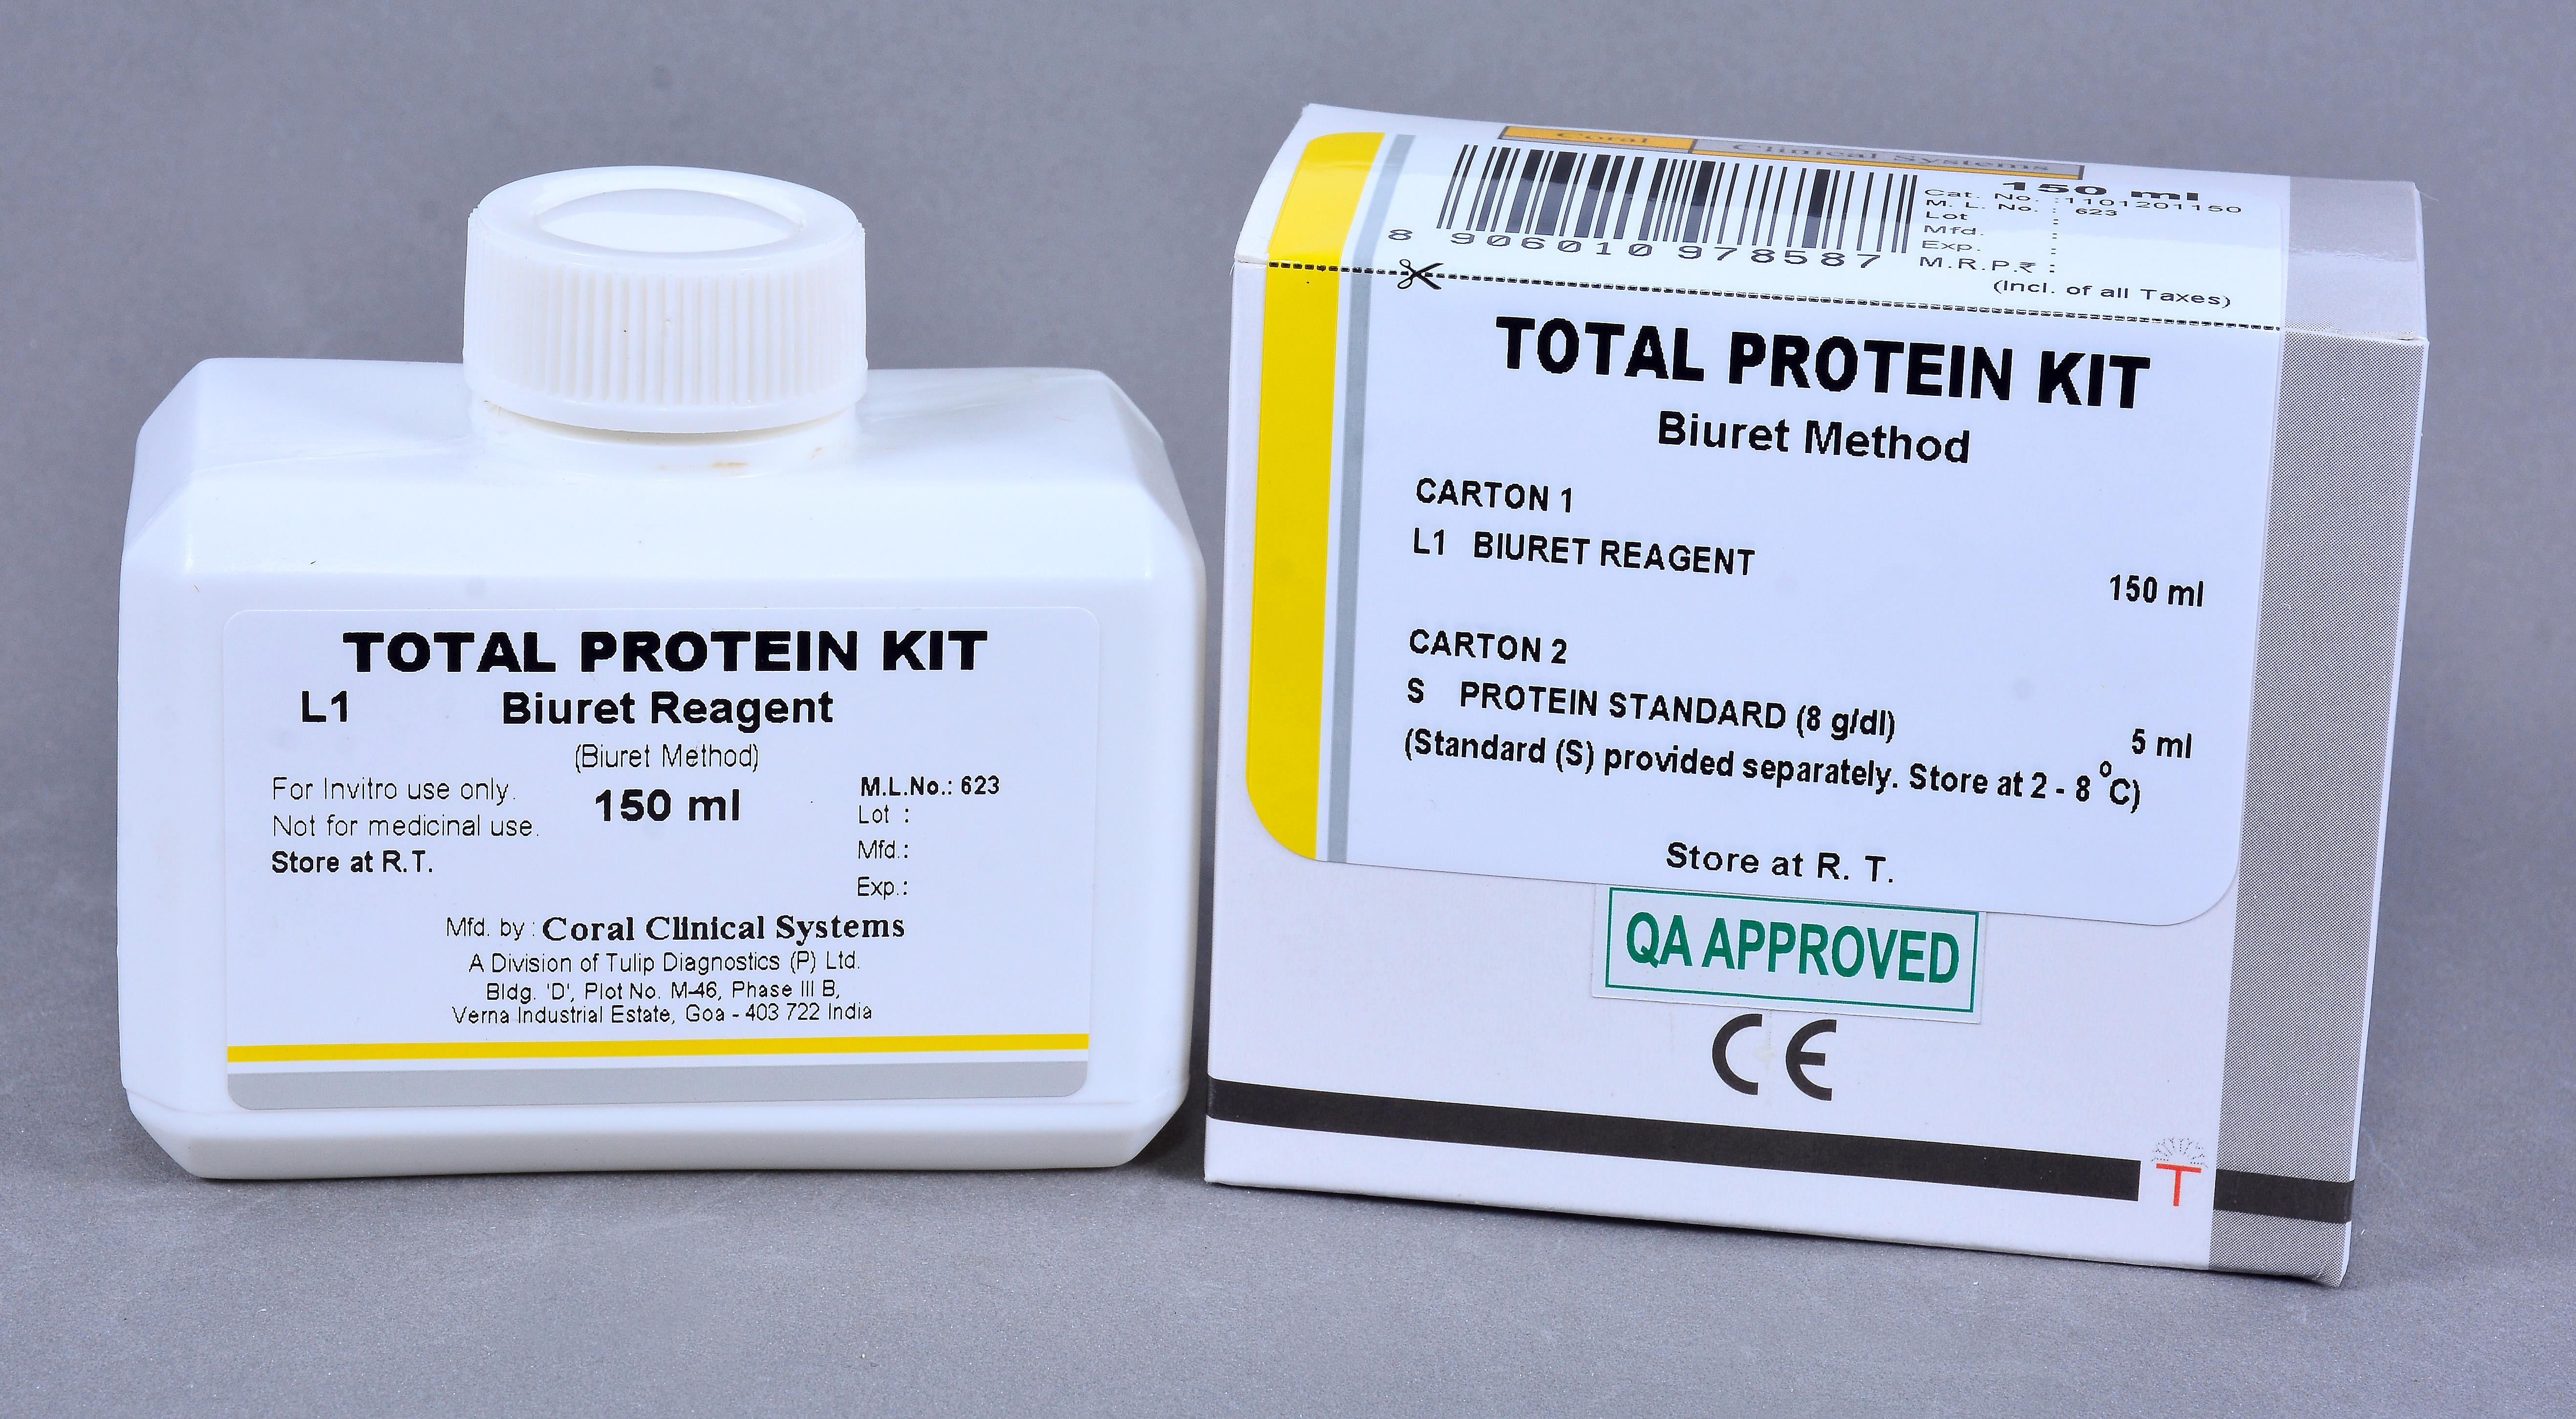
The biuret reaction is the backbone of most reagent-based total protein tests. Copper ions in an alkaline solution bind to peptide bonds, producing a violet complex that absorbs light at 540 nanometers. You add your reagent to the sample, wait the prescribed time, and read the absorbance. That is the whole mechanism in a sentence, but the part nobody tells you is how many things can go wrong between mixing and reading. The reagent itself is usually a stabilised alkaline copper sulfate solution with potassium sodium tartrate to keep the copper in solution and sometimes bicinchoninic acid for the BCA variant. The biuret reagent is cheaper and faster. BCA is more sensitive and tolerates some detergent interference, but it takes longer and costs more. Pick the one that matches your lab's throughput and sample budget. I ran into a specific issue last year with a batch of serum samples that were mildly hemolyzed. The free hemoglobin was consuming some of the copper reagent before it could react with the proteins, and the readings came out about twelve percent low across the board. I did not catch it initially because the control materials looked fine. The workaround was straightforward: I prepared a blank from each hemolyzed sample by running it without the copper reagent and subtracting that baseline from the measured absorbance. It added about forty seconds per sample, but it kept the data honest. I also started flagging samples with a visible pink tint now instead of pushing through and wondering later why the pool mean drifted.
The biggest pitfall I see people make is assuming the reagent works the same way across all sample types. Lipid samples, for example, scatter light and will push your absorbance reading higher than the true protein concentration. I once saw a triglyceride level of fourteen millimoles per litre cause a false elevation that looked like hyperproteinemia. The fix is either a clear supernatant after high-speed centrifugation or switching to a method that is less susceptible to turbidity, like the Lowry variant if your lab has it set up that way. Another thing people miss is the linear range. The standard biuret method is generally linear up to about eight grams per decilitre. If you are testing concentrated dialysate or pure protein fractions, you need to dilute into range. Running undiluted and extrapolating back is how people get numbers that look plausible but are actually off by thirty percent or more. Check the calibration curve yourself rather than trusting the spreadsheet to tell you when you have left the linear zone. Reagent storage matters more than most protocols admit. Open the bottle too many times and the alkaline reagent absorbs CO2 from the air, which shifts the pH and changes the copper complex stability. I keep mine in a tightly capped amber bottle on the bench, not in the door of the refrigerator where temperature swings are worse. The manufacturer shelf life is based on unopened vials. Once opened, treat it as good for about six to eight weeks depending on how often you pull it. If your daily controls start showing a gradual upward drift over two weeks without any other change, check the reagent age before you recalibrate the instrument.
Calibration is where the method either holds together or falls apart. Use a certified reference material, not just a homemade albumin standard if you can avoid it. Commercial calibrators are matrix-matched, which accounts for some of the protein-reagent interaction variability. A homemade bovine serum albumin standard in plain water will give you a different response curve than patient serum in the same tube. I ran a side-by-side comparison once and the patient samples read about eight percent lower against the homemade calibrator. That eight percent difference matters when you are trying to track a patient's albumin trend over months. Here is what the process looks like in practice on a busy morning. You thaw the controls, run them first, and verify they sit within your established ranges. If they pass, you run the calibrator and let the system build the curve. Then samples go in batches of ten to fifteen with a rinse cycle between high-concentration and low-concentration specimens to minimise carryover. The whole run for a moderate batch takes about twenty minutes from start to first result, and another fifteen to clean the probe and close out. If you are processing more than fifty samples a day, you will want to optimise your batch size so you are not waiting around for the cuvette to stabilise between each reading. The method has real limitations. It cannot distinguish between different protein types, so a total protein number does not tell you whether the elevation is from albumin, globulins, or an acute phase reactant. That is why it is always paired with electrophoresis or a targeted assay when you need specifics. It is also vulnerable to certain drugs and contrast agents. Iodinated contrast can interfere with some reagent formulations, and high-dose heparin has been known to cause spurious results in older reagent batches. If you suspect an interference, run the sample on a second platform or use a different detection principle and compare.
Get the Full Details
Quality control should not be a once-a-day checkbox. Run a second level control at mid-range and high-range at least once per shift. If your laboratory processes samples overnight, run controls at the start and end of the analytical run. This catches reagent degradation that happens gradually and would not show up on a single control check. I keep a Levey-Jennings chart for each control level and watch for trends, not just Westgard violations. A slow drift over five days is easier to catch manually than waiting for a rule breach that may arrive too late to save the patient results already reported. For labs that want a simpler workflow, the point-of-care options using test strips exist, but do not expect the same precision. Strip-based total protein readings have a wider confidence interval and are better suited for screening than for longitudinal patient management. If you are making clinical decisions on a number, use the laboratory-grade reagent method and keep the strip results for triage only. Documentation is unglamorous but essential. Record the reagent lot number, opening date, control results, calibration curve parameters, and any abnormal sample flags in a single run log. When an inspector or an auditor asks why a particular batch of results looks slightly different from the previous month, you need those details. I lost three days of work last year because I had swapped reagent lots without recording it, and I could not reconstruct which calibrator was valid for which run. Do not rely on memory for reagent tracking. It will fail you at the worst possible moment.
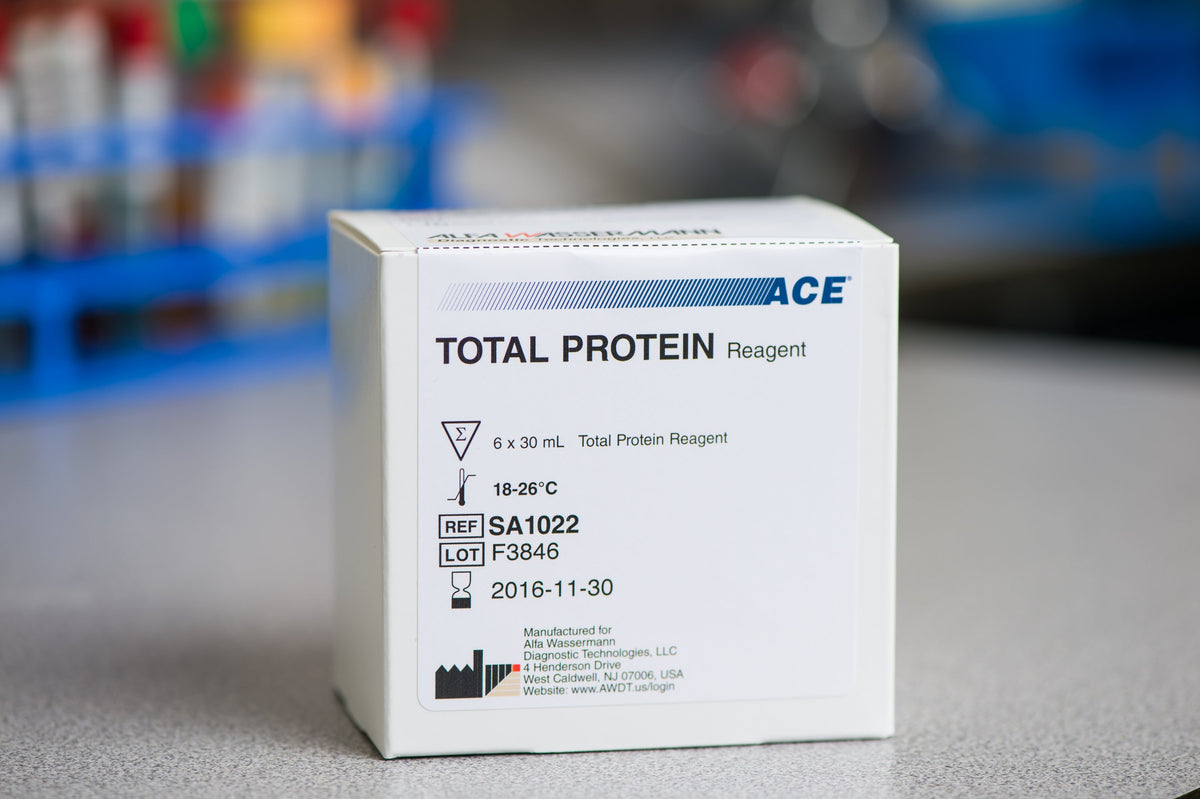
If you need the official package insert and a detailed protocol for your specific instrument, those are available directly from the reagent manufacturer's website. Look for the product datasheet under the quality assurance or clinical applications section, and download the version that matches your analyzer model. Some manufacturers also provide Excel-based calculation templates that handle the linear regression and quality control limits automatically, which saves manual math errors if you run this method frequently.