Reality Testing as a Grounding Tool
Reality testing for delusions isn't about winning an argument. It's a structured questioning technique used in clinical and peer-support settings to help someone examine whether a strongly held belief might not be grounded in observable, shared evidence. The person doing the testing doesn't lead with contradictions. They lead with open questions that create a gap between the belief and the person holding it. That gap is where the work happens. I've spent years watching this go wrong in online support communities and clinical handoff situations. Most people who try to use reality testing end up sounding like they're interrogating someone. The questions come out sharp and loaded, and the person immediately digs in. The technique falls apart in those moments because it requires a tone that sounds genuinely curious, not skeptical. Here's how it actually works in practice.
Reality Testing Questions For Delusions
The core set of questions falls into a few categories. Evidence-based questions ask someone to describe what specifically led them to the belief. Alternative-explanation questions invite them to consider other possible causes. Predictive questions ask what would happen if the belief were wrong. Predictive-checking questions ask what concrete event would change their mind. Perspective-taking questions ask how someone they trust would view the same situation. Here is a working list you can use as a starting point: What evidence do you have right now?
Where did you first notice this belief starting? Has anything in the past ten days contradicted this? If someone else saw exactly what you saw, what might they conclude?
Get the Full Details

What would need to happen for you to feel less certain? Are there any other reasonable explanations for what's happening? What are you expecting to happen next based on this belief?
Have you checked this with anyone you trust, and what did they say? Those questions are deliberately soft. They don't state the person is wrong. They don't offer a competing narrative. They ask the person to do the cognitive work themselves. The structure matters more than memorizing the list. Each question should land in a conversation where the person feels at least a little safe. If they feel cornered, they shut down. That's normal. The technique was never designed to work under pressure.
I learned that the hard way. A few years ago I was running a peer-support thread where someone was convinced their neighbor was monitoring them through household appliances. Standard reality testing was failing because every question I asked felt like I was probing for weaknesses in their story. The person escalated fast. What finally moved the conversation forward wasn't a new question. It was me saying, "I want to understand what makes this feel real to you, not convince you it isn't." I reframed the entire approach as collaborative investigation instead of correction. We spent two hours going through each piece of evidence they had, and only then did some of the questions start landing. By the end, they admitted they'd noticed patterns that didn't quite line up. That was the opening. It wasn't dramatic. It was just slow, unglamorous, repetitive questioning from a place that didn't feel adversarial. There's a specific edge case where reality testing breaks down completely and most people don't talk about it. Acute psychosis. When someone is in the middle of a florid psychotic episode, their brain is generating false perceptions that feel indistinguishable from real ones. Asking a person in that state to evaluate evidence is like asking someone with a broken leg to run a sprint. The cognitive machinery required for reality testing simply isn't accessible. They can't do it. I've tried to push the technique in those situations before, and it only made things worse. The workaround is straightforward: drop the questioning entirely until the person is stabilized. Focus on safety, de-escalation, and connecting them to clinical care. Reality testing has a place, but that place is not during an acute episode. Another thing that trips people up is timing. Reality testing works best when the person already has some doubt bubbling underneath the surface. If someone is fully committed to a delusion with zero internal uncertainty, the questions will bounce right off. They need a crack in the conviction first. That crack usually comes from exhaustion, confusion, or a moment when the belief produced an unexpected result. Your job is to notice that crack and move slowly into it. Don't force it open.

Here are a few counter-intuitive points that most introductory guides miss: Distinguishing delusions from fixed false beliefs is important. A delusion is a fixed belief that is culturally impossible and persists despite clear contradictory evidence. Not every wrong belief is a delusion. People hold mistaken ideas about everything from health to relationships to politics. Reality testing for delusions requires actual clinical-level conviction, not just stubbornness. If you apply this technique to someone who is simply misinformed, you're wasting time. Direct information provision works better there. The goal isn't always belief abandonment. A lot of people treat reality testing as a binary success metric. Either the person drops the delusion or it failed. That's wrong. Partial is also success. If the person moves from "this is absolutely true" to "maybe I should look at this differently," you've done the work. Complete abandonment of a delusion during a single conversation is rare. Most progress is incremental.
Tone is the technical skill here. You need a flat, calm delivery. Any hint of sarcasm, impatience, or superiority will destroy the process. People with delusions are often hypersensitive to perceived threat. They pick up on micro-expressions and tone shifts that neurotypical people miss entirely. Practice the questions out loud before using them on someone. Record yourself. Listen back. If you sound even slightly condescending, start over. I keep a printed reference card with the question list above. It lives on my desk. I don't read it during sessions. I've internalized the structure. The card is for quick glances when my brain is tired and I'm worried I'm about to drift into lecture mode instead of questioning mode. Having it physically present keeps me honest about staying in the right frame. Here are the limitations you need to accept upfront:
This technique does not work for everyone. Some people with entrenched delusional systems will reject every question and dig in deeper. That is a known outcome, not a failure on your part. In those cases, continuing to push reality testing is counterproductive. Switch to supportive listening and professional referral. It requires a baseline level of verbal and cognitive functioning. Non-verbal individuals, people with significant cognitive impairment, or those in active mania cannot engage with structured questioning. Use different approaches for those populations. Reality testing should never replace clinical treatment. It is a supplementary communication tool, not a therapeutic intervention on its own. If someone is experiencing delusions, the first recommendation should always be evaluation by a qualified mental health professional. Peer support and reality testing can complement treatment, but they cannot substitute for it.
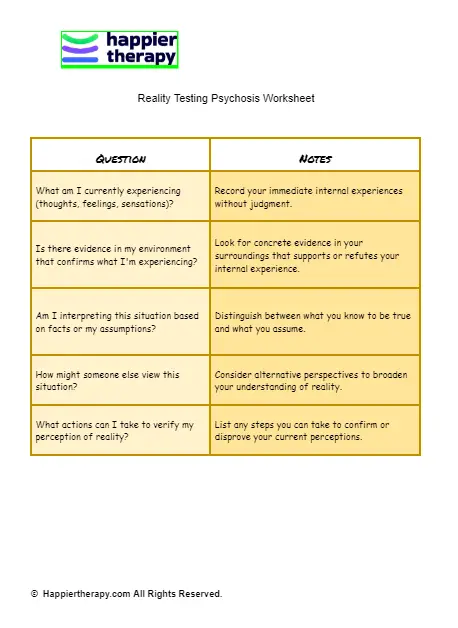
One final note on documentation. If you're using this in a peer-support or clinical-adjacent setting, write down which questions you asked and how the person responded. Not for bureaucracy. For pattern recognition. You'll start to see which questions produce the most movement for which types of beliefs. That personal data is more useful than any generic guide you'll find online.