
The Abdomen Is a Messy Place If You Try to Describe It Exactly
When I started teaching anatomy to med students, I kept expecting them to nail the nine-region mapping on day one. They didn't. About 70% of them still mix up the left and right sides after the first exam, which is kind of pathetic because it's basically just a grid on your belly. But here's the thing nobody tells you until you're actually working with patients — the grid lines move when someone breathes, flexes, or has a distended abdomen. That's when the whole system falls apart a little. I remember this one case where a patient came in with what looked like classic appendicitis. Right lower quadrant pain, rebound tenderness, all the textbook signs. But when I traced the pain using the nine-region framework instead of just the four-quadrant method, I realized the actual inflammation wasn't at all where we expected. The appendix had migrated behind the colon — retrocecal position — and the pain was referring upward toward the right lumbar region rather than sitting cleanly in the right iliac fossa. We ended up ordering a CT instead of rushing to surgery, and sure enough, the appendix was wrapped around the cecum. If we had relied purely on the standard four-quadrant approach, we might have gone in blind.
Why You Should Know Regions Of The Abdomen Beyond Basic Anatomy
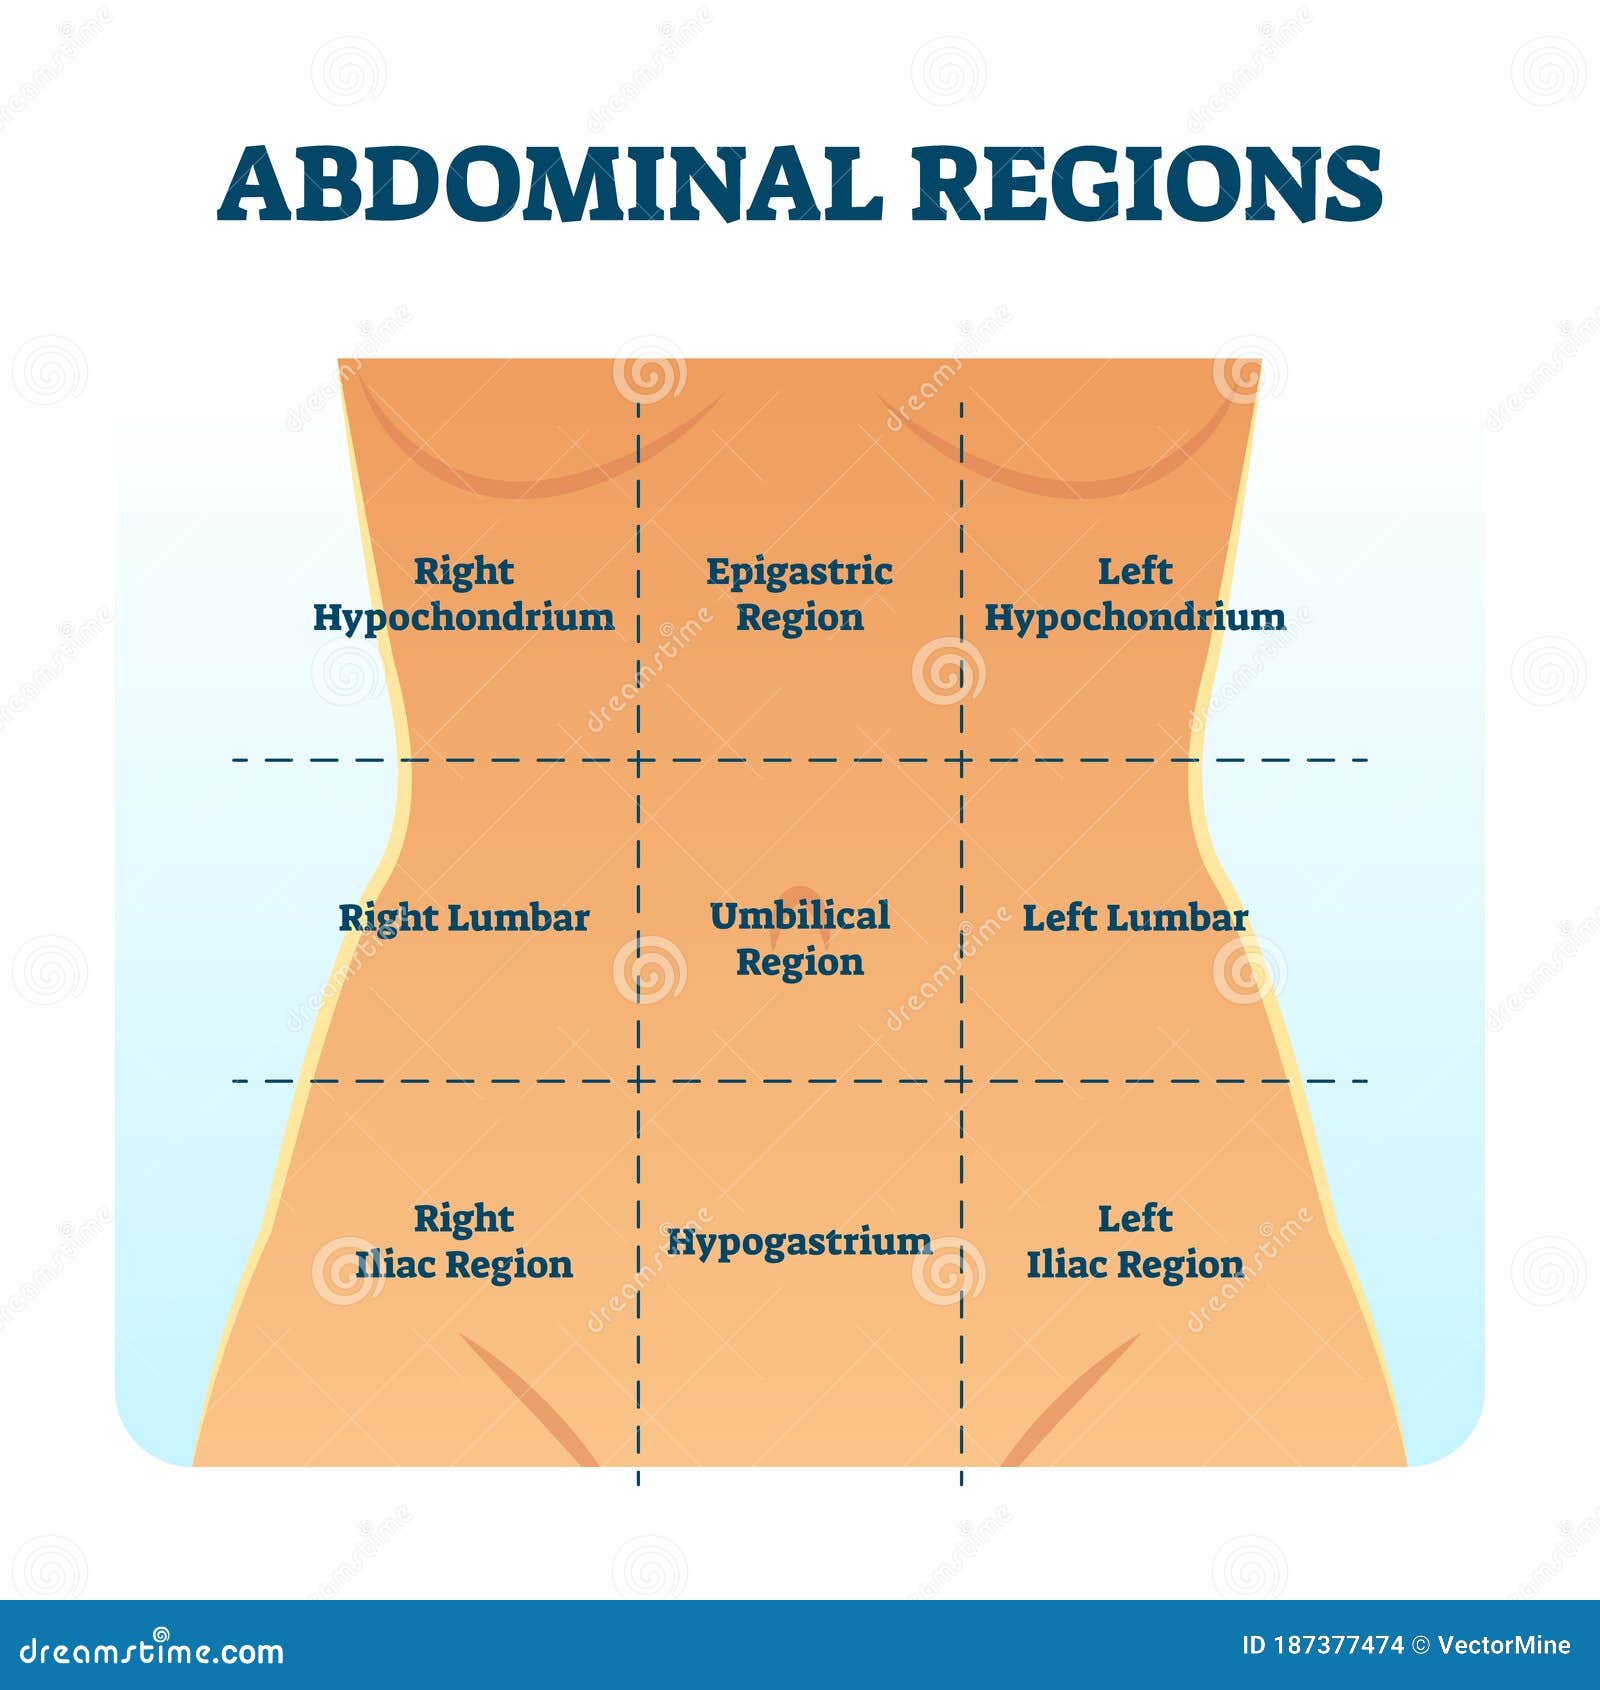
The nine-region system divides the abdomen using two vertical planes and two horizontal planes. The vertical planes are the midclavicular lines, running down from the middle of each clavicle. The horizontal planes are the subcostal plane at the level of L3 and the transtubercular plane at the level of L5. These create nine regions: the right and left hypochondriac regions up top, the epigastric region in the middle, the umbilical region around the belly button, the right and left lumbar regions on the sides, and the right and left iliac (or inguinal) regions down below with the hypogastric or pubic region at the very bottom. The four-quadrant system is simpler — just one vertical midline and one horizontal line through the umbilicus. It's faster for emergency situations where you don't have time to be precise. But the nine-region system gives you more granularity, which matters when you're trying to trace referred pain from something like a pancreatic issue that could present in the epigastric region and radiate to the back. One thing I learned the hard way is that surface landmarks don't always match internal anatomy the way textbooks suggest. A gallbladder problem might manifest as right hypochondriac pain, but sometimes it refers to the right shoulder blade through the phrenic nerve. I've had patients insist their pain was "in my shoulder" when it was actually biliary colic. Don't assume the surface region maps perfectly to the organ beneath it.
Here's another nuance that beginners miss: body habitus changes everything. A thin person with well-defined abdominal walls will have landmark lines that are easy to trace. An obese patient? Good luck finding the subcostal margin. The palpable landmarks shift, and your region boundaries become approximations rather than precise guides. I developed a habit of using the anterior superior iliac spines and the xiphoid process as anchor points first, then working outward, because those bony landmarks don't move even when there's significant subcutaneous fat.
Get the Full Details
The Practical Stuff Nobody Emphasizes Enough
When you're doing an abdominal exam, you have to think about what organ sits where, but also what can refer pain to adjacent regions. The kidneys sit retroperitoneally, so renal colic might present in the lumbar regions or radiate downward toward the iliac regions. Liver pathology shows up in the right hypochondriac area but can refer to the epigastrium. Pancreatic issues tend to localize to the epigastric region with a characteristic band-like radiation to the back. I use a specific sequence when examining — inspection first, then auscultation before percussion and palpation because touching the abdomen first can alter bowel sounds. This order matters more than people realize. I once missed an early obstruction pattern because I palpated before listening, and the patient's guarding made the auscultation unreliable. The biggest limitation of the regional system is that it was designed for relatively thin, average-built adults in a supine position. In clinical practice, patients are often obese, pregnant, post-surgical, or positioned at angles that distort the surface anatomy. The system becomes a rough guide rather than a precise map. For those cases, imaging is non-negotiable. I stopped relying solely on surface landmarks after my third near-miss with an atypical presentation, and now I cross-reference every ambiguous finding with ultrasound or CT when I can.
There's also the issue of visceral versus somatic pain. Visceral pain from intra-abdominal organs is dull, poorly localized, and often centered around the midline regardless of which region the organ actually occupies. Somatic pain from the parietal peritoneum is sharp and well-localized to the specific region. Teaching students to distinguish between these two types of pain based on region mapping alone is nearly impossible without clinical context. Another practical consideration: children and the elderly present differently. Pediatric abdomens are proportionally smaller, and the relative positions of organs shift as the body grows. An elderly patient with diminished abdominal wall tone might have organs that sit more inferiorly than the standard maps suggest. I've adjusted my mental model for these populations rather than forcing their anatomy into adult templates. If you're studying this for exams, focus on the organ-region correlations but don't treat them as absolute. Memorize that the stomach is primarily in the left hypochondriac and epigastric regions, the liver spans the right hypochondriac and epigastric regions, and the appendix lies in the right iliac region. Then learn to recognize when real patients violate every rule you memorized. That's where actual clinical competence begins.
Common Pitfalls and How to Avoid Them
The most frequent mistake I see is assuming symmetry. Just because something hurts in the right iliac region doesn't automatically mean appendicitis. Ovarian pathology, hernias, musculoskeletal strain, and even skin conditions like shingles can mimic visceral pain in the same region. I spent an entire residency learning that region-based diagnosis is a starting hypothesis, not a conclusion. Another pitfall is ignoring the patient's position. Pain that shifts when a patient moves from supine to standing or rolling to the side can reveal things that static examination misses. A psoas abscess, for example, might cause pain in the right lumbar region only when the hip is extended. Positional testing adds a dimension that flat regional mapping simply doesn't capture. The nine-region system also breaks down completely with massive ascites. When the abdomen is distended with fluid, all the surface landmarks become unreliable. The organ positions shift, and the regional divisions lose their anatomical meaning. In those cases, percussion and shifting dullness become more useful tools than any region-based approach.

I've found that combining regional mapping with a quick mental organ survey works better than relying on regions alone. Identify the region of maximal tenderness, then ask which organs occupy that space, what structures could refer pain there, and what atypical presentations you've encountered in that region. This tripartite approach reduces diagnostic errors significantly. For self-study, I recommend tracing the region lines on yourself and a few friends with different body types. Palpate the anatomical landmarks — costal margins, ASIS, xiphoid process — and notice how they shift with breathing and posture. Then correlate those surface points to what you know about underlying organs. Hands-on practice with real bodies builds an intuition that textbook diagrams simply cannot provide.


