Getting Your Head Around the Rehab Optima Documentation System
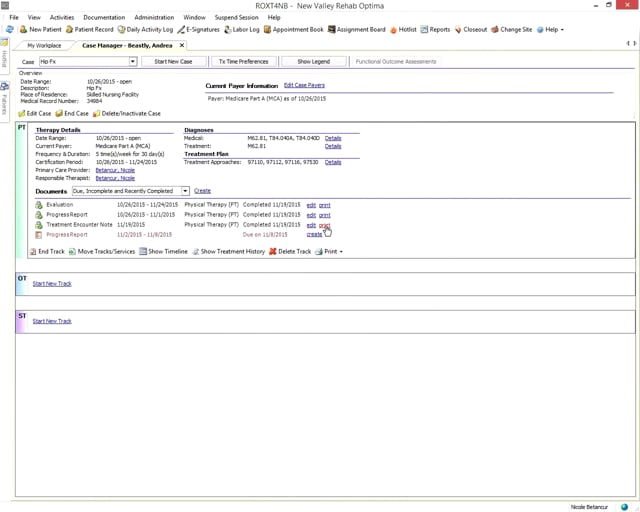
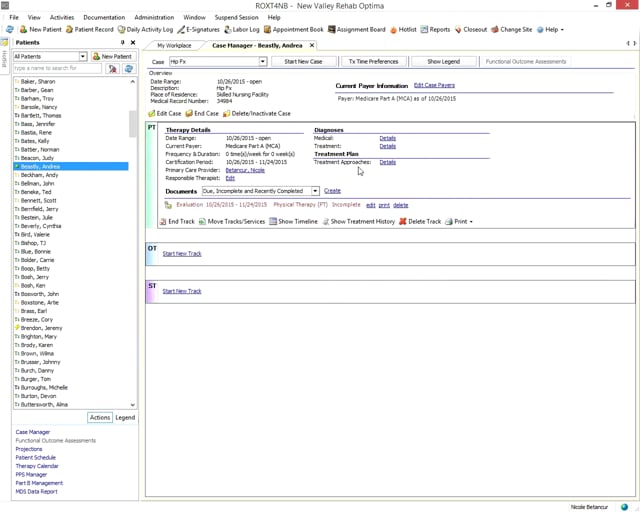
Rehab Optima Documentation is essentially the charting and billing module within the Rehab Optima therapy practice management platform. It handles treatment documentation, progress notes, billing coding, and compliance reporting for physical therapy, occupational therapy, and speech-language pathology clinics. If you are running a small rehab practice and have spent more than a week with this system, you already know it does the job but has enough quirks to make your head spin on a bad Tuesday. At its core, the documentation module handles patient charts, visit notes, plan of care tracking, and insurance claim generation. It is built around a template-driven note system where each discipline—PT, OT, SLP—has its own preset structures. You can customize those templates but the customization interface is not intuitive. The system also pulls scheduling data from the other Rehab Optima modules, so patient no-shows and late cancellations feed directly into your documentation workflow. That integration is one of the fewer things that works smoothly out of the box. I spent about three weeks trying to get our clinic's custom template for pediatric SLP to behave correctly. The problem was that the system would not let me save conditional fields unless I filled them in the exact sequence the template engine expected. I ended up just creating duplicate templates—one for younger kids with simpler fields and one for older kids with the full set—and mapping patients manually. It worked. It is not elegant.
How to Navigate the Documentation Workflow
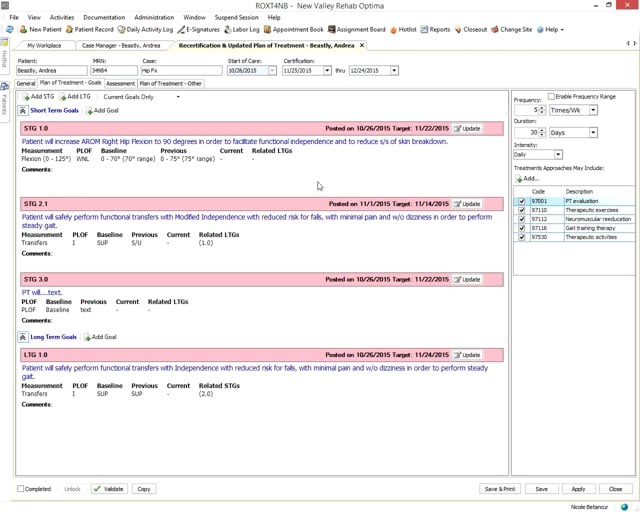
Start by making sure your provider credentials and NPI numbers are entered correctly in the admin section. I cannot stress this enough because incorrect provider setup will silently corrupt your claims output, and the system does not warn you about it. Once that is straight, you can begin populating templates. Here is the part nobody mentions: the documentation module allows bulk editing of note fields for the current day only. I figured this out accidentally after spending forty-five minutes editing individual notes for a full afternoon schedule. After that, I learned to batch my charting by appointment block rather than trying to complete notes in real time during the shift. The plan of care tracking section requires you to re-certify treatment plans at set intervals depending on payer. Medicare requires recertification every thirty days for skilled therapy, and Rehab Optima flags approaching deadlines but does not prevent you from scheduling beyond the certified window. This is a feature, not a bug, but it absolutely requires staff attention. I have seen clinics miss recertification windows because they assumed the system was blocking them. It is not. It only sends alerts.
The Billing Bridge and Where It Usually Breaks
Documentation feeds directly into billing through a mapping layer that connects CPT codes to diagnosis codes and modifier usage. The default mappings are reasonable but often wrong for your specific payer contracts. If you run a multi-payer clinic, you will need to audit the code-to-diagnosis mappings within the first month of setup. I found that two of our most common payers had flipped the modifier 59 and XE mappings entirely, which caused claim denials until I traced it back to the documentation settings. This took about an hour to diagnose and another hour to correct across all active patient profiles. The system also generates a UB-04 output file for institutional claims. The export function is reliable but the formatting assumes you understand medical billing layout conventions. If you are unfamiliar with form locators and revenue codes, you will spend extra time cross-referencing the output against your payer requirements. There is no built-in validation for claim completeness before export. You have to run your own check, usually by reviewing the eligibility and diagnosis fields manually for the patients in your billing queue.
Get the Full Details

Pain Points You Should Know About Before You Commit
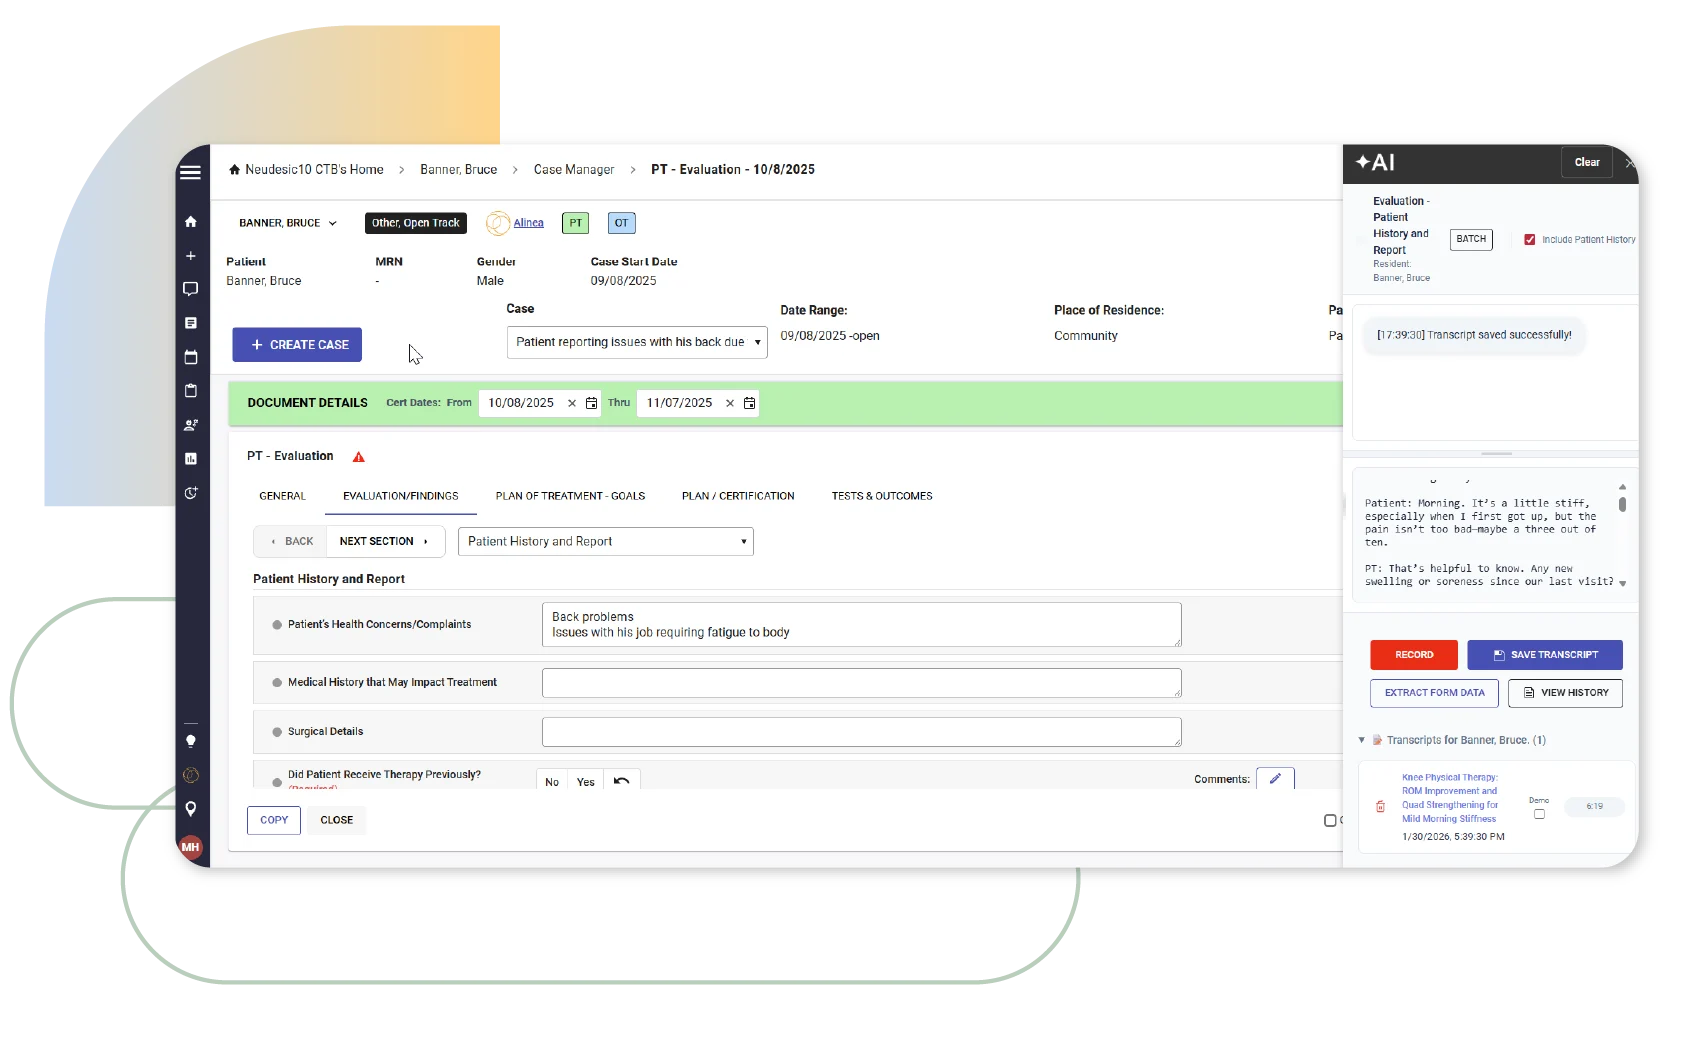
Rehab Optima Documentation lacks native voice-to-text integration. This sounds minor until you realize that manual note entry for a high-volume clinic adds roughly forty to sixty minutes per therapist per day. I worked around this by exporting documentation fields to a CSV, feeding them into a third-party dictation service, and re-importing the corrected text. It added a step but cut total documentation time significantly. The system does support basic copy-paste, so if your therapists use EHR systems from other vendors, they can pull existing clinical language and adapt it. The formatting usually carries over poorly and requires cleanup. Another limitation is the reporting module. It produces standard compliance reports but the custom report builder is limited. You cannot join tables from different data sources within a single report, which means if you want a report that combines documentation timestamps with billing outcomes, you need to export both separately and merge them in Excel or a BI tool. I do this routinely. It takes about fifteen minutes per month for a mid-size clinic. Mobile access to documentation is functional but slow on older tablets. The offline mode exists but sync conflicts are common when multiple providers edit the same patient record while disconnected. I recommend enforcing a policy where providers complete notes before ending their shift rather than relying on offline drafting.
A Practical Walkthrough for New Users
Create a new patient record under the clinical module first. Enter diagnosis, referral source, and insurance details before moving to scheduling. Then navigate to the documentation tab and select the appropriate template for the discipline. Fill in the subjective section, objective section, and assessment fields using the available dropdowns wherever possible. Dropdown usage speeds up processing and reduces typos that trigger billing errors later. Once the note is saved, assign the CPT codes and modifiers through the billing linkage screen. Generate the claim file at the end of each business day rather than waiting until the end of the week. Daily exports catch errors while the details are fresh. If you are migrating from another system, import your patient demographics and active plans of care in batches of fifty to one hundred records. Larger batches tend to time out or silently drop rows. I learned this after a migration attempt lost approximately twenty patient records because I submitted a batch of two hundred. Those records were not flagged as errors. They simply vanished from the import log.
Rehab Optima Documentation Common Pitfalls and Fixes
Provider signature fields sometimes appear as blank after template edits. The fix is to delete the template field placeholder and recreate it from the field library rather than attempting to edit the existing placeholder. Template modification through direct HTML or CSS editing is not supported and will break the rendering engine. Another issue is duplicate patient records created when insurance ID formats vary between payer portals. I implemented a patient search rule that checks for name plus date of birth matches before creating a new record. It reduced our duplicate rate from about eight percent to under one percent within a month. The system does not handle telehealth modifier 95 placement automatically in all templates. You need to add the modifier manually to the CPT entry screen or the claim will likely be rejected by payers that require it. This is a known gap that has been on the development roadmap for several years without a public release date.
When This System Is the Right Fit
Rehab Optima Documentation works well for clinics with two to fifteen providers who want an all-in-one practice management and documentation solution. It is less suitable for large multi-site operations that need advanced customization, deep analytics, or integration with hospital-based EHR systems. In those cases, you are better off using a dedicated documentation platform like TherapyNotes or an enterprise EHR with rehab-specific modules. The integration effort required to make Rehab Optima behave in a large-scale environment usually exceeds the value it provides compared to purpose-built alternatives. For smaller clinics willing to invest time in initial setup and template configuration, the system handles day-to-day documentation adequately and the billing pipeline is functional once configured correctly. The main ongoing cost is staff time spent managing exceptions and workarounds rather than using the system in its intended design. That is the honest tradeoff.