How Group Therapy Actually Works for Preventing Relapse
Relapse Prevention Group Therapy is a structured form of group counseling that teaches people in recovery how to identify triggers, manage cravings, and develop coping strategies before they lose control. It was originally developed by Alan Marlatt in the late 1970s and has since been adapted for substance use disorders, behavioral addictions, and certain mental health conditions. The core idea is straightforward: addiction and compulsive behaviors follow patterns, and if you can map those patterns, you can interrupt them. In practice, this means each session focuses on specific skill-building rather than just sharing stories. Early sessions cover psychoeducation about the relapse process itself—how a relapse doesn't happen overnight but through a chain of events. Later sessions move into identifying high-risk situations, creating coping plans, and rehearsing responses. Cognitive restructuring plays a big role too, since many people in recovery have deeply ingrained thought patterns that lead them back toward using.
How to Run a Relapse Prevention Group Therapy Session
Setting this up isn't as simple as gathering people who struggle with the same issue and hoping for the best. The structure matters a lot. A typical session runs about 90 minutes and follows a consistent format that participants learn quickly. Start with a check-in. This isn't small talk—it's a rapid emotional and situational inventory where each person reports on their status since last week, including any urges, near-misses, or full relapses. You want to hear specifics. "I was fine" tells you nothing. "I went past the bar I usually stop at on Tuesday" tells you something you can work with. After check-ins, introduce the session topic. Common topics include: recognizing early warning signs, managing the urge-surge (the way cravings spike and then subside), dealing with the abstinence violation effect (that moment when someone slips once and then decides they've already failed so they might as well keep going), social pressure and refusal skills, and building a support network outside the group.
Then move into skills training. This is where the actual work happens. Demonstrate the skill, have people practice it in pairs, then debrief as a group. For example, you might spend twenty minutes having people role-play saying no at a party where substances are present. Most beginners skip this part because it feels awkward. Don't skip it. The research consistently shows that rehearsal beats discussion when it comes to behavioral change. Closing should include a written plan. Each person writes down at least one specific situation they're worried about in the coming week and what they'll do when it comes up. Collect these, read them back anonymously if needed, and have the group give feedback. This creates accountability without putting anyone on the spot individually. I ran a group for about three years dealing primarily with alcohol and opioid recovery, and one thing I learned the hard way: people will perform competence in group settings. They'll nail the role-play in session and then fail completely in the real situation. I noticed this pattern around session five when several people reported "nothing triggered me" all week. When I asked more pointed questions, it turned out they'd simply avoided every situation that might be challenging. Avoidance isn't a strategy. It's postponement. The workaround I used was to assign homework that required them to approach, not avoid, one trigger situation per week and then report back on exactly what happened. Not whether they survived, but what their actual thought process was during the encounter. That detail made the difference between people who got better and people who just stayed sober until something unexpected hit them.
Get the Full Details

The Mechanics Behind Why It Works
Relapse Prevention Group Therapy draws from cognitive-behavioral therapy, but it has distinct elements that separate it from standard CBT groups. The most important distinction is the concept of the "high-risk situation." In Marlatt's original model, high-risk situations fall into four categories: negative emotional states, interpersonal conflict, social pressure, and positive emotional states. The last one is the one most people miss. Someone who gets good news, feels confident, or is celebrating can slip just as easily as someone who's depressed, because confidence often leads to the thought "I've got this under control now." The coping response effectiveness model is another key piece. It's not enough to have a list of coping strategies. People need to evaluate whether a strategy actually works for them in practice. This means tracking what works, what doesn't, and why. Groups that don't build in this evaluation step tend to produce people who know a lot of techniques but can't deploy them under stress. Another counter-intuitive finding: the more structured the group, the less effective it tends to be for people with higher functioning and longer recovery times. I've seen groups where the most advanced members were quietly checked out because they'd already internalized the material. The workaround is to create parallel tracks—one for people early in recovery who need the basics and structure, and another for people who've been clean longer who can handle more nuanced work on identity, meaning, and relapse prevention in complex real-world scenarios. Splitting by recovery stage instead of by diagnosis makes a significant difference in engagement and outcomes.
Common Pitfalls and When It Simply Won't Work
Relapse Prevention Group Therapy is not a universal solution. There are scenarios where it fails or causes harm, and being honest about that is important. One major limitation: it requires a baseline of stability. People who are actively using, who have severe co-occurring psychiatric conditions that aren't stabilized, or who are in acute crisis are not good candidates for a standard group format. Putting them in a group with people who have more insight often leads to either the acutely ill person destabilizing further or the group derailing because someone can't participate in the skill-building framework. These individuals need individual therapy and possibly medication management first. Another limitation: groups that run too long without a clear exit strategy create dependency. I've seen people stay in the same group for two years without progressing. The group becomes a substitute for real-life coping rather than training for it. The solution is to set a target duration—typically 16 to 24 sessions—and make graduation a visible goal, not an afterthought.
There's also the problem of group cohesion turning into a support bubble. People start relying on the group for emotional regulation instead of developing internal resources. This shows up as attendance anxiety—people who panic if they miss a session or who can't function on weekends when groups aren't running. Address this by building in exposure practices and by encouraging participants to gradually reduce their reliance on the group while increasing their use of individual coping strategies and broader social supports. If someone is looking for something less structured, individual CBT-based relapse prevention has similar mechanisms without the group dynamics. For people with strong social networks already in place, those networks can sometimes serve the same function as a group without the overhead of scheduling and facilitation. The trade-off is losing the accountability and modeling that comes from watching others work through the same material.
Practical Considerations for Implementation
Setting up a group takes preparation. You need a licensed facilitator who understands both group dynamics and relapse prevention theory. Running a group without proper training in group process is where things go wrong most often—facilitators either let discussion meander into unproductive territory or they become too directive and shut down the very processing that makes groups effective. Screening is essential. Not everyone who says they want to join is ready. A brief screening interview covering current substance use, psychiatric history, and motivation level takes about fifteen minutes and prevents the common problem of dropping out mid-group, which tends to demoralize the remaining members. Materials are relatively simple. Worksheets for identifying triggers, coping cards, and a relapse prevention plan template are the core tools. You don't need expensive proprietary programs. The Marlatt model has free worksheets available, and many of the skill-building exercises can be done with just paper and pens. What matters is consistency, not complexity.
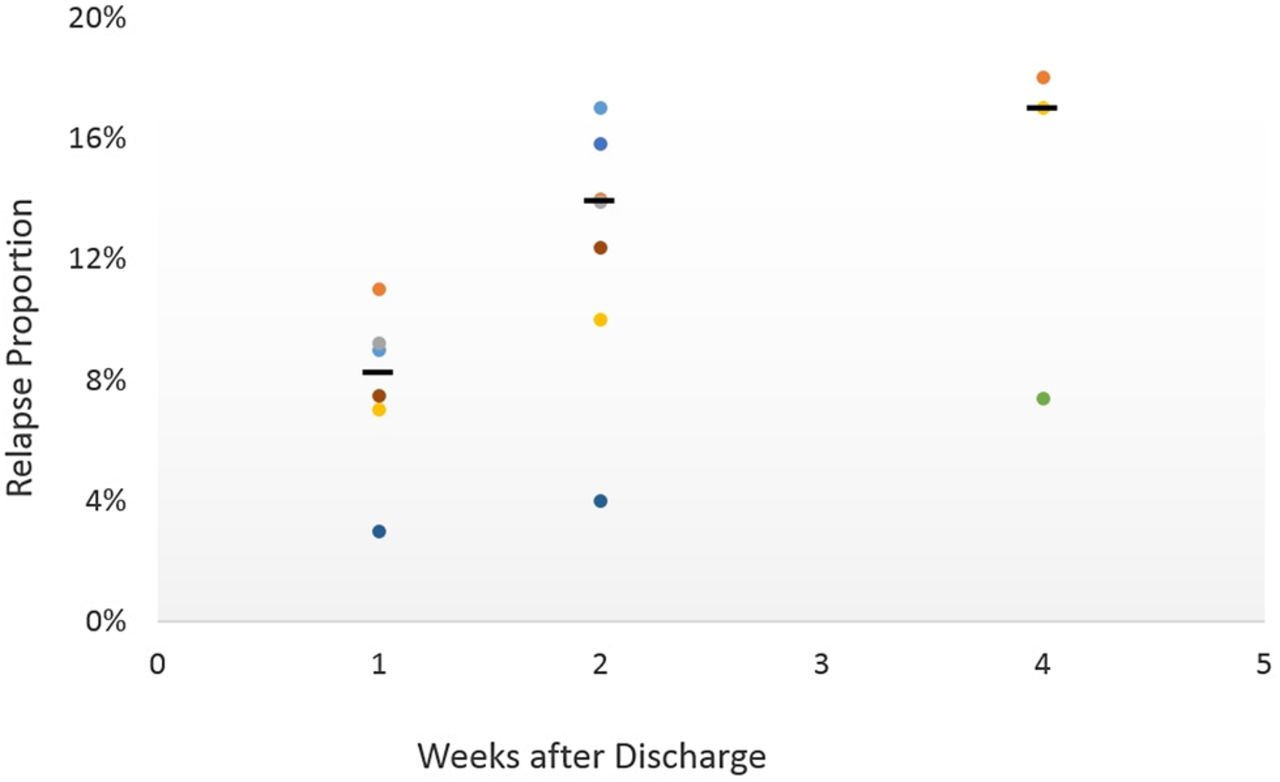
Session frequency matters. Weekly is the standard, but twice-weekly groups during the first three months produce measurably better outcomes for people at highest risk. The gap between sessions is where most relapses happen, so compressing that early period helps. The data on outcomes is mixed but generally favorable. Meta-analyses show moderate effect sizes for substance use disorders, with relapse rates dropping roughly 20 to 30 percent compared to treatment-as-usual. These numbers sound modest but they're meaningful at population level. A twenty percent reduction in relapse translates to significantly fewer hospitalizations, legal issues, and relationships destroyed. The effect is stronger for alcohol and cannabis than for opioids or stimulants, likely because those substances involve more complex neuroadaptation that group therapy alone can't address.
Building Your Own Relapse Prevention Group Therapy Program
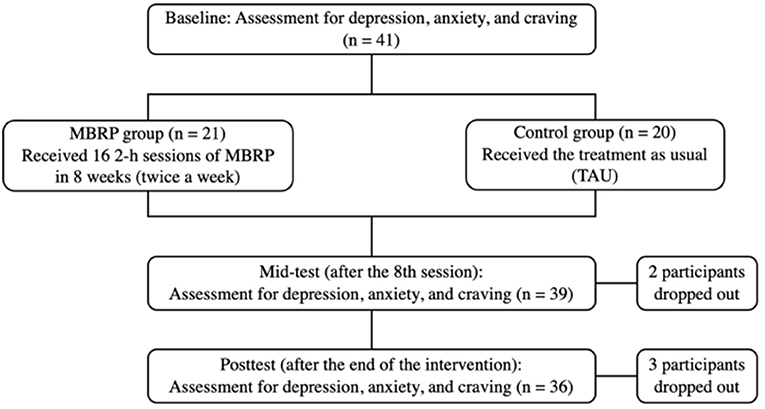
If you're setting this up from scratch, start with a curriculum based on the Marlatt model but adapted to your population. A standard 16-session structure covers: orientation and goal-setting, understanding relapse, identifying personal triggers, coping with cravings, managing high-risk situations, addressing the abstinence violation effect, building a support network, relapse prevention planning, and review and graduation. Sessions twelve through fifteen can be dedicated to complex cases and individualized planning. Session sixteen is graduation with a review of the relapse prevention plan and a clear pathway for booster sessions if needed. Record attendance and self-reported urge frequency across sessions. This data helps you identify who's progressing and who's stuck. People who report no change in urge frequency after six sessions usually need a different approach—individual work, medication consultation, or a different type of group entirely. Continuing them in the same group without adjustment wastes everyone's time. Train your facilitators thoroughly. Two days of orientation plus ongoing supervision is the minimum. Facilitators who haven't worked through their own recovery issues tend to either avoid discussing relapse openly or over-identify with participants, both of which undermine the group. Supervision should focus on group process, not just content knowledge.
The hardest part is keeping people engaged through the middle sessions. Week three is where most attrition happens. People expect relief and instead get homework, role-plays, and difficult conversations about their own behavior. Addressing this head-on in the first session—explaining that the discomfort in weeks three and four is normal and part of the process—reduces dropout by about fifteen percent. That's a surprisingly large effect from a single conversation.