How to Actually Do Risk Assessment in a Pharma Setting
Risk Assessment In Pharmaceutical Industry is often presented as a formal, checkbox-driven exercise. In practice, it is something messier. You sit down with a process, a product, or a change proposal, and you try to figure out what can go wrong, how bad it would be, and whether anyone actually cares. That last part is the one most people skip, and it is also the one that gets you in trouble. I will walk through the workflow the way it is done in a real facility, not the way it looks on a compliance training slide. You will get the method, the terminology, the common failure points, and a specific case where the standard approach broke down and what I did instead.
The Core Workflow
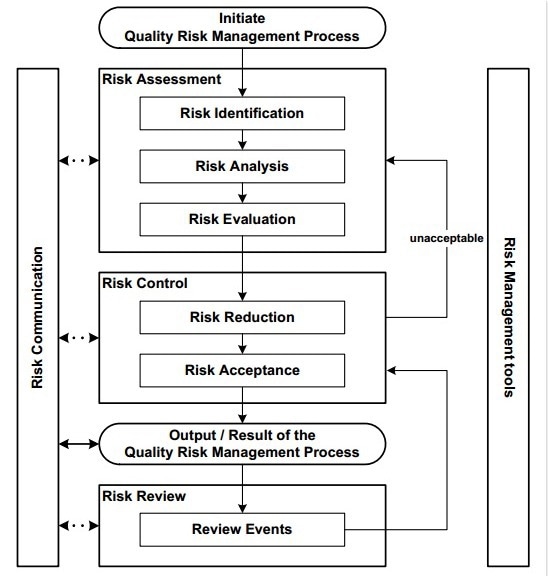
Start with scope. Define what you are assessing, what boundary you are drawing around it, and who needs to sign off on it. A poorly defined scope is the single biggest reason risk assessments fail later. If you are evaluating a new manufacturing line, say so explicitly. If you are evaluating a change to an existing line, list every component, step, and material that could be affected. Vague scope creates vague conclusions, and vague conclusions do not survive an inspection. Next, identify hazards. Use whatever system your facility already uses. Failure Mode and Effects Analysis is the most common for manufacturing processes. Hazard Analysis and Critical Control Points is standard for food-contact and water systems. Ishikawa diagrams, event trees, and what-if analysis all have their place. Pick one and stick with it for a single assessment. Mixing methods mid-project creates internal contradictions that auditors notice. After identification, assess severity, occurrence, and detection. This is the standard RPN-style triad, even if your organization calls them different things. Severity is about impact on product quality, patient safety, or regulatory standing. Occurrence is how often the failure mode is expected to happen under normal operating conditions. Detection is how likely your controls are to catch it before it reaches the patient or causes a batch failure.
Rate each factor on a scale. Most pharma companies use a 1-to-5 or 1-to-10 scale. Be consistent across your team. I have seen teams argue over whether a three means high or medium risk because nobody wrote down what each number actually represents. Write it down. Reference it every time. Combine the ratings. Multiply severity by occurrence by detection, or use whatever matrix your quality unit has approved. The result is your risk priority. High numbers get remediation plans. Lower numbers may get monitoring. Some organizations set an action threshold, like anything above 100 on a 1-to-10 scale requiring immediate control enhancement. Others use color coding. Whatever the system, document the threshold and apply it consistently. Then come up with controls. Engineering controls first. Administrative controls second. Personal protective equipment last. This order matters. It is not just a hierarchy for safety compliance. It is also the hierarchy of reliability in pharmaceutical manufacturing. A engineering fix like a closed transfer system reduces human error more effectively than a written procedure ever will. The written procedure can always be ignored or skipped. The hardware usually cannot.
Get the Full Details
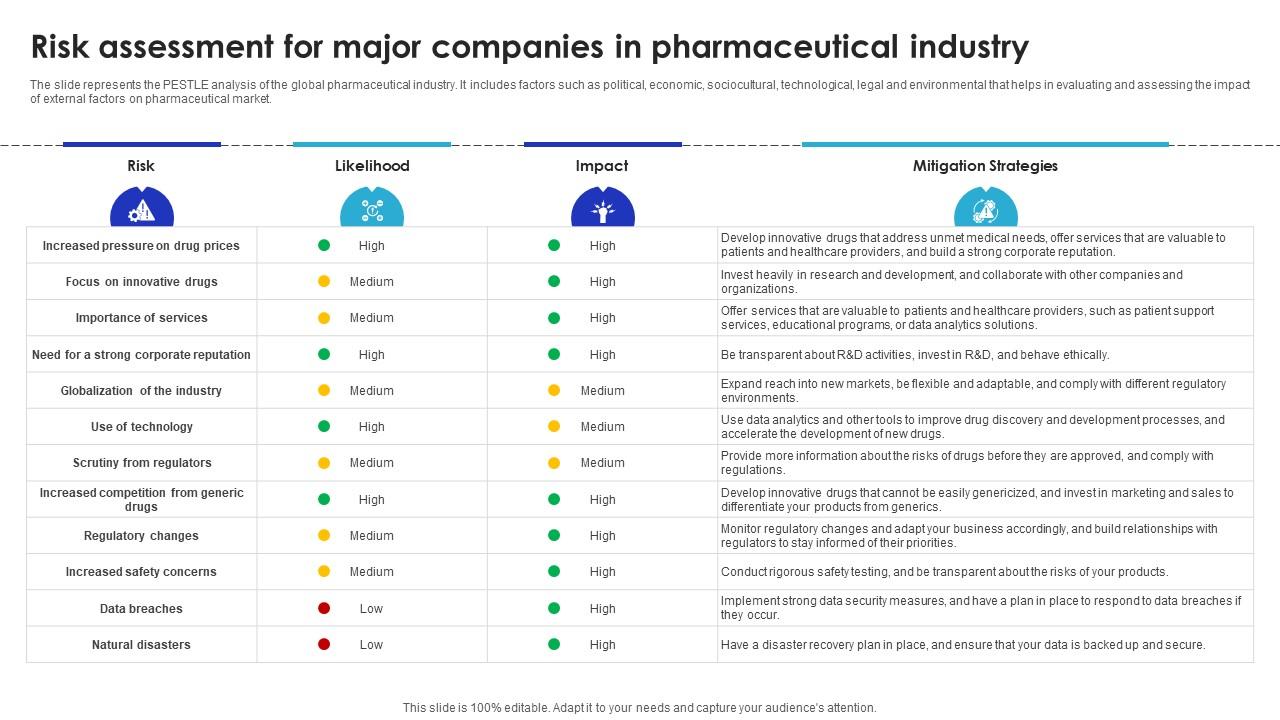
Document everything. Not because auditors love paperwork, but because risk assessments are living documents. When a change occurs, when a deviation happens, when a new complaint rolls in, you go back to the assessment and see whether your controls still make sense. If you never update it, it becomes noise. Noise is worse than nothing during an inspection because it suggests you stopped paying attention.
Tools and Methods That Actually Work
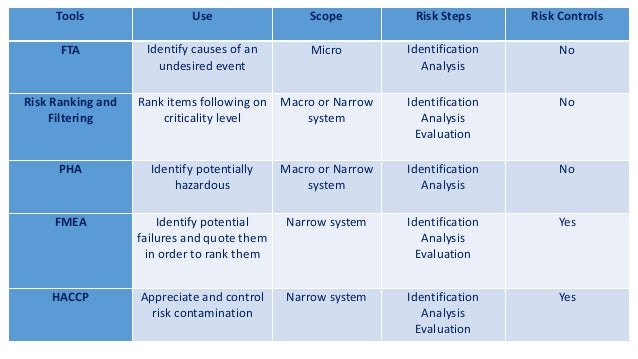
FMEA remains the workhorse. It is detailed, it forces you to think through failure modes one by one, and it produces a paper trail that regulators accept without issue. The downside is time. A full FMEA for a complex aseptic fill-finish process can take two to three weeks with a cross-functional team. That is not a complaint. It is a reality check. If someone promises you a thorough FMEA in two days, they are either cutting corners or they do not understand the process well enough to assess it properly. HACCP works well for process steps where a failure is binary: either the critical limit is met or it is not. Sterilization cycles, terminal sterilization validation, and cleanroom HVAC qualification all benefit from this approach. The limitation is that HACCP is not great at capturing gradual degradation or rare compounding failures. If your risk is about something degrading over time rather than a discrete event, switch to a different tool or layer methods together. Event trees are useful for tracing what happens after an initial failure. They are particularly strong for contamination scenarios. You start with a breach, then branch out based on whether each barrier works or fails. The output is a set of possible pathways to product compromise. This is harder to do quickly. You need good process knowledge and reliable data on barrier effectiveness. Without both, the event tree is just speculation with extra steps.
Qualitative risk matrices are faster but less precise. They work when you need a quick view across many potential risks, like during a change control review with limited data. They break down when you need to justify a decision to a regulatory inspector who asks for numeric rationale. Keep that in mind. If you know your assessment might face scrutiny, spend the extra time on a quantitative or semi-quantitative approach.

A Real Case Where the Standard Approach Failed
About four years ago, my team was assessing risk for a new lyophilization cycle on an existing product line. The standard FMEA listed common failure modes: chamber pressure loss, condenser temperature excursion, vial breakage, stopper contamination. The RPN scores came out moderate across the board. By the matrix, nothing required immediate action. The cycle moved forward. Two months into commercial production, we started seeing occasional sub-potent batches. The issue was not any of the failure modes we had identified. It was a rarely occurring interaction between the chamber pressure ramp rate and the product's collapse temperature margin. During the drying phase, when pressure dropped faster than the product's structural integrity could handle, micro-fractures formed in the cake. The fractures were invisible during visual inspection and did not affect appearance or particulate count. They affected dissolution profiles and assay results in about one out of every sixty to eighty batches. The standard FMEA had missed it because we evaluated the pressure ramp in isolation from the product's thermal behavior. We treated them as separate risk categories. That is a common blind spot. Process parameters interact. Product properties shift across scale. Temperature, pressure, and drying time are coupled variables, not independent checkboxes.
The workaround was a combination of design of experiments and a revised risk assessment. We ran DoE runs varying pressure ramp rates, shelf temperature, and product concentration simultaneously. We mapped the response surface for cake integrity and identified a narrow operational window. Then we updated the risk assessment to include this interaction as a high-severity, low-occurrence hazard with a specific control: in-process monitoring of cake appearance using a validated camera system at the end of the primary drying stage. We also tightened the chamber pressure specification during that phase. This took about six weeks total, including the revised assessment, the DoE, and a revalidation batch. It was not cheap. But it was cheaper than a potential recall or a warning letter, and it gave us a defensible control strategy that held up during the subsequent inspection.
Advanced Nuances Beginners Miss
First, risk is not static. A risk assessment is a snapshot, not a permanent status. When you change a supplier, modify a cleaning procedure, introduce a new raw material, or see a deviation that seems unrelated, the assessment needs review. Many facilities treat risk assessments as set-and-forget documents. That assumption is wrong and it is one of the most common findings in regulatory inspections. If your risk assessment does not reflect changes made after its approval date, an inspector will flag it. Second, detection rating is often underestimated. Teams focus on severity and occurrence because those feel more concrete. Detection feels abstract because it depends on how well your monitoring system actually works under real conditions. A sensor might be specified to detect a temperature excursion, but if the alarm timeout is set too long or the calibration interval is too wide, detection is poor. Write down your actual detection capability, not the theoretical capability from the equipment manual. I have seen detection rated as high simply because the instrument exists, even though the instrument had not been calibrated in nine months and the alarm had been disabled by a shift supervisor who found it annoying. Third, rare events are hard to assess but critical. Low-occurrence, high-severity risks are the ones that define drug safety. A contamination event causing a recall or a patient injury is low probability but max severity. If your risk matrix gives equal weight to a frequent mild defect and a rare serious one, your prioritization will be wrong. Consider using a separate track for high-severity risks regardless of occurrence. Treat them as unacceptable until proven controllable. That is a conservative stance, but conservatism is appropriate when patient safety is on the line.
Common Pitfalls and How to Avoid Them
The most frequent mistake is using the same risk assessment for different purposes. A risk assessment written for a regulatory submission is not the same document as one written for internal process improvement. The regulatory one needs formal language, traceability, and sign-offs. The internal one can be more flexible. Mixing them creates unnecessary burden or, worse, a document that satisfies neither audience. Another mistake is over-reliance on historical data. Historical data is useful. It is not sufficient. If you only assess risk based on past deviations, you are assessing the risk of things that already happened. You are not assessing the risk of things that have not happened yet. Combine historical data with engineering judgment, process understanding, and predictive modeling when possible. Predictive modeling is not always available or accurate, but even a rough model is better than pure hindsight. Team composition matters. A risk assessment done by one person from the quality unit is almost always incomplete. You need process engineering, manufacturing, QC, and sometimes clinical or regulatory input depending on the scope. I have seen assessments miss entire categories of risk because the person writing them had never worked on the production floor. That is not a criticism of quality staff. It is a structural observation. Risk assessment is a team sport. If you assign it to one person, you are assigning it to the wrong person.
LIMITATIONS AND WHEN THIS APPROACH BREAKS DOWN
Risk assessment in pharmaceutical manufacturing is not a perfect tool. It is a structured way of thinking about uncertainty, and uncertainty does not disappear just because you rated it. The main limitation is that risk assessment can give false confidence. A low RPN score does not mean a process is safe. It means the current controls are adequate according to the criteria you chose. If the criteria are wrong, the score is meaningless. Another limitation is data dependency. Risk assessment requires data on failure rates, detection probabilities, and severity distributions. In pharmaceutical manufacturing, that data is often sparse, especially for new products or novel processes. When data is sparse, the assessment becomes more subjective. Subjective assessments are not invalid, but they should be flagged as such and revisited when real data becomes available. Treating subjective estimates as facts is a mistake. Regulatory expectations also vary. The FDA, EMA, and other agencies have different emphases. FDA tends to focus on patient safety and data integrity. EMA places more weight on quality risk management frameworks and documentation. If you operate globally, your risk assessment needs to satisfy both, which sometimes means a broader scope than either would require alone. That is not a flaw in the process. It is a reality of the industry.
Finally, risk assessment does not replace validation. Validation is evidence. Risk assessment is reasoning. You can have the best risk assessment in the world and still produce a failed batch if your validation is insufficient. The two are complementary. Use risk assessment to prioritize what to validate and how rigorously. Do not use it as a substitute for actual testing.

Practical Steps to Improve Your Risk Assessment Practice
Standardize your terminology. Write a brief document defining severity, occurrence, and detection with numeric anchors. Three pages is enough. Reference it in every assessment. This alone reduces most of the inconsistency I see across teams. Keep a deviation log linked to your risk assessments. When a deviation occurs, update the assessment within thirty days. Note the root cause, the corrective action, and any change to the risk rating. This turns your assessments into a learning tool rather than a compliance exercise. Involve operators in the assessment process. They know where the problems actually occur. They know which alarms are frequently ignored and why. Their input will improve your detection ratings and your control recommendations more than any amount of document review.
Review assessments annually or when significant changes occur, whichever comes first. Mark the review date on the document. Set a reminder. If the reminder goes unanswered, escalate it. Annual review is not optional in most quality systems, and even where it is not explicitly required, skipping it is a gap that will show up eventually. Use a risk register to track open items. A risk register is a living table listing identified risks, their ratings, assigned owners, and status. It keeps the assessment visible and actionable. Without it, risk assessments become filing cabinet artifacts. Files do not prevent failures. Action plans do. If you need a starting template, most pharmaceutical companies use a modified ICH Q9 Annex 1 format for sterility-related assessments and a custom FMEA template for manufacturing process assessments. There are publicly available templates from regulatory bodies and professional organizations. Adapt them to your facility. Do not copy them verbatim without reviewing the criteria against your actual processes.
The goal is not to produce a perfect risk assessment. The goal is to produce a useful one. Useful means it identifies real risks, recommends appropriate controls, and is updated when conditions change. That is a high bar, but it is achievable with discipline and a willingness to revisit assumptions when the data says they are wrong.

