How to Actually Use Rn Icu Medical Assessment Answers Without Failing Your Exam
I spent three years covering ICU shifts and then another two helping nurses prep for their assessment exams. What I learned is that most people approach these materials completely wrong. They treat the answers like trivia instead of clinical reasoning practice. That mistake alone causes half the failures I see. The legitimate sources are limited and most of what floats around online is recycled content from old exam banks that have been updated since. Stick to materials published within the last two years. The AACN Synergy Model for Patient Care and the latest ANCC guidelines changed significantly in 2023 and 2024, especially around sepsis protocols and ventilator management questions. Anything older and you are studying for a test that no longer exists. My go-to resources were the AACN Essentials of Critical Care Nursing study guide and the actual practice banks from Pearson VUE's partner sites. The free stuff online works fine for basic assessment patterns but falls apart on the complex hemodynamic scenarios that show up on the harder sections.
The Assessment Framework Itself
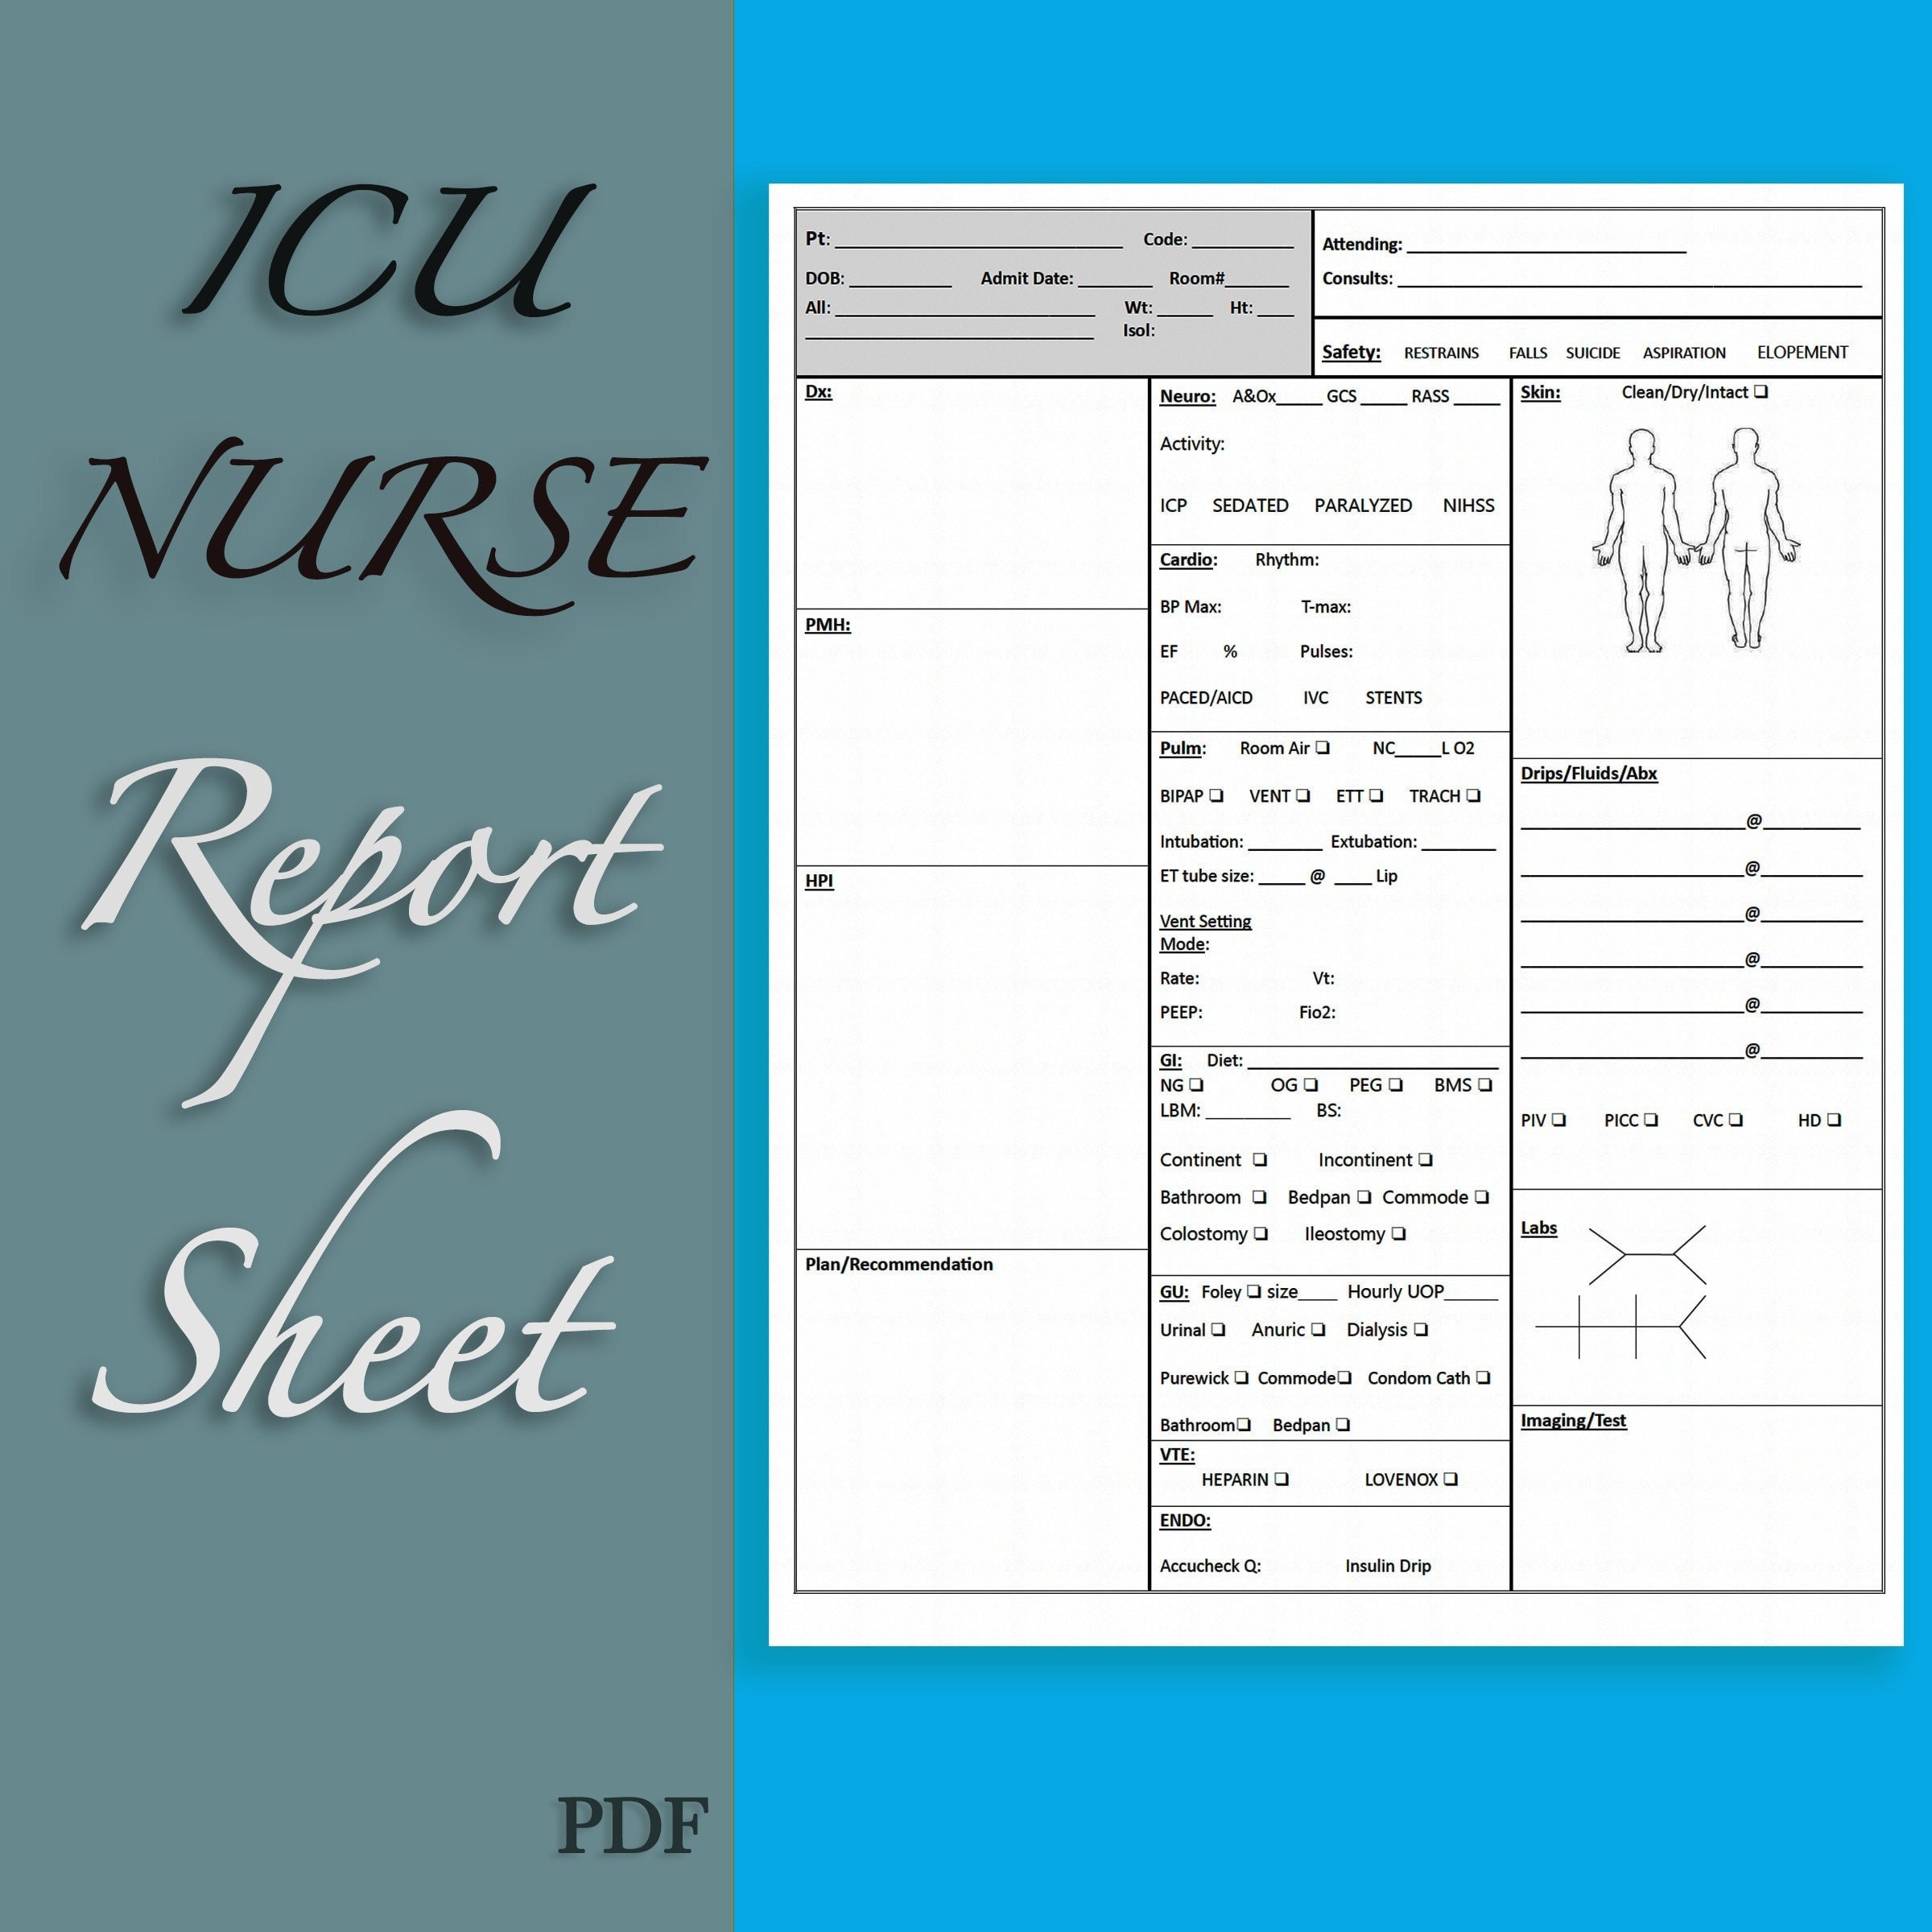
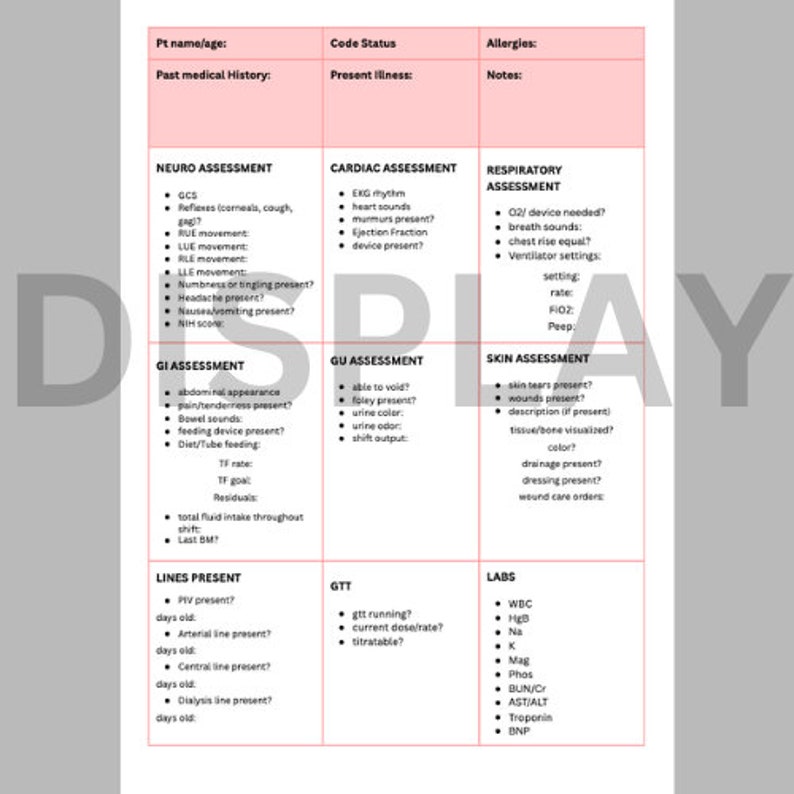
ICU medical assessments follow a structured but flexible approach. You are evaluating airway, breathing, circulation, disability, exposure, and then layering in device-specific monitoring. The key difference from med-surg is that in the ICU every system is already compromised or being supported by technology. Your assessment has to account for that baseline immediately. I once had a nurse candidate who kept missing questions because she was answering based on textbook normals instead of the patient's actual trajectory. One question described a post-cardiac surgery patient with a central line, arterial line, and chest tubes. The answer choices all looked plausible at first glance. She picked the one about holding a beta blocker because the heart rate was 110. The correct answer was about recognizing that tachycardia in that context is expected and the priority is assessing drain output and hemoglobin, not chasing a number. That pattern repeats constantly across these exams.
How to Study This Material Efficiently
Do not read through the answers. Work the questions like cases. For every question you get wrong, write out the clinical reasoning chain: what finding is abnormal, why it matters in this specific patient context, what intervention follows, and what would make you escalate. Most people skip the why and just memorize the letter. That strategy collapses under the weighted, multi-part questions that make up the exam. I recommend doing timed blocks of 25 questions with no notes, reviewing every answer immediately, and then spending twice as long on the ones you missed. A typical 50-question block plus review takes about 90 minutes. Doing this daily for three weeks before the exam covers more ground than passive reading ever will.
Get the Full Details
Common Pitfalls That Trip People Up
The biggest trap is overinterpreting lab values without clinical context. A potassium of 5.4 on its own sounds dangerous but in a patient on continuous renal replacement therapy with a bicarb of 18 and active hemolysis from a pump, it is routine. The exam tests whether you can separate signal from noise in a noisy ICU environment. Another pitfall is fixating on the first abnormal finding and ignoring trend data. If a question mentions a patient whose MAP has dropped from 85 to 72 over six hours despite increasing vasopressor, that trajectory matters more than the absolute number. The right answer usually involves reassessing volume status or looking for a secondary cause like bleeding or sepsis, not just turning up the pressor.
What These Materials Cannot Do for You
Let me be straightforward about the limitations. No answer key or study guide can substitute for actual ICU hours. The questions simulate clinical judgment but they flatten the complexity. In the real unit you have seven monitors going off, a family member asking questions, and a attending who wants an update every hour. Exams present one patient, one scenario, one correct answer. That simplification helps you study but it also means scoring well on practice tests does not guarantee you will think clearly when something actually goes wrong at 3 AM. If you are short on clinical hours, the workaround I found effective was volunteering for night float shifts before the exam. Even two or three nights in the ICU recalibrated how I read assessment questions. The tactile memory of actually assessing a breath sound or checking a pulse ox waveform under stress makes the written scenarios feel familiar instead of abstract. The most practical tip I can offer is to track your wrong answers by category. If you are consistently missing questions on neuro assessments or acid-base balance, those are your gaps. Spend targeted time there instead of re-doing questions you already understand. This approach typically cuts study time by half while improving retention because you are not reinforcing what you already know.