Why most Root Cause Failure Analysis attempts are useless
I ran over a thousand RCA projects over the years, and the majority were basically theater. Someone fills out a five-whys form, writes "operator error" as the root cause, and moves on to the next incident report. The problem actually recurs three months later. This isn't speculation, it happens constantly in manufacturing, IT operations, and healthcare. The real method is a lot drier than the textbooks make it sound. You need a structured way to trace a failure back through every layer of the system without stopping at the first obvious answer. The framework most people actually need is a combination of fault tree analysis and Ishikawa diagrams, used together, not alternately.
Getting started with Root Cause Failure Analysis
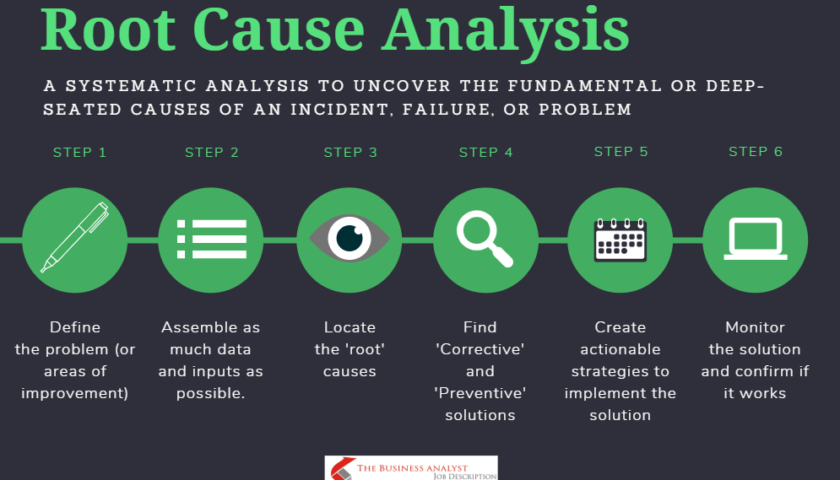
Begin with a precise timeline of the failure. I don't mean "the system went down at approximately 2 AM," I mean the exact sequence of events, alarms, and state changes from the moment the anomaly started to the moment it was contained. If you can't produce this timeline in writing, you aren't ready for the analysis portion yet. Most teams skip this and jump straight into brainstorming, which is how you get vague conclusions. Map the system boundaries before you draw anything. What falls inside your responsibility, what falls outside, and where the handoffs are. The failure point is almost always at a boundary, not in the middle of a well-understood process. I learned this the hard way on a logistics platform we managed. The error codes pointed to a database lock timeout. The DBAs confirmed it. The application team confirmed it. We spent two weeks chasing database performance tuning, adding indexes, restructuring queries. The actual root cause was a third-party shipping carrier's API returning malformed timestamps that caused a cascading insert conflict. Nothing to do with databases at all. The workaround was brutal but effective. I pulled the raw API response logs from the carrier and found the malformed entries were embedded in a batch payload that the application should have rejected at the ingestion layer. We never would have found it by looking at application logs or database metrics alone. We added a validation gateway before the primary write path and the failures dropped to zero within a sprint.
The actual step-by-step process
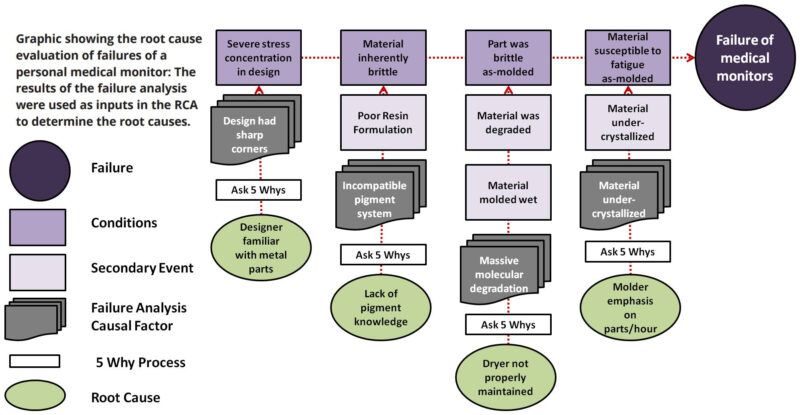
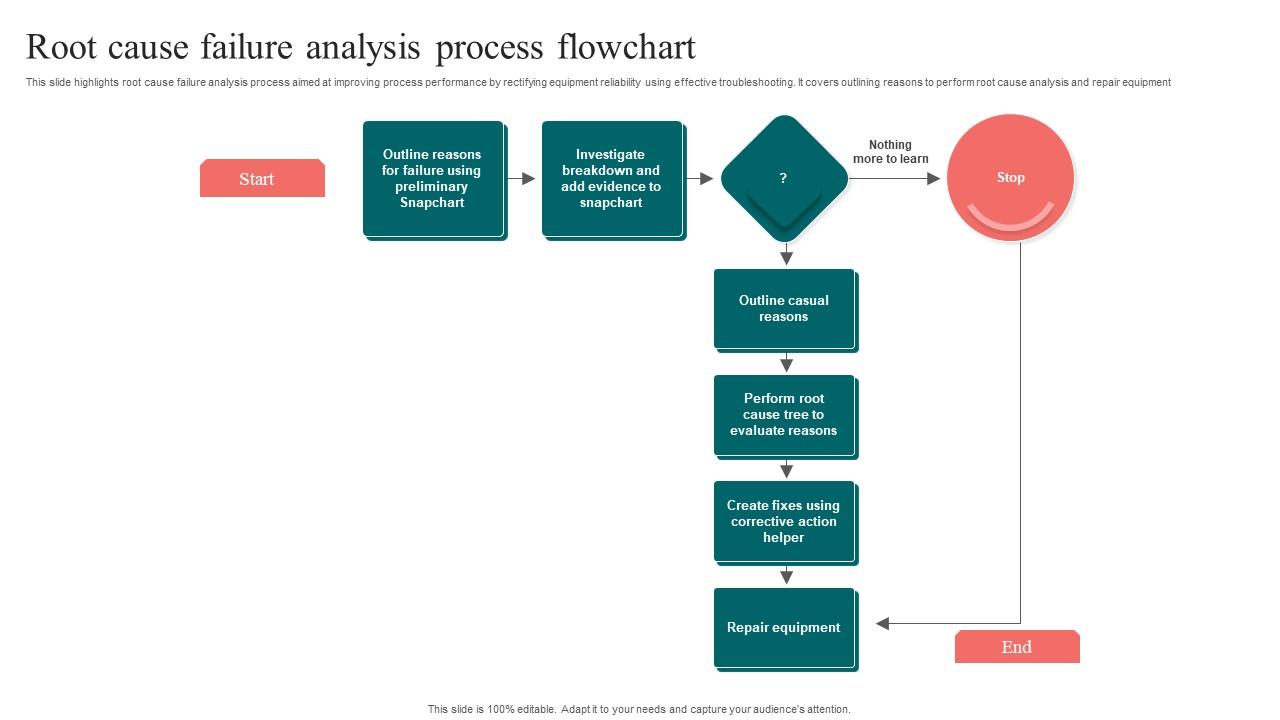
Once you have your timeline and your boundary map, you do a causation chain breakdown. Start from the failure mode itself and work backward through every necessary condition. Each condition is a question: "What had to be true for this to happen?" Then you take the answer to that question and ask the same thing again. Not "why" in the human sense, necessarily, but "what condition enabled this." This is where people mess up. The five-whys method is fine as a mental exercise, but it collapses under complexity. Fault tree analysis forces you to distinguish between AND gates and OR gates. Did multiple things have to align for the failure to occur, or did any one of several independent factors suffice? A fault tree makes this explicit. A five-whys form hides it. Build the fault tree from the top event downward. Identify the immediate causes. For each cause, determine whether it requires other causes to be present simultaneously (AND) or whether it could occur independently (OR). Assign probabilities if data exists. If data doesn't exist, flag it and move on. You'll be surprised how often the analysis is already complete once the tree structure forces you to confront these logic relationships.
Get the Full Details
Apply the Ishikawa diagram to categorize the causal factors you've identified. Man, Machine, Method, Material, Environment, Measurement. This isn't a template exercise, it's a coverage check. If your fault tree has seven causal factors and none of them fall under Measurement, you've probably missed something. Every branch should land somewhere on that diagram. If it doesn't, either the diagram needs expanding or you've got an uncategorized factor that deserves attention.
Counter-intuitive things nobody tells you
Here's something that consistently catches people off guard: the root cause is rarely the thing that caused the failure. It's usually the thing that allowed the failure to go undetected until it became catastrophic. In my experience, detection gaps account for roughly sixty percent of what gets labeled "root cause" in post-mortems. The actual trigger is often benign and recoverable. The reason it wasn't caught is where the system genuinely broke. Another thing: redundant systems are the number one source of false confidence in RCA. When you have backup components, the primary system's degradation can go unnoticed until the backup fails too. I worked on a power distribution incident where the primary UPS had been running degraded for eleven months. Nobody noticed because the secondary UPS absorbed the load perfectly. The root cause wasn't the battery failure. It was the monitoring system that only compared total load capacity, not individual unit health. Two functioning units looked fine. One failing unit looked invisible.
Pitfalls that will waste your time
People treat RCA as a documentation requirement rather than a diagnostic tool. They rush through it to close the ticket. The output is a PDF that satisfies an audit, not a plan that prevents recurrence. This is the single biggest waste of the process. If you're doing Root Cause Failure Analysis and you don't have concrete, assigned, time-boxed action items at the end, you haven't done it properly. Another trap is the hindsight bias that creeps in once you know the answer. You start seeing the causal chain as obvious in retrospect when it was genuinely opaque in real time. Document what was knowable at each point in the timeline, not what you know now. This distinction matters when you're designing controls that need to work under uncertainty, not just under investigation conditions.
When RCA won't help you
Let me be clear about the limitations. Root Cause Failure Analysis is a diagnostic tool for discrete, investigable failures with observable data trails. It does not help with chronic, low-level issues that are diffuse across the system. If your defect rate is five percent and it varies by shift, by supplier batch, and by ambient temperature, an RCA is the wrong tool. You need statistical process control, DOE, or regression analysis. RCA assumes a clear failure event. Chronic problems don't have those. It also fails when the data has been lost or altered. I've seen incidents where log rotation policies had silently truncated evidence for six months. The team conducted a thorough RCA on incomplete data and drew incorrect conclusions. The real cause was buried under deleted records. Validate your data chain before you validate your causal chain. This step takes about ten minutes and saves weeks of misdirection. Finally, RCA doesn't account for intentional behavior. Sabotage, fraud, and deliberate circumvention of controls fall outside the framework. If there's any possibility of malicious action, you need a forensic investigation, not a systematic failure analysis. The methodologies overlap superficially but diverge completely in practice.
Practical tips from the field
Keep a standard data pull checklist so you aren't scrambling for logs and configs after an incident. I maintain a one-page document for each system that lists exactly which logs to extract, which config files matter, and where the backups are. Reduces first-hour triage from two hours to about fifteen minutes. The exact time depends on your setup, but the improvement is consistent. Assign a dedicated scribe during the analysis session. People who are talking about the problem can't also document it accurately. The scribe captures the causal chain as it's being built, notes disagreements, and flags assumptions. This alone improves the quality of the final output significantly. Review your past RCAs quarterly. I know that sounds like paperwork, but it's the only way to catch the pattern where the same root cause keeps resurfacing under different incident numbers. We found three separate incidents over eighteen months that traced back to the same undocumented configuration change made by a contractor who had left the company. The quarterly review caught it because the initial investigations each stood alone and looked complete.