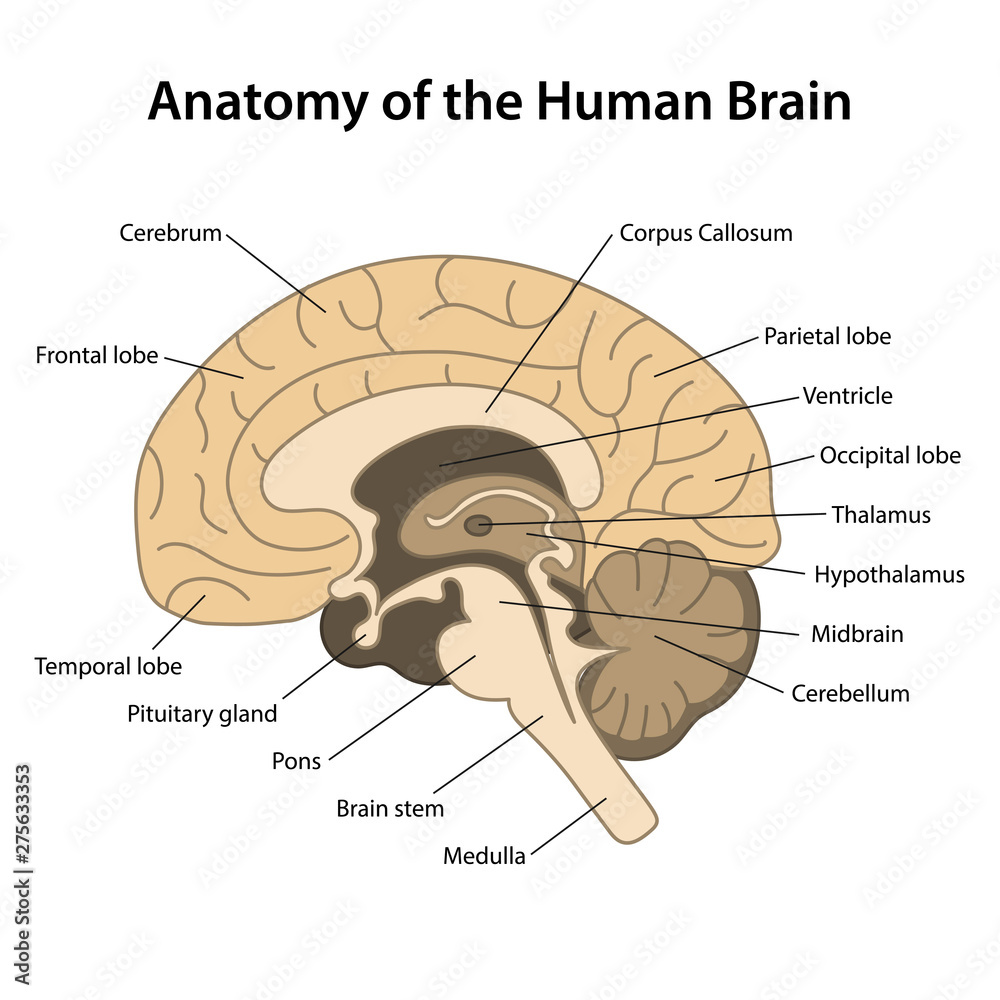
Reading Sagittal MRIs Is Harder Than You Think
Most people learning neuroanatomy start with the sagittal plane because it's the most intuitive. You can see the whole midline architecture in one slice – corpus callosum arching over the ventricles, brainstem dropping down, cerebellum tucked behind. It looks clean on textbook diagrams. Real clinical scans are messier. Motion artifact, partial volume effects, and patient positioning errors turn what should be a straightforward midline view into something you have to work for. I spent years reading sagittal sequences for pituitary and skull base pathology. The midline sagittal cut is arguably the single most important plane in neuroradiology, which is why getting it right matters so much. But here's the thing that doesn't get emphasized enough: a properly acquired sagittal scan requires the patient's head to be positioned with the interaural line perpendicular to the long axis of the scanner bore. If the head is tilted even fifteen degrees, your midline structures shift laterally and you're no longer looking at true midline anatomy. You're looking at a parasagittal slice that mimics midline but isn't. I've seen this cause missed lesions more than once – a small pituitary microadenoma hiding just off-center because the technologist didn't verify alignment before running the sequence.
What You're Actually Looking At in a Sagittal Cut Of Brain
The standard sagittal sequence on a 1.5T or 3T scanner is usually a T1-weighted spin echo or gradient echo, sometimes a T2 FLAIR depending on what the referring clinician is asking about. A typical acquisition runs about 5 to 8 minutes for a standard 5-millimeter slice thickness with a 1-millimeter gap. At 3T with thinner slices – 2 to 3 millimeters – you're looking at maybe 10 to 12 minutes depending on the coil and parallel imaging factors. Midline structures to systematically check in order: the corpus callosum should show normal thickness throughout its body, the genu shouldn't be attenuated, the splenium should have uniform signal. The third ventricle is a slit, not a dilated cavity. The pituitary stalk sits just anterior to the infundibulum and should track straight up to the hypothalamus without deviation. The brainstem shows the normal curvature – midbrain, pons, medulla – without flattening or kinking that would suggest tonsillar herniation. The cerebellar vermis should be intact and symmetric. On T2-weighted sagittal images, the CSF in the aqueduct of Sylvius should be bright and patent. A narrowed or obscured aqueduct on sagittal view is an early sign of obstructive hydrocephalus and something you catch before it becomes an emergency.
Common Pitfalls That Waste Time
The biggest issue I see in practice is mistaking a slightly off-midline sagittal slice for a true midline cut. The anatomical landmarks look similar enough that a hurried reader won't notice until something doesn't add up. The lateral ventricles will appear asymmetric if you're even a centimeter off midline. The mammillary bodies should sit right at the posterior edge of the optic chiasm on a true midline view – if they're displaced or one is prominently visible while the other isn't, your slice is parasagittal. Another problem is susceptibility artifact from dental work. Even with modern shimming techniques, someone with fillings or braces will have signal dropout in the anterior cranial fossa that can completely obscure the frontal pole and inferior frontal lobes on sagittal images. I had a case where a 4-millimeter meningioma at the olfactory groove was invisible on the initial sagittal series because of this artifact. Switching to a higher field strength scan with specific frequency-selective saturation bands around the dental region cleared it up and the lesion became obvious. Not every facility has a 3T scanner available, but it's worth knowing when the answer isn't in the image you're looking at. Gradient echo sagittal sequences are useful for detecting cavernomas and old hemorrhage because of their sensitivity to blood products, but they're also the most vulnerable to motion degradation. A patient who can't hold still for more than thirty seconds will produce a sagittal GRE sequence that's basically unreadable. Spin echo or fast spin echo sequences tolerate motion better and should be your default when patient cooperation is limited.
Get the Full Details

When Sagittal Imaging Falls Short
Sagittal cuts alone cannot reliably characterize suprasellar masses. A craniopharyngioma, a Rathke's cleft cyst, and a tuberculum sellae meningioma can all look similar in sagittal plane – they're all in the same anatomical corridor. You need coronal images to assess lateral extension into the cavernous sinus and to see whether the carotid arteries are being displaced or encased. Axial images are necessary for evaluating the temporal lobes and the posterior fossa circulation. A sagittal-only workup of sellar pathology is incomplete by definition. Similarly, sagittal diffusion-weighted imaging has limited utility in the posterior fossa due to severe susceptibility artifact from the skull base. An ischemic stroke in the basilar artery territory might be completely missed on sagittal DWI. You need axial DWI for posterior circulation assessment. This isn't a criticism of the sagittal plane itself – it's just a boundary condition that people forget when they're trying to memorize protocol checklists. If you're working with lower-field scanners or older hardware, sagittal resolution drops noticeably. A 1.5T machine from ten years ago will struggle to resolve the internal architecture of the corpus callosum in a patient with multiple sclerosis. You'll see the plaques as hyperintensities on T2, but determining whether they're truly periventricular or just adjacent to the ventricular surface becomesguesswork without the higher resolution of a modern 3T system. This limitation is mostly relevant in resource-constrained settings, but it's real and it affects diagnostic confidence.
Practical Tips That Actually Help
Always scroll through the entire sagittal stack before committing to a diagnosis. A single "perfect" midline slice can be misleading if the pathology is just anterior or posterior to it. I developed the habit of checking slices three millimeters on either side of the midline before calling anything normal. It adds maybe twenty seconds to your reading time and has caught lesions that would otherwise have been missed. When evaluating the pituitary, look at the dynamic contrast-enhanced sagittal series if it's available. A normal pituitary enhances within thirty seconds of gadolinium injection. A microadenoma typically enhances more slowly and will appear relatively hypointense during the early phase. By the time you're looking at the delayed sagittal images at six to eight minutes, the lesion may have equilibrated and become isointense – that's when it disappears into the background. Timing matters more than anything else in pituitary imaging. If you're learning to read sagittal anatomy, start by orienting yourself on the landmarks before you try to detect pathology. Find the corpus callosum first. Trace it from genu to splenium. Find the brainstem. Find the fourth ventricle between them. Once those three structures are anchored in your visual field, everything else falls into place. It takes about a week of focused practice to build that automatic recognition, but after that it's just pattern matching and you're reading at speed.


