Working Scar Tissue Directly Changes How It Organizes
Scar tissue forms when the body lays down collagen fibers in a single direction to patch a wound quickly. That's efficient for healing but useless for movement. The fibers cross in neat parallel lines, which means the scar glides in one plane and snags in every other direction. Over months and years, that tissue fuses to the underlying fascia, muscle, and even nerve endings. You feel it as tightness, restricted range of motion, or a dull ache that shows up when you stretch a certain way. Most people assume this is permanent. It isn't, but working on it requires a specific approach and a lot of patience. Scar Tissue Massage Therapy is the process of applying targeted mechanical pressure to break up those aligned collagen bundles and encourage the tissue to reorganize along more functional lines. It's not about rubbing the surface harder. It's about using sustained pressure at the right depth to physically separate the scar from the layers beneath it and then mobilizing it through range of motion. The technique takes time. A single session on a mature, decades-old scar might only produce a few minutes of actual work per square centimeter, and you'll likely need six to twelve sessions before you see real change. The good news is that the tissue does respond. I've seen post-surgical scars from abdominoplasties that hadn't moved in five years gain meaningful glide after about eight weeks of consistent work.
What Actually Happens During a Session
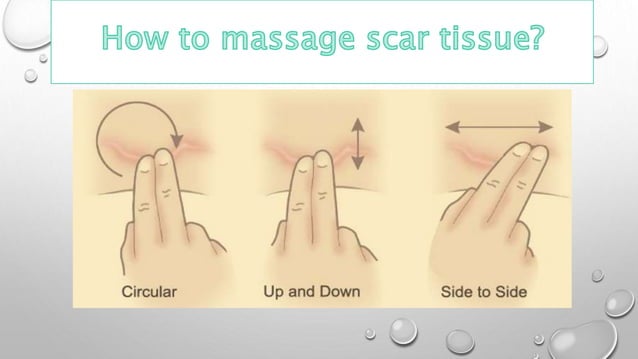
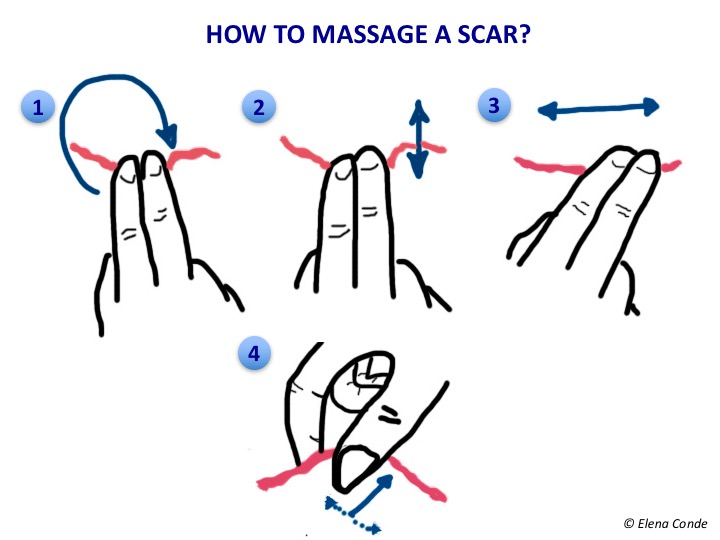
The therapist identifies the scar's boundaries and tests how freely it moves across the underlying tissue. They press two or three fingers into the skin at the edge of the scar and glide it side to side. If it sticks, that's where the adhesion is. Then they apply slower, deeper pressure directly over the scar line, moving perpendicular to the fiber orientation. The goal is to create a shearing force that physically separates the scar from the fascia underneath. This takes about two to four minutes per spot. After that, they move through passive and active range of motion to stretch the tissue while it's warm and pliable. The whole session is usually forty-five to sixty minutes for one area. I worked on a client last year who had a C-section scar from twelve years prior. She'd never had any real work done on it and complained of lower back pain that worsened after sitting for long periods. The scar was completely anchored to the rectus sheath with zero mobility. I spent the first three sessions just working on superficial glide because the adhesion was too dense to tackle deep right away. By session four, I was able to lift the scar slightly off the underlying tissue. By session eight, she reported the back pain had dropped significantly. She continued once a month for maintenance. It wasn't a cure for everything, but it was the most impactful thing we did for her.
Common Mistakes That Slow Things Down
The biggest mistake is using fast, surface-level strokes. Friction rubs the skin but doesn't reach the adhesive bonds. The pressure needs to be slow and deep enough that you can feel the tissue moving under your fingers. Another mistake is working only on the scar itself without addressing the surrounding tissue. The scar doesn't exist in isolation. The fascia above and below it is almost always tightened from compensatory patterns. If you only focus on the line of the scar and ignore the neighboring areas, you'll waste half your session. A less obvious mistake is ignoring the timeline of the scar. Fresh scars under six weeks old should not receive aggressive manual therapy. The wound hasn't fully closed and the collagen is still laying down. Massaging it too early can actually disrupt healing and make the scar worse. Wait until the wound is fully epithelialized and the tissue has matured. For surgical scars, that's usually eight to twelve weeks minimum. For injury-related scars, it depends on severity. When in doubt, ask a medical professional before starting any work. There's also a misconception that more pressure equals better results. It doesn't. Pressing too hard causes the tissue to guard and tighten, which defeats the purpose. You want enough pressure to feel the adhesion release, not so much that the person flinches or holds their breath. The release usually happens as a gradual softening over several minutes, not a sudden pop. If you're waiting for a crackling sensation, you're chasing something that rarely happens and isn't actually the goal.
Get the Full Details

Limitations You Need to Know
Scar tissue massage therapy does not work for every type of scar. Hypertrophic scars and keloids are different animals. Keloids in particular tend to grow beyond the original wound boundary and are driven by genetic and inflammatory factors. Massage alone won't flatten a keloid. It might reduce some discomfort around it, but the primary treatment for keloids is corticosteroid injection, silicone sheeting, or laser therapy. Don't waste six weeks on a keloid expecting manual therapy to reshape it. Another limitation is the density of old, mature scars. A scar that's twenty or thirty years old with thick, rope-like bands will respond very slowly. Some of that tissue has essentially calcified in terms of its mechanical behavior. You might see marginal improvement after twelve sessions, and the gain might only be a few millimeters of glide. In those cases, combining massage with instrument-assisted soft tissue mobilization (IASTM) tools like a Graston-style instrument can sometimes accelerate progress. The metal tool allows you to apply more focused pressure without the fatigue you'd get from using your fingers for the same amount of time. Nerve-related scars are another scenario where massage has a ceiling. If the scar has trapped or entrapped a nerve, the symptoms are burning, shooting pain, or numbness. Manual therapy might relieve some of the surrounding tension, but if the nerve is physically compressed, no amount of massage will free it. That requires medical evaluation and potentially surgical release. Pushing through nerve pain during a session is a bad idea. If the person feels electric shock sensations or increased numbness, stop immediately and recommend they see a doctor.
What You Can Do Between Sessions
Consistency matters more than intensity. Ten minutes of gentle scar mobilization daily beats one aggressive hour once a week. The tissue needs regular, moderate stimulation to keep remodeling. Use your fingertips to pick up the scar and roll it gently between your skin and the underlying tissue. Move in all directions: up and down, side to side, and in small circles. Don't rub the skin surface. Lift and move the tissue itself. Hydration plays a role too. Collagen fibers absorb water and become more pliable when well-hydrated. Drinking adequate water and applying a simple moisturizer or vitamin E oil can make the skin and superficial fascia easier to work with. This isn't a magic bullet for scar appearance, but it does affect tissue texture in a measurable way during mobilization. Heat before the work helps. A warm compress for five to ten minutes increases blood flow and makes the collagen more extensible. I've seen clients who skip this step report less relief after sessions compared to those who take the time to warm the area first. It's a small step that changes the outcome noticeably.
There's no shortcut app or device that replaces hands-on work for this. Wearable vibration tools might provide some temporary relief for discomfort, but they don't create the directional shear forces needed to release adhesions. The evidence for IASTM tools is stronger than for consumer-grade vibrators, but even those work best when used by someone who knows what they're feeling for under the skin. A therapist who understands fascial anatomy can distinguish between a real adhesion release and tissue being bruised. That distinction matters for long-term results.