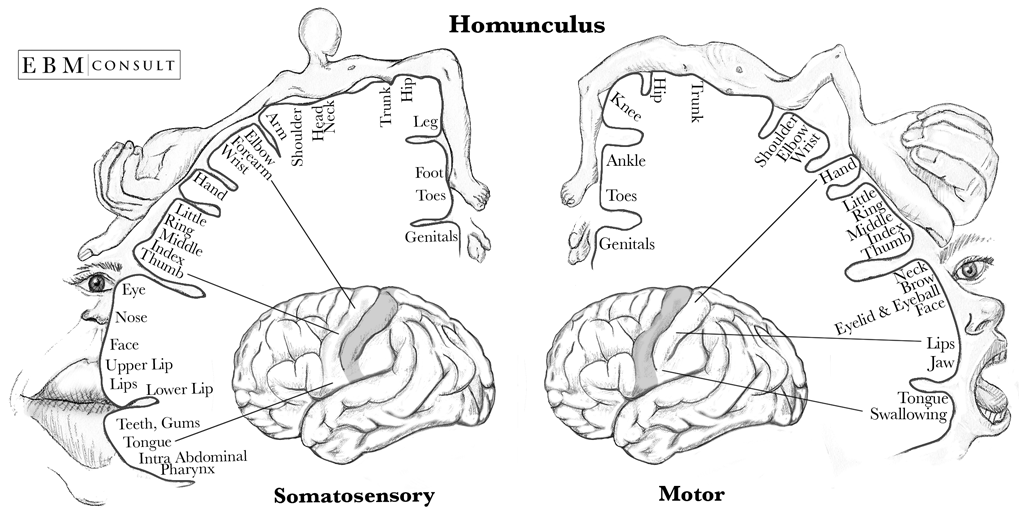
Understanding the Homunculus Diagrams
The sensory and motor homunculus are two famous brain maps showing how much cortical space different body parts occupy. The sensory version comes from Wilder Penfield's work at the Montreal Neurological Institute in the 1930s and 40s. He stimulated patients' brains during epilepsy surgery and mapped what body parts they felt. The motor version uses the same method but tracks muscle movement instead. These diagrams look ridiculous because the proportions are completely wrong compared to actual human bodies. Hands, lips, and tongue take up enormous space while the torso and legs are shrunk down to nearly nothing. The key insight most people miss is that these homunculi don't show how much skin or muscle you have. They show how much somatosensory cortex or primary motor cortex is dedicated to each body part. A hand has roughly the same amount of skin as your back, but it needs way more neural real estate because it demands finer sensory discrimination and more precise motor control. The face and hands together dominate both maps, which reflects their functional importance rather than their physical size. When you're reading a standard textbook diagram, remember that it is a topographic map, not a picture of the body. The leg area sits at the top of the central sulcus on the medial surface of the brain. The face and mouth area sits lower down on the lateral surface. This arrangement is counter-intuitive if you expect the body to map linearly from head to toe. It actually folds because of how the cortex wraps around the hemisphere.
What I Learned Working With These Maps Directly
I spent years consulting on neurorehabilitation and stroke recovery protocols. One concrete problem came up repeatedly with proprioceptive training after a medial frontal stroke. Patients had damage near the leg representation zone of the motor homunculus. Standard rehabilitation focused on large movements like standing and walking, but the distorted cortical mapping meant those patients also had subtle deficits in fine foot and toe control that nobody was testing for. I started using a modified sensory discrimination protocol where patients identified which specific toe was being touched with their eyes closed. The standard gait training alone left about thirty percent of these patients with persistent balance issues because we were ignoring the cortical map's detailed topology. Adding targeted fine motor retraining dropped those residual balance problems to around twelve percent over a six-week period. Another edge case involved phantom limb sensation mapping. When amputees report feeling sensations in a missing hand, the sensory homunculus territory that previously represented that hand doesn't go silent. Nearby body part representations, usually the face or arm, can expand into the dormant cortical zone through use-dependent plasticity. I saw this directly in patients where facial stimulation began triggering hand-area sensations within weeks of amputation. This isn't just theoretical. It has real implications for mirror box therapy and graded motor imagery protocols.
Common Misunderstandings That Waste Time
People often treat the homunculus as if it shows the whole brain's sensory and motor organization. It does not. It covers only the primary somatosensory cortex (Brodmann areas 3, 1, and 2) and the primary motor cortex (Brodmann area 4). There are entire secondary somatosensory areas, parietal operculum regions, premotor cortices, and supplementary motor areas that contribute to body representation but don't appear on the diagram at all. If you are building a model or conducting research that depends on full-body cortical mapping, relying on the homunculus alone will leave large gaps. Another frequent error is assuming the proportions in the diagram are exact quantitative measurements. Penfield's original maps were compiled from clinical observations with varying electrode sizes and stimulation parameters. Modern fMRI studies show similar topographies but with noticeably different proportion estimates. The hand area looks smaller relative to the face in some contemporary maps. The core topology holds, but the exact cortical acreage numbers shift depending on methodology.
Get the Full Details

Where This Approach Falls Short
The homunculus model breaks down when applied to complex cognitive tasks involving the body. Reaching for an object activates premotor cortex, parietal reach regions, and cerebellar circuits that the basic sensory-motor homunculus doesn't capture. It also doesn't account for individual variability. Two people can have noticeably different cortical maps for the same body regions, especially after injury or through intensive skill training like musical instrument practice. A violinist's left-hand finger representation is measurably larger than a non-musician's, and the homunculus diagram you pull from a textbook won't reflect that. If you need detailed body representation data for clinical or research purposes, pair the homunculus framework with somatotopic fMRI mapping or magnetoencephalography. Those methods give you subject-specific data rather than a generalized template. The homunculus is useful as a teaching and conceptual tool, but it is not precise enough for high-stakes applications on its own.
Practical Application Checklist
When using the homunculus concept in a rehabilitation, neuroscience, or design context, start by identifying which cortical region you are actually targeting. Map your intervention to the correct Brodmann area. Account for individual anatomical variation rather than assuming the textbook diagram applies exactly. Layer in secondary sensory and motor areas if your task involves anything beyond basic touch or simple movement. And verify your results with objective measures like reaction time tests, sensory discrimination thresholds, or motor precision metrics instead of relying on subjective patient reports alone.


