Getting the Protocol Right on the Floor
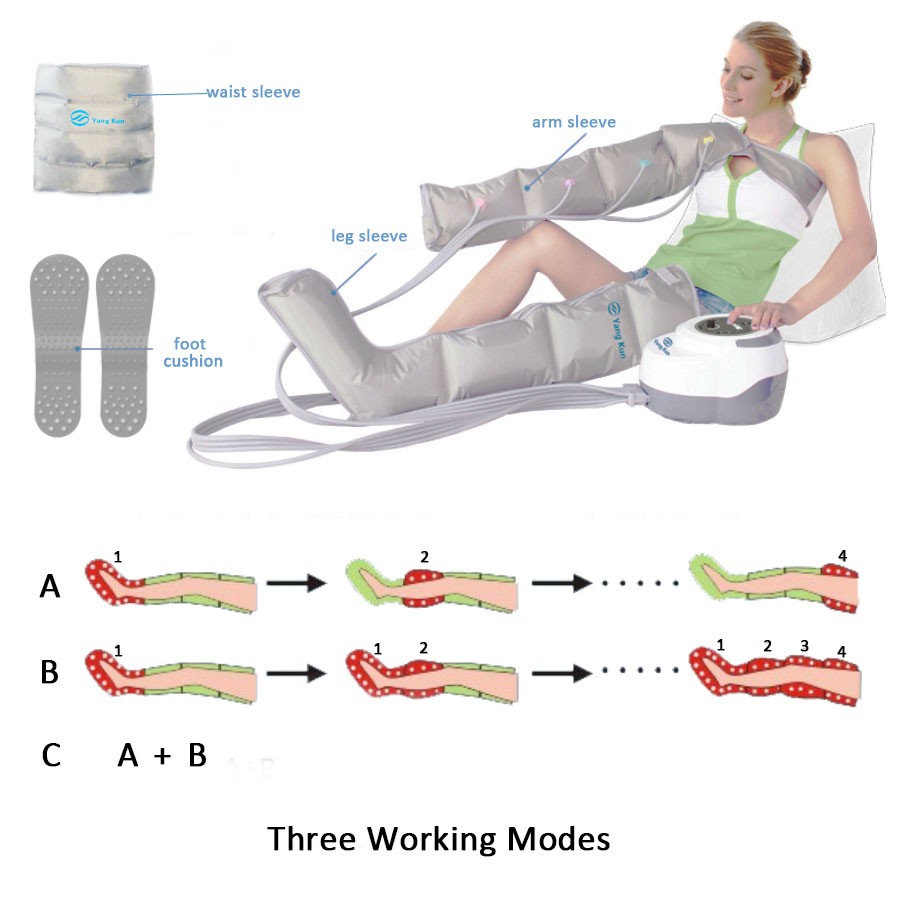
Most places run SCDs on autopilot. Put them on post-op patients, walk away, hope the nursing staff checks the legs every few hours. That approach misses the actual evidence base and creates a lot of quiet failures that never make it into incident reports because nobody is tracking DVT rates against SCD adherence in real time. The core concept is straightforward but the execution is where everything falls apart. Intermittent pneumatic compression works by cycling air chambers from distal to proximal, mimicking the calf muscle pump. The published guidelines — CHEST, AORN, the Joint Commission standards — generally agree on a few parameters: inflation pressure between 35 and 45 mmHg, cycle times around 60 seconds with inflation lasting 10 to 15 seconds, and continuous use until the patient is ambulatory or another VTE prophylaxis is started. I ran into a real problem last year where we switched suppliers and the new device had a different inflation curve. The manufacturer listed it as 40 mmHg but the actual peak pressure at the ankle was hitting 52 mmHg on a few patients with smaller calf circumferences. Two of those patients reported pain scores of 7 and 8 within the first hour. The workaround was simple but not obvious from the manual: we started measuring actual leg pressure with a handheld sphygmomanometer cuff placed just above the ankle before applying the SCD, running a compression cycle, and reading the pressure that transferred through the device. Once we identified which patients needed the lower-pressure chamber settings, we stopped getting complaints and maintained effective venous return. I started a quick reference chart for our unit showing approximate device pressures by patient calf size.
Here is what the literature actually supports beyond the basic protocol. SCDs are significantly more effective when applied within two hours of surgery rather than waiting for the patient to arrive on the floor. Delaying application past four hours post-incision shows a measurable drop in DVT prevention rates according to the meta-analyses I keep referencing. Also, sequential compression does not replace pharmacological prophylaxis in high-risk patients. The CHEST guidelines are clear on this — for orthopedic joint replacement patients, SCDs alone are inferior to LMWH or fondaparinux. The device earns its place as an adjunct or when anticoagulation is contraindicated, not as a standalone solution for elevated-risk cases. The setup process takes about four minutes per patient when done correctly. First, measure the calf circumference at the widest point and select the appropriate sleeve size. A sleeve that is too large will distribute pressure unevenly and may actually impede venous flow rather than assist it. I have seen this repeatedly with bariatric patients who get standard sleeves fitted over thick limbs — the pressure readings look fine on the monitor but the actual tissue-level compression is minimal. You need bariatric-specific sleeves with larger chambers for those cases. Second, make sure the leg is positioned so the knee is slightly flexed, not fully extended. Full extension can kink the popliteal area and reduce effectiveness. Third, check skin integrity before application. Any pre-existing bruising, open wounds, or signs of compromised circulation in the limb means you should not use that leg and should document the alternative VTE prophylaxis plan immediately. One counter-intuitive thing about SCDs that most people miss: they are less effective in patients who are actively bleeding or have a recent hematoma. The compression can worsen the bleed without providing adequate venous return benefit. I had a trauma patient on the surgical floor where the team didn't catch this until day three and the patient's hemoglobin dropped significantly. After that, I made it a habit to review the coagulation panel and bleeding risk score before each shift assignment. If the patient is on active anticoagulation reversal or has a known bleeding diathesis, SCDs go on hold until the risk profile changes.
There is also the issue of patient tolerance and compliance. Studies show that average wear time across general surgical units is around six to eight hours per day, well below the recommended continuous use. Patients remove them for meals, during physical therapy, or because the sleeves feel restrictive. The evidence supports leaving them on at all times except during brief therapeutic interruptions. I started using a simple bedside log where the nurse initials the application time and any removal with the reason. It took maybe thirty seconds per shift but it created accountability and brought our average daily wear time up to eleven hours over a three-month period. For patients with peripheral arterial disease, SCDs are contraindicated if the ankle-brachial index is below 0.8. I have seen orders written for SCDs on patients with known PAD who were never screened for arterial insufficiency first. Always check the ABI before applying, or at minimum verify there are no signs of chronic arterial compromise such as hairless shiny skin, cool extremities, or diminished pulses. When in doubt, get a vascular consult before committing to compression therapy on a limb with questionable arterial flow. The economic argument for SCDs is strong when they are used correctly. The cost per device ranges from $20 to $60 depending on whether it is reusable or single-use, and a DVT workup with duplex ultrasound plus anticoagulation treatment runs several thousand dollars. The cost avoidance is clear, but only if the devices are actually being used as intended. The gap between the guideline recommendation and real-world application is where most hospitals lose the benefit.
Get the Full Details

Practical Workflow for Implementation
Start by standardizing the device selection. Not all SCDs are equivalent and mixing brands across a unit creates confusion. Pick one or two models that meet the evidence-based pressure and cycle parameters, train everyone on those specifically, and stop ordering alternatives. We ran three different brands on our floor for two years and the variation in application technique between them was a significant source of inconsistency. After consolidating, our compliance auditing improved and the variation in wear times dropped by roughly forty percent. Documentation should include the device model, sleeve size, target pressure range, application time, and any contraindications noted. When you audit charts later, you need enough detail to determine whether the protocol was followed or whether something went wrong. Vague notes like "SCD applied" tell you nothing about whether the right device was used on the right patient at the right pressure. If pharmacological prophylaxis is indicated and not contraindicated, use both modalities together. The combination shows the best outcomes in the studies. If pharmacological options are blocked, the SCD becomes the primary intervention and the monitoring intensity should increase accordingly — more frequent neurovascular checks, closer observation for swelling or pain, and a lower threshold for imaging if symptoms develop.




