What You Actually Need to Know Before Buying or Using a Shock Wave Therapy Machine
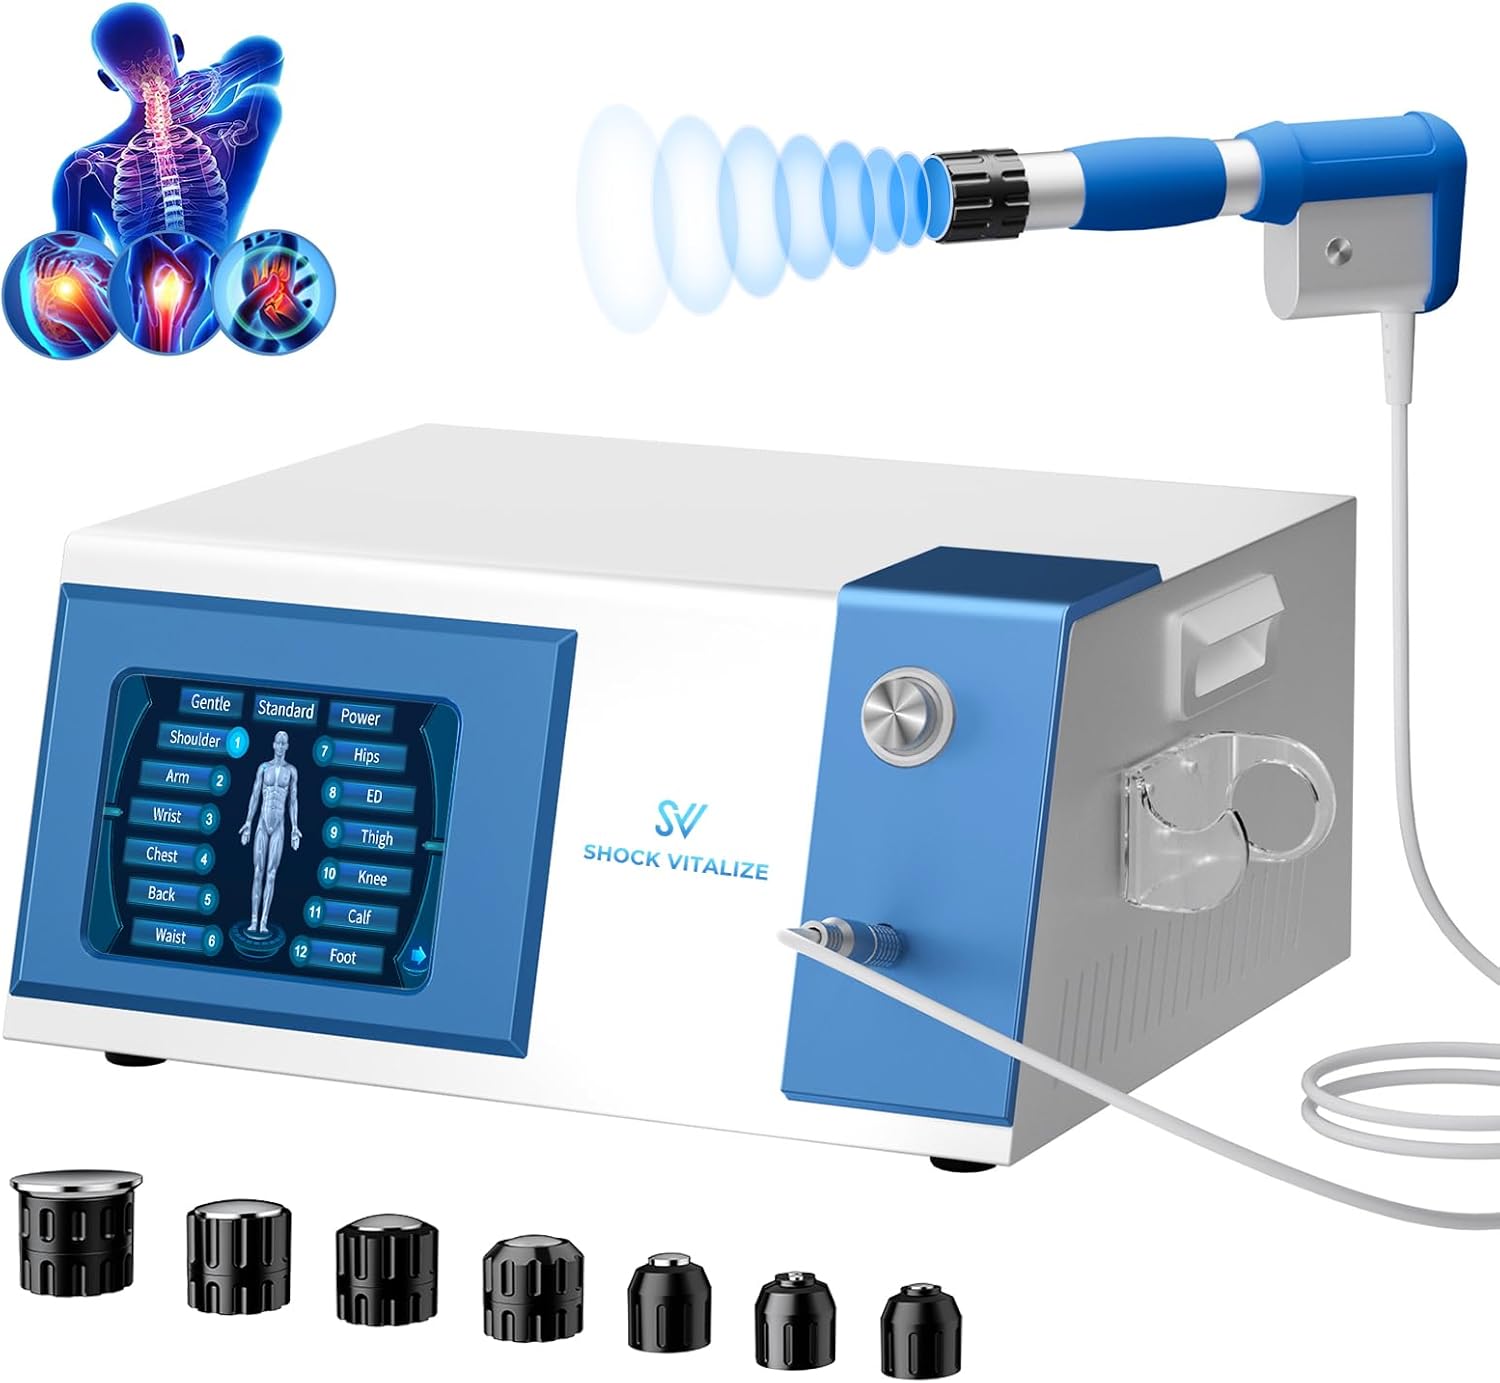
I've been running these devices in a clinical setting for over a decade. The marketing around them is almost always inflated. Here is what the equipment actually does, where it falls apart, and what most people overlook when they set one up for the first time. A Shock Wave Therapy Machine delivers either focused or radial acoustic pulses into tissue. The two types are not interchangeable. Radial devices blast air-driven waves that scatter across a wider area and stay mostly superficial. Focused devices use electromagnetic or piezoelectric arrays to converge energy at a specific depth, usually between 1 and 6 centimeters. You need both kinds if you are doing anything beyond basic soft tissue work. Most cheaper units on the market are radial only, which limits their usefulness significantly. The physics is straightforward enough. A high-energy pressure wave travels through gel coupling medium, hits the fascia or bone interface, and creates microtrauma. That microtrauma triggers a cascading inflammatory response: angiogenesis, neovascularization, and the breakdown of calcified deposits. The body repairs the tissue, and that is the whole mechanism. It sounds dramatic but it is just controlled injury followed by healing.
I used to run a focused unit at 0.25 millijoules per square millimeter for calcific tendinitis of the shoulder. The standard protocol from the manufacturer said three sessions spaced one week apart. What actually happened in practice was different. The first session broke up the bulk of the calcium deposit, but patients reported a sharp increase in pain for about 72 hours after each treatment. I dropped the fluency to two sessions at 0.20 mJ/mm² instead, gave patients NSAIDs to take before coming in, and the compliance rate went up noticeably. The outcomes were the same. The manufacturer's protocol was written for a population that never actually shows up consistently. Here is a thing most guides will not tell you. Pressure matters more than energy setting. A device set to 0.30 mJ/mm² with poor coupling gel contact will underperform a device at 0.18 mJ/mm² that is properly coupled. Air bubbles under the transducer block the wave entirely. I have seen technicians run an entire session without realizing the gel had dried out halfway through. The patient felt nothing. The machine was beeping normally. Make sure you feel the tapping sensation on the skin surface before you start treating deeper structures. Another practical issue that nobody talks about: the skin test. Before any full power pass, fire one low-energy pulse on an area of intact skin near the treatment site. Watch for blanching or immediate wheal formation. That tells you the patient's local vascular response. If the skin reacts aggressively, you dial back the energy and slow the pulse rate. Some people have hyperreactive capillary beds, especially those on blood thinners or with connective tissue disorders. Ignoring this leads to hematomas, not improvements.
Setting Up and Operating the Device Correctly
Start with the patient in a position that puts the target tissue under mild tension. This is not optional. Treating a relaxed biceps brachii for impingement gives you a shallow target depth that shifts with every cycle. Pull the arm slightly across the body. The tissue stabilizes. The focal point stays where you placed it. Apply coupling gel generously. Not a thin layer. A thick layer. Reapply every four to six minutes during longer sessions. Gel dries fast under the transducer head, especially with higher pulse rates. Dry coupling is the single most common reason treatment sessions fail without any obvious error on the machine's display. Map the treatment area in a grid pattern. I use 5 to 10 mm spacing between shots. For acute trigger points, overlap the grid slightly so each zone gets hit twice. For chronic calcifications, use a lower density at first, then increase over subsequent sessions as the tissue becomes more responsive. Tissue tolerance changes. The same settings that crushed a calcification in session two will do nothing by session four if you do not adjust.
Get the Full Details
Pulse frequency usually runs between 4 and 16 Hz. Lower frequencies like 4 to 8 Hz are better for deeper focused work because each pulse has more time to deposit energy before the next one arrives. Higher frequencies like 12 to 16 Hz are fine for radial surface work but waste energy on deep targets. Match the frequency to the depth, not the other way around. Total pulse count depends on the condition. Chronic plantar fasciitis typically needs 2000 to 3000 pulses per session. Calcific tendinitis may need 3000 to 4000. Trigger point work might only need 500 to 1000 per point. More is not better. I have seen therapists blast 6000 pulses into a single area and produce nothing but bruising and patient dropout. The evidence does not support going past 4000 pulses in one session for any indication.
Where This Modality Actually Fails
Shock wave therapy does not work for acute muscle strains. The microtrauma mechanism will make an acute tear worse. It also does not work well for nerve entrapment syndromes unless you are using very low energy as a neuromodulation approach, which requires a focused device and specific protocols. Radial units are essentially useless for nerve issues. Diabetic patients with peripheral neuropathy respond poorly. Reduced microcirculation means the inflammatory cascade that drives healing never really gets going. These patients sometimes report temporary numbness after treatment instead of improvement. It is worth screening for this before committing to a full course. Coagulation disorders and anticoagulant therapy are contraindications. Not just a warning. A hard stop. Hematoma formation over the treatment site can be severe, especially with focused devices at higher energies. I once treated a patient who was on apixaban and had a significant intramuscular bleed that required surgical drainage. The pulse count was only 1500. The medication made the difference.
Tumors in the treatment field are an absolute contraindication. The mechanotransduction effects could theoretically stimulate angiogenesis around a malignancy. This is not theoretical in the sense that it has happened. I do not want to elaborate on a specific case from my early career. Just avoid treating over any known or suspected neoplastic tissue.

Practical Considerations for Buyers
If you are looking at a Shock Wave Therapy Machine for your practice, check the transducer head compatibility first. Many systems lock you into proprietary consumables. The gel pads, coupling heads, and replacement lenses add up to significant recurring costs. A unit that accepts standard third-party transducers will save you money within a year. Ask about this before signing any purchase agreement. Also verify whether the machine has real-time depth adjustment. Some cheaper focused units have a fixed focal point at a single depth. You cannot adjust it. If you are treating structures at varying depths, this limitation makes the device nearly useless. Look for electromagnetic or piezoelectric systems with variable focus range of at least 10 to 60 mm. Calibration matters. These machines drift over time. A focused unit that reads 0.25 mJ/mm² on the display might actually be delivering 0.17 or 0.33 depending on the age of the coil or crystal array. Budget for annual calibration checks, usually around 150 to 300 dollars depending on the service provider. Skipping this is how you end up with inconsistent patient outcomes and no explanation for why.
The data on shock wave therapy is decent for a handful of conditions and weak for most others. Plantar fasciitis, calcific rotator cuff tendinitis, and lateral epicondylitis have solid evidence behind them. Everything else is largely anecdotal or based on small studies with methodological problems. Do not market it as a cure-all. The patients will find out quickly enough. If you are dealing with conditions outside those three indications, consider whether ultrasound-guided injection therapy or dry needling might be more efficient. I switched several of my chronic knee osteoarthritis patients to a structured exercise and injection protocol after realizing the shock wave machine was producing marginal results at best. The time investment was not justified by the outcome. Training is another area that gets glossed over. A two-hour online module does not prepare you to use this equipment safely. Look for hands-on workshops with supervised practice sessions. The difference between knowing the theory and knowing how to adjust in real time based on patient feedback is substantial. I spent about 40 hours of supervised clinical practice before I felt confident running focused shock wave independently. Your learning curve will vary, but do not skip the practical component.
The technology has improved over the years. Newer transducers last longer, cooling systems are more reliable, and software interfaces are less clunky. But the fundamental physics has not changed. The device is a tool. How well it works depends entirely on your understanding of the anatomy, the pathology, and the physics involved. Buy the machine. Then learn how to use it properly.


