Setting Up and Running a Shockwave Protocol
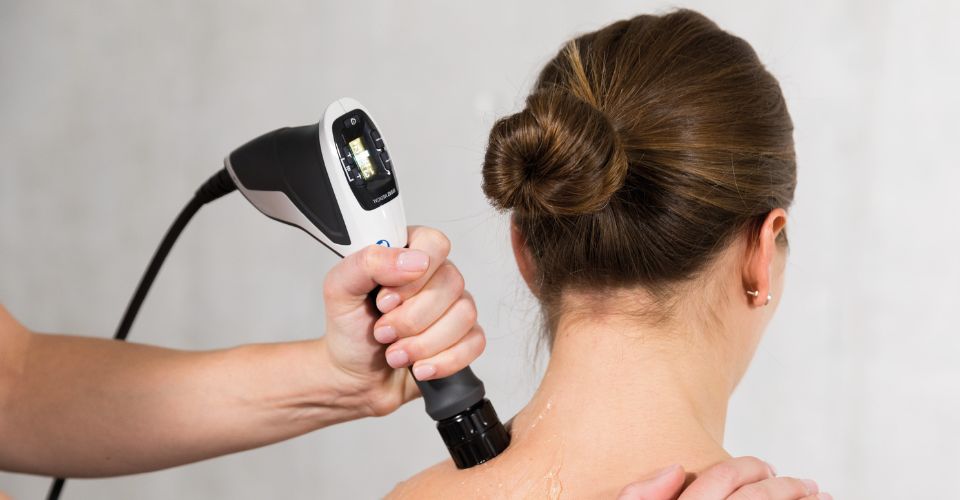
The machine does most of the thinking for you. You just need to pick the right parameters and stay consistent. I use a standard protocol of 240 shocks per session at 4 Hz, applying the transducer with light pressure across the thinning zone. The gel needs to be thick enough to eliminate air pockets. If you can hear a squeaking sound during the pass, you're not getting good energy transfer and the treatment is pretty much useless. Most modern devices come with preset programs. I don't blindly trust them. I adjust based on patient comfort and skin response. The energy flux density typically ranges from 0.08 to 0.25 mJ/mm² for hair loss applications. Lower settings work fine for maintenance. Higher settings are where you see actual changes in follicular cycling, but they also increase the chance of mild scalp tenderness afterward. I usually start patients at 0.12 and build up over four to six weeks if they tolerate it well.
What Shockwave Therapy For Hair Loss Actually Does
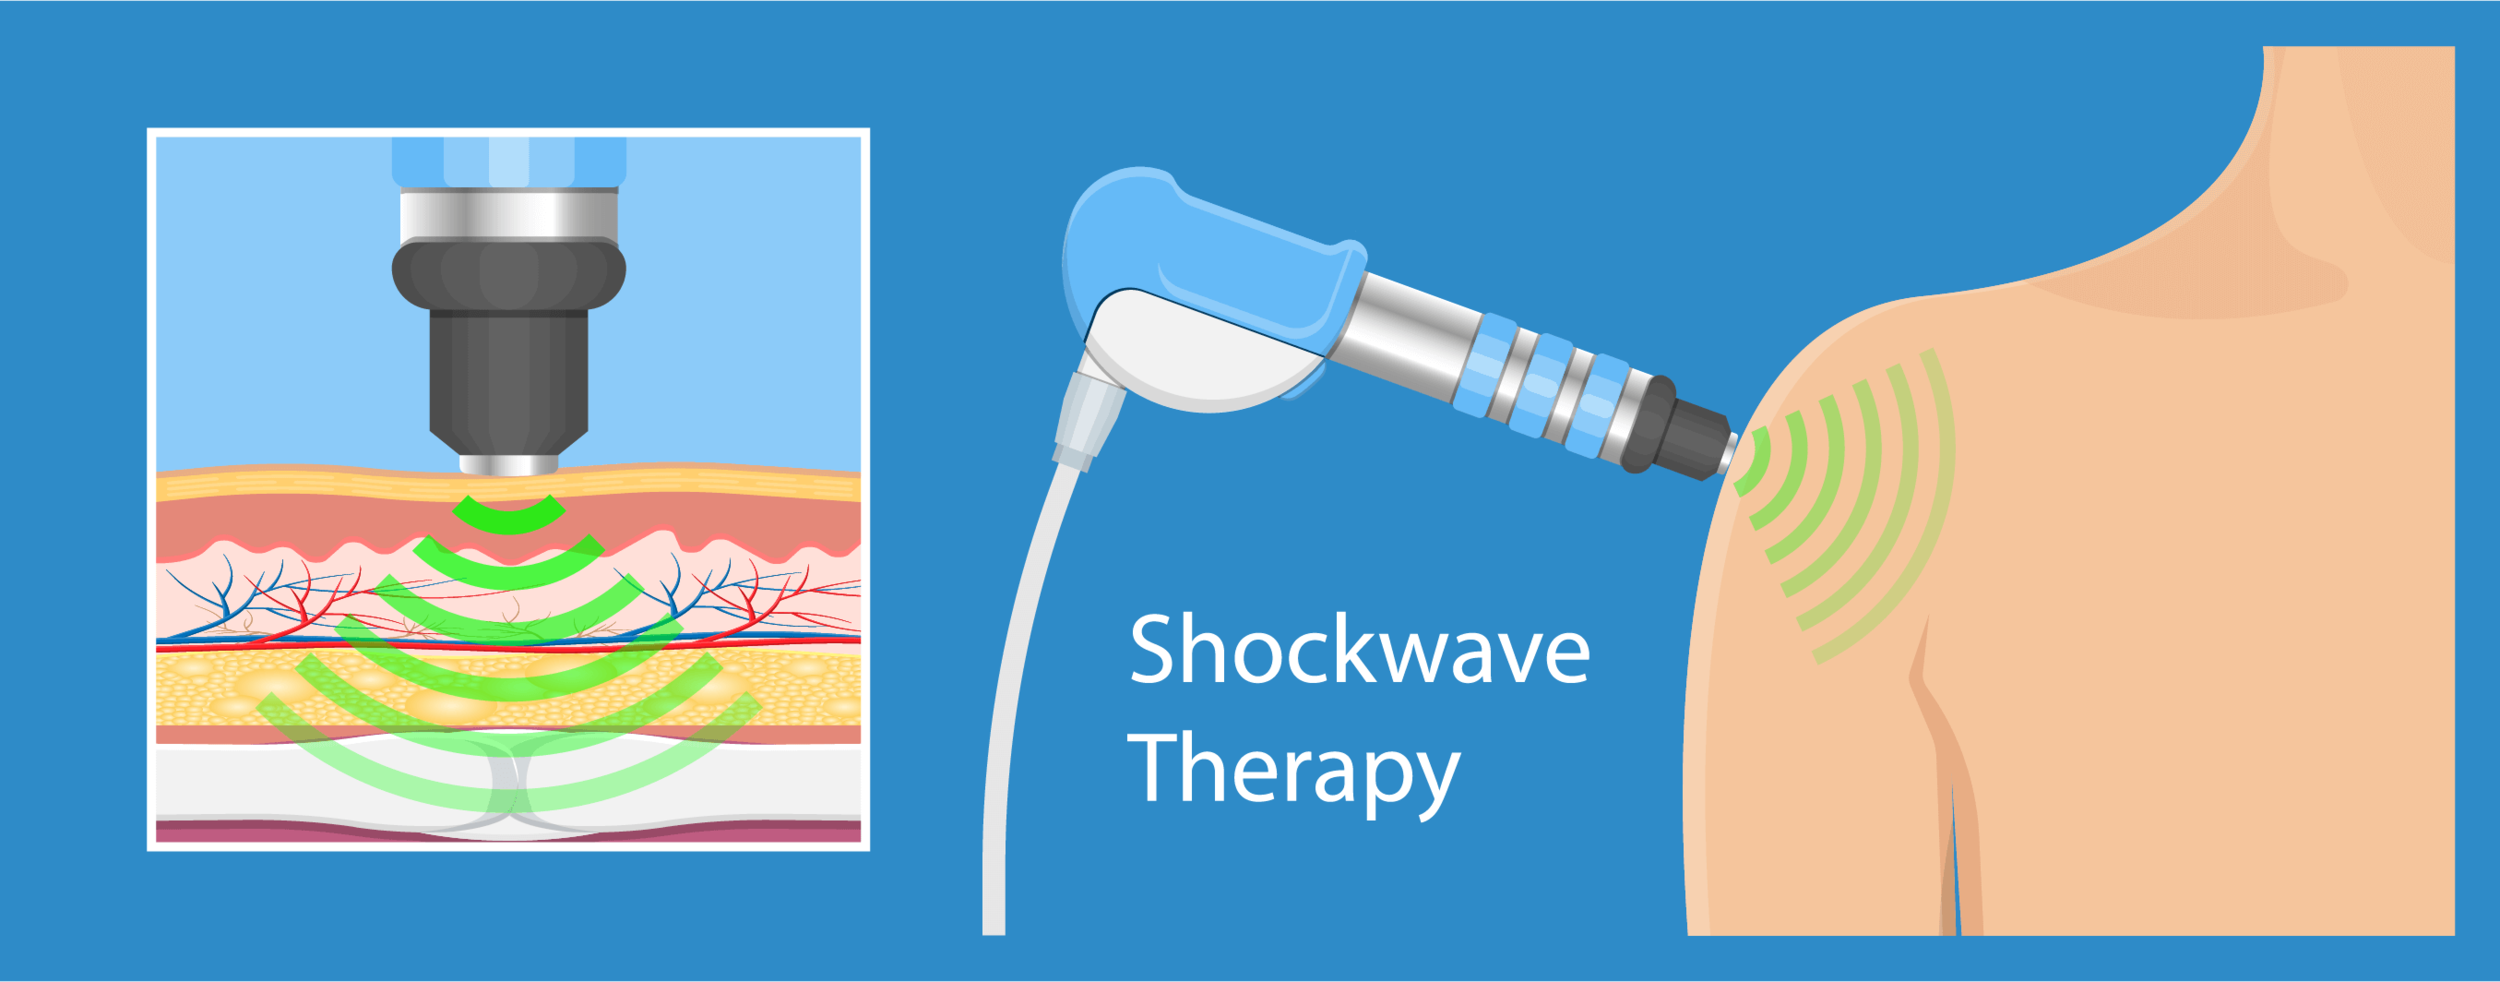
It creates mechanical stress on the tissue. That stress triggers a cascade. Angiogenesis is the big one — new blood vessel formation around existing follicles. You also get upregulation of vascular endothelial growth factor and stem cell activation in the hair bulb. The follicles essentially get pushed out of the resting phase and back into active growth. It's not a permanent fix. The effects fade if you stop treating, and most protocols recommend maintenance sessions every four to six weeks after the initial course. I had a patient once who came in with early-stage androgenetic alopecia. His scalp was tight, almost leathery from years of tension and inflammation. Standard shockwave settings weren't penetrating well because the tissue density was higher than average. I switched to a lower frequency setting at 2 Hz and increased the number of shocks per area to 400. We also spent extra time working the temporal regions where his thinning was worst. After twelve sessions, he had noticeable regrowth in the crown. That one case taught me to assess tissue texture before committing to a protocol. The edge case I run into most often is patients with significant scarring from prior procedures. Shockwave energy doesn't penetrate scar tissue the same way it penetrates healthy dermis. The energy dissipates differently. I mark the scarred areas on the patient's scalp before starting and skip over them entirely. Trying to force treatment through a graft site or a burn scar just wastes time and energy. The surrounding hair usually benefits enough from the nearby treatment zones that skipping the scar isn't a problem.
Setting Up Your Own Treatment Parameters
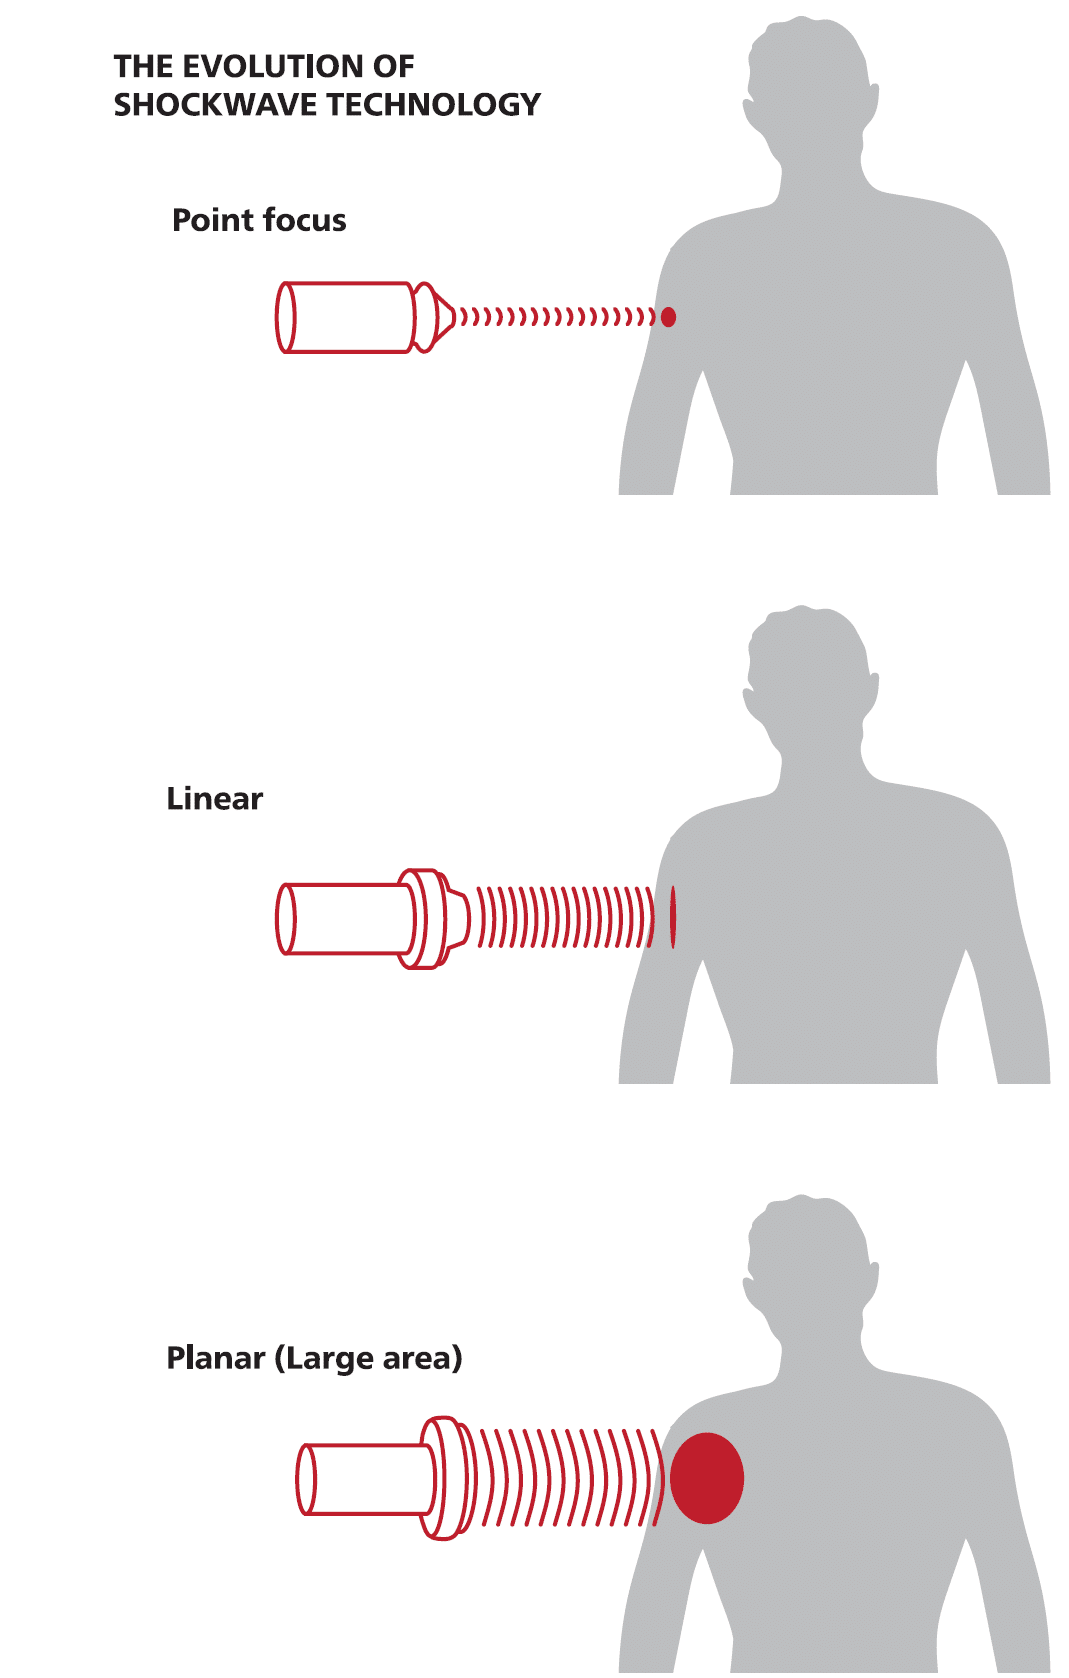
Start with the patient's diagnosis. Shockwave works best on androgenetic alopecia in the early to moderate stages. It's less effective on total baldness where the follicles are already miniaturized beyond recovery. If a patient shows little to no response after six sessions, reconsider whether they're a candidate or if there's an underlying issue like thyroid dysfunction or iron deficiency that needs addressing first. The applicator head size matters more than most people realize. A smaller contact area concentrates energy but covers less ground per pass. A larger head treats faster but with slightly lower intensity at any single point. I typically use a 25mm head for the frontal and temporal zones where precision matters. A 35mm head works better for the occipital and mid-scalp areas where coverage speed is more important. Number of sessions is non-negotiable. One session does nothing measurable. The minimum effective course is eight to twelve sessions spaced two to three days apart. I see patients twice a week for the first month, then once a week for the second month. After that, monthly maintenance keeps results stable. Skipping sessions breaks the biological momentum. The angiogenic response takes time to establish and consolidate.
Get the Full Details
Combining shockwave with other treatments accelerates results. I pair it with minoxidil in most cases. The mechanical stimulation from shockwave and the vasodilation from minoxidil work on different pathways. They complement each other. Some clinics add platelet-rich plasma injections on the same day. That's more aggressive and needs careful timing to avoid overstimulating the follicles. I personally prefer staggering PRP by a few days rather than doing both in one session. Here's something people don't usually mention: the scalp needs to be clean and free of products. Leave-in conditioners, styling gels, even residual sweat can interfere with the coupling between the transducer and the skin. I have patients wash their hair the morning of treatment and come in with completely dry, product-free scalps. It takes two minutes extra but it makes a real difference in energy delivery consistency. Side effects are minimal but not zero. Mild redness is common and fades within an hour. Some patients report a headache lasting a few hours after treatment, especially if you're working the frontal region near the temples. I've seen occasional small bruises where the transducer hit a sensitive spot with too much pressure. Nothing serious, but it's worth telling patients about beforehand so they don't panic.
The main limitation is cost and access. Quality shockwave devices run anywhere from fifteen thousand to sixty thousand dollars depending on the model and specifications. Not every clinic has one. The treatments themselves aren't cheap either. A full course can run two to four thousand dollars out of pocket since most insurance plans don't cover it for hair loss yet. Patients need to understand the financial commitment before starting. Another limitation is patience. Results don't appear overnight. Most patients see initial improvement around session six or eight. Full results take four to six months. I've had patients cancel mid-treatment because they didn't see immediate changes. That's fine, it just means the treatment didn't work for them or they weren't realistic about the timeline. Neither is a failure of the technology, just a mismatch of expectations.
The Long-Term Picture
Shockwave isn't a cure. It's a treatment that manages the condition while you're using it. Stop treating and the gains gradually reverse over several months. The follicles return to their previous state. That's why maintenance matters and why patients who stick with it long-term tend to keep their results. The ones who treat for three months and quit usually lose everything they gained within six months. For patients in their twenties or thirties with early thinning, shockwave can be a meaningful intervention that delays progression significantly. For someone in their fifties with advanced recession, it might add some density back but won't restore a juvenile hairline. Be honest about what the treatment can and can't do. Setting realistic expectations upfront prevents disappointment later and builds trust with the people you're working with.