Why Most People Mess Up Health Literacy Screening
I spent about four years running health literacy screenings in a community clinic setting before I figured out what actually works and what is just paperwork theater. The Short Assessment Of Health Literacy is one of those tools that looks straightforward on paper and completely falls apart in practice if you do not understand what it is actually measuring. The tool itself is basically six reading comprehension questions derived from real health materials. Participants read short passages and answer questions about them. It takes about three minutes to administer. Score ranges from zero to twelve, and anything below nine flags potential limited health literacy. That is the official cutoff used by most hospitals and public health departments. Here is the part nobody tells you: the HAL9 is not a diagnosis tool. It is a flagging mechanism. A low score does not mean someone cannot manage their health. It means the materials they just read were probably too complex for their current reading level, which correlates loosely with broader health literacy challenges. The correlation is about 0.45 to 0.55 depending on the study. Moderate at best.
Running The Short Assessment Of Health Literacy Correctly
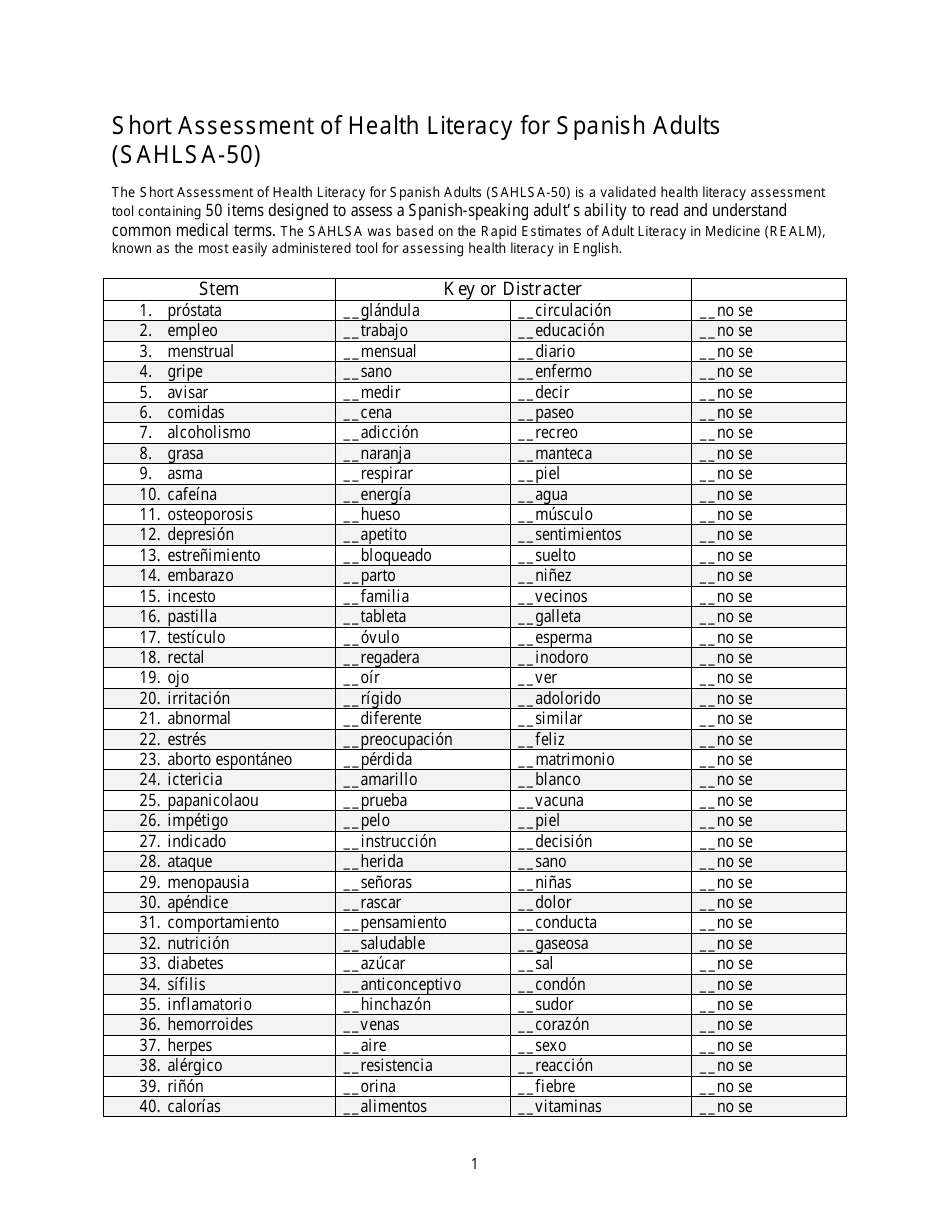
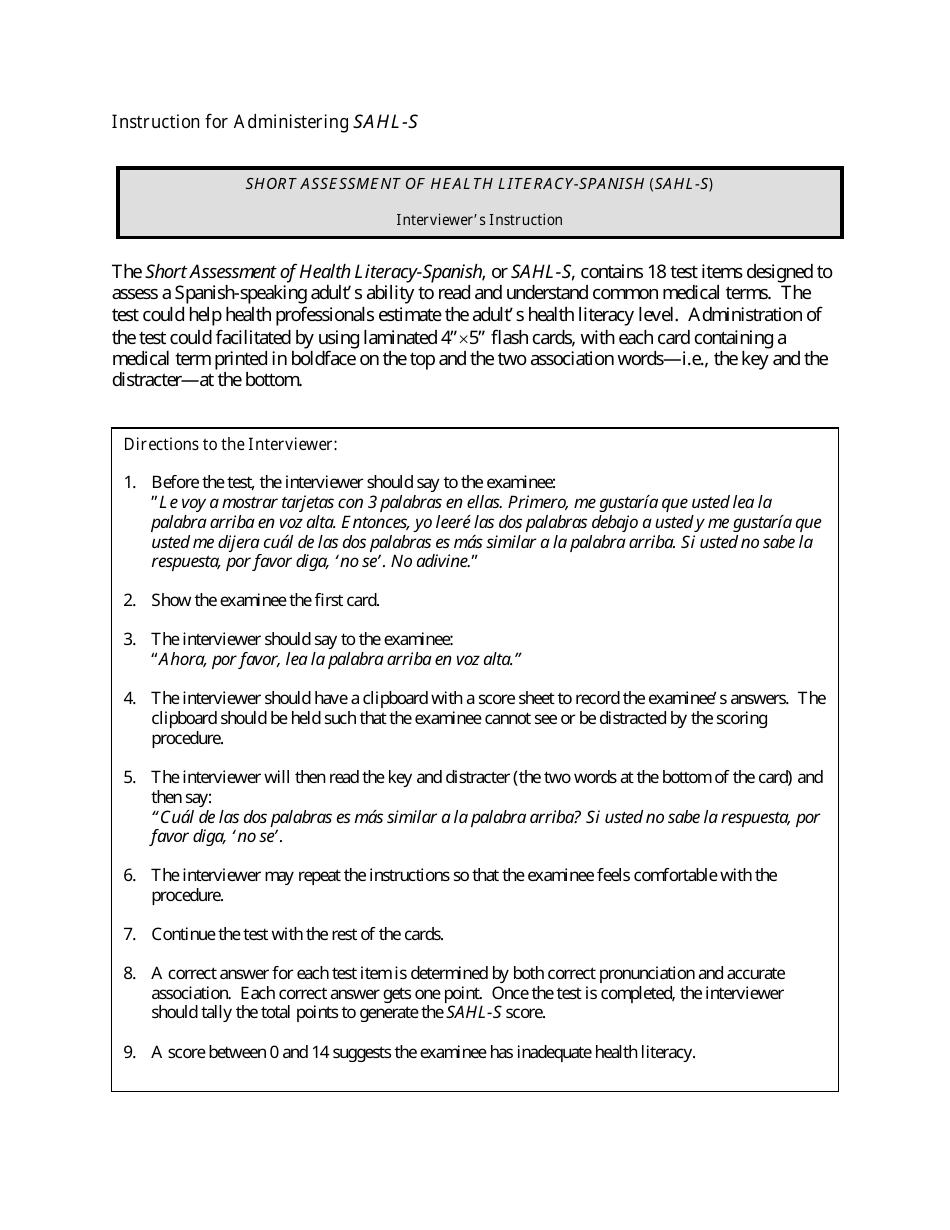
You can get the tool itself free from the Department of Health and Human Services or through the TOFHLA publisher's website. It is in the public domain. The passages are on medical consent forms, prescription labels, and appointment instructions. You read them aloud to the participant yourself. Do not hand them the paper and walk away. The standard administration requires verbal delivery because the tool was normed that way. Self-administration skews the results lower by about a point on average. I keep a printed copy on my desk and a digital version on my tablet. When I run it, I sit across from the person, not beside them. The seating arrangement matters more than you would think. People perform differently when they feel like they are being tested sideways versus face to face. I also make it clear in the first thirty seconds that this is not about intelligence. I say something like "This checks whether these instructions are clear enough for everyday use, not whether you are smart." It reduces test anxiety enough to matter. The scoring is simple addition. Wrong answer gets zero points. Correct answer gets one. Six items, maximum score of twelve. I learned early on to never round or adjust scores retroactively. There is a temptation to bump someone from eight to nine because you feel bad about the result. Do not do it. That invalidates whatever data you are collecting and misleads the next person who reviews the chart.
What The Tool Actually Misses
Health literacy is multidimensional. It covers functional skills like reading dosage instructions, interactive skills like asking clarifying questions during a visit, and critical skills like evaluating health information online. The HAL9 only measures functional reading comprehension. It does not capture whether someone can navigate a hospital system, dispute a billing error, or find reliable information on the internet. That gap is significant. I ran into this problem with a patient last year. She scored a ten out of twelve on the HAL9, which should indicate adequate health literacy. She also could not figure out how to refill her prescription through the pharmacy portal, did not understand her insurance explanation of benefits, and kept showing up to the wrong clinic location because she could not parse the scheduling text messages. She clearly had functional reading ability but very low interactive and critical health literacy. The tool missed her entirely. My workaround was to add two follow up questions after the HAL9. I asked "Can you show me how you would use this medication bottle label?" and "What would you do if the instructions on this form did not make sense?" These are not scored. They are observational. The first question reveals whether someone can translate reading comprehension into actual action. The second reveals whether they know how to seek help when confused. Both are legitimate health literacy behaviors that a multiple choice test cannot measure.
Get the Full Details
If you are doing this in a clinical setting where time allows, the NVS — New Victor Health Literacy Screen — is worth considering as a supplement. It uses a nutrition label as a stimulus and tests numeracy alongside reading. It takes about six minutes instead of three. The additional time is usually worth it because numeracy deficits in health contexts are common and the HAL9 completely ignores them.
Pitfalls That Wreck The Data
The biggest problem I see is people administering this tool without training in culturally responsive communication. A patient who scores low might be responding to dialect differences, unfamiliarity with standardized test formats, or genuine language barriers rather than health literacy issues. I once had a patient who scored a five despite being a college-educated nurse. She was stressed, had just received bad news, and rushed through the questions without really engaging with the passages. Her score meant nothing about her actual capabilities. Another issue is the reading level of the passages themselves. They are calibrated to roughly a sixth to eighth grade level, which sounds accessible but assumes familiarity with American English syntax and medical terminology conventions. Immigrant populations, elderly patients who learned English in different educational contexts, and people with learning disabilities like dyslexia will all score artificially low regardless of their actual health literacy. The tool was normed on predominantly white, English-speaking, middle-class samples. That sample does not represent most clinical populations anymore. If your organization is using HAL9 scores for quality metrics or payer reporting, be aware that the Centers for Medicare and Medicaid Services does not currently require health literacy screening as a condition of participation. Some Joint Commission surveys look for evidence of it, but there is no federal mandate. The data you collect here is mostly for internal quality improvement. Treat it that way. Do not let it become a compliance checkbox exercise where you score people and file the results without any follow up action. That is pointless and wastes everyone's time.
The tool works when you use it as one data point among many. It fails when you treat it as definitive. Most clinicians who rely on it too heavily end up labeling patients incorrectly and then designing interventions based on those false labels. I have seen it happen. A patient labeled as having low health literacy gets simplified materials that are actually infantile for their actual needs. Their real problem — navigation complexity, financial confusion, digital access issues — goes unaddressed because the screening tool gave you a number and you stopped looking. The Short Assessment Of Health Literacy is useful. It is just not as useful as people pretend it is. Use it, document it, and then actually do something with what you learn or admit that you are just checking a box.