Understanding What Actually Works for Sickle Cell Disease Treatments
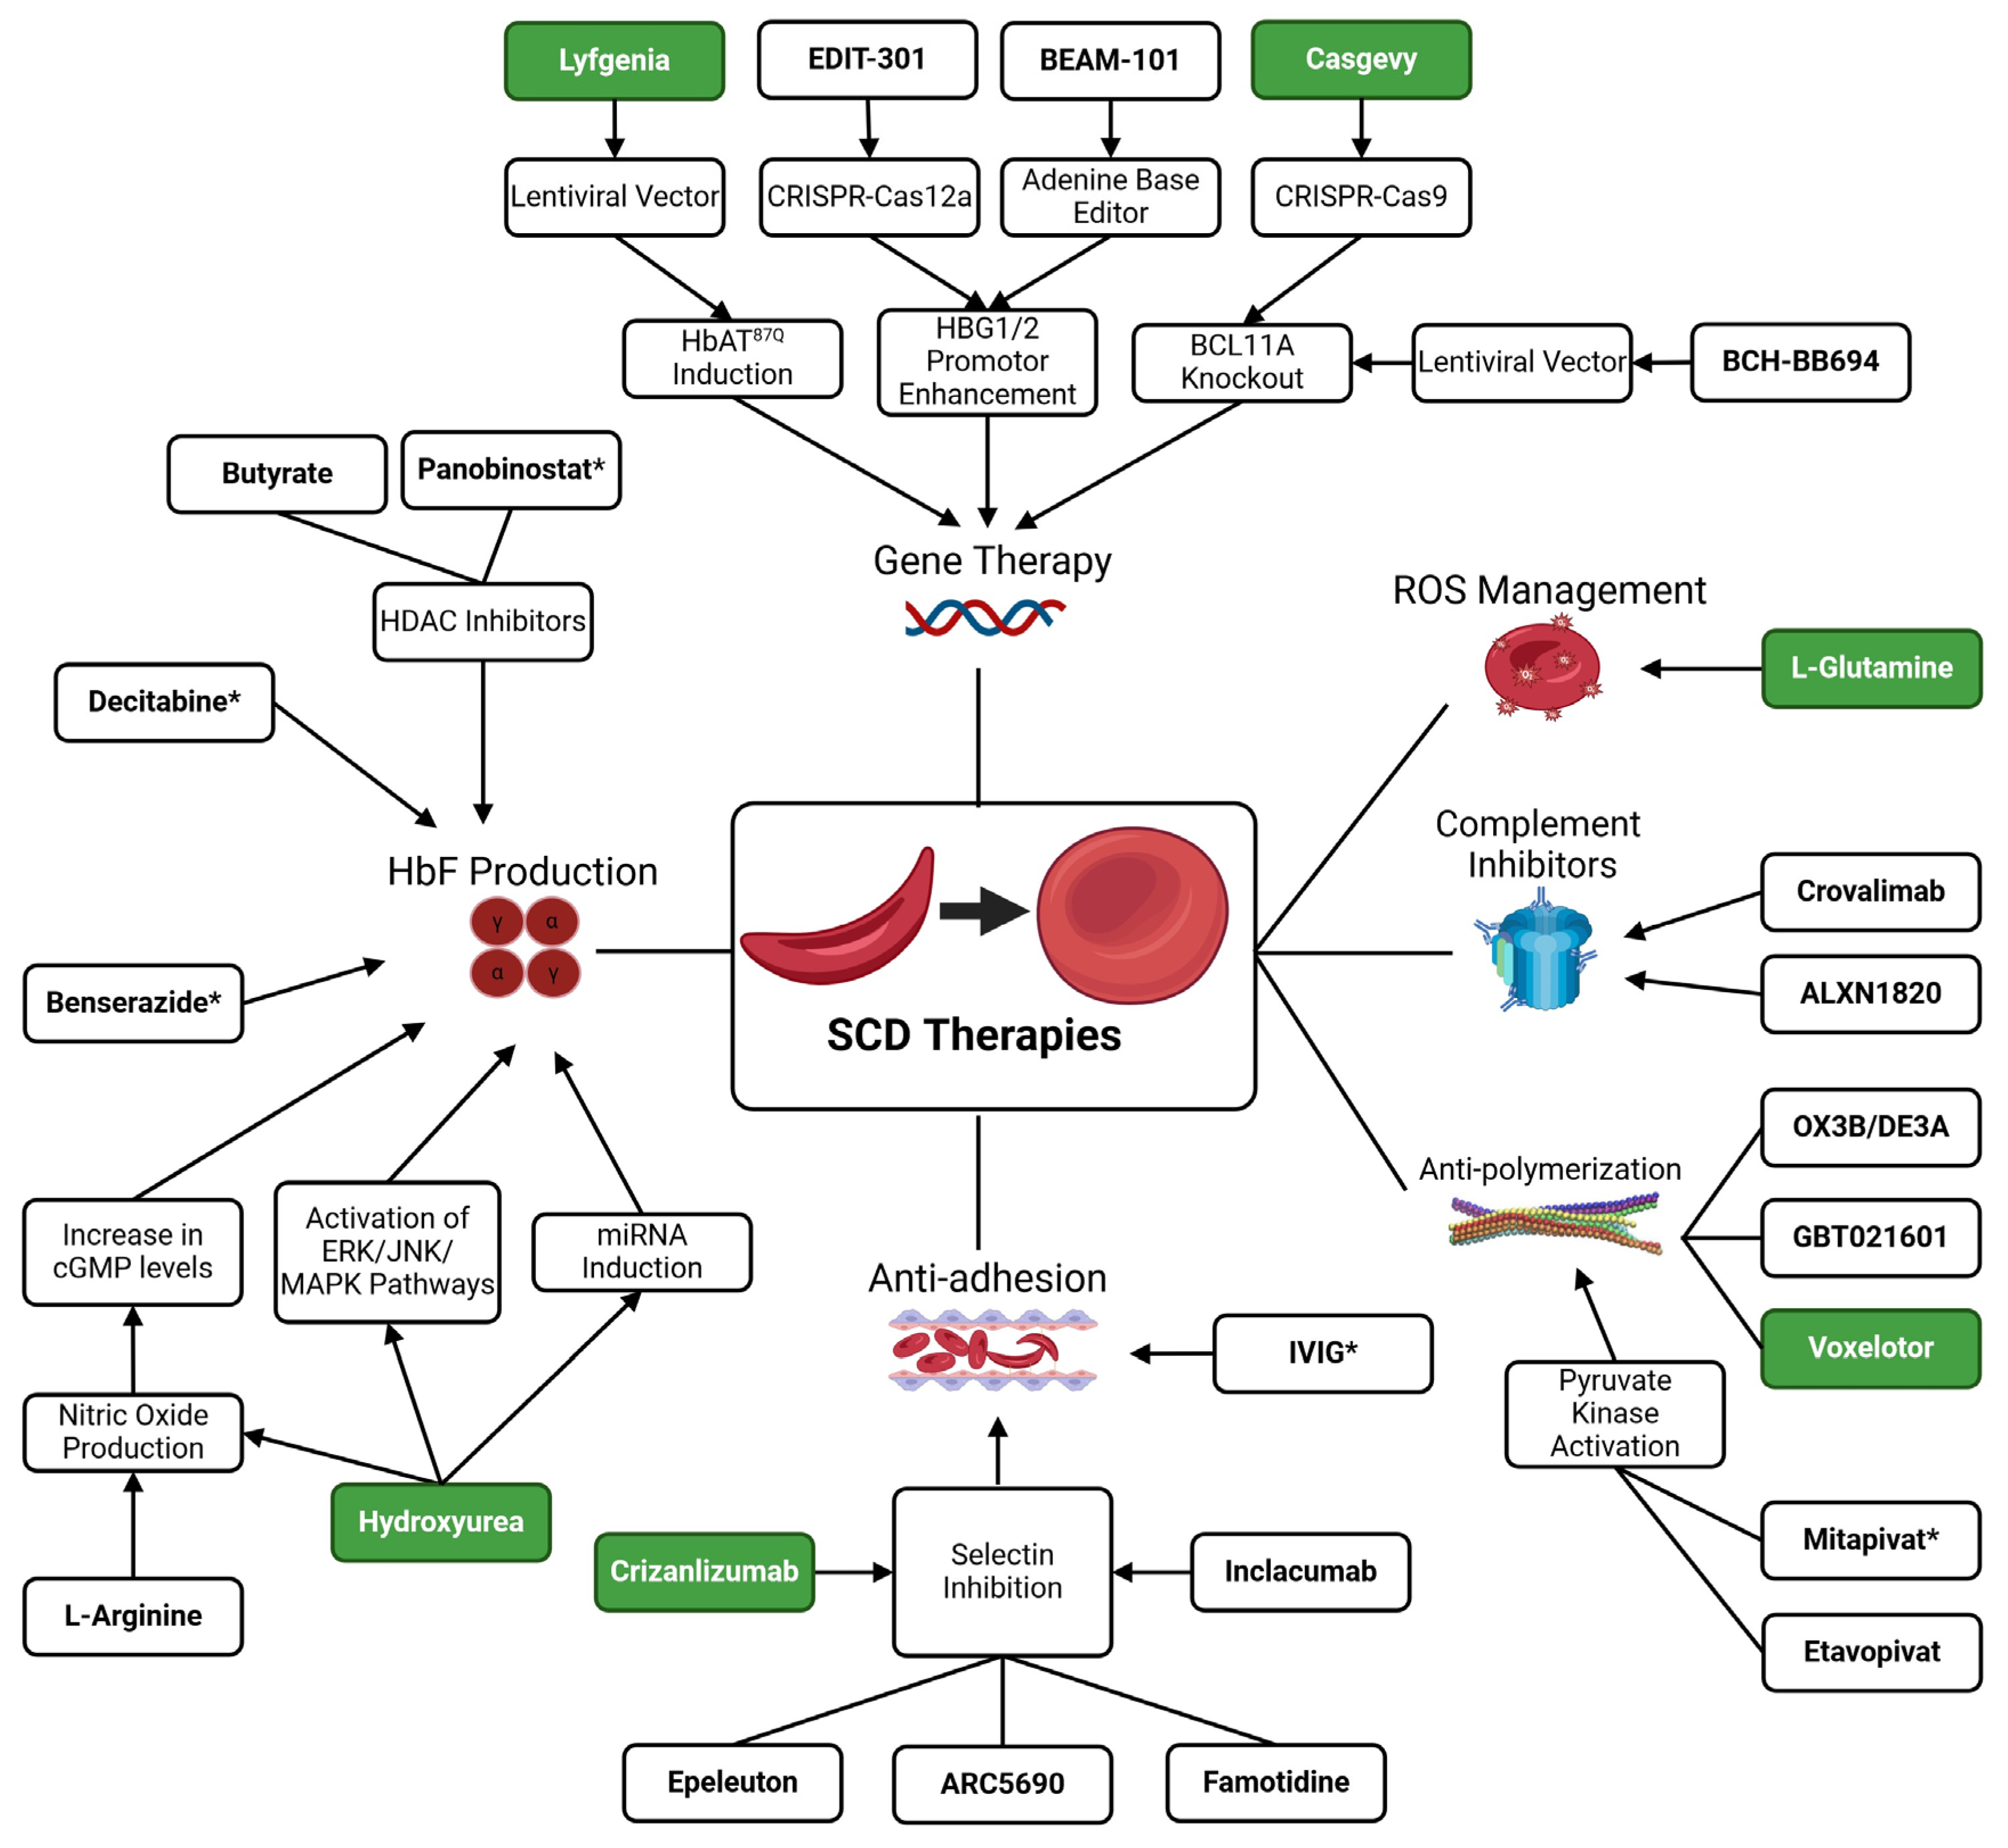
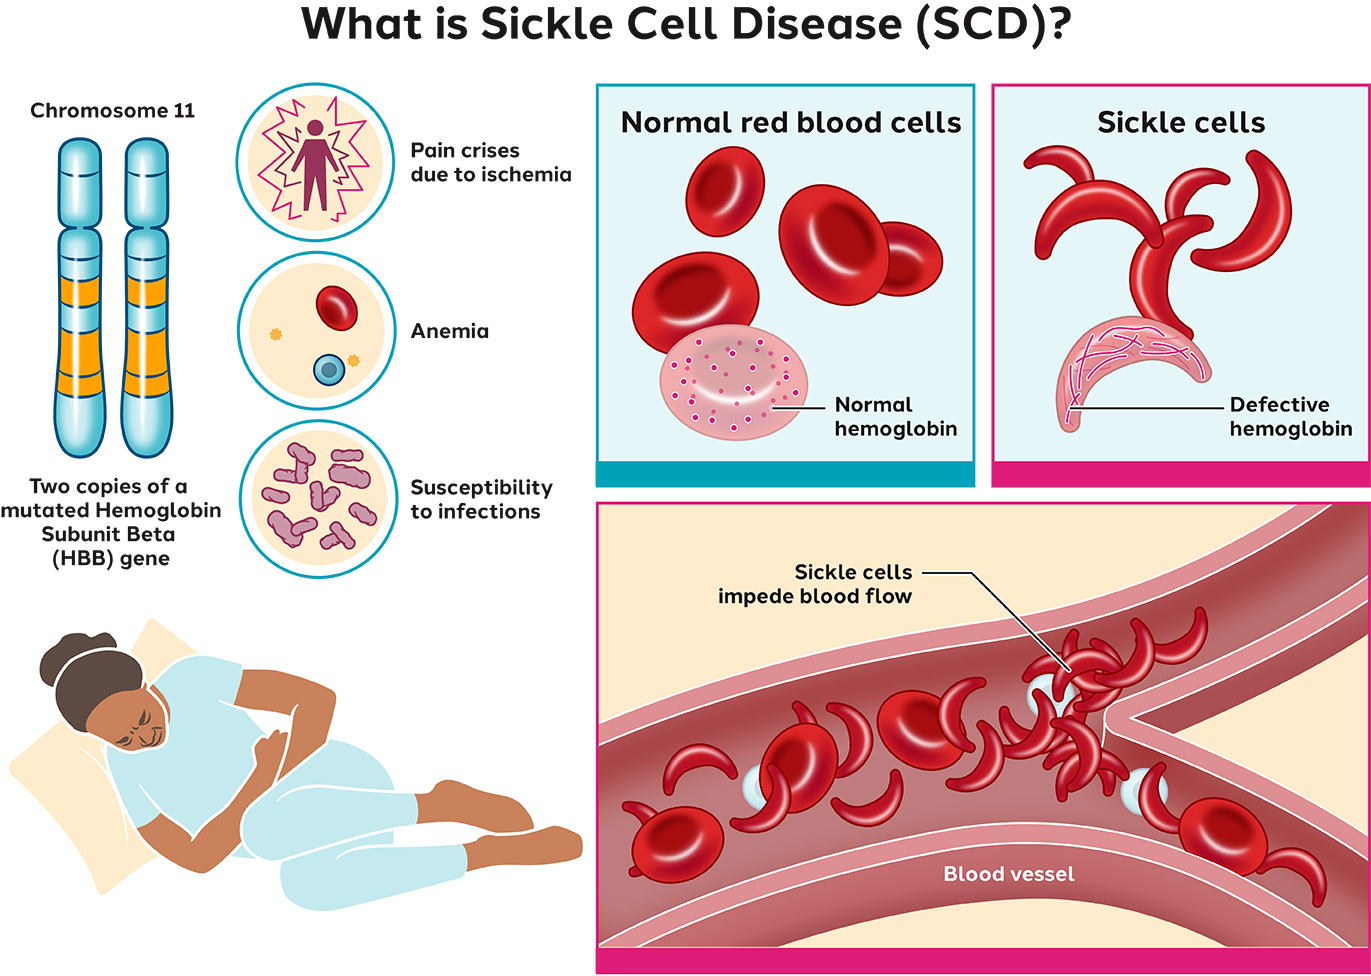
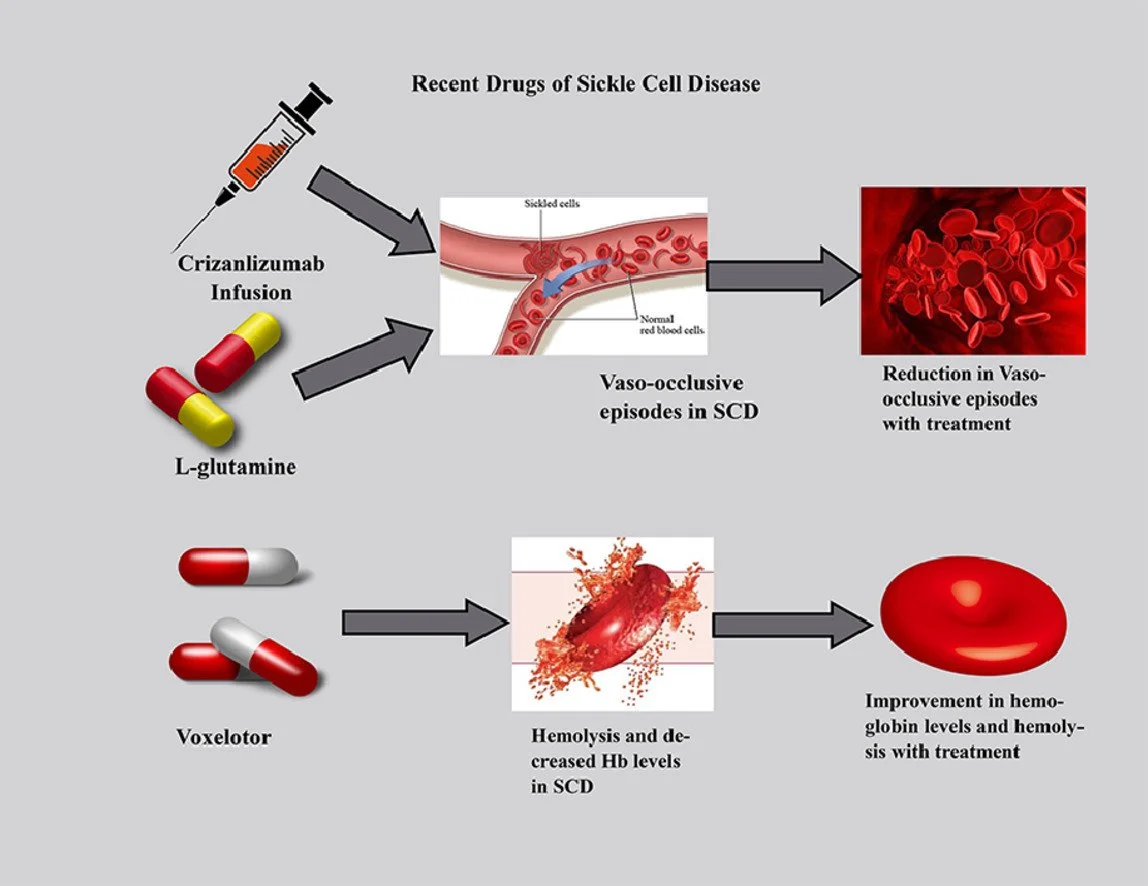
Hydroxyurea has been the backbone of management for years, and for good reason. It raises fetal hemoglobin levels in most patients, which slows down the polymerization of sickle hemoglobin inside red blood cells. The mechanism is straightforward — it inhibits ribonucleotide reductase and forces erythroid precursors to switch to a fetal hemoglobin program. I saw this play out repeatedly in clinical practice. A patient who was coming in every three months with vaso-occlusive crises would drop to once a year after six months on a properly titrated dose. Not always, but often enough that it matters. Hydroxyurea dosing is typically 15 to 35 mg per kilogram per day, adjusted based on tolerance and response. You start low and go slow. Check the absolute neutrophil count and platelet count every few weeks during initiation. If the ANC drops below 1,500 or the platelets fall below 50,000, you cut the dose. That is the main limiting factor in real-world use, not the drug failing to work but the bone marrow not tolerating it. In my experience, about 60 to 70 percent of patients can stay on a therapeutic dose. The rest either cannot tolerate it or do not respond adequately, and then you look at the newer options. Voxelotor, approved in 2019, works through a different pathway. It binds to the alpha chain of hemoglobin and increases oxygen affinity, which keeps the hemoglobin in the R-state and prevents sickling. The clinical trial showed a meaningful rise in hemoglobin and a drop in markers of hemolysis. But it does not reduce pain crises as clearly as hydroxyurea does. That distinction matters when you are counseling someone. You tell them: this may improve your anemia numbers, but it is not a guarantee against the crises you have been dealing with.
L-glutamine came through earlier, in 2017. It is an oral supplement that reduces oxidative stress in red blood cells. The data from the phase 3 trial showed a modest reduction in pain crises and hospitalizations, roughly one crisis fewer per year on average. The effect size is small. Some patients report that it helps them feel slightly better overall, though that may be a combination of genuine physiological effect and the placebo component of taking something daily. The safety profile is excellent. Gastrointestinal side effects are the most common complaint.
Newer Therapies and What They Actually Change
Oxbryta (ufibritin) is a hemoglobin S polymerization inhibitor that showed promise in phase 2 trials. It did not carry forward into phase 3 development with the same enthusiasm as some other candidates, but it sits in a class of drugs that target the physical process of polymerization directly rather than the metabolic pathways. That approach has theoretical appeal because it gets at the core mechanism, but translating that into clinical benefit has been harder than expected. Crizanlizumab is a monoclonal antibody against P-selectin. The idea here is that P-selectin on endothelial cells and platelets mediates the adhesion of sickled cells to the vessel wall, which is a major driver of vaso-occlusion. Blocking it should reduce crises. The study published in the New England Journal of Medicine in 2019 showed a significant reduction in average annual pain crises, from about 4.76 per year on placebo to about 2.67 per year on the drug. That is a real effect. The downside is that it is an intravenous infusion given monthly, and you need to premedicate with antihistamines and acetaminophen because infusion reactions are common. The cost is another practical barrier — it runs into tens of thousands of dollars annually. The combination of hydroxyurea with crizanlizumab is something I have seen used in practice for patients who are not fully responding to hydroxyurea alone. The data on combination therapy is still emerging, but the rationale is sound. You are hitting two different pathways — fetal hemoglobin induction and reduced adhesion — at the same time. I watched one patient who had been stabilized on hydroxyurea but still had breakthrough crises during weather changes and high altitude. Adding crizanlizumab dropped her rescue visits from two per quarter to zero over the next year. She was on a moderate hydroxyurea dose, so we were not optimizing that side of things, which is worth noting as a confounder.
Get the Full Details
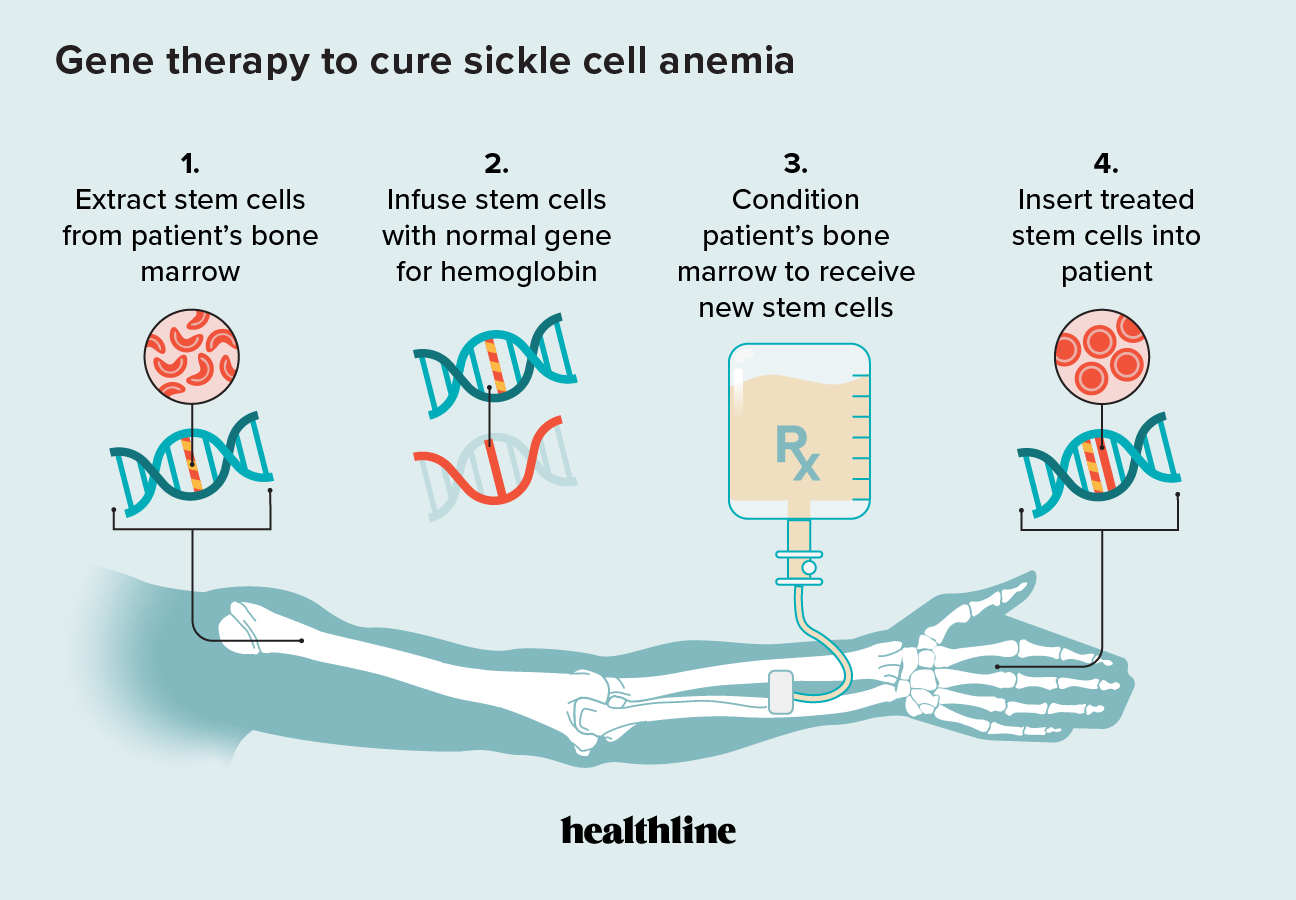
Sickle Cell Disease Treatments: Gene Therapy and Transplantation
Curative options exist now, and they are no longer experimental. Hematopoietic stem cell transplantation with a matched sibling donor has been the standard curative approach for young patients with severe disease. The transplant-related mortality rate is around 5 to 10 percent depending on conditioning regimen and patient condition. For those who are candidates, it is the most reliable path to a cure. The problem is that only about 17 percent of patients have a matched sibling donor. The rest are looking at other options. Gene therapy has closed part of that gap. Lyfgenia (lovotibeglogene autotemcel) and Casgevy (exagamglogene autotemcel) are both autologous stem cell gene therapies approved in the United States. Casgevy uses CRISPR-Cas9 to disrupt the BCL11A enhancer, which removes the repression on fetal hemoglobin production. The result is similar to what hydroxyurea achieves pharmacologically, but permanently. The phase 3 data showed that the vast majority of patients who received the treatment were free from severe vaso-occlusive crises for at least 12 months. Some had relapse after two years, but the initial results were striking. Lyfgenia takes a different approach. It introduces a modified beta-globin gene that produces hemoglobin S that cannot polymerize as easily. The approval came with a boxed warning for the risk of genotoxicity and transcriptional dysregulation from lentiviral vector insertion. That is not a trivial concern, even if the absolute risk appears low. You need to discuss that with patients and families. The treatment process itself is intensive — leukopheresis to collect stem cells, conditioning with busulfan, infusion, and then a prolonged period of monitoring before engraftment. Total timeline from start to full engraftment is roughly four to five months. Cost estimates run well over a million dollars per patient, though the long-term economics may favor it if you are counting avoided hospitalizations and transfusions over a lifetime.
I remember the first time a patient asked me about gene therapy. They had read about it online and were hopeful. I was honest with them about what we know and what we do not. The follow-up period is still relatively short. Five years is good data, but sickle cell is a lifelong disease. We do not yet know what happens at year ten or twenty. The patient understood that and chose to wait. That is a decision more people should feel comfortable making.
Practical Challenges That Nobody Talks About Enough
The biggest problem with Sickle Cell Disease Treatments is not the science. It is access. Hydroxyurea costs pennies per day. Crizanlizumab costs thousands per infusion. Gene therapy costs over a million dollars upfront. Insurance authorization for the newer drugs is a full-time job for many clinic staff. Prior authorizations get denied. Peer-to-peer reviews are scheduled weeks out. Patients miss work. They miss school. The disease does not pause because the pharmacy benefit manager is reviewing a claim. I had a patient once who was stable on hydroxyurea but needed crizanlizumab added. The prior authorization was denied twice on the grounds that she had not failed "an adequate trial of crizanlizumab" before being denied the drug. That is circular reasoning. We appealed with a letter from the attending physician explaining the clinical situation. The third submission went through, but it took eight weeks. During those eight weeks, she had two pain crises and was hospitalized once. That is the cost of bureaucratic friction measured in human terms, not dollars. Another issue is the pediatric gap. Many of the newer therapies were studied primarily in adults. The dosing and safety data for children under 16 are thinner. Hydroxyurea has extensive pediatric data and is standard of care for children with HbSS or HbS-beta zero thalassemia who meet certain criteria. But insurance coverage for pediatric crizanlizumab or gene therapy is less established. I dealt with a family whose 12-year-old had severe disease and was being considered for gene therapy, but the center that was doing the procedure required the patient to be at least 16. That age cutoff is arbitrary from a medical standpoint and reflects site-level policy, not biology. The family had to travel to another state to find a program that would treat their child.
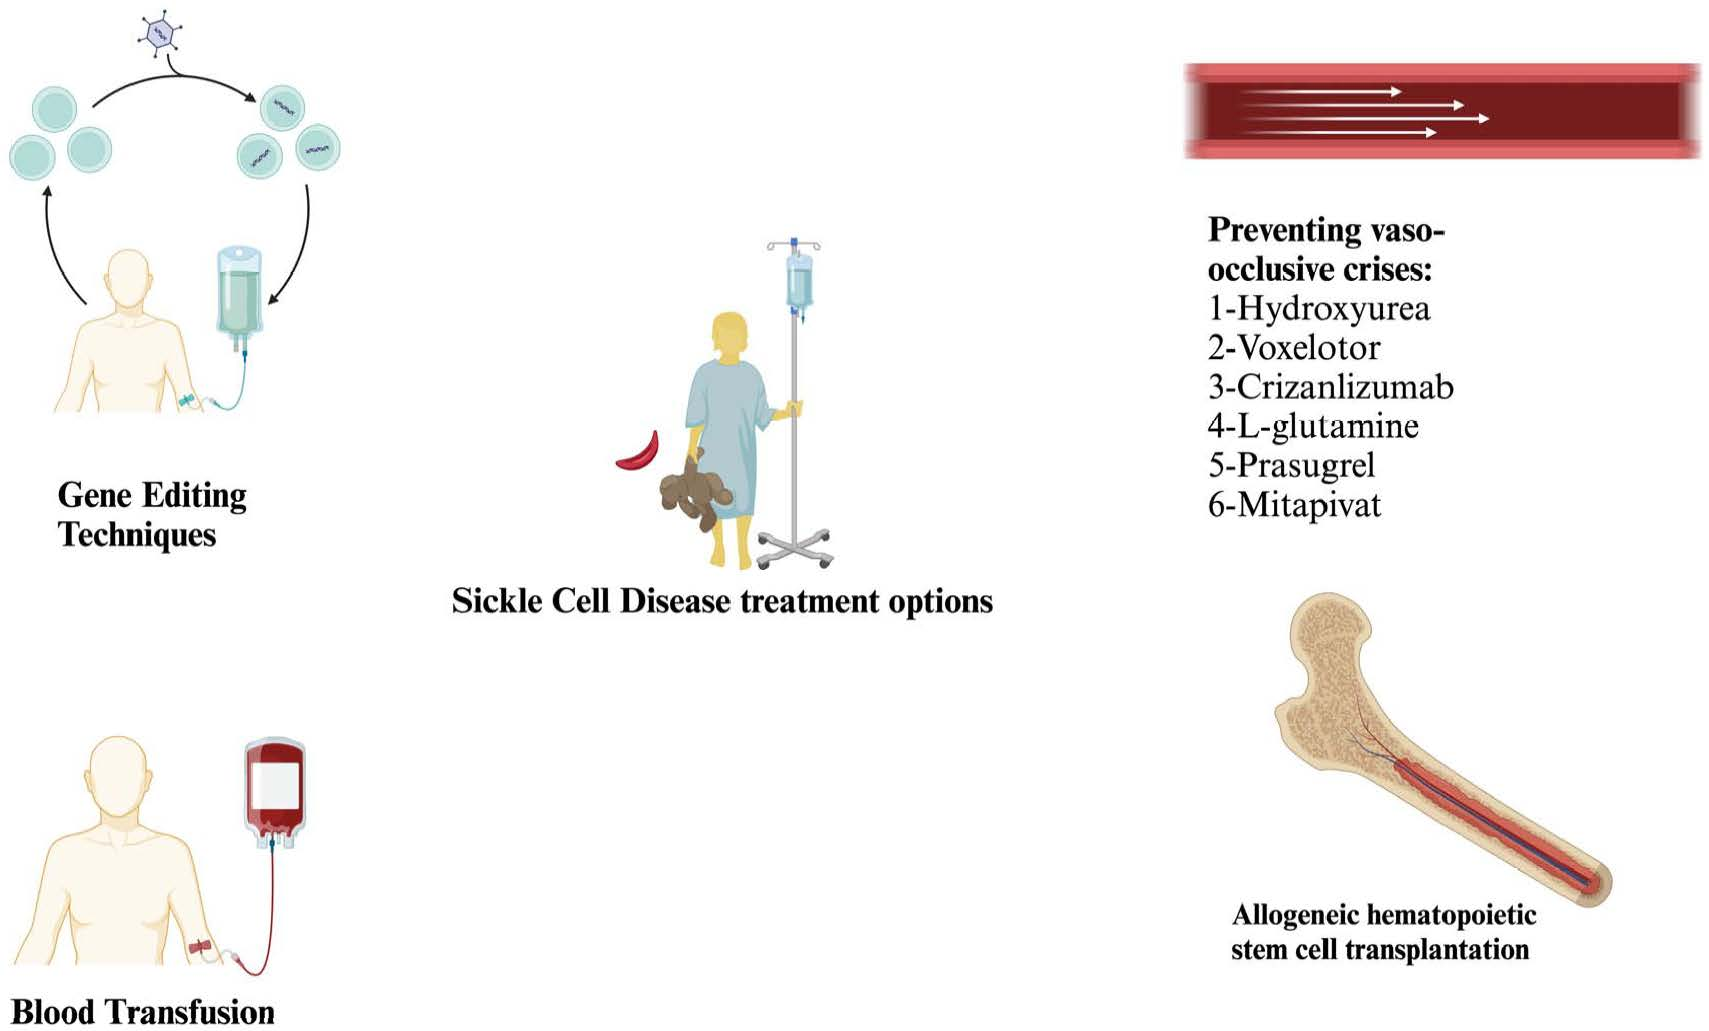
Supportive Care That Still Matters
Folic acid supplementation is standard — 1 mg daily — because chronic hemolysis increases folate demand. Penicillin prophylaxis is recommended for children under five, and some centers extend it. Pneumococcal, meningococcal, and influenza vaccines are essential. These are not treatments for the disease itself, but they prevent complications that can be fatal in a population with functional asplenia. Chronic transfusion programs are used for stroke prevention in children with abnormal transcranial Doppler velocities. The stroke prevention study (STOP) showed that maintaining the sickle hemoglobin below 30 percent through regular transfusions reduces stroke risk dramatically. The follow-up study (STOP II) showed that you can stop transfusions in many patients after a couple of years without losing that protection, but you need close monitoring. Iron chelation becomes necessary if transfusion burden is high. Deferasirox is commonly used, and monitoring liver iron concentration with MRI is part of long-term management. Pain management during crises requires a balance. Opioids are often necessary, and there is stigma attached to their use in sickle cell patients that is unwarranted and harmful. I have seen patients turned away from emergency departments because providers suspected drug-seeking behavior. The pattern of repeated visits for the same type of crisis, predictable dosing requirements, and consistent clinical findings should be enough to recognize that this is not addiction in the vast majority of cases. That recognition is not universal, and it is a problem that needs to be addressed systemically, not just at the individual provider level.
What Comes Next in Sickle Cell Disease Treatments
The pipeline is active. Several other gene editing approaches are in early clinical stages. Some target different genes beyond BCL11A. Others use base editing or prime editing for more precise modifications. Small molecule inhibitors of the Rho/ROCK pathway are being studied for their potential to reduce vascular adhesion. Antisense oligonucleotides that modulate gamma-globin expression are another approach that avoids the permanence of gene editing but retains the goal of increased fetal hemoglobin. The economic landscape is shifting too. Some countries have negotiated price agreements that bring gene therapy costs down significantly. The United Kingdom's National Health Service approved Casgevy at a price that was reported to be substantially lower than the US list price. Whether that model can scale to other health systems remains to be seen. The United States pricing environment is different, and the long-term budget impact of curing thousands of patients with a million-dollar procedure will require creative payment models — annuity payments, outcomes-based contracts, or similar structures. On a practical level, the field is moving from a single-drug paradigm to combination strategies. We are learning that hitting multiple pathways simultaneously produces better outcomes than maximizing any single intervention. The question now is how to sequence these therapies, how to identify which patients benefit most from which approach, and how to make all of this available to the people who need it most. The science is ahead of the infrastructure. That gap is where the next decade of work will happen.