
Working With Simple Squamous Epithelium Under the Scope
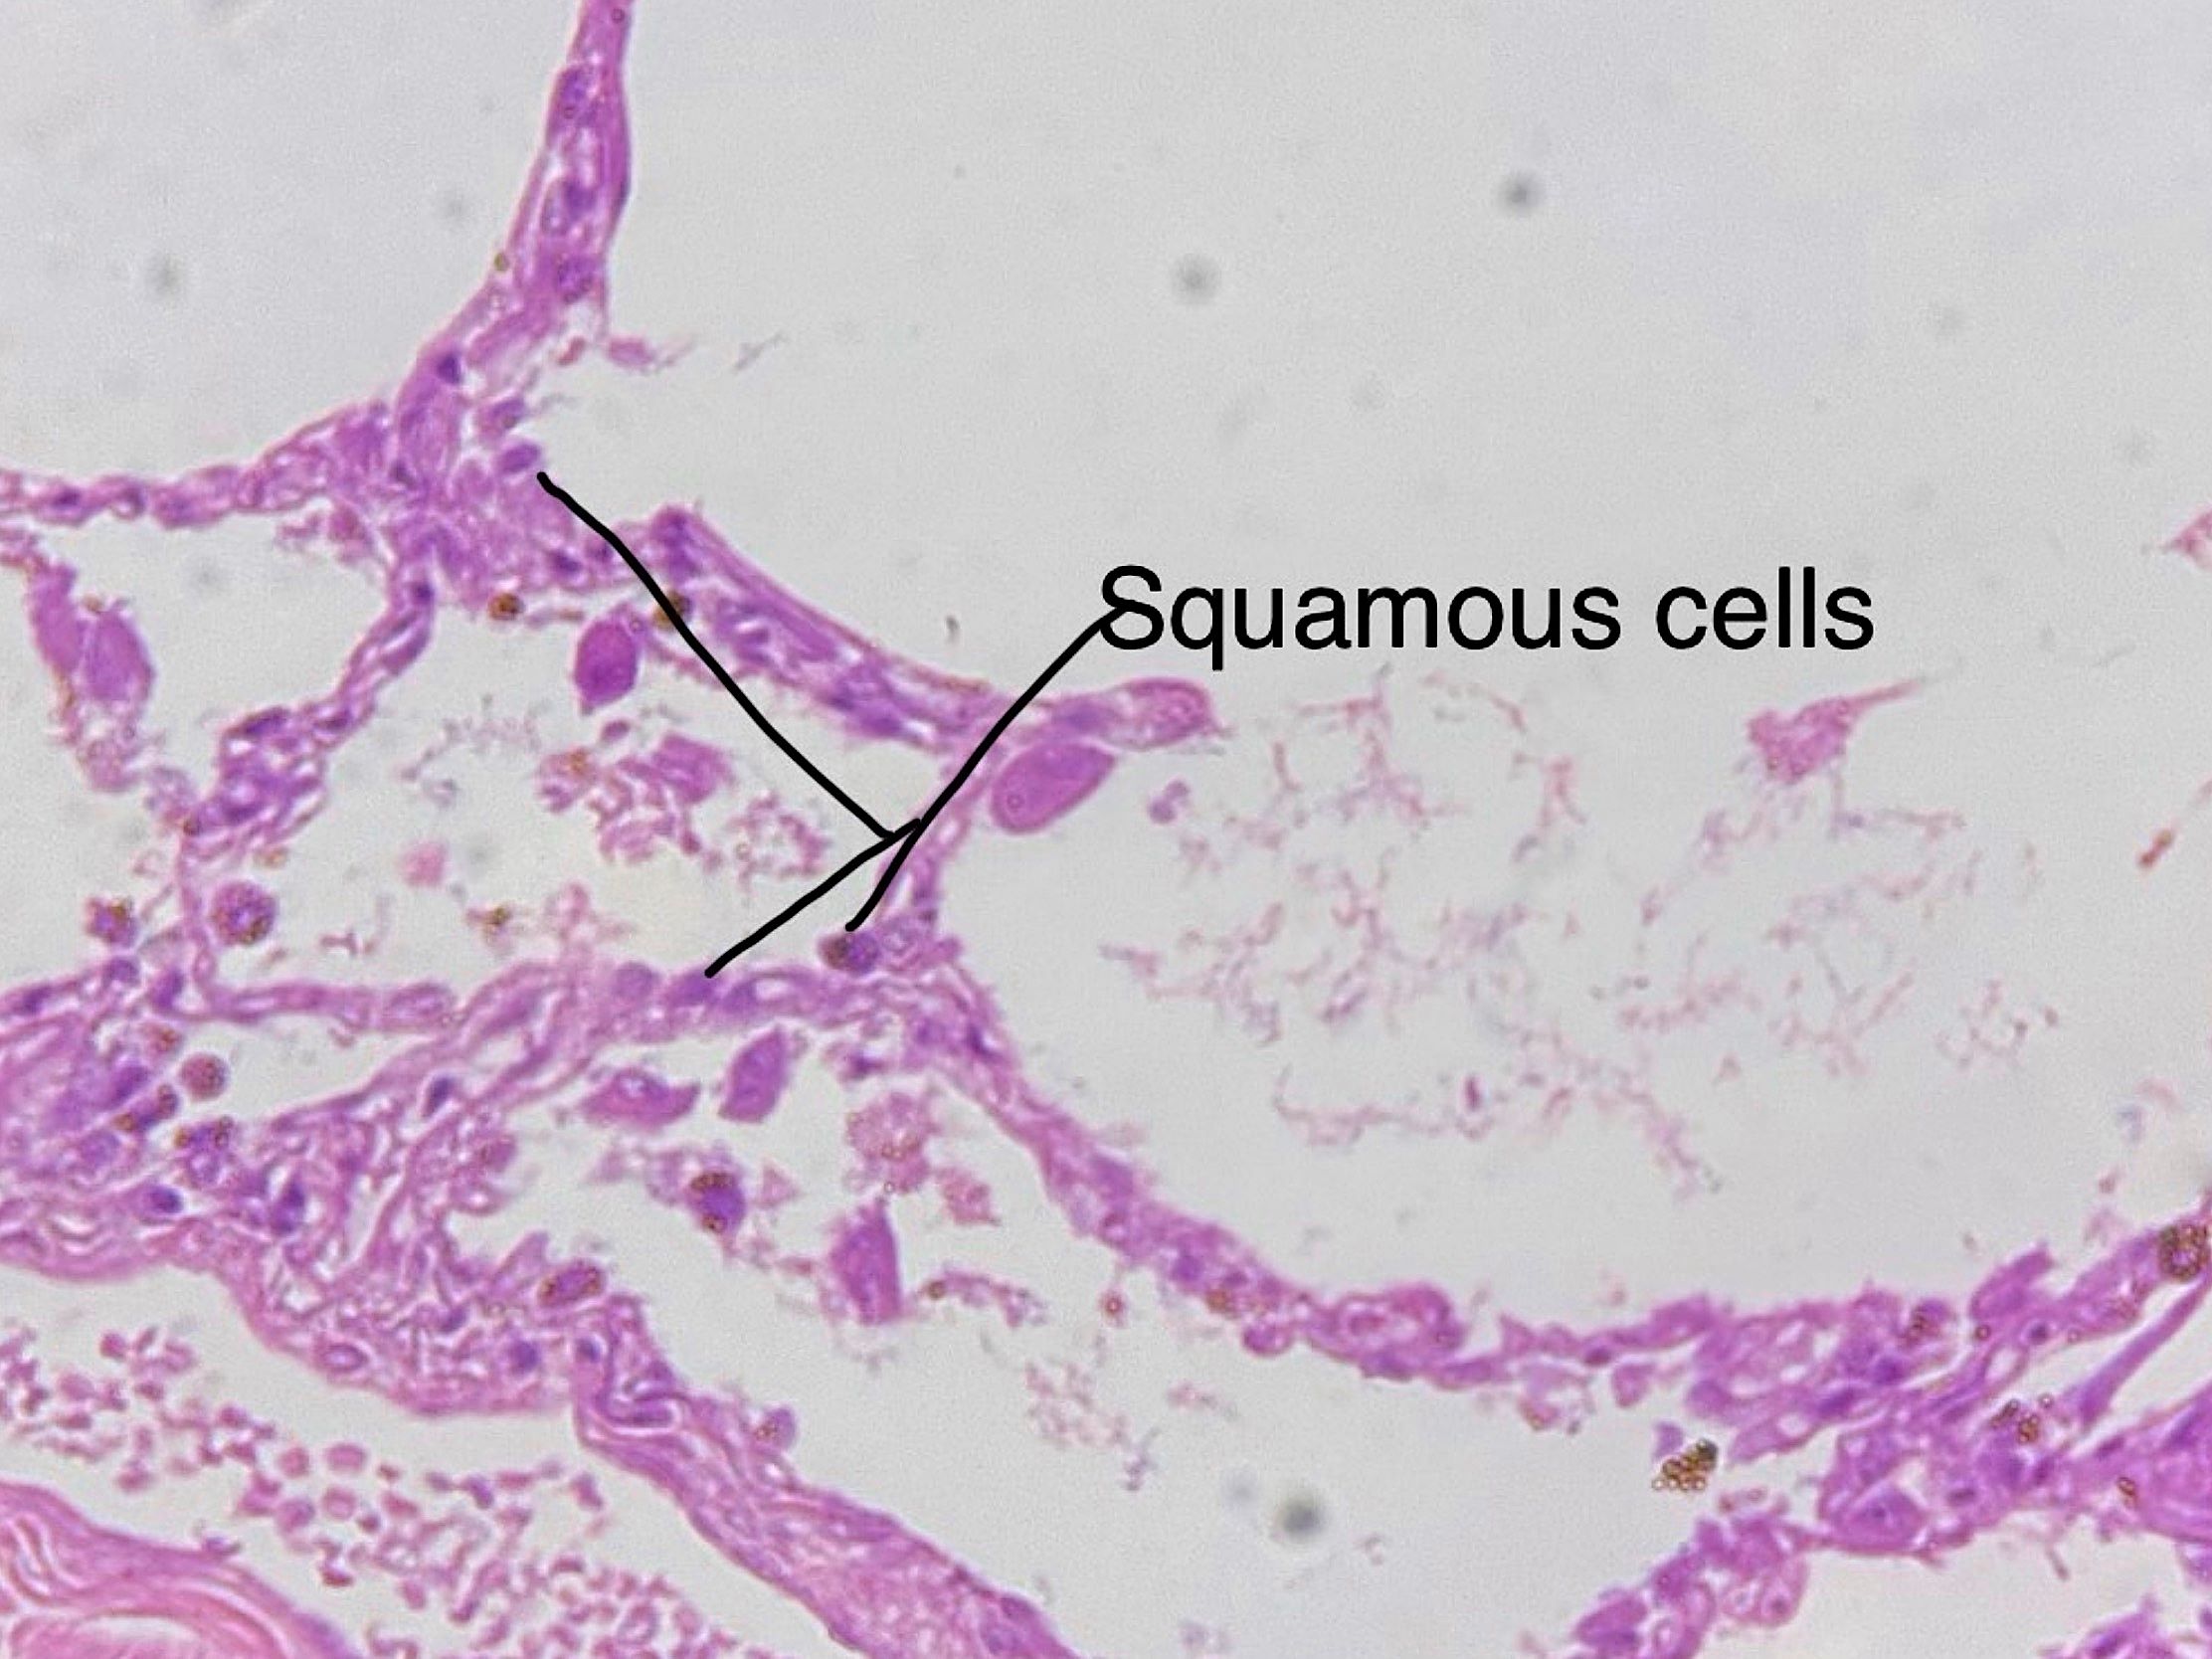
Simple squamous epithelium histology is one of those things that looks straightforward on paper but can drive you insane when you actually have to identify it in a slide. The tissue is just a single layer of flat cells. That is it. But pinning it down during an exam or when you are grading slides at 8pm on a Friday requires you to know exactly what to look for and, more importantly, what to rule out. The cells are scale-like, extremely thin, and you can usually see the nucleus bulging slightly from the center of each cell. The cytoplasm between nuclei is so thin that it often disappears entirely, making the tissue look almost transparent. You will see these cells lining blood vessels, the alveoli of the lungs, the lining of the heart and blood vessels (endothelium), and the Bowman's capsule in the kidney. Here is where people get tripped up. The endothelium of capillaries and the mesothelium of body cavities are both simple squamous epithelium. They look nearly identical under low magnification. The only reliable way to tell them apart is by context. Endothelium always has red blood cells either inside the lumen or pressed against it. Mesothelium sits on top of connective tissue without blood vessels immediately underneath. If you are looking at a random section and cannot find that context clue, you are just guessing.
I spent an entire residency rotating through pulmonary pathology before I stopped second-guessing alveolar vs. pleural mesothelium on H&E sections. The trick is not to look at the cells themselves. Look at what is adjacent to them. Alveolar epithelium faces air spaces, which appear empty or filled with pink proteinaceous material in edema. Pleural mesothelium faces the pleural space, which may contain a thin serous fluid but never alveolar septa extending into it. Once I started anchoring my identification to the surrounding architecture instead of just counting cell layers, my accuracy shot up significantly.
How to Identify It on a Slide
Start at 4x objective. Find regions where there is a clear boundary between an open space and a thin cellular lining. Move to 10x and confirm that the lining consists of only one cell layer thick. Then go to 40x and examine the nuclei. In true simple squamous epithelium, the nuclei are flattened and disc-shaped, not oval or round like you would see in simple cuboidal or columnar epithelium. If the nuclei look rounded or elongated perpendicular to the basement membrane, you are probably looking at simple cuboidal or even transitional epithelium that has been sectioned tangentially. Tangential sectioning is the most common pitfall. A simple squamous layer cut at an angle can appear to have multiple layers because the section passes through different planes of the same cell sheet. The cells in the middle of the field will look thinner and have flatter nuclei than those at the edges. If you suspect tangential sectioning, trace the layer and look for the characteristic thinning toward the center. Real stratified epithelium will maintain consistent thickness throughout. Another thing that throws people off is endothelial cells in larger vessels. In arteries and veins, the endothelium can appear slightly cuboidal because the vessel is distended and the cells are stretched. The nuclei may also appear more prominent. This does not make the tissue anything other than simple squamous. Check for the internal elastic lamina just beneath the endothelium in arteries. Its presence confirms you are looking at vascular endothelium, not some other simple squamous lining.
Get the Full Details
Staining and Preparation Notes
Hematoxylin and eosin is standard. The nuclei stain dark purple and the cytoplasm is barely visible, often appearing as a thin pale pink line. If the tissue is thick or poorly fixed, the cytoplasmic borders become even harder to distinguish, and the nuclei may appear to be overlapping or touching more than they actually are. This can create the illusion of stratification. Immunohistochemistry can help when morphology is ambiguous. CD31 or CD34 marks endothelial cells. Calretinin and WT-1 are useful for confirming mesothelial origin. I use calretinin frequently when I am evaluating pleural biopsies and the distinction between reactive mesothelial hyperplasia and adenocarcinoma matters. Reactive mesothelial cells can become cuboidal and form complex structures that mimic malignancy, but they retain calretinin positivity and do not show the invasive growth pattern of carcinoma. This is not a trivial distinction to make on routine H&E alone. If you are working with frozen sections, simple squamous epithelium is harder to identify. Frozen sections are thicker, the cellular detail is poorer, and artifacts from the cutting process can distort the appearance. Take your time and use higher magnification. Do not rely on a quick low-power scan.
Practical Considerations and When Simple Squamous Epithelium Histology Falls Short
There are situations where identifying simple squamous epithelium by light microscopy is simply not sufficient. In renal pathology, for example, distinguishing between normal Bowman's capsule and early fibrinoid necrosis of the glomerular tuft can be impossible without electron microscopy or special stains. The parietal epithelium of Bowman's capsule is simple squamous, but as soon as you start seeing cellular proliferation or deposits on the epithelial side, you are dealing with pathology that requires a different diagnostic approach entirely. Similarly, in the lung, the type I pneumocytes that make up the vast majority of the alveolar surface area are so thin that they are virtually invisible on standard H&E. You see the nuclei of type II pneumocytes, which are cuboidal, but the actual gas-exchange surface is composed of type I cells that are barely detectable. If you are trying to assess alveolar damage or septal thinning quantitatively, light microscopy has real limitations. Stereology or image analysis with specific markers like claudin-5 for tight junctions gives you data that H&E cannot provide. One more practical note: when you are teaching this to students, do not spend too much time on textbook diagrams. The drawings are clean and idealized. Real slides are messy. Show them cases where the epithelium is attenuated by pathology, where there is overlying debris or exudate, and where the tissue has been folded during processing. Those are the images they will actually encounter on exam day and in clinical practice.
I keep a folder of annotated real-world images on my workstation. It includes lung, kidney, peritoneum, and vascular specimens where simple squamous epithelium appears in all its messy variation. When someone asks me to confirm their identification, I pull up the folder instead of describing it from memory. It takes about three seconds to find the right reference and it prevents a lot of back-and-forth confusion.


