
So You Need to Pick a Site for IV Insertion
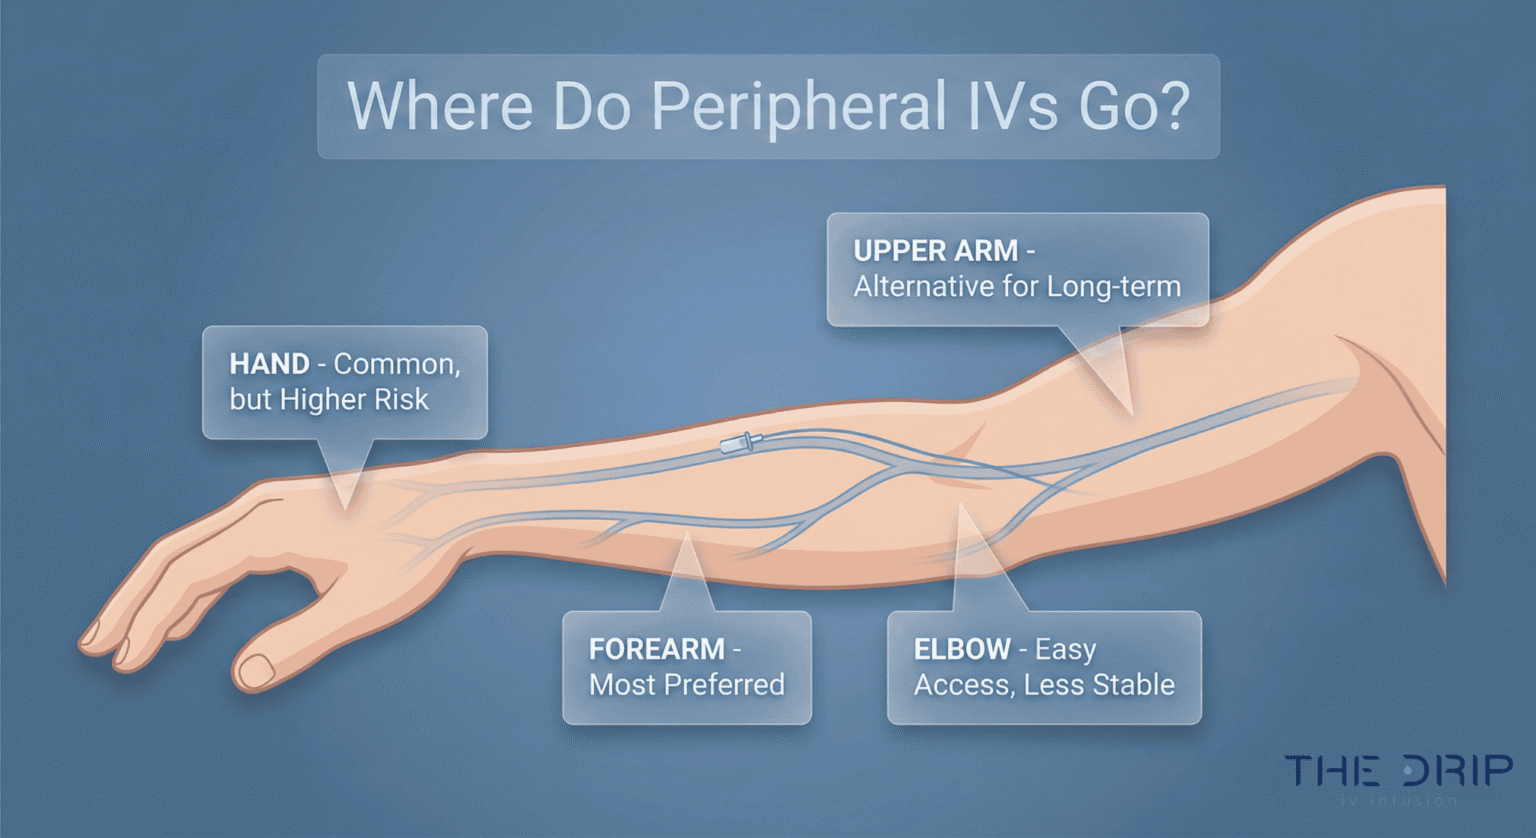
The reality is that picking a good spot for a peripheral IV isn't as straightforward as just rolling up someone's sleeve and going for it. Most people think the back of the hand is the default, but it's often a nightmare in practice. I've seen more failed starts on dorsal hand veins than anywhere else, especially on elderly patients or anyone with fragile, rolling veins. When I'm setting up an IV, I start distally and work my way proximally. That's textbook, but it matters because if you blow a vein in the hand, you've burned through your best option before you even got to the forearm. The forearm is where you want to be for anything that needs to stay in place for more than a few hours. Antecubital fossa veins are fat and easy, sure, but they limit arm mobility and aren't ideal for prolonged infusions or vesicant medications. I learned the hard way once on a trauma shift that checking for collateral circulation isn't optional. I placed an IV on a patient's left arm without doing a proper assessment because the radial vein looked prominent. Two hours later, the limb was compromised downstream because there was insufficient ulnar flow. That was my reminder that a tourniquet check and a modified Allen test before committing to a site can save you from a much uglier problem down the line. Not every hospital has the equipment or protocol for a full modified Allen, but a quick assessment of pulse quality distal to the insertion point takes about ten seconds and prevents a lot of downstream issues.
Getting Sites For Iv Insertion Right
Here's how the process actually works when you're standing at the bedside with a tray and not enough time to overthink it. Gather your supplies first: appropriate catheter size, tourniquet, chlorhexidine prep, transparent dressing, and flushes. Most adult peripheral IVs go in with a 20-gauge or 22-gauge catheter. If you're running blood products or doing CT contrast, bump up to an 18-gauge. Smaller gauges like 24-gauge have their place in pediatrics or for fragile veins, but they're not built for rapid infusion and they clog easier. Tourniquet placement matters more than most people admit. Put it about four to six inches above your intended insertion point, not wrapped so tight that arterial flow is cut off. You want venous engorgement, not ischemia. If the veins aren't showing after five minutes of tourniquet use, try warming the area with a warm pack or having the patient swing their arm gently. Heat causes vasodilation and makes even previously invisible veins pop out. The angle of insertion is where technique separates the people who succeed on the first try from the ones who end up with a hematoma the size of a grapefruit. For most peripheral veins, you're looking at 15 to 30 degrees. Lower angle for superficial veins, slightly steeper for deeper ones. Once you get flashback, lower the angle almost flat and advance the catheter another quarter to half centimeter to make sure it's fully in the lumen before you thread the catheter off the needle.
I had a patient once whose cephalic vein was essentially a tunnel under the skin. It felt like a rigid tube that wouldn't yield. Standard approach failed three times in a row. What I ended up doing was using my non-dominant hand to anchor the vein well below the insertion site and stabilizing from above, then threading the catheter at about a 10-degree angle while maintaining downward traction on the skin. The key was keeping the vein from rolling by compressing it firmly against the underlying tissue. It went in on the fourth attempt without flashback, but I knew it was in because of the resistance change when the catheter entered the lumen. This is one of those cases where anatomical knowledge beats brute force every time.
Get the Full Details

Common Pitfalls and Where People Go Wrong
The biggest mistake I see is picking the wrong gauge for the clinical situation. People default to 22-gauge because it's easier to place and hurts less, but then they try to run viscous fluids or pressurized bags through it and wonder why the infusion is crawling along at half the intended rate. A 22-gauge catheter has roughly a quarter of the flow capacity of an 18-gauge. If you need rapid volume replacement, start with an 18-gauge in the antecubital or a large forearm vein. Don't baby your way into a situation where the patient needs a larger bore and you've already compromised two smaller sites. Another thing that causes problems is excessive needle advancement after flashback. When you see blood return, some clinicians keep pushing the needle forward thinking they need more depth. They're actually punching through the far wall of the vein. What you should do is stop at flashback, lower the angle, advance the catheter assembly only, and watch for flashback again through the hub. If you get it, you're in. If you don't, you've gone through the vein and you're in the tissue around it now. Securing the IV properly is where a lot of aftercare failures happen. A transparent semi-permeable dressing is standard, but if the patient is diaphoretic or has irregular skin surfaces, the dressing will lift and the site becomes a gateway for infection within hours. I've seen dressings fail in under an hour on patients who were sweating through everything because the nurse didn't consider skin prep and adhesion before applying the dressing. Use an adhesion aid or a wrap to secure it properly, and document the site condition at the time of insertion.
What About Challenging Veins?
Rollicking veins, collapsed veins, and dehydrated patients are where people give up too early. Before you move on to an ultrasound-guided approach or call for a centralized line, try a few things that are often overlooked. Hydration matters enormously. A patient who's been NPO for eight hours will have veins that feel different from a well-hydrated one. Giving half a liter of normal saline before attempting difficult IV access can make a dramatic difference in vein fill and palpability. It sounds simple, and in most non-fluid-overloaded patients it's exactly the right call. Tourniquet pressure is another adjustable variable. Too light and the veins don't distend enough. Too tight and you collapse the very veins you're trying to access. Find the sweet spot where you occlude venous return but maintain arterial pulse distal to the tourniquet. If you can't feel a radial pulse while the tourniquet is on, ease the pressure slightly. Ultrasound guidance has changed the game considerably for difficult access. I remember when we had to rely entirely on palpation and anatomy landmarks. Now most hospitals have portable ultrasound units with high-frequency linear probes that make veins visible even when they're not palpable. If you have access to one, use it. The learning curve is maybe an afternoon for basic visualization, and the success rate improvement is substantial. I've placed IVs on patients that I would have walked away from five years ago because I couldn't find a single peripheral vein worth attempting.
Aftercare and Monitoring
Once the IV is in, documenting the gauge, site location, insertion difficulty, and patient tolerance is standard practice. But monitoring doesn't stop there. Phlebitis develops in a significant percentage of peripheral IVs, and the earlier you catch it, the better the outcome. Signs to watch for are redness along the vein track, warmth, swelling, and pain that's disproportionate to what you'd expect from a fresh stick. Most hospitals use a phlebitis scale, and anything above a 2 should trigger evaluation and likely removal of the catheter. Infiltration is another common complication, especially with vesicant medications or in patients with poor tissue integrity. The fluid leaks into the surrounding tissue instead of staying in the vein. Early signs include coolness at the site, swelling, and slowed or stopped infusion despite a clear pathway. If you suspect infiltration, stop the infusion immediately, remove the catheter, and elevate the extremity. Some facilities use specific reversal agents for vesicant extravasation, so know your institution's protocol before the event happens. The lifespan of a peripheral IV is typically 72 to 96 hours according to most current guidelines, but that's not a hard rule. If the site looks good and the patient needs continued access, some protocols allow extension with documented assessment. However, the evidence supporting extended dwell times is mixed, and the infection risk increases with each day beyond the recommended window. Replace the IV if it's no longer needed, not just because it's been there a while.
Bottom line, Sites For Iv Insertion is a skill that improves with repetition and attention to detail. Start distally, assess before you commit, secure properly, and monitor continuously. The patients who get the worst outcomes are usually the ones whose IVs were placed carelessly and then forgotten about until something went wrong.


