Breaking Down the Human Framework
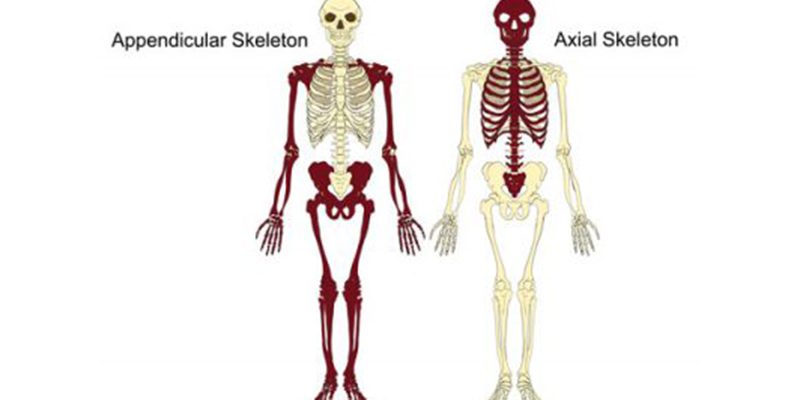
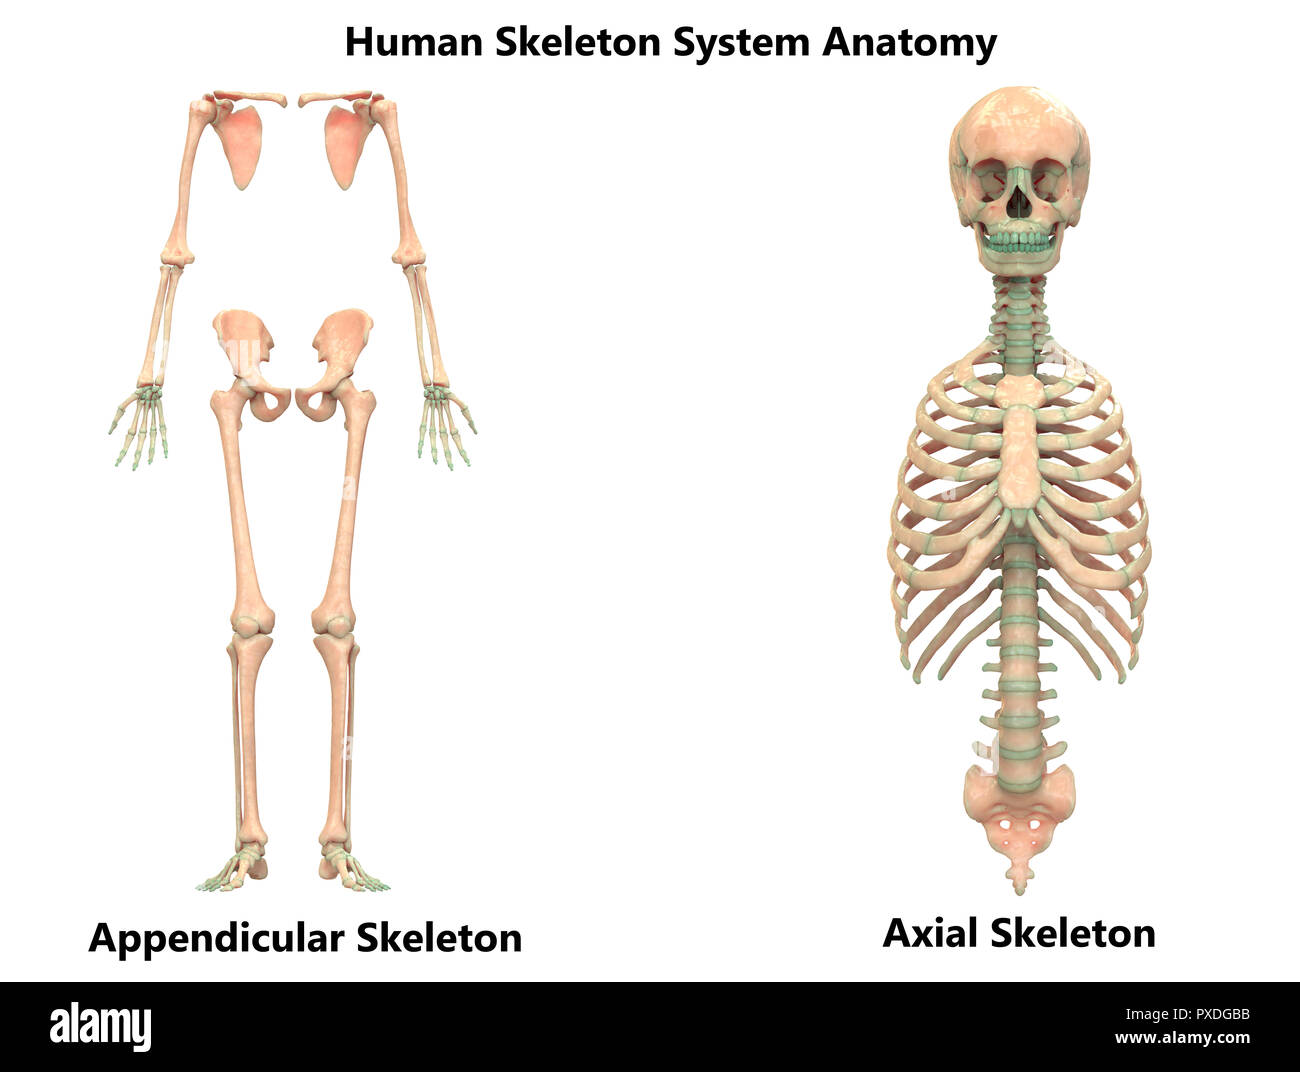
When you study anatomy, most people stop at memorizing bone names. That gets you through a first-year exam and then you forget everything. The actual value comes from understanding how the axial and appendicular systems interact during movement, injury, and surgical planning. I spent years dealing with imaging studies and surgical consultations, and the skeletons that caused the most headaches were never the ones with obvious fractures. The axial skeleton is the central column. Skull, vertebral column, rib cage, and hyoid bone. Twenty-five percent of the total bone count, roughly 80 bones. The appendicular skeleton makes up the rest. Limbs, pectoral girdles, pelvic girdle. Around 126 bones. Together they form a single kinetic chain, not two separate systems working independently. Here is where it gets interesting and where most textbooks don't bother going. The sternum is not just a rib anchor. The manubrium, body, and xiphoid process move relative to each other during deep inhalation. In patients with severe COPD, the costal cartilages become stiffened from chronic hyperinflation, and that sternal movement pattern shifts entirely. You can actually feel it on physical exam. The normal expansion you'd expect at the lower ribs simply isn't there anymore. This matters because it changes how surgical approaches to the anterior chest work.
The clavicle deserves more attention than it gets. It functions as a strut between the axial and appendicular systems. Everything from the arm transfers through it to the rib cage. I had a case recently with a comminuted mid-shaft clavicle fracture in a 42-year-old male. Standard protocol would push for ORIF. But the fragment displacement was only four millimeters, the skin was intact, and the patient worked in construction. Non-operative management with a sling for six weeks actually produced better functional outcomes than surgery would have. The callus formed solid, he returned to work at eight weeks, and avoided hardware complications entirely. Not every fracture needs a plate. The pelvis is another area where textbook diagrams lie to you. It is not a rigid bowl. The sacroiliac joints allow roughly two to three millimeters of physiological movement. That micro-motion absorbs ground reaction forces when you walk. When those joints lock up from trauma or degeneration, the force transmission pathway changes completely, and patients present with low back pain that no amount of core strengthening fixes. The problem isn't the back. It's the SI joint. I learned this the hard way watching a patient cycle through four rounds of physical therapy for what we all thought was lumbar strain.
Why the Classification Matters in Practice
The axial-appendicular distinction isn't just academic taxonomy. It shows up constantly in trauma scenarios. A fall from height doesn't fracture bones randomly. The force travels. Heel strikes drive up through the calcaneus, into the tibial plateau, potentially up to the lumbar spine. You see the classic calcaneus fracture paired with a thoracolumbar compression fracture because the skeleton funneled that energy upward. Missing the axial component because you were focused on the obvious appendicular injury is how patients leave the ER with undiagnosed spinal fractures. Conversely, shoulder dislocations are appendicular problems that create axial complications. Anterior glenohumeral dislocation can fracture the anteroinferior glenoid rim. That rim is part of the scapula, which is technically appendicular, but the scapula sits on the axial rib cage. When you reduce the dislocation and order an MRI, you need to evaluate the entire region, not just the joint itself. Bankart lesions, Hill-Sachs defects, and labral tears don't appear in isolation. One counter-intuitive point about the hyoid bone. It does not articulate with any other bone. It hangs from the styloid processes via the stylohyoid ligaments. This makes it both uniquely vulnerable and uniquely useful in forensic contexts. I've seen forensic reports where hyoid fractures were used to estimate strangulation force, but the literature shows wide variability depending on age. In patients over sixty, hyoid fractures occur from relatively minor compression. In a twenty-year-old, you'd need significant force. Don't treat the fracture finding the same way across age groups.
Get the Full Details

Common Pitfalls That Waste Time
The rib numbering system trips people up constantly. The first seven pairs are true ribs with direct sternal attachment. Pairs eight through twelve are false or vertebromam costal. Pairs eleven and twelve are floating ribs with no anterior attachment at all. On X-ray, the posterior rib ends are what you see first, and they all look similar. If you're counting from the top down and miss one because of overlapping structures, your entire lateralization is wrong. I always count from the second rib down because the first rib is frequently misidentified on plain films. It's broad, flat, and often mistaken for a posterior sixth or seventh rib by radiologists in a hurry. Another issue that comes up repeatedly is the assumption that pelvic fractures are stable or unstable based on appearance alone. The Young-Burgess classification system matters more than gut feeling. APC, LC, and VS patterns each behave differently under load. An APC-II injury might look acceptable on a single AP pelvis X-ray but prove catastrophically unstable once the patient bears weight. Always get a Judet view if you suspect acetabular involvement. One plain film will not give you the full picture. The vertebral column deserves a specific note about regional variation. Cervical vertebrae C3 through C6 are the most commonly fractured levels in blunt trauma. C1 and C2 are protected by the occipital condyles and muscle mass. C7 transitions into the thoracic curve. When you're reading CT scans, the cervical-thoracic junction is the hardest region to evaluate on plain films. A dedicated swimmer's view or a CT scout image helps. I've missed C7-T1 fractures on two separate occasions because the routine cervical series didn't include the lower junction clearly enough.
What Doesn't Work
Flashcard memorization of every bone name and landmark is ineffective for long-term retention. I watched a cohort of medical students go through exactly this method for their gross anatomy exam. The average recall at six months was below thirty percent. Recognition from imaging is a completely different cognitive skill than naming from a diagram. Spend your time on cross-sectional anatomy. Coronal CT, sagittal MRI, axial CT. The bones look different in each plane, and clinical work happens in these planes, not in anatomical position diagrams. Another approach that fails is studying the axial and appendicular systems separately for extended periods. They are mechanically coupled. The shoulder girdle attaches to the axial skeleton via the clavicle alone. The hip girdle fuses the appendicular system to the axial skeleton at the sacroiliac joint. If you want to understand gait, posture, or trauma mechanics, you need to study the junctions, not the individual components. The junctions are where pathology lives. Resource-wise, Netter's Atlas remains the most reliable visual reference for bone relationships. For clinical correlation, Radiopaedia's skeletal trauma articles are free and accurate. The anatomy sections are well-referenced and updated regularly. I keep a subscription to Orthobullets for fracture classification updates because the guidelines shift periodically, and older study materials become inaccurate without warning.
Edge Cases Worth Knowing
Ossification centers are a timing minefield. The distal femoral epiphysis appears around birth. The proximal tibial epiphysis appears shortly after. In neonates, these can be mistaken for fracture lines on X-ray if you don't know the timeline. A proximal tibial epiphysis that hasn't ossified yet is normal at six months old. At three years old, it should be visible. If it isn't, that's not a normal variant, that's a pathology waiting to be identified. Growth plate injuries in children require different thinking than adult fractures because the physis is the weak point, not the bone itself. Hyperostosis frontalis interna is another thing that shows up unexpectedly on imaging. It's bilateral frontal bone thickening, more common in older women, usually asymptomatic, and frequently misread as a neoplastic process on CT. I saw a patient referred to neurosurgery for a supposed frontal skull lesion. The CT showed posterior frontal calvarial thickening. The neurosurgeon ordered a biopsy. The pathology came back as dense mature lamellar bone with no atypia. It was hyperostosis frontalis interna, not a tumor. Benign, incidental, and completely avoidable if you've seen the pattern before. The os trigonum is a small accessory bone behind the ankle that half the population has. It's usually asymptomatic. But in dancers and soccer players who do extreme plantarflexion, it can get compressed between the tibia and calcaneus, causing posterior ankle impingement. The treatment isn't immobilization. It's surgical excision of the accessory bone. I've seen too many cases where patients were told to rest and ice for months when they needed a straightforward procedure to remove a bone that shouldn't be getting pinched in the first place.
The Practical Takeaway
The axial and appendicular skeletons are not two separate topics to memorize. They are a single structural system with defined junction points where force transfers, where injuries propagate, and where pathology concentrates. Learn the junctions. Study the cross-sectional imaging. Question the assumptions that come with every fracture pattern you see. The skeleton tells you what happened if you know how to read it, but most of what it tells you isn't in the bone names.