Why people confuse these two and what actually matters
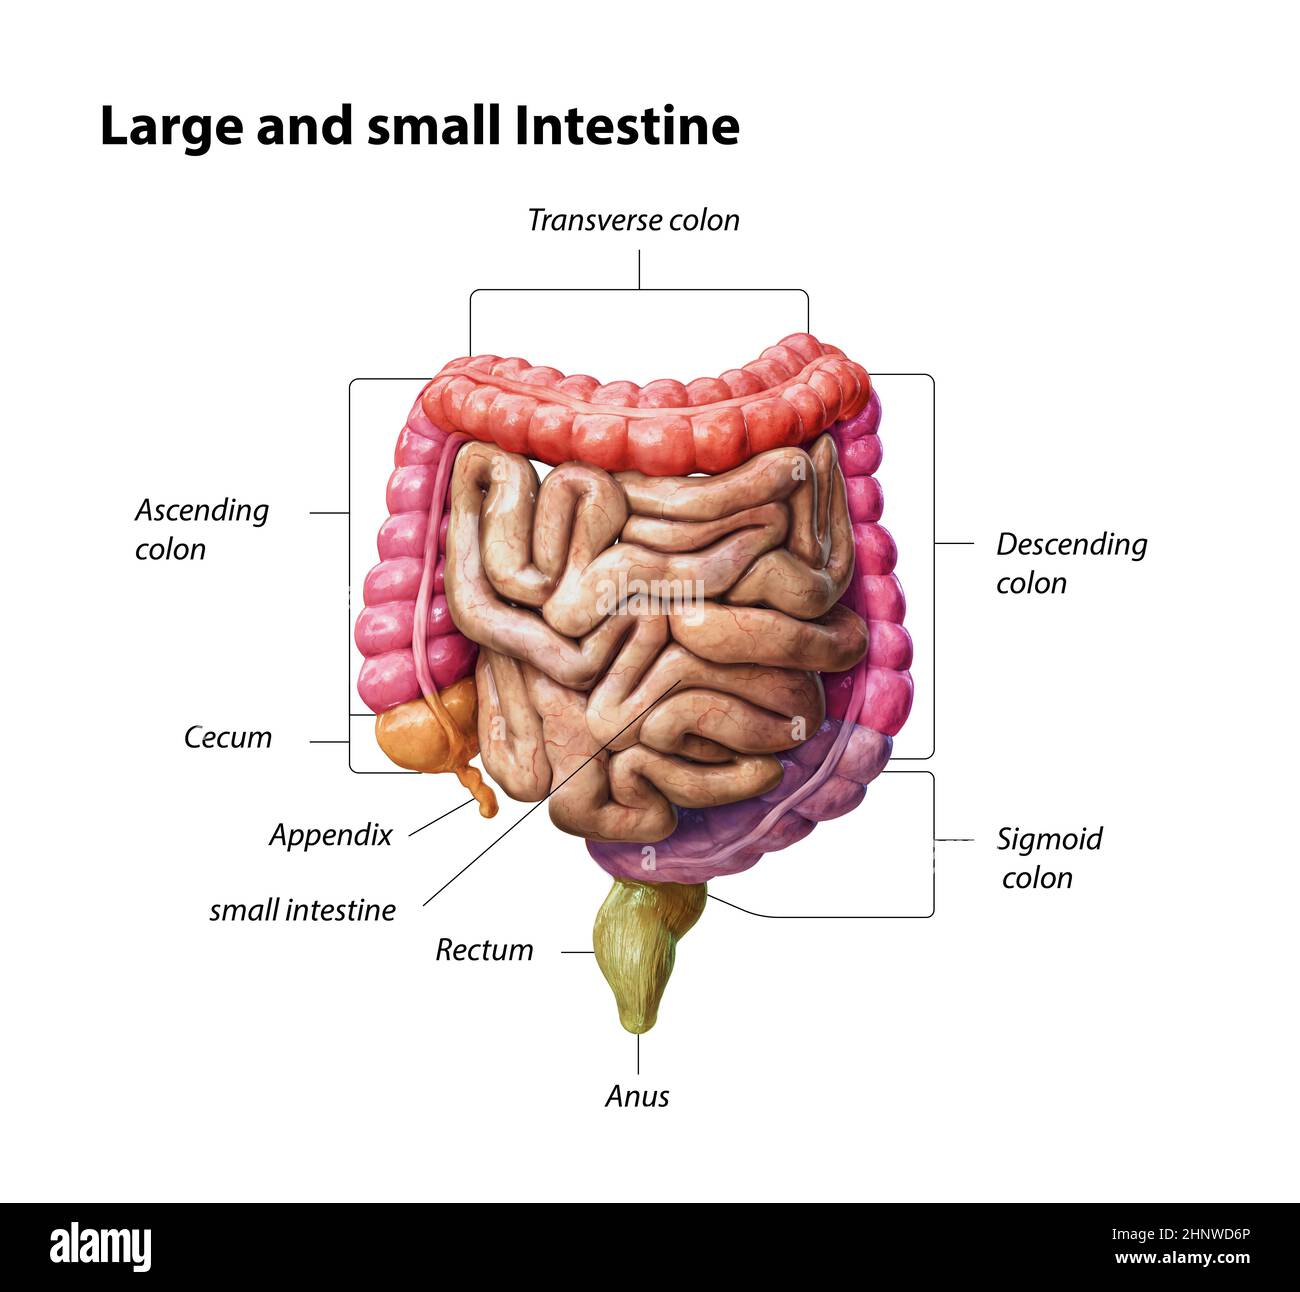
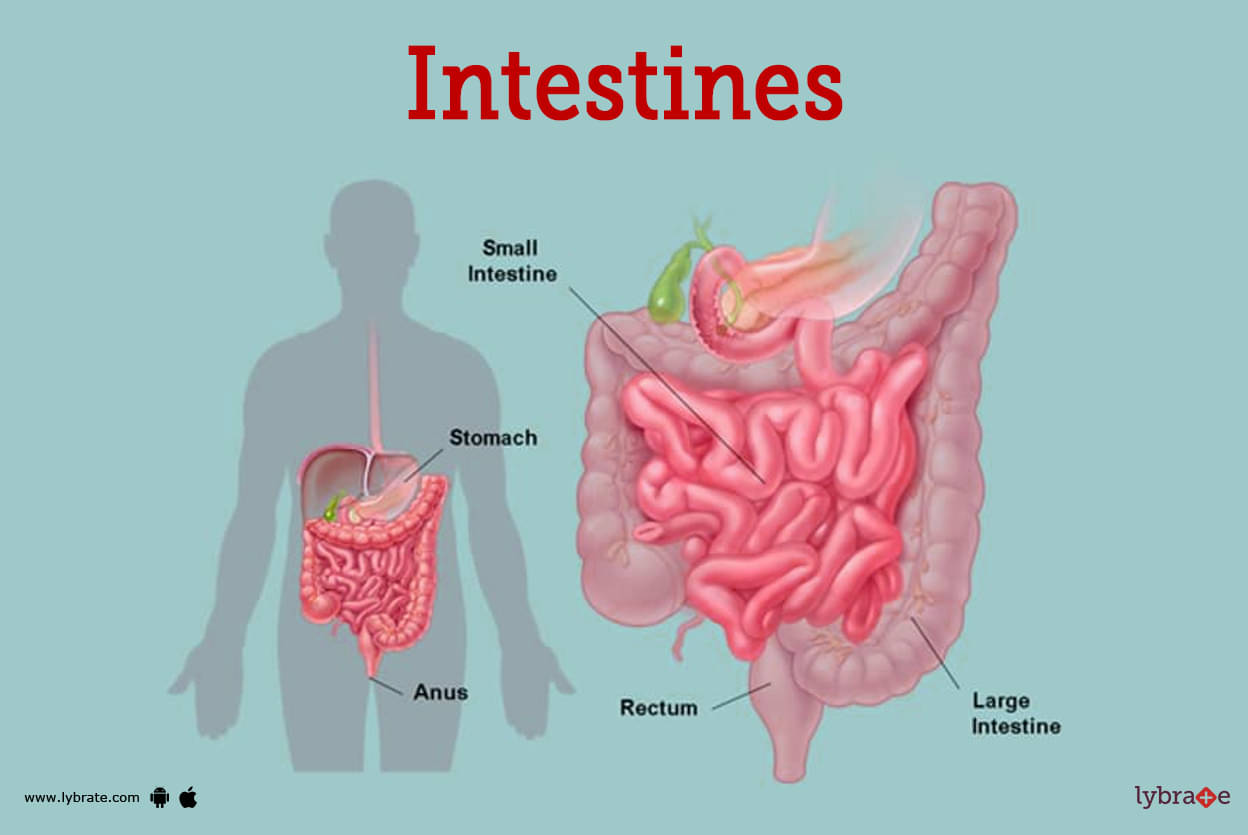
I used to give a quick overview of the small and large intestine during anatomy review sessions, and almost every student would mix up the job descriptions. They think the large intestine does most of the digestion because it sounds more important, or they assume the small intestine is where waste gets processed since it literally follows the small path. Neither is right, and the confusion tends to cause real problems when you start studying pathologies, interpreting scans, or working in surgical fields where knowing the exact segment matters for incision planning. The small intestine is roughly six meters long in a cadaver, though it collapses to about three meters in living tissue due to muscle tone. It runs from the pylorus of the stomach through the duodenum, jejunum, and ileum before dumping into the cecum. The large intestine is shorter at about 1.5 meters but significantly wider, running from the ileocecal junction through the colon and rectum, ending at the anal canal. Length versus diameter is the first functional divide, and it explains almost everything else about how each organ operates. The small intestine is built for absorption, not storage. Its interior surface area is approximately 250 to 300 square meters thanks to the plicae circulares, villi, and microvilli, a structure that would make any textbook diagram look wildly excessive if you had never seen the organ gross. The large intestine has no villi, very few plicae, and a smooth inner wall that is mostly designed to reclaim water and electro Lytes from chyme, compaction the residue, and hold fecal matter until defecation. Digestion is finishing in the small intestine; the large intestine is essentially a drying and staging facility.
I ran into this practically last year when I was helping a medical coding team sort out a billing dispute for an endoscopic procedure. The report listed "small bowel resection" but the surgical notes described a right hemicolectomy, which is large intestine. The coder had initially pulled the code for a small intestinal resection because the surgeon mentioned "the small bowel was mobilized during the approach." The workaround was straightforward once you know the landmarks: if the resection line included the ileocecal valve or the cecum, it is large intestine regardless of how the small bowel was handled for exposure. The appendiceal orifice is also a hard boundary marker. You should map the resection margins against those anatomical points instead of relying on operative shorthand, because surgeons often refer to the terminal ileum casually in a colectomy note without meaning to imply a small bowel procedure. There is a counter-intuitive detail most people miss about the large intestine. Despite its name, it does not absorb large molecules or nutrients in any meaningful amount. The colon absorbs water, sodium, chloride, and short-chain fatty acids produced by bacterial fermentation. If you are dealing with malabsorption conditions like celiac disease or pancreatic insufficiency, the problem is almost always in the small intestine, not the colon, and running colon-focused tests on those patients will waste time and produce nothing useful. The small intestine is the actual nutrient highway; the large intestine handles residual processing. Another nuance that trips people up is motility. The small intestine uses segmentation and peristalsis continuously throughout the day, moving content forward in millimeter increments. The large intestine has mass peristalsis, which is a much slower, stronger wave that typically happens only three to four times a day, usually after eating. This is why you can go hours between bowel movements and why laxatives that stimulate colonic mass movements have a delayed onset of about six to twelve hours. If you need rapid GI transit, targeting the small intestine with prokinetics is faster, but that comes with its own set of arrhythmia and electrolyte risks that most clinicians overlook.
Practical breakdown by function
Digestion: The small intestine is where the bulk of chemical digestion occurs. Bile salts and pancreatic enzymes mix with chyme in the duodenum, and brush-border enzymes complete the breakdown of carbohydrates, proteins, and fats along the jejunum and ileum. The large intestine has no significant digestive enzyme activity beyond what gut bacteria contribute. Absorption: Glucose, amino acids, fatty acids, vitamins B12 and K, bile acids, and most water are absorbed in the small intestine. The colon absorbs the remaining water and electrolytes, roughly 100 to 200 milliliters per day under normal conditions, plus the short-chain fatty acids from bacterial fermentation of indigestible fiber. Secretion: The small intestine secretes intestinal juice rich in bicarbonate and mucus, about one to two liters daily, to protect the mucosa and neutralize acidic chyme. The large intestine secretes primarily mucus for lubrication, with minimal fluid or electrolyte secretion compared to the small bowel.
Get the Full Details
Bacterial load: The duodenum and jejunum are relatively low in bacteria, maybe 10 to 105 colony forming units per milliliter. The ileum climbs to 108, and the colon is densely populated at 1011 to 1012 CFU per milliliter. This gradient matters clinically. Small intestinal bacterial overgrowth, or SIBO, is a real condition that causes bloating, diarrhea, and B12 deficiency, and it gets missed because the symptoms overlap with irritable bowel syndrome. The large intestine flora is expected and necessary; the small intestine flora should be low.
When you need to differentiate them on imaging
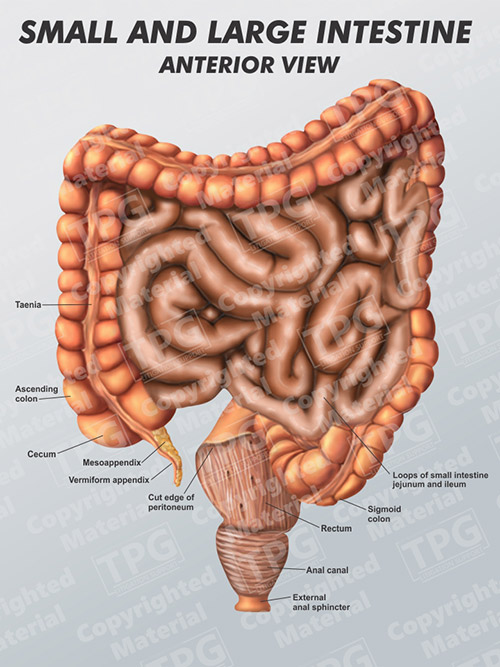
On CT scans, the small intestine has a characteristic folded mucosal pattern called plicae circulares that are visible as transverse folds in the jejunum, while the colon shows haustral folds, which are much broader and less frequent. The taeniae coli, three distinct longitudinal muscle bands, are a reliable landmark for identifying the colon. If you see those bands converging at the appendix base, you are looking at the cecum, which is large intestine. On endoscopy, the small bowel lumen is narrower and the folds are more prominent and circular, whereas the colon has a wider lumen with visible haustra and the appendiceal orifice. The ileocecal valve is the transition point, and it looks like a bulging flap that you can sometimes compress gently with the scope to peek into the terminal ileum. I worked through a case a couple of years ago where a gastroenterology fellow kept referring to the transverse colon as the "mid-small bowel" during a teaching round. The confusion was not just terminology. They had misidentified the lesion location and were planning a colonoscopy approach for what was actually a small bowel issue visible only on push enteroscopy. The fix was to trace the taeniae back to their origin at the cecum and confirm the lesion was between the hepatic flexure and the splenic flexure. Once that was locked in, the follow-up procedure was correct. Mislabeling the segment leads to wrong tests, wrong approaches, and delayed diagnosis.
Common pitfalls and where the model breaks down
The short version is that the boundary between these organs is not always clean in practice. The ileocecal region is a gray zone. Surgeons and endoscopists sometimes struggle to clearly delineate whether a lesion is in the terminal ileum or the cecum, especially with inflammatory bowel disease where both segments can be involved simultaneously. Crohn's disease does not respect the small-large boundary, and that makes anatomical labeling frustratingly imprecise. Another failure point is assuming that because the large intestine is shorter, it is less clinically significant. It is not. Diverticulosis affects roughly half of people over sixty, and colorectal cancer is one of the leading causes of cancer mortality. The small intestine is also prone to pathology, including carcinoid tumors, lymphoma, and adenocarcinoma, but those are rarer and often diagnosed late because there are fewer routine screening tools for the small bowel compared to colonoscopy. If you are trying to manage GI symptoms and only focus on one segment, you will miss things. A patient with chronic diarrhea might have a small intestinal issue like SIBO or celiac, but if you jump straight to colonoscopy and find mild hemorrhoids, you have treated the wrong problem. Similarly, a patient with constipation might have slow transit colonic inertia, which means the large intestine is the culprit, but if you only test the small bowel, you are spinning your wheels.
The most practical workaround I have found is to use a combination of history, lab work, and targeted imaging before committing to a single-segment workup. Check B12 and folate levels for small intestine issues. Look at C-reactive protein and fecal calprotectin for inflammation, which can point to either region but often suggests small bowel involvement if elevated. For colonic evaluation, colonoscopy remains the gold standard. For small bowel evaluation, capsule endoscopy or MR enterography is more useful, depending on the suspected pathology.