What You're Actually Looking At
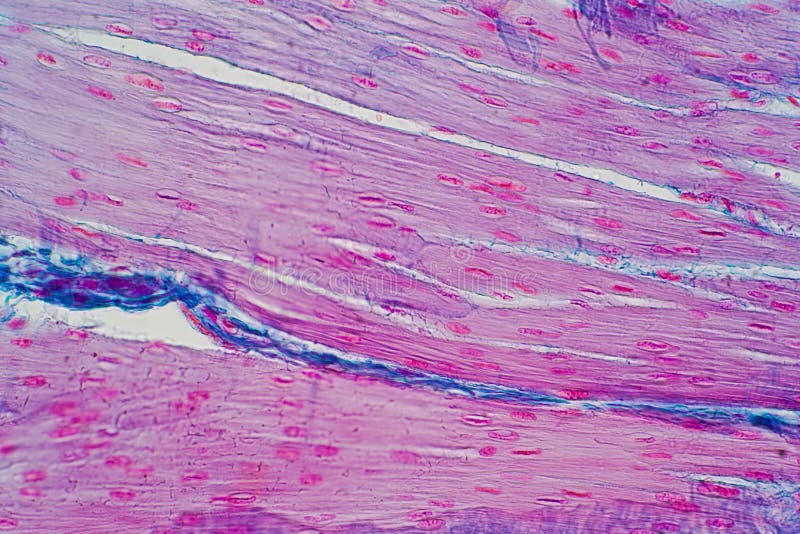
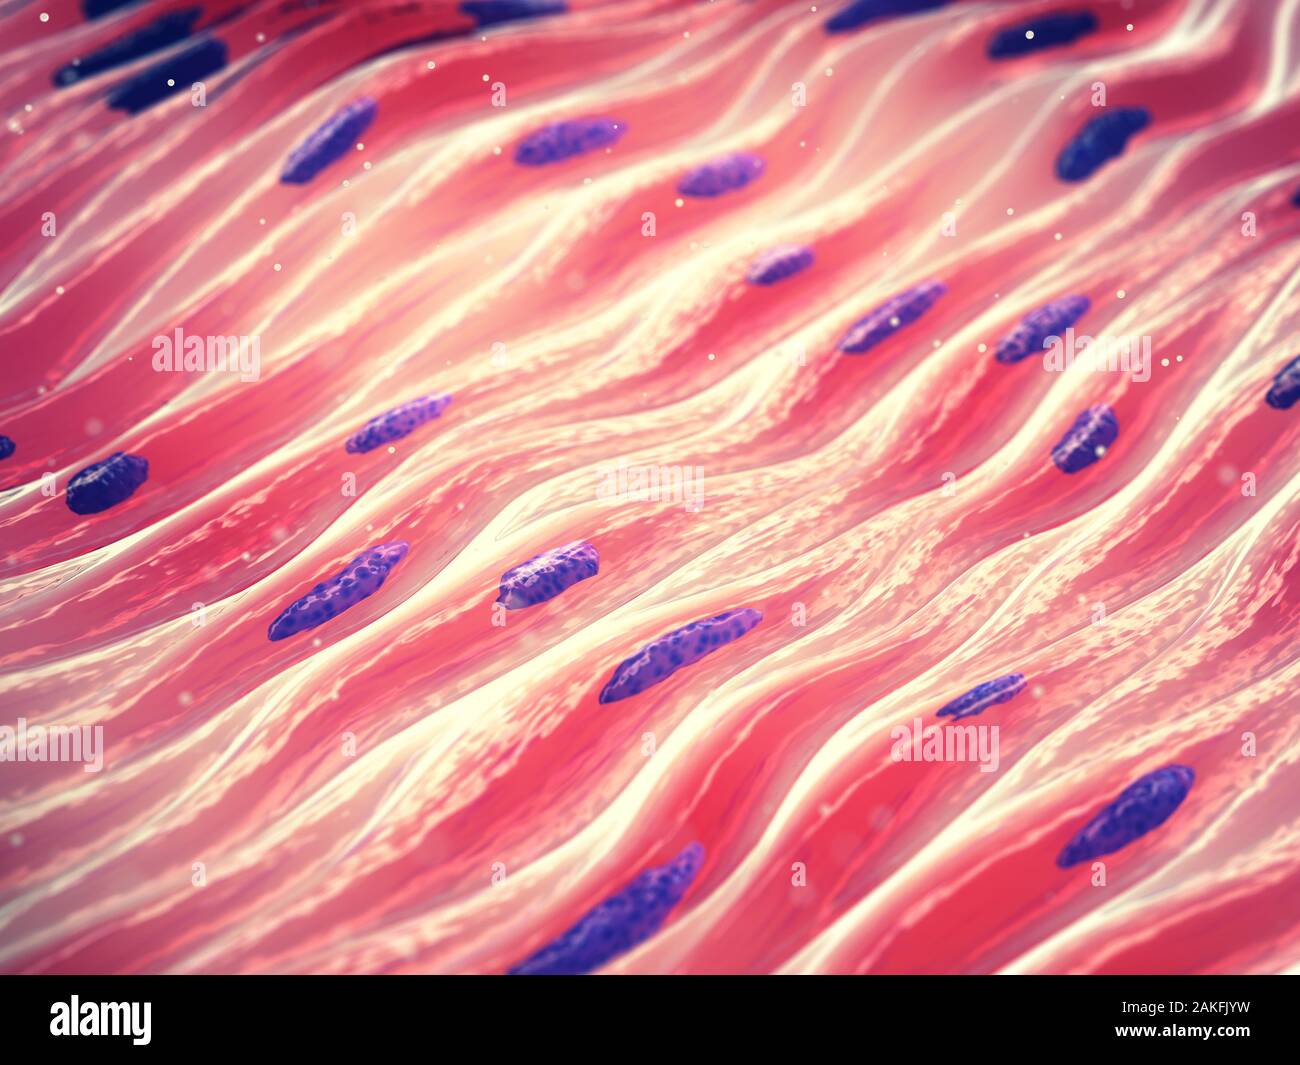
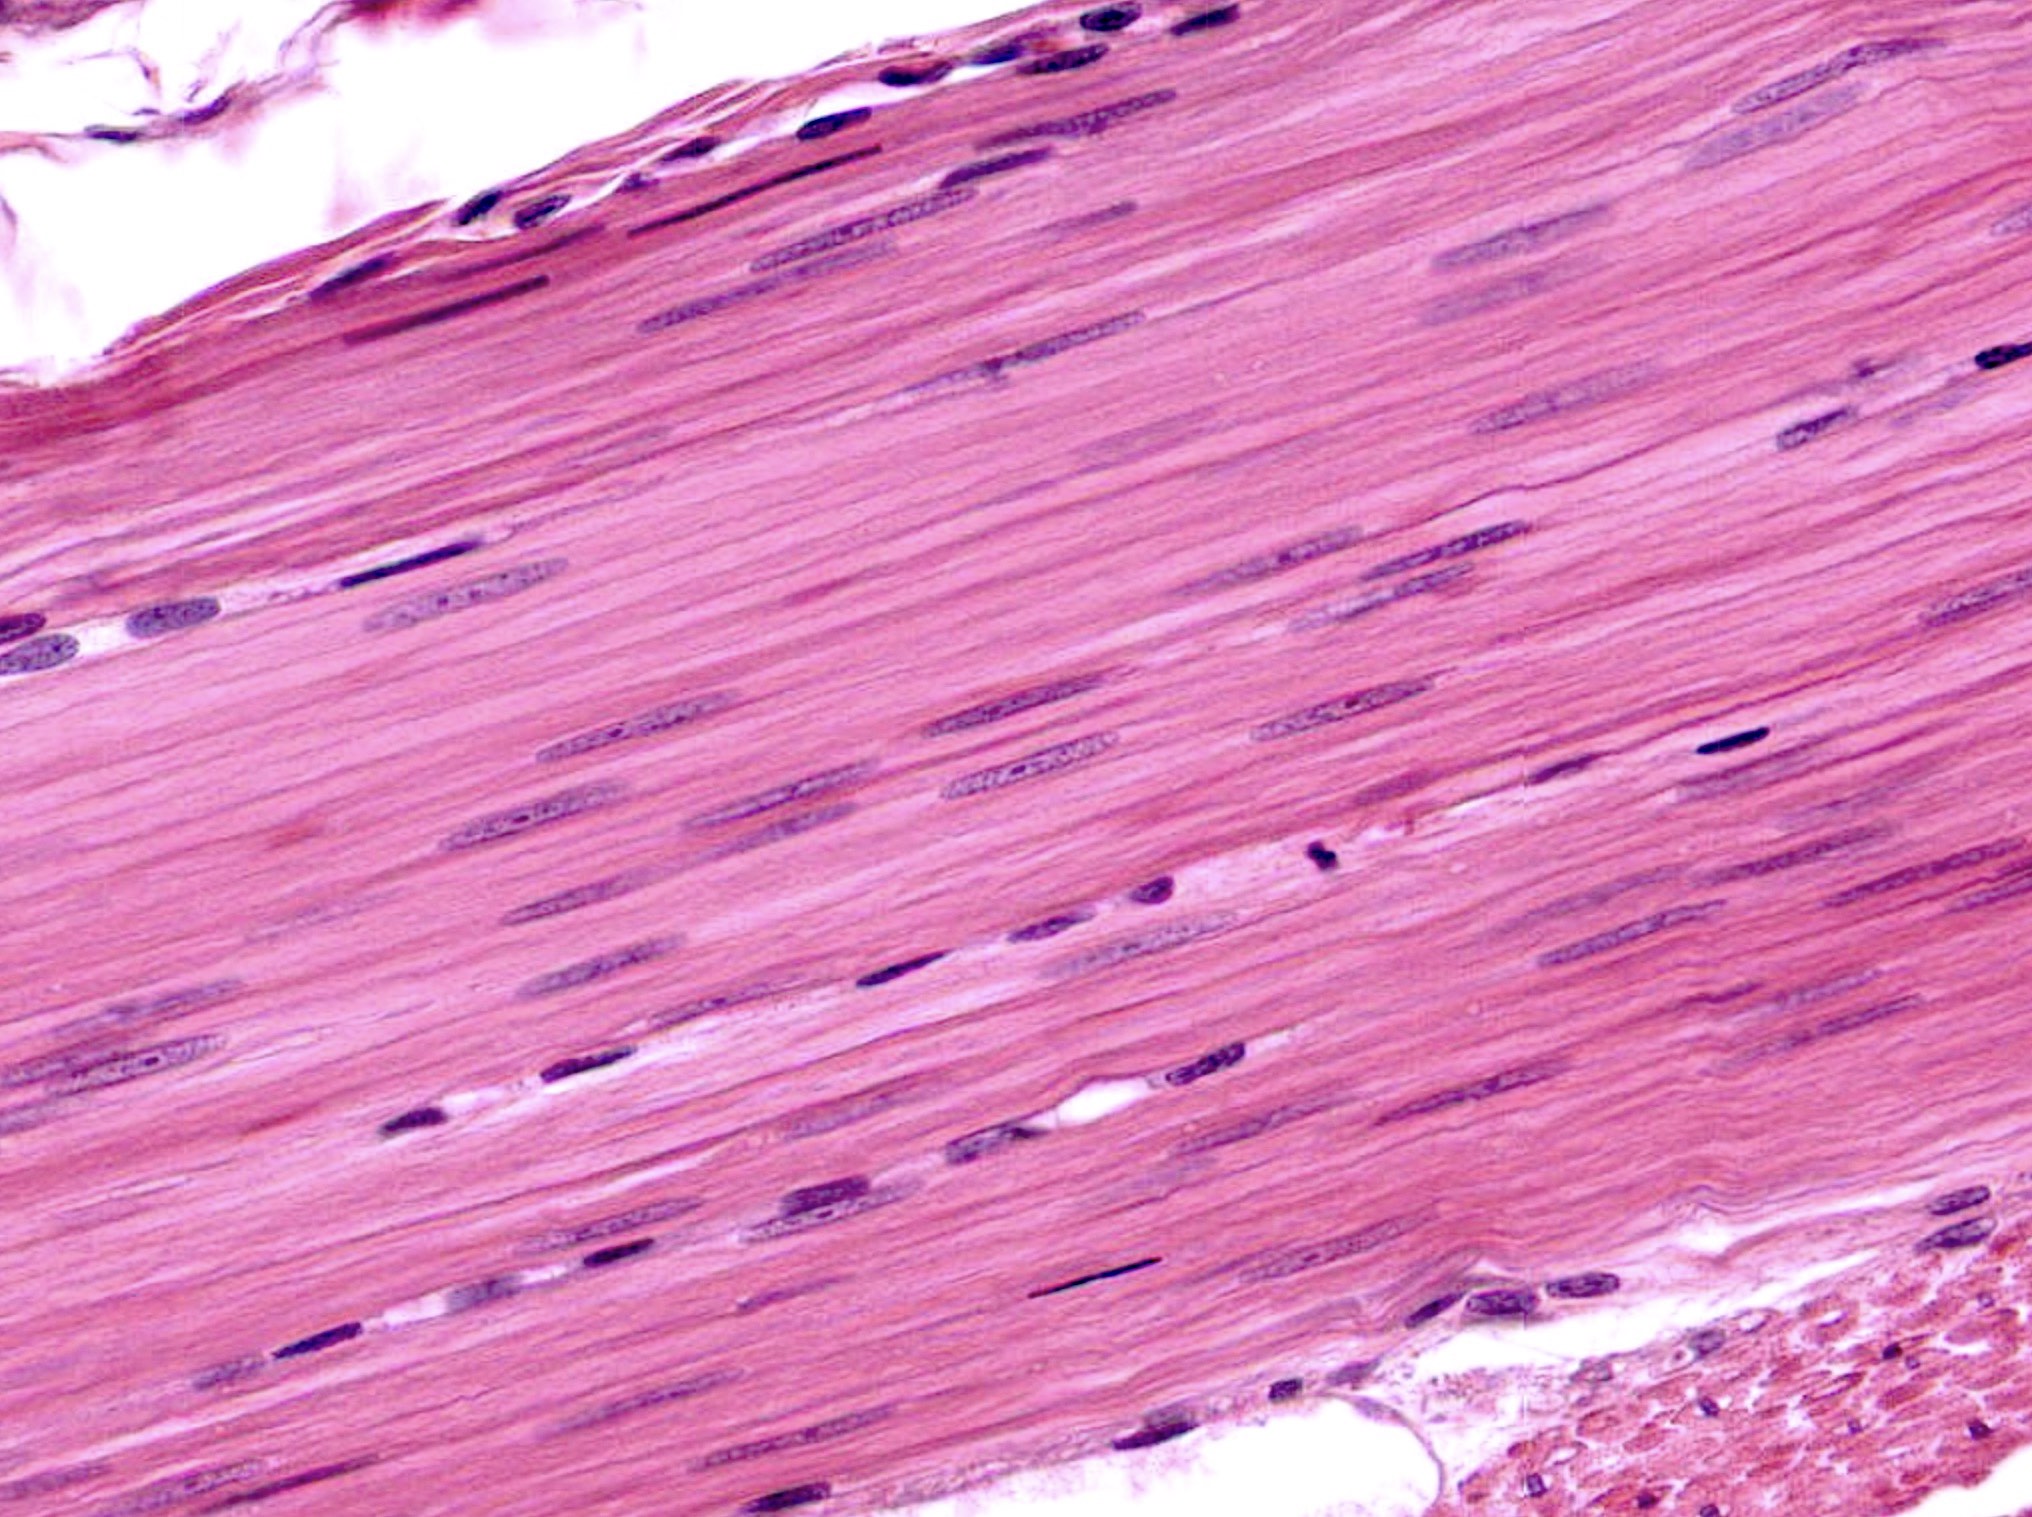
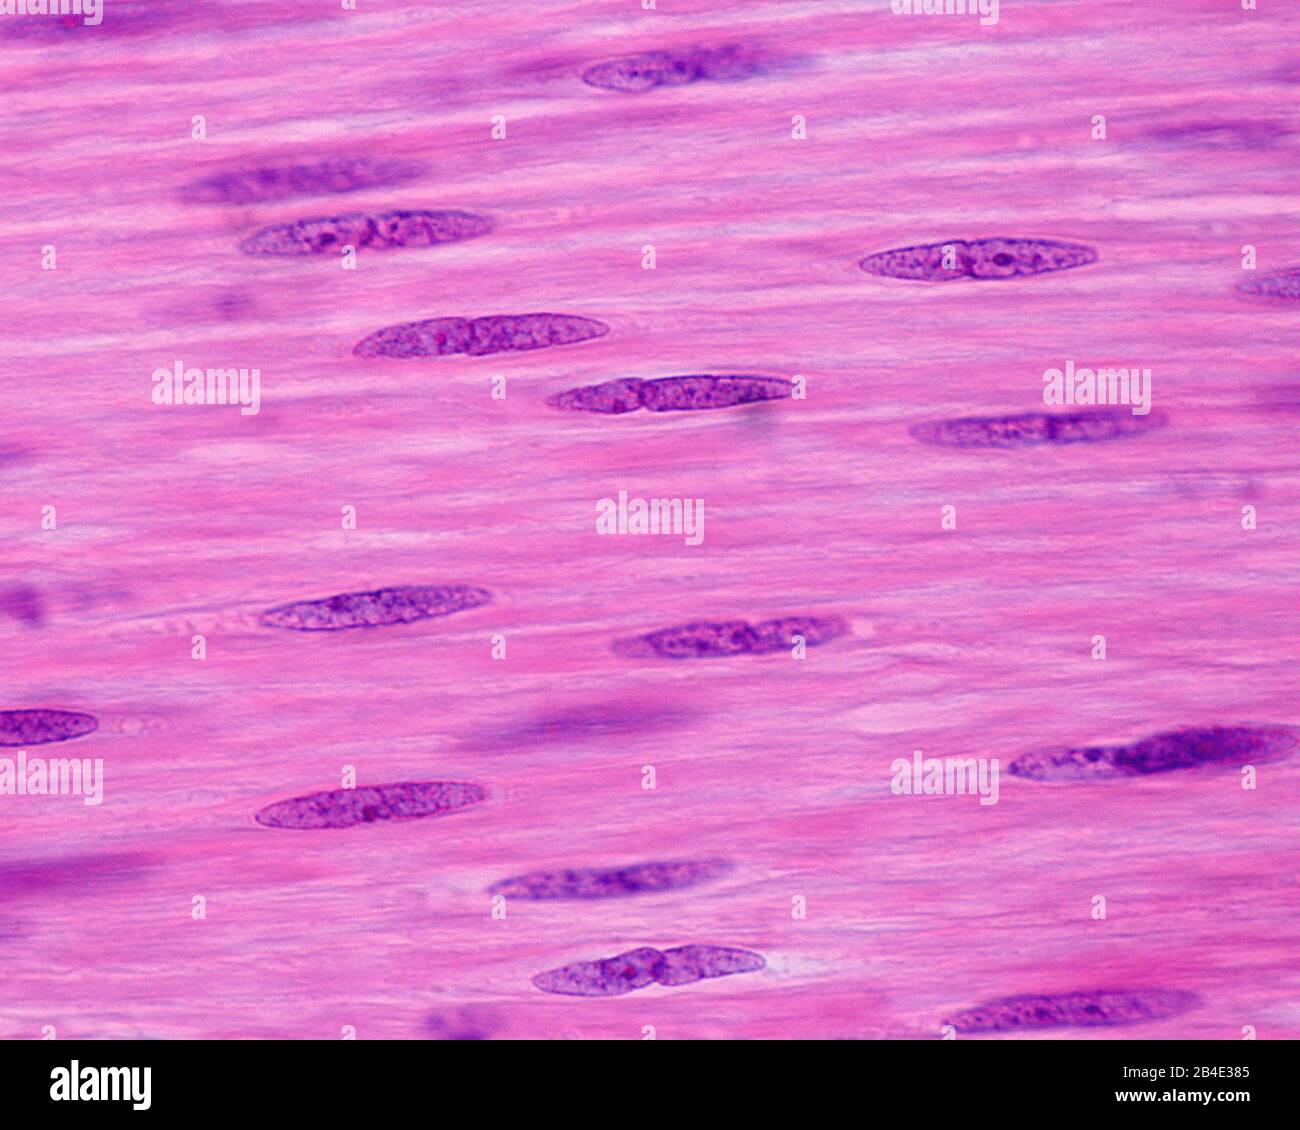
When you put smooth muscle under a light microscope, you're looking at spindle-shaped cells with a single central nucleus. They don't stripe. That's the thing most people miss immediately when they first look at a slide and start comparing it to skeletal or cardiac muscle. The fibers run in sheets or bundles, oriented in different directions depending on which organ they came from. A cross-section looks like a honeycomb of small circles. A longitudinal cut shows those tapered ends stretching out. The staining matters more than most people realize. Standard H&E will show the pink cytoplasm and the purple nuclei, but the detail is thin. The cells are small, usually 20 to 500 micrometers depending on location, and they pack tightly together with very little extracellular matrix between them. You won't see much structure beyond the nucleus unless you've done the prep right.
Smooth Muscle Under Microscope: What You Need to Know
If you're trying to actually identify smooth muscle and not just confirm that something is muscle tissue, you need to understand how it differs from the other two types. Skeletal muscle has those obvious striations and multiple nuclei per cell pushed to the edges. Cardiac muscle has striations too, plus intercalated discs that look like dark lines running perpendicular to the fiber. Smooth muscle has neither. It's smooth. The name is literally descriptive. The sarcoplasmic reticulum is sparse. You won't see the organized T-tubule system you find in skeletal muscle. Instead, smooth muscle relies on caveolae, those tiny invaginations of the plasma membrane, for calcium handling. Under a regular light microscope you can't see caveolae, obviously. But it explains why smooth muscle contracts slower and sustains contraction longer than skeletal muscle. That's not trivia. It matters when you're trying to figure out what organ a sample came from based purely on microscopic appearance.
Preparing the Slide Yourself
Fixed tissue sections are fine if your lab already provides them. Fresh tissue is where things get interesting, and where most people fail. If you're working with something like intestinal smooth muscle from a fresh dissection, you need to act fast. The tissue starts degrading within minutes once it's out of the body, and the artifacts you create during that window will make identification nearly impossible. I once spent two hours trying to figure out why my smooth muscle samples looked like they had bizarre vacuoles scattered through the cytoplasm. I kept thinking the staining protocol was wrong. Turns out I'd left the tissue on ice too long before fixing it. Ice crystals were forming in the cells, creating artifactual clear spaces that looked pathological. Cutting the time from excision to fixation down to under five minutes eliminated the problem entirely. Nowhere in any textbook does this specific issue get mentioned, but anyone who's prepped fresh GI tract samples will recognize it immediately.
Get the Full Details
Sectioning and Staining Details
Paraffin embedding is the standard approach. Cut sections at 4 to 6 micrometers thick. Anything thicker and the individual cell borders blur together. You'll still see the nuclei clearly, but you lose the ability to distinguish individual cells from the bundle. Thinner than 4 micrometers and you're cutting through the nucleus so often that the slide looks like a field of overlapping donuts, which is not helpful for anything. H&E is sufficient for basic identification. Verhoeff-Van Gieson is better if you need to see the elastic fibers around blood vessels in the muscularis layer. The trichrome stains work too, especially Masson's, which will color the muscle fibers red and the collagen blue, making the boundary between muscle and connective tissue actually visible instead of blending into an ambiguous pink zone. For research purposes, immunofluorescence against smooth muscle actin (SMA) or caldesmon gives you definitive confirmation, but that's a different workflow entirely.
Common Identification Pitfalls
Myofibroblasts are the number one confusion point. They look almost identical to smooth muscle cells under H&E. Both have spindle shapes, both have central elongated nuclei, and both exist in connective tissue. The difference is functional and molecular, not really visible on a routine stain. Myofibroblasts have more prominent rough ER, more collagen production machinery, and they express alpha-smooth muscle actin too, which defeats the purpose of using SMA as a marker if you're relying solely on morphology. You need electron microscopy or a panel of additional markers like smooth myosin heavy chain to tell them apart reliably. Another issue: vascular smooth muscle versus visceral smooth muscle. Vascular SM is arranged in a single concentric layer around the vessel lumen. The cells are more uniformly oriented. Visceral SM, found in organs like the uterus or intestines, forms layers that interweave. In the gut you have an inner circular layer and an outer longitudinal layer, and between them the cells mix and change direction. Under the microscope, a cross-section of a blood vessel will look dramatically different from a cross-section of intestinal wall, even though both are smooth muscle. Beginners often think they're seeing two different tissues because they don't account for orientation.
What to Look for When Identifying It
Start by checking for striations. If you see them, it's not smooth muscle, period. Check nuclear count and position. Multiple nuclei at the periphery means skeletal muscle. One central nucleus means either smooth muscle or a fibroblast. Then check the overall architecture. Are the cells bundled in parallel sheets? Do they taper at the ends? Is there a noticeable amount of connective tissue separating individual cells? Smooth muscle cells sit close together but not fused. There are gap junctions in visceral smooth muscle that allow electrical coupling, but you can't see those optically. The cytoplasm is homogeneous and eosinophilic. No granules, no inclusions, no vacuoles unless you made an artifact. The nucleus is cigar-shaped or ovoid, sometimes appearing comma-shaped if it's cut at an angle. Remember that angle effect. A longitudinal section through the middle of the nucleus looks elongated. A oblique cut makes it look rounder, which can be mistaken for a different cell type entirely.
Limitations of Light Microscopy
You can identify smooth muscle confidently at this level, but you cannot determine its contractile state, its differentiation status, or its specific subtype without going further. Dense body proteins, intermediate filaments, the arrangement of thin and thick filaments, the density of calcium channels, the presence or absence of gap junctions — none of that is visible with standard light microscopy. If you need any of that information, you're moving into electron microscopy territory or immunohistochemistry, and the workflow changes completely. Additionally, formalin-fixed paraffin-embedded tissue undergoes some protein crosslinking that can make the cytoplasm appear more densely packed than it actually was in vivo. Frozen sections preserve more native structure but introduce their own artifacts, particularly ice crystal damage in vascular smooth muscle where the cells are smaller and more fragile to begin with. There's no perfect preparation method. You pick the compromise that fits your question.