The Usual Way People Talk About Aging Is Wrong
You will find that almost every introduction to gerontology opens with the same three assumptions: that aging is a biological decline, that older people are uniformly vulnerable, and that society should fix them. These assumptions are wrong, and they have cost researchers a lot of time over the years. The Sociological Perspective Of Aging does not start from biology at all. It starts from the observation that age is a social category first, and the biological changes that come with it are interpreted through that category. That distinction is small on paper and huge in practice. I spent most of my early career trying to merge life-course theory with institutional policy analysis, which is a combination that sounds impressive until you realize the two traditions speak completely different languages. Life-course folks want individual trajectories. Policy wonks want aggregate cohorts. The first time I tried to use macro-level pension data to explain why one neighborhood's elderly population was self-organizing mutual aid networks while the one two miles away collapsed into dependency, I hit a wall. The data literally could not see what was happening. What saved me was going into the field and talking to people for three months instead of running another regression on census tract variables. The Sociological Perspective Of Aging does not care about your R-squared value when the mechanism you are looking for is informal caregiving between neighbors who do not consider themselves related.
Why the Sociological Perspective Of Aging matters more than the medical model
The medical model asks what is broken in the body. The sociological perspective asks what the body is being asked to do inside a society that has decided certain ages are productive and others are not. That is a very different question and it produces very different answers. Take the example of retirement. Medicine calls it a health transition. Sociology calls it a status passage that varies by class, race, gender, and geographic labor market. The same person can exit formal employment and immediately enter three different social realities depending on which of those axes they sit on. The core frameworks you actually need to know There are a handful of frameworks that recur constantly in this literature. You should know them, but more importantly you should know their failure modes. Life-course theory is the big one. It gives you principles like the timing of lives, linked lives, and human agency. The principle of linked lives is the most useful and the most abused. It simply means that individual trajectories are embedded in social networks, so one person's aging is structurally connected to another person's. When you apply that in a real study, it often means you have to account for the fact that an older woman living alone is not actually alone if her daughter provides daily phone check-ins and coordinates medical appointments across two states. Isolated by address, embedded by network. That distinction changes your entire analytical setup.
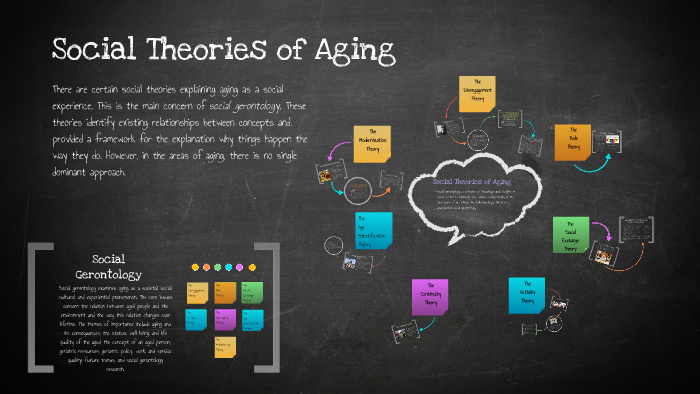
Role theory is another one you will see everywhere. It explains aging as a sequence of role gains and losses, and the standard advice is to recommend new roles for older adults to replace retired ones. That advice is correct and it is also almost useless in practice. I once worked on a program evaluation where every older participant had successfully adopted a volunteer role after retirement, but their health was declining because the volunteer schedule ignored the fact that chronic pain fluctuates day to day. The role substitution framework had no variable for fatigue. Adding a simple self-paced participation metric fixed the evaluation, but only after we threw out the original logic model and built a new one from the participant feedback forms. Age stratification theory treats society as layered by birth cohorts, each cohort carrying different historical experiences into old age. The baby boomers and the Silent Generation age differently not because of genetics but because they grew up under completely different welfare state arrangements, labor markets, and cultural scripts around aging. This is not a subtle point. It is the difference between predicting that older adults will use digital health tools and finding that a large portion of them cannot access portals because their cohort entered the workforce when paper records were the standard and nobody ever trained them for electronic systems. Activity theory and disengagement theory are the ones most people have heard of. Activity theory says older adults stay healthy by maintaining activity levels. Disengagement theory says withdrawal is natural and functional. Both are partially right and both are dangerously incomplete. I have seen both misused in policy documents as justification for either forcing social programs onto reluctant participants or writing off disengaged elders as beyond help. The actual research does not support either conclusion. What it supports is the observation that meaningful engagement looks different across cohorts, personalities, and material circumstances, and that the definition of meaningful is almost never defined by the older adult themselves.
Get the Full Details

Practical application: how to actually use this perspective
If you are designing a study or a program, start by mapping the social structure around aging rather than starting with individual deficits. This means identifying cohort effects, institutional age thresholds, and normative age expectations in the specific context you are working in. An age threshold is something concrete like the eligibility age for a benefit, a mandatory retirement age, or a Medicare enrollment window. These thresholds create structural turning points that no amount of individual motivation can smooth over. When I audit interventions, I look for what they call social models versus clinical models. A social model treats the environment as the primary variable. A clinical model treats the older person as the variable. This sounds abstract until you see the budget line items. Social models fund transportation, community coordination, and intergenerational programming. Clinical models fund screenings, medication management, and fall prevention. Neither is inherently better. They answer different questions. If your question is whether a pill reduces hospital readmissions, use the clinical model. If your question is whether older adults can age in place without moving into assisted living, the clinical model will not give you an answer and you will waste money trying. The method you choose depends on what level of analysis you are willing to work at. Macro studies use census data, policy registers, and cohort comparison designs. Meso studies look at institutions, neighborhoods, and organizations. Micro studies use interviews, ethnography, and diary methods. The best work combines levels. I stopped believing in single-level analyses after watching a municipal aging report completely miss a crisis because it only tracked formal service utilization while informal support networks were silently collapsing under caregiver burnout. The formal numbers looked fine. The informal reality was a series of hospitalizations that never appeared in the data until someone actually visited the homes.
For mixed methods, the practical workaround is to let the qualitative phase define the variables for the quantitative phase rather than the other way around. Too many projects run surveys first and then do interviews to explain surprising results. That is backwards. The surprises are usually the signal. When I run an aging study now, I start with open-ended conversations with older adults and their informal support networks, code the themes, and only then design the survey instrument. It takes longer upfront but it cuts the revision cycle in half because you are measuring what actually exists instead of what the literature assumes exists.
Where the Sociological Perspective Of Aging breaks down
I need to be blunt about the limitations because the literature rarely is. This perspective struggles when applied to populations with severe cognitive impairment. Social construction depends on the ability to narrate and negotiate meaning, and dementia removes that capacity from most people in its later stages. You can still study caregiver experiences and institutional responses, but the older adult's own perspective becomes inaccessible without proxy respondents, and proxy respondents are notoriously unreliable for capturing internal states. The perspective also struggles with rapid technological change. Most of the foundational theories were built in the twentieth century around industrial labor markets, mandatory retirement, and clear generational boundaries. Digital aging does not fit those templates neatly. An eighty-five-year-old who uses telehealth, orders groceries online, and participates in virtual community groups does not match the disengagement or activity frameworks in a straightforward way. The frameworks are not wrong, they are just incomplete for this population. You have to supplement them with digital literacy research and platform studies rather than forcing the data into old bins. There is also a real risk of romanticizing informality. Mutual aid networks and family care are often praised in the sociological literature, and they are valuable, but they are also unpaid labor that disproportionately falls on women and minorities. When you treat informal support as a happy alternative to formal services, you risk justifying the defunding of public programs by pointing to private networks that are already stretched thin. I have seen this happen in budget hearings where a city council member cited a neighborhood mutual aid group as proof that senior meal delivery was unnecessary. The group existed, but it was running on the goodwill of three women in their seventies who were themselves aging and whose capacity was not infinite.

Another limitation is the Western bias in the core theories. Life-course principles, role theory, and age stratification were developed primarily in industrialized, individualistic societies. They do not translate cleanly to collectivist contexts where filial piety, extended household structures, and state-family obligation blur the boundary between informal and formal care. If you are working outside North America or Western Europe, you need to pair these frameworks with local aging literature or you will produce analysis that looks rigorous and is fundamentally wrong. The biggest practical limitation is that sociological analysis does not produce quick policy prescriptions. It produces context. Context is necessary but it is not sufficient for decision makers who need yes or no answers. I have spent more hours than I want to admit explaining to program directors that the reason their intervention failed was not implementation quality but a cohort mismatch between the designers and the participants. The designers were baby boomers who expected digital fluency and individual choice. The participants were silent generation adults who expected face-to-face interaction and prescribed routines. Neither side was wrong. The program just assumed a shared social context that did not exist. The takeaway is not that the Sociological Perspective Of Aging is flawed. It is that it is a lens, not a toolkit. It tells you where to look and what questions to ask. It does not tell you what the answer will be. That part still requires fieldwork, data, and the willingness to be surprised by what older adults actually do rather than what the theory predicts they should do.