What You Actually Need to Know About Plantar Anatomy
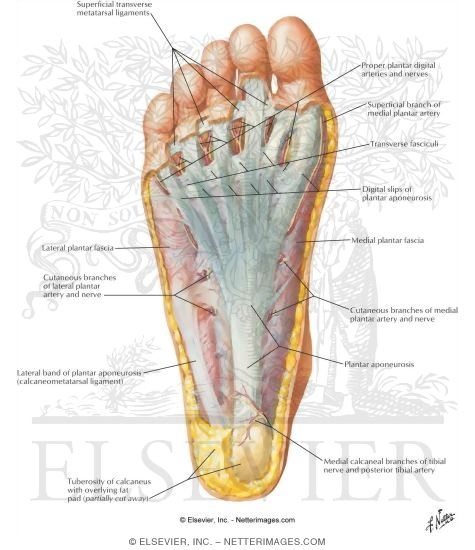
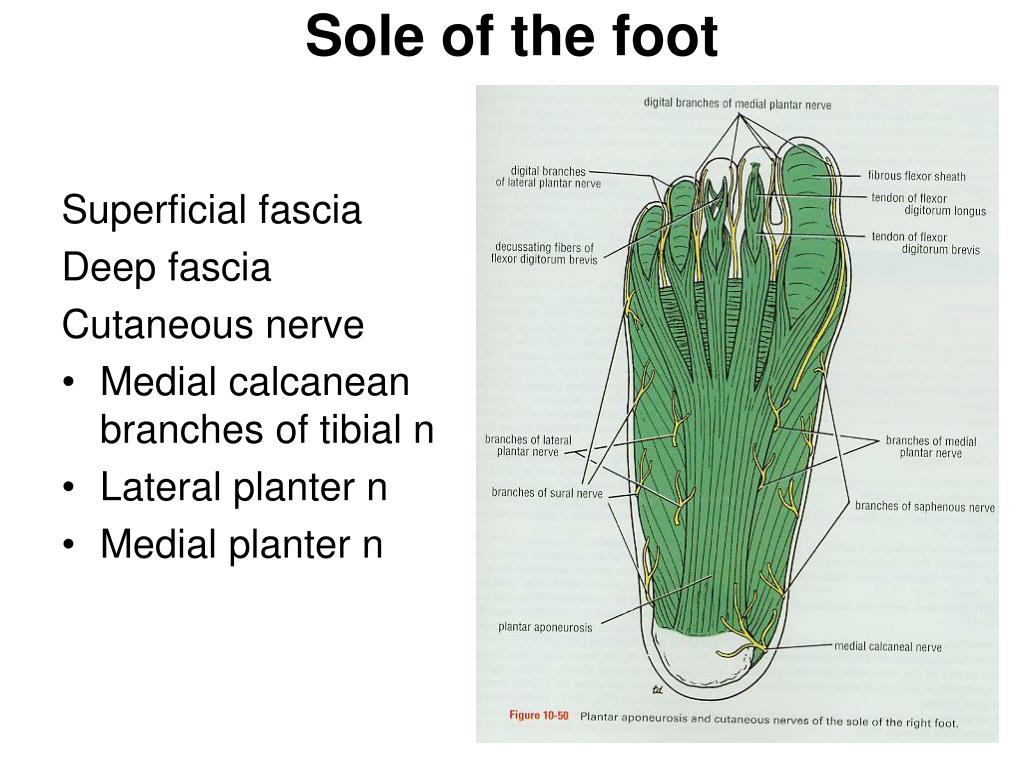
The bottom of your foot is a layered mess of fascia, fat pads, and tendons that most people only notice when something goes wrong. I spent years working with patients who came in complaining about heel pain, and the vast majority of them had no idea what was actually happening underneath their skin. That's the thing about sole of the foot anatomy — it's not just a diagram in a textbook. It's a biomechanical system that takes real punishment every time you walk, run, or stand for more than a few minutes.The plantar fascia is the thick band of connective tissue that runs from your heel bone to the base of your toes. Most people know it as the structure that causes plantar fasciitis when it gets irritated. What they don't always understand is that the fascia isn't a single uniform sheet. It divides into three distinct bands — medial, middle, and lateral — each with different thicknesses and attachments. The medial band is the thickest and bears the most load. The middle band connects to the second through fourth toes and can be a source of forefoot pain if it becomes tight. The lateral band is the thinnest and often overlooked, but it's critical for lateral arch support. Beneath the skin and superficial fascia lies the deep fascia, which includes the plantar aponeurosis. Under that are the fat pads — specifically the calcaneal fat pad at the heel and the metatarsal fat pads in the ball of the foot. These pads are segmented by fibrous septa that keep them in place during weight bearing. When those septa weaken or the fat pad atrophies, especially in older patients, the cushioning effect is gone and you're essentially walking on bone against the ground. I've seen patients with significant fat pad atrophy who got more relief from a simple silicone heel cup than they did from months of stretching and anti-inflammatory medication. The muscles of the sole are organized into four layers. The first layer includes the abductor hallucis, flexor digitorum brevis, and abductor digiti minimi. The second layer houses the lumbricals and quadratus plantae, along with the tendon sheaths of the flexor digitorum longus and flexor hallucis longus. The third layer contains the flexor hallucis brevis, adductor hallucis, and flexor digiti minimi brevis. The deepest fourth layer includes the interossei muscles and the plantar and dorsal aponeuroses. Understanding this layering matters because it dictates how pathologies present and how interventions should be approached.
One thing beginners consistently miss is the relationship between the windlass mechanism and the medial longitudinal arch. When you lift your big toe during push-off, the plantar fascia tightens and the arch raises. This isn't just a curiosity — it's why someone with a stiff big toe joint (hallux rigidus) often develops secondary plantar fascia strain. The mechanism can't function properly, so the fascia absorbs forces it wasn't designed to handle alone. I had a patient who'd been treated for chronic plantar fasciitis for over a year with zero improvement until we addressed the underlying hallux restriction. The fasciitis resolved within weeks once the toe joint started moving again. The vascular supply is worth noting too. The plantar arteries derive primarily from the posterior tibial artery, which splits into the medial and lateral plantar arteries. The medial plantar artery supplies the medial two-thirds of the sole, while the lateral plantar artery supplies the lateral third and gives rise to the plantar arch. In diabetic patients, compromised circulation in these terminal branches can lead to ulceration that patients don't feel until it's severe. This is one reason foot exams in diabetic populations need to include pedal pulse assessment and monofilament testing, not just visual inspection. A practical problem I ran into involved a patient with persistent lateral foot pain that imaging showed no structural cause for. After spending time palpating the peroneal tendons, the cuboid bone, and the bifurcate ligament, I traced the pain to the peroneus brevis insertion at the base of the fifth metatarsal. Standard calf stretches weren't touching it because the issue was at the peroneal tendon itself, aggravated by subtle hindfoot pronation. We switched to eccentric peroneal strengthening and a brief course of relative rest, and the pain dropped significantly within three weeks. The lesson here is that lateral sole pain isn't always lateral plantar fasciitis or peroneal tendonitis in the way textbooks describe it — sometimes it's a junctional issue that needs targeted attention.
Another counter-intuitive point: the plantar fat pads aren't just passive cushions. They actively redistribute pressure through viscoelastic deformation. Under load, the fat pad spreads laterally and flattens, increasing its contact area. This is why barefoot walking on uneven terrain feels different from walking on flat ground — the fat pads respond to surface geometry in real time. Orthotic devices that completely rigidify the sole can actually reduce this natural pressure distribution, which is why some patients feel worse after getting rigid custom orthotics despite the intention to support the arch. A semi-rigid or graded-density device often produces better outcomes because it allows some of the fat pad's natural function to continue. If you're studying this for clinical practice, don't just memorize the muscle origins and insertions. Palpate them. Have a partner walk around while you press along the plantar surface and note where pressure reproduces symptoms. The difference between knowing the anatomy and being able to use it clinically is the ability to connect surface findings to deep structures. A tender spot on the medial heel isn't always the plantar fascia origin — it could be the medial calcaneal nerve, the abductor hallucis, or even referred pain from the L5-S1 nerve roots.
Get the Full Details