The actual mechanics of getting this to work
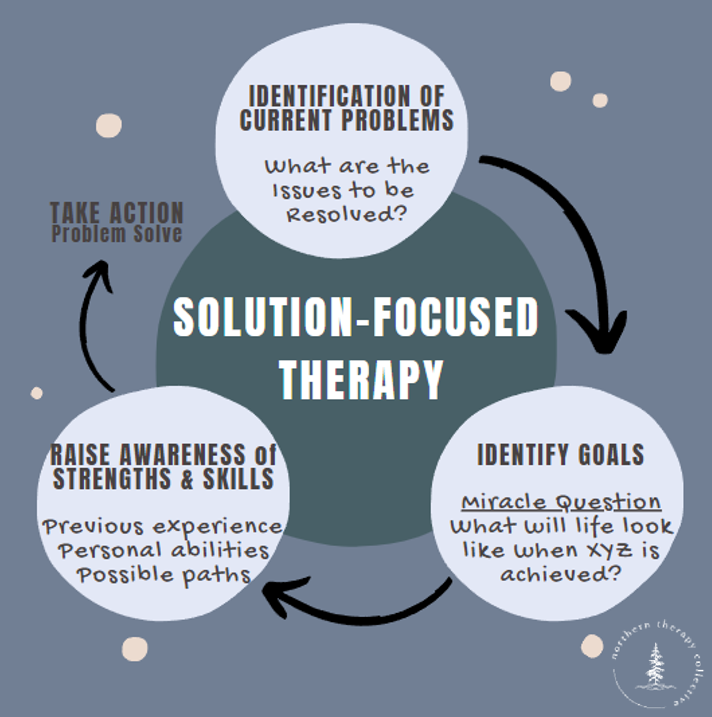
Most people who first encounter Solution Focused Brief Therapy Sfbt walk into it expecting a gentle coaching session where the therapist asks a few questions and magic happens. That is not what it looks like when you are actually doing it. The structure is tighter than most therapists initially realize, and if you let it slide into open-ended exploration, you lose the one thing that makes it fast in the first place. SFBT operates on the premise that spending less time analyzing the problem and more time constructing the solution produces better outcomes faster. The model was built by Steve de Shazer and Insoo Kim Berg at the Brief Family Therapy Center in Milwaukee back in the 1980s. They noticed that some of their clients improved between sessions without much therapeutic intervention, which led them to study what actually worked rather than what theory said should work. The entire framework grew out of that observation. What you get now is a highly pragmatic approach built around a handful of specific questions and techniques. The miracle question is the most well-known tool, but it is also the most misunderstood. It goes like this: imagine that overnight, while you were sleeping, a miracle happened and the problem that brought you here was resolved. How would you know? What would be different?
I run into the same issue every time a new therapist trains with me on this. They ask the miracle question with the expectation that the client will paint a vivid, elaborate picture of their ideal future. About half the time, the client gives you nothing. A shrug, a flat "I don't know," or silence. The trained response is not to push harder or rephrase the question repeatedly until something surfaces. That buries the technique under its own weight. Instead, I drop the frame and move to something smaller. I ask what the person wants instead. I ask for a tiny observable detail. If they say they want things to be better, I ask what a slightly better day would look like on Tuesday morning. You are building from whatever fragment they hand you, not from some imagined breakthrough moment. Scaling questions are the workhorse of this model. You ask someone to rate their current situation on a scale from zero to ten, where zero is the worst it has ever been and ten is the goal state. Then you ask follow-up questions that extract actual behavioral data: What puts you at a four instead of a two? What would a five look like on a concrete day? Who would notice first if you moved up a point? The scaling question works because it turns vague emotional states into measurable, observable increments. That makes progress visible to both therapist and client in a way that narrative therapy alone often struggles to produce in a short timeframe. The coping question is where I see the most avoidable mistakes. The standard form runs like this: given everything you are dealing with, how have you managed to keep going? It sounds simple but requires precision. If a client is in active crisis, this question can backfire by minimizing what they are experiencing. I learned that the hard way with a client who was dealing with acute domestic instability and financial ruin. I asked the coping question during session three and she looked at me like I had lost my mind. She needed validation of the severity first, not a nudge toward her resilience. We paused the SFBT framework entirely and spent two sessions on stabilization before returning to it. The lesson was straightforward: SFBT is not a universal framework. It does not apply cleanly to acute crisis, active psychosis, or severe substance withdrawal. Using it prematurely is one of the quickest ways to damage the therapeutic alliance.
Here is a nuance that rarely gets taught in introductory courses. The preset goals technique is far more powerful than it sounds on paper. At the end of each session, you ask the client to define exactly what change they will notice before the next session. Not what they hope for. What they will specifically observe. This creates a built-in feedback loop that measures whether the intervention is working. Most generalist therapists skip this step because it feels too transactional. It is not transactional. It is accountability wrapped in a question. Clients who engage with it typically show measurable shift within three to five sessions. Clients who never do it tend to drift into longer, less structured therapy with ambiguous outcomes. Another counter-intuitive point that people miss: SFBT therapists are deliberately directive in a way that looks like passivity from the outside. You are not following the client wherever they lead. You are steering them toward resource identification and future orientation with a fairly rigid internal map. When a client starts narrating their trauma history in detail, you acknowledge it briefly and redirect. "That sounds incredibly difficult. When was the last time you felt even slightly in control?" The redirection is not dismissive. It is structural. Spending forty-five minutes analyzing why a problem exists contradicts the entire model. The summary and feedback portion of a session deserves more attention than it gets. Towards the end, you reflect back what you heard, highlighting the client's strengths, exceptions, and desired changes. Then you ask them to tell someone before the next session. This is not an arbitrary ritual. It serves two functions. It reinforces the client's own narrative of competence, and it generates observable behavior between sessions that you can build on next time.
Get the Full Details

If you want to practice this, the core structure of a typical SFBT session runs about twenty to thirty minutes for the focused work portion. The initial assessment can take longer depending on how much history you need to gather to determine whether the model is appropriate. A full introductory training program from an accredited body like the International Solution-Focused Institute typically runs four to six days spread over several weeks. You can find foundational materials and practitioner guides through the Institute's website or the Solution Focused Brief Therapy Association. There are no licensing requirements specific to SFBT itself since it is a modality, not a credential. Any licensed therapist can adopt it with appropriate training. The limitations are worth stating plainly. SFBT underperforms with clients who struggle with abstract thinking or who require extensive processing of past trauma before they can engage with future-oriented questions. It also depends heavily on the client having some baseline cognitive and emotional capacity to identify goals. If someone cannot articulate what they want, the model stalls. In those cases, pairing SFBT techniques with more structured approaches or temporarily shifting to a different modality is the practical move rather than forcing the framework into a shape it was not built for.
How to actually implement Solution Focused Brief Therapy Sfbt in practice
Start by committing to the question set before the session begins. Write down the three questions you plan to use. Most experienced practitioners stick with a consistent core: the miracle question, a scaling question, and the exception-finding question. "Tell me about a time when the problem was less intense or absent. What was different then?" These rotate across sessions. You do not need to invent new ones every time. Track your session count. The "brief" in SFBT is not aspirational. It is a constraint. If you are consistently running past eight to twelve sessions without clear measurable progress indicators, the model is not failing. You are using it incorrectly. Re-examine whether you are accidentally drifting into problem-talk territory. Check whether your scaling questions are producing concrete behavioral markers or vague improvements. Adjust from there. The model rewards discipline. It punishes the urge to explore, interpret, and analyze. The therapists who get good at it are the ones who can sit with silence and resist the pull to fill it with clinical curiosity. That is harder than it sounds. It requires genuine comfort with not knowing where the conversation is going and trusting that the structured questions will produce enough signal on their own.




